Learn the principles of oral medicine, including provisional and definitive diagnosis, and the standardized descriptive framework for accurately documenting oral lesions.
In clinical oral medicine, the ability to accurately observe and interpret findings is the foundation of effective patient care. A clinician's role begins with precise observation—noting exactly what is seen—and moves into interpretation, where those observations are used to form a diagnostic hypothesis. Because many oral conditions can mimic one another, practitioners must rely on a standardized descriptive framework to ensure that clinical records are accurate, reproducible, and useful for longitudinal monitoring.
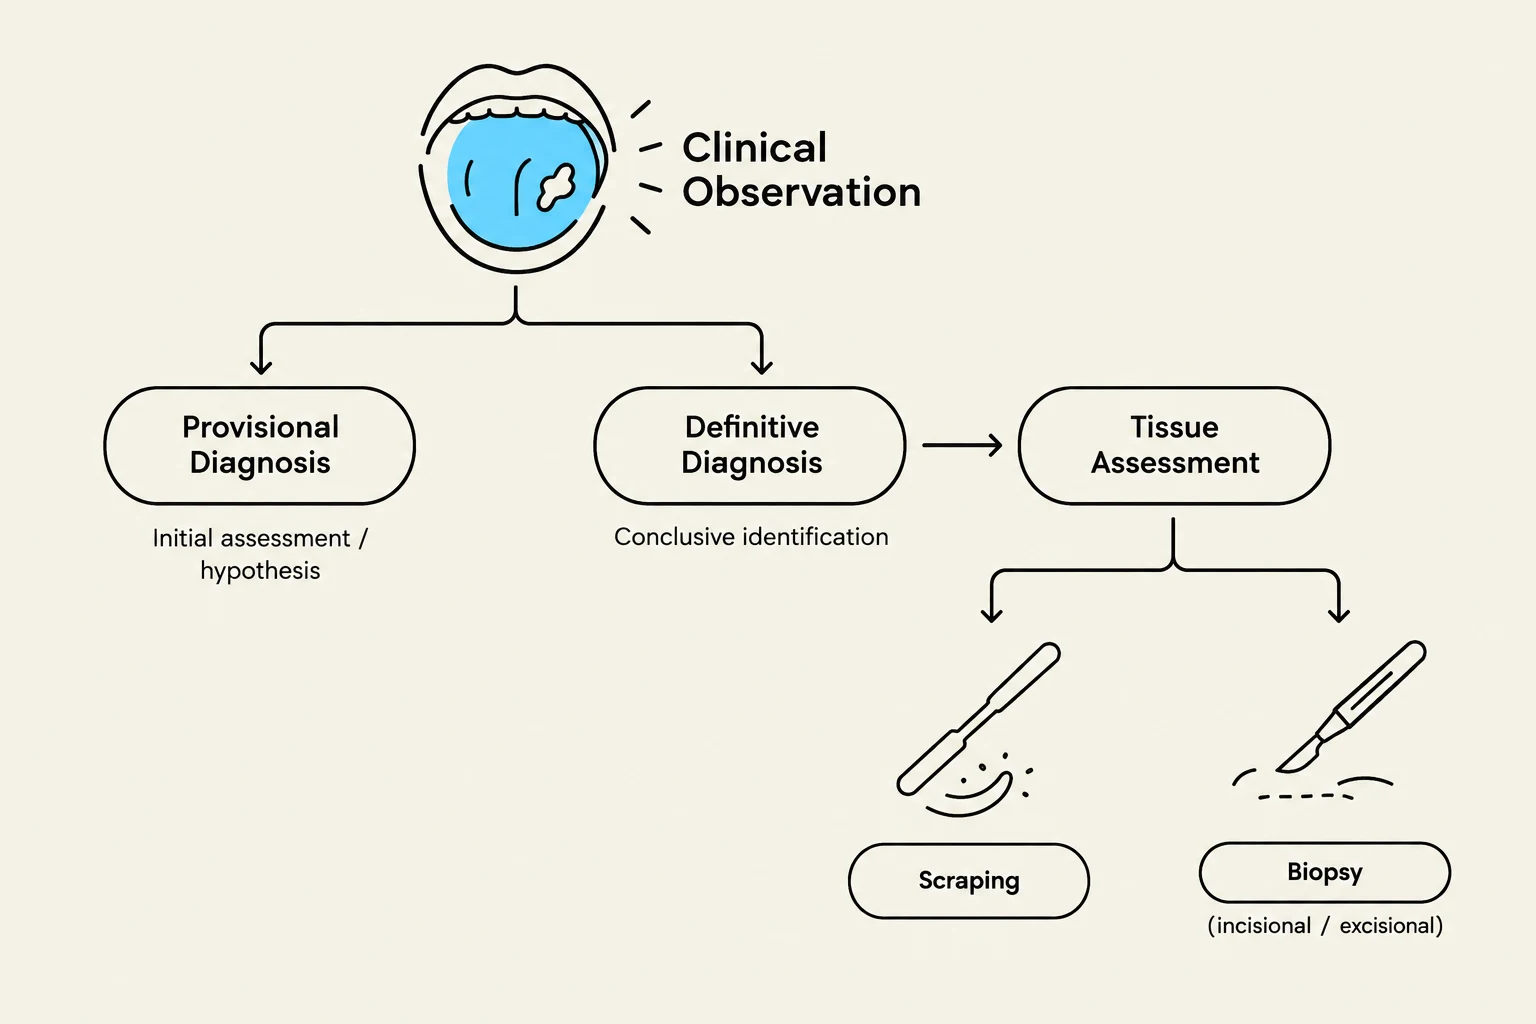
This diagram illustrates the process of clinical observation leading to diagnosis and tissue assessment, including methods like scraping and biopsy.
Diagnostic Classifications
The diagnostic process is a journey from uncertainty to certainty. Clinicians typically navigate through two primary levels of diagnosis:
Provisional Diagnosis
A provisional diagnosis is an initial assessment based on the available clinical evidence and the patient's history. It represents "what the lesion might be" given the current presentation. For example, if a patient presents with a white patch on the cheek caused by chronic rubbing against a sharp tooth, the clinician might propose a provisional diagnosis of frictional keratosis.
Definitive Diagnosis
A definitive diagnosis is the conclusive identification of the condition. This often requires advanced tissue assessment to confirm the exact nature of the cells involved. Methods to reach this stage include:
Scraping: Wiping the tissue to check for specific organisms or surface changes.
Biopsy: Taking a tissue sample (either incisional or excisional) for microscopic examination by a pathologist.
Clinical Pearl: Never allow a negative adjunct test (like a negative biopsy or swab) to override your clinical judgment. If the patient's symptoms, risk factors (like smoking or weight loss), and the physical appearance of the lesion strongly suggest malignancy, you must reassess and potentially repeat the biopsy or refer to a specialist.
Standardized Clinical Description
To communicate effectively with specialists and maintain accurate records, clinicians must use precise morphological language. A complete description should cover the following parameters:
Site, Location, and Distribution
Always specify the exact anatomical sub-site (e.g., left buccal mucosa, hard palate, or floor of the mouth) and the side (left, right, or bilateral).
Bilateralism: It is essential to compare the affected site with the corresponding site on the opposite side. Lesions that are bilateral are frequently non-neoplastic (non-cancerous).
Number and Distribution: Determine if the lesion is solitary (a single lesion), multiple, or diffuse (widely scattered, like sand tossed on a surface). Terms like focal or multifocal are also used to describe how the lesions are clustered.
Dimensions and Shape
Measurements should be recorded in millimeters. For irregular shapes, record the longest dimension and the perpendicular width. If the lesion is three-dimensional and clinically accessible, record the height and depth as well.
The shape can be described as circular, ovoid, linear, or irregular. Additionally, note the base of the lesion: a lesion sitting on a stalk is described as pedunculated.
Morphology: The Vocabulary of Lesions
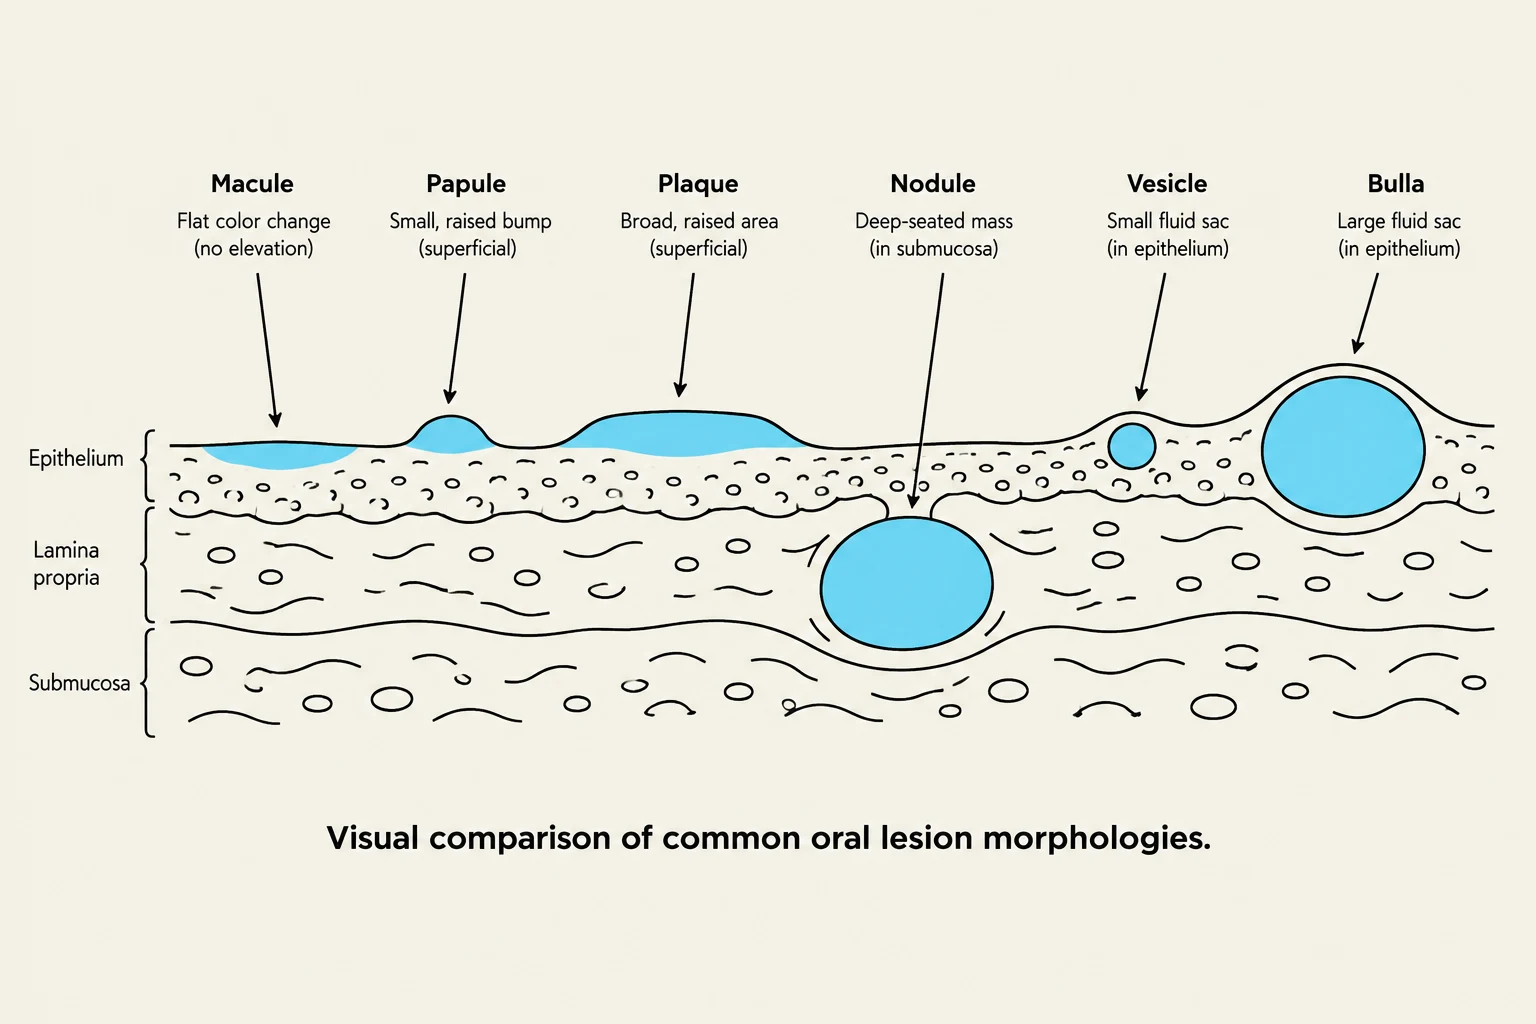
This diagram illustrates and defines various common oral lesion morphologies, including macules, papules, plaques, nodules, vesicles, and bullae, showing their location within the skin layers: epithelium, lamina propria, and submucosa.
Using the correct term for the type of elevation or change is critical for a professional record:
Term
Description
Macule
A flat change in color; no change in tissue elevation.
Patch
A larger version of a macule; a flat, large area of color change.
Papule
A small, solid elevation (a "bump").
Plaque
A broadly raised, relatively flat elevation.
Nodule
A solid elevation that extends deeper into the connective tissue.
Vesicle
A small, fluid-filled sac.
Bulla
A large, fluid-filled sac (a "bigger vesicle").
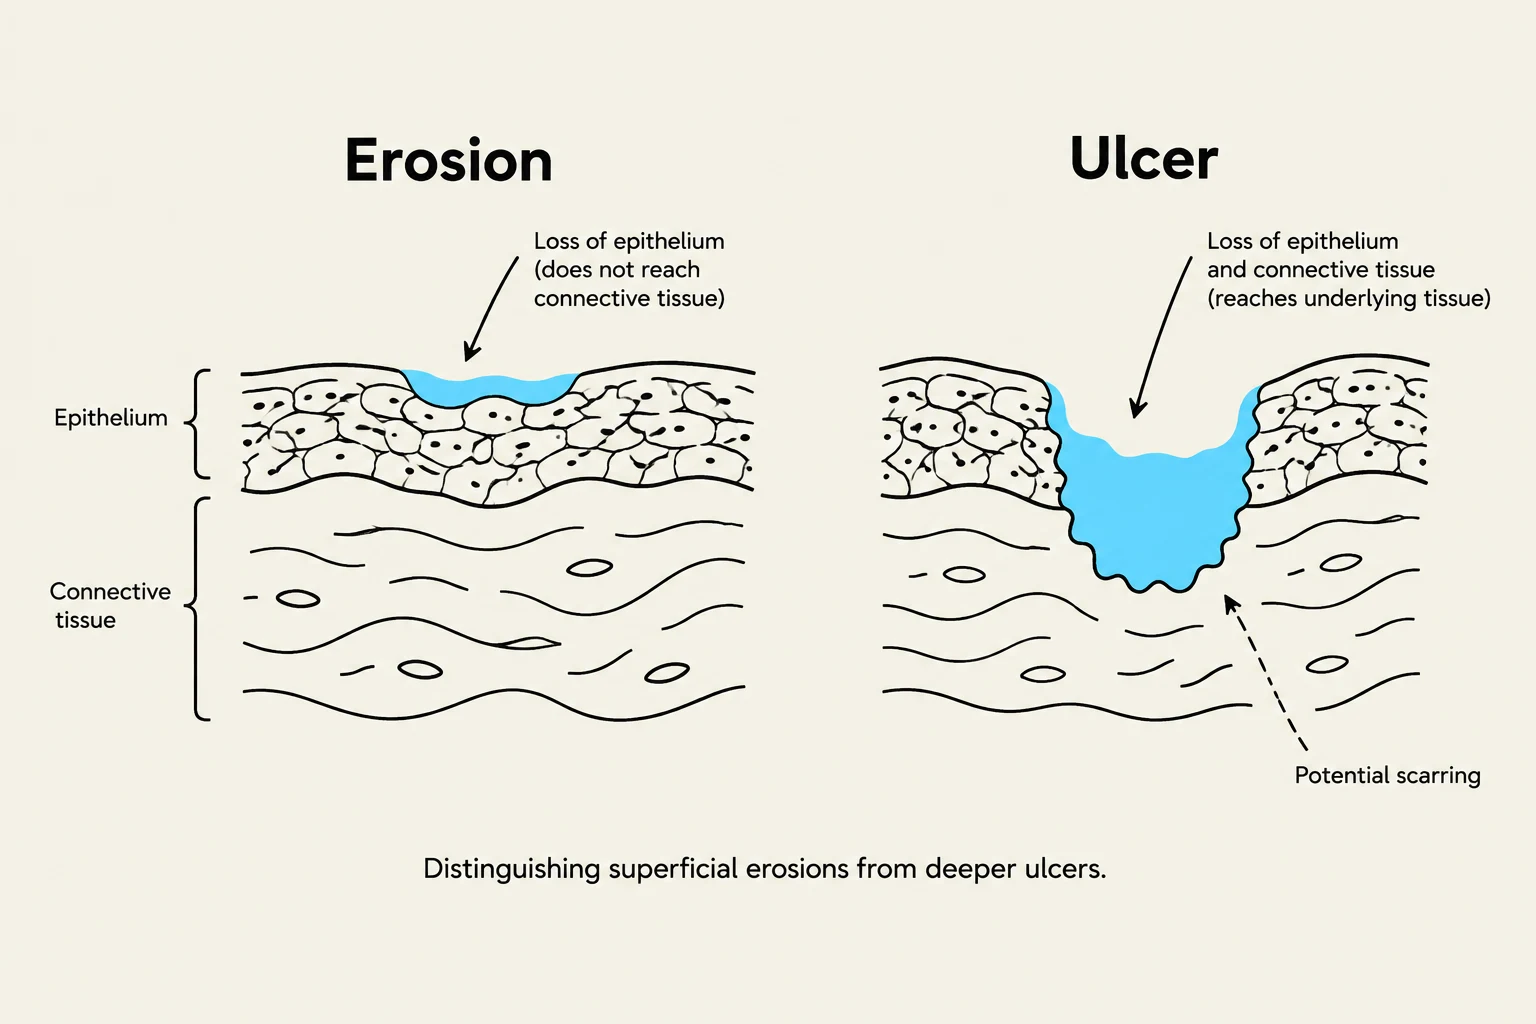
Erosions vs. Ulcers:
An erosion is a superficial loss of the epithelial layer that typically heals without a scar. An ulcer is deeper, extending through the epithelium and potentially into the connective tissue, often leaving a scar.
Color, Surface, and Borders
Color: Note if the lesion is white, red, pigmented (brown/black), or variegated/speckled (a mix of colors, such as red and white). Avoid using "pink" as a descriptor for normal tissue, as not all patients have pink gingiva; instead, use "normal" to indicate the lesion blends into the adjacent tissue.
Surface: Describe the texture—is it smooth, rough, papillary, reticular (lacy), or crusted? If saliva obscures the view, gently blot the area with gauze rather than rubbing it.
Borders: Characterize the margins as either well-defined (clear demarcation) or irregular/poorly defined (blending into surrounding tissue).
This diagram illustrates the difference between an erosion, which is a superficial loss of epithelium, and an ulcer, which is a deeper loss of epithelium and connective tissue that can lead to scarring.
Clinical Context and Monitoring
A diagnosis cannot be made in a vacuum. A complete clinical assessment must include the patient's history and a systemic review.
History and Systemic Involvement
Ask the patient about the duration of the lesion and any changes over time. It is vital to check for extraoral sites; some syndromes present with oral lesions alongside involvement of the palms, genitals, or conjunctiva of the eyes.
Inquire about:
Local trauma: Recent dental work, sharp teeth, or even hot foods (e.g., "pizza burns").
Systemic symptoms: Weight loss, fatigue, or changes in immune status.
Risk factors: Tobacco use, vaping, or medication changes.
Longitudinal Monitoring
When monitoring a lesion over time (e.g., checking a suspicious area in two weeks), consistency is paramount. Use the same probe, the same lighting, and the same clinical technique to ensure that any observed changes are due to the lesion's progression and not due to different measurement methods.
Exam Tip: If you encounter a suspicious, indurated (hardened) lesion on the lateral or ventral surface of the tongue, your immediate priority should be a referral for a biopsy to rule out malignancy.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.