An overview of nutritional status, including assessment methods, common alterations, medication-food interactions, and specialized dietary patterns for various medical, cultural, and religious needs.
Nutrition is the body's intake and use of necessary nutrients to support tissue growth, energy production, and the maintenance of vital body systems. When there is an imbalance between nutrient intake and the body's physiological needs, the result is malnutrition. For healthcare providers, understanding the complex relationship between diet, disease, and medication is essential to promoting optimal health and managing clinical complications.
Cardiopulmonary and Digestive Alterations
Nutritional status is deeply intertwined with various physiological systems. In the cardiopulmonary system, excessive intake of certain substances can lead to significant pathology. For instance, substances secreted from fat cells can contribute to the development of coronary artery disease and atherosclerosis, which may ultimately lead to myocardial infarction.
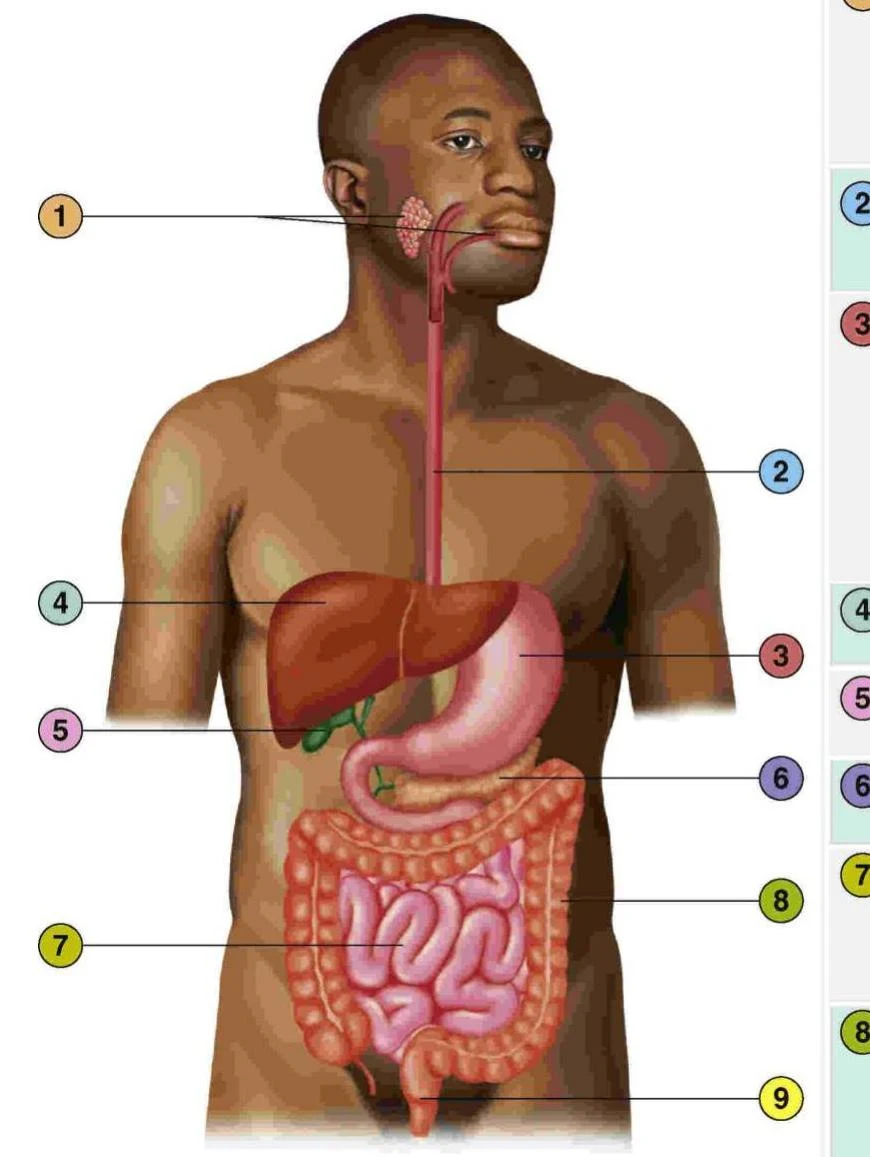
Digestive alterations directly impact how the body processes nutrients. Conditions such as malabsorption—where the intestinal tract cannot adequately absorb nutrients—and inflammatory bowel diseases like Crohn's disease or ulcerative colitis can lead to profound nutritional deficits.
Diagram of the human digestive system, showing the esophagus, stomach, liver, intestines, and salivary glands.Figure 30.2 (Yoost & Crawford, 2023)
Metabolic and Psychological Alterations
Metabolic conditions often dictate strict dietary requirements. Diabetes mellitus occurs when there is insufficient insulin, leading to excessive glucose in the circulatory system. Obesity, defined by a Body Mass Index (BMI) over 30, increases the risk for hyperlipidemia.
Psychological factors also play a critical role in nutritional health. Eating disorders such as Anorexia Nervosa involve limited caloric intake and obsessive behaviors, while Bulimia Nervosa is characterized by cycles of binging and purging.
Nutritional Assessment (Cues)
A thorough nutritional assessment requires a multi-dimensional approach to identify risks before they manifest as severe malnutrition.
Nutrition History and Laboratory Studies
Clinicians should evaluate dietary intake over the last 24 hours, appetite changes, and recent weight fluctuations. Laboratory studies provide objective data to support these findings; key markers include prealbumin, albumin, transferrin, hemoglobin, hematocrit, and Blood Urea Nitrogen (BUN) and creatinine.
Physical Assessment
Physical cues can reveal hidden deficiencies:
Skin and Hair: Thinning, dry, or dull hair; skin that is pale, easily bruised, or shows "tenting" (a sign of decreased skin turgor/dehydration); and the presence of petechiae.
Oral Health: Deep red lips, lesions, cracks in the corners of the mouth, tooth decay, or a tongue with white irregular areas.
Body Composition: Height, weight, and BMI, as well as waist circumference.
Elimination Patterns
Assessment of the abdomen, including bowel sounds and the character of stools (e.g., constipation or diarrhea), is vital for understanding nutrient absorption and gastrointestinal health.
Malnutrition in Older Adults
Older adults are at a heightened risk for malnutrition due to multifactorial physiological and social changes.
Physiological declines include reduced thirst, decreased kidney function, slower digestion, and a decline in the immune system. Furthermore, sensory changes—such as reduced taste and smell—and physical limitations like poor dental health or reduced hand function can significantly decrease food and fluid intake.
Dysphagia and Aspiration Risk
Dysphagia, or difficulty swallowing, is a common complication following a stroke (CVA) or other neurological injuries. This condition poses a severe risk for aspiration, where food or fluids are inhaled into the lungs and bronchi, potentially leading to pneumonia, respiratory distress, or death.
Management often involves a multidisciplinary team:
Speech Therapists: Conduct swallow studies to assess safety.
Registered Dietitians: Determine appropriate food textures and hydration methods.
Physicians: Decide if nonoral routes are necessary, such as nasogastric (NG) tubes for short-term therapy or Total Parenteral Nutrition (TPN) for long-term needs.
This chart illustrates different levels of liquid thickness, from slightly thick to extremely thick, with corresponding descriptions of their consistency and how they are consumed.
Medication-Food Interactions
Medications can significantly alter how the body processes nutrients or how nutrients affect the drug's efficacy. Clinicians must perform regular medication reviews.
Avoid grapefruit juice and St. John's wort; take with evening meals.
Antihypertensives
Avoid licorice, high-potassium salt substitutes, and grapefruit juice.
Antihistamines
Avoid alcohol and grapefruit juice.
Specialized Dietary Patterns and Interventions
Dietary interventions must be tailored to the patient's medical, religious, or cultural needs.
Cultural and Religious Patterns
Kosher (Jewish): Prohibits pork, shellfish, and the combination of meat and dairy.
Islamic: Prohibits alcohol, pork, and caffeine.
Mormon: Avoids alcohol, tobacco, and caffeine.
Catholic: Includes fasting and no meat consumption on Fridays during Lent.
Vegetarianism
Variations include Lacto-ovo vegetarian (includes milk and eggs) and Vegan (no animal products consumed).
Medical Diets
Consistency-based: Clear liquids (e.g., broth, apple juice), full liquids (e.g., yogurt, juices), pureed (blended foods), and mechanical soft (e.g., scrambled eggs).
Disease-specific:
Diabetic: Focuses on carbohydrate management.
Cardiac: Low salt and low cholesterol.
Renal: Restricts potassium, sodium, protein, and phosphorus.
Nutritional Support Routes
When oral intake is impossible or insufficient, alternative routes are used:
Enteral (Intestinal): Includes Nasogastric (NG) tubes for short-term use, or PEG/J tubes for long-term use.
Parenteral (Intravenous): Total Parenteral Nutrition (TPN) is administered into a large central vein (e.g., PICC or CVC) when the GI tract is non-functional.
💡 Clinical Tip: Assisting with Feeding
When assisting a patient with meals, always ensure the Head of the Bed (HOB) is elevated to 30–45 degrees to prevent aspiration. Provide oral care (including dentures) before and after meals, and carefully document the percentage of the meal consumed and any signs of choking or aspiration.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.