An overview of nursing quality and patient safety, including definitions, QSEN competencies, error management (adverse and sentinel events), root cause analysis, just culture, communication strategies, and national patient safety goals.
In the complex environment of modern healthcare, the dual pillars of Safety and Quality form the foundation of nursing practice. While these terms are often used interchangeably, they represent distinct concepts that work together to ensure optimal patient outcomes. Safety focuses on the prevention of harm and the minimization of errors, while quality addresses the excellence, efficiency, and effectiveness of the care provided. For nurses, mastering these concepts is not just a professional requirement but a vital component of clinical competence and patient advocacy.
This diagram illustrates the relationship between safety and quality in nursing practice, highlighting key components of each and their contribution to optimal patient outcomes.
Defining Safety and Quality
To improve care, we must first define what we are aiming to achieve.
Safety is defined as the ability to keep both patients and staff free from harm by minimizing errors through established protocols, memory checklists, and advanced technology, such as bar-code medication administration. It requires nurses to possess the knowledge to assess their environment, the skills to utilize safety tools, and the professional attitude to recognize human limitations.
Quality is a broader concept that refers to the degree of excellence in care. It is often viewed through multiple lenses:
Patient Satisfaction: How the patient perceives the care received.
Evidence-Based Practice: Using the best current research to guide clinical decisions.
Resource Efficiency: Minimizing the waste of time, cost, and supplies.
Exam Tip: When distinguishing between the two, remember that Safety is about the absence of harm (preventing errors), whereas Quality is about the presence of excellence (achieving optimal outcomes).
The QSEN Competencies
The Quality and Safety Education for Nurses (QSEN) initiative provides a framework of essential competencies that every nurse must integrate into their practice. These six pillars guide how care should be delivered:
Safe: Practicing within your legal scope of practice and demonstrating appropriate knowledge of the patient's health status.
Effective: Addressing the most critical health concerns while avoiding both the underuse and overuse of healthcare services.
Timely: Reducing waiting times to prevent harmful delays in care delivery.
Patient-Centered: Responding to the individual preferences, needs, and values of the patient, treating them as a full partner in their care.
Efficient: Using resources—including time, money, and supplies—in a way that minimizes waste.
Equitable: Ensuring that the quality of care provided does not vary based on gender, ethnicity, geographic location, or socioeconomic status.
Managing Errors: Adverse and Sentinel Events
Despite rigorous protocols, errors can occur due to human fallibility or poor system design. It is critical to categorize these errors to determine the appropriate response.
An adverse event is a variation in the standard of care that may or may not result in harm. However, a sentinel event is a much more serious category. A sentinel event is a serious adverse event that results in an unavoidable death or significant permanent harm to a patient. Examples include wrong-side surgery, patient suicide, or severe postoperative complications.
Root Cause Analysis (RCA) and the "5 Whys"
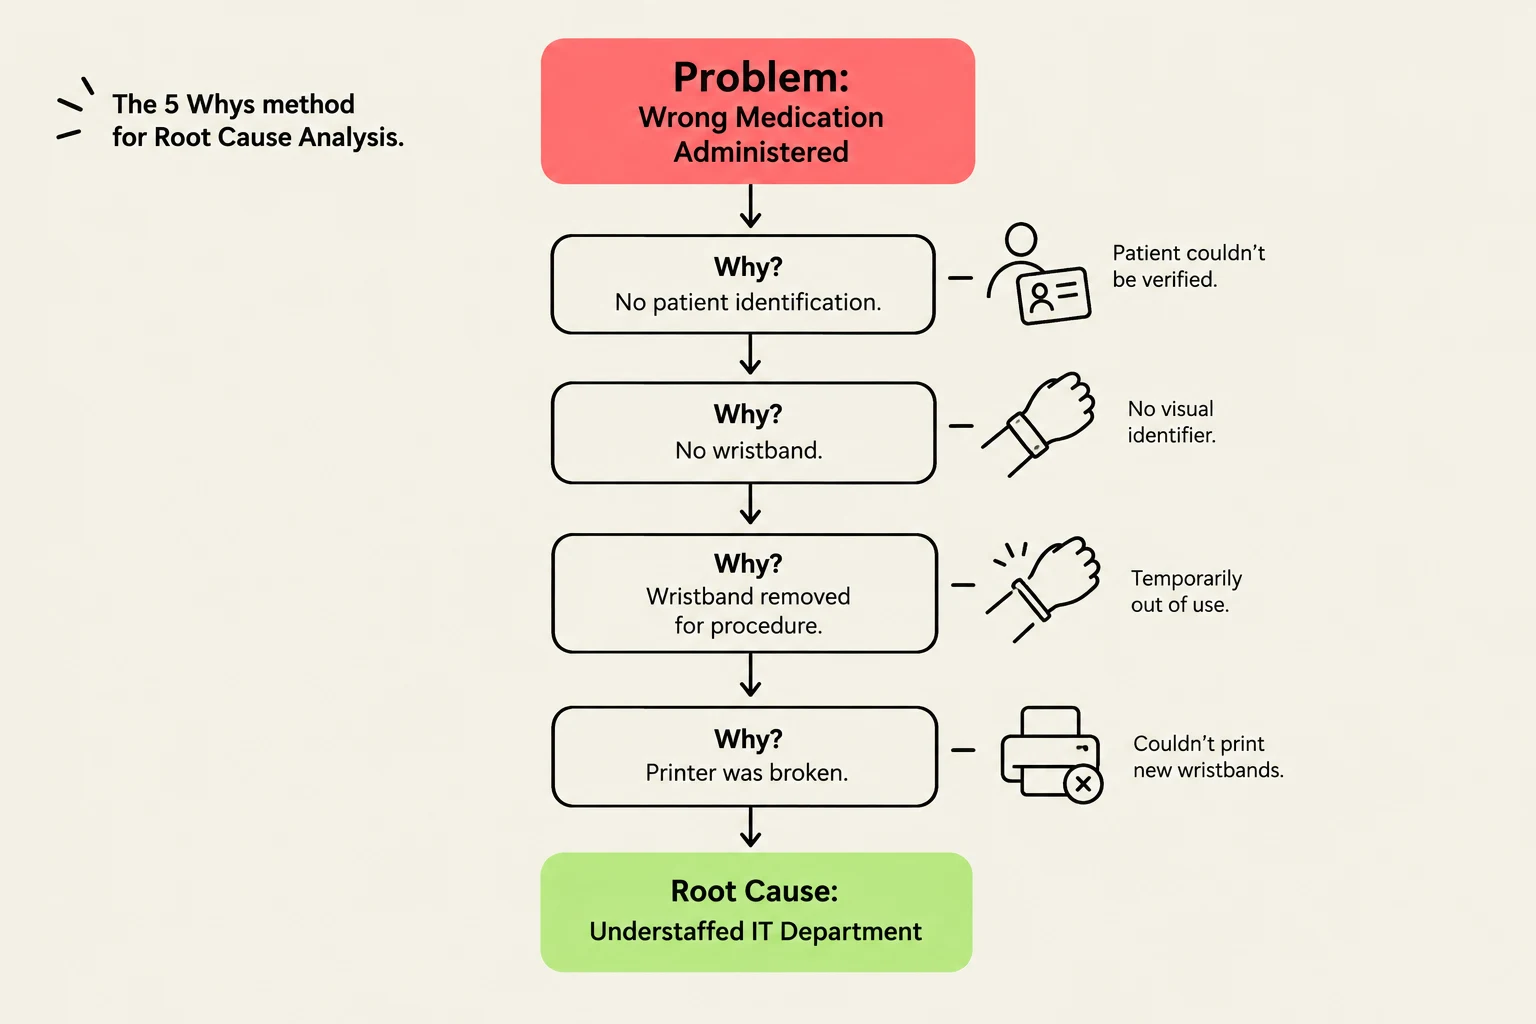
The 5 Whys method for Root Cause Analysis, illustrating a problem with wrong medication administration due to issues with patient identification and wristbands, ultimately identifying an understaffed IT department as the root cause.
When a sentinel event occurs, accredited organizations are required to perform a Root Cause Analysis (RCA). The goal of an RCA is not to assign individual blame, but to identify the underlying systemic factors that allowed the error to happen. An RCA seeks to answer three fundamental questions:
What happened?
Why did it happen?
What can be done to prevent it from happening again?
A common technique used during an RCA is the "5 Whys" method. This involves repeatedly asking "why" to peel back the layers of a problem until the actual causal factor is found.
Example of the 5 Whys:
Problem: A patient received the wrong medication.
Why? The nurse did not complete patient identification.
Why? The patient did not have a wristband.
Why? The wristband was removed for a procedure and not replaced.
Why? The printer for the wristbands was broken.
Why? IT support staff had been reduced and were overworked.
By identifying that the "overworked IT staff" was the root cause, the organization can fix the system (e.g., hiring more IT staff) rather than simply reprimanding the nurse.
Fostering a Just Culture
To make error reporting effective, healthcare systems must move away from a culture of fear. A Just Culture is a blame-free environment that encourages nurses to disclose clinical errors and potential "near-misses" without fear of punitive action.
In a Just Culture, the focus shifts from "Who did this?" to "What went wrong with our system?" This transparency allows the entire healthcare team to learn from mistakes, promoting collective accountability and continuous improvement.
Communication Strategies for Error Prevention
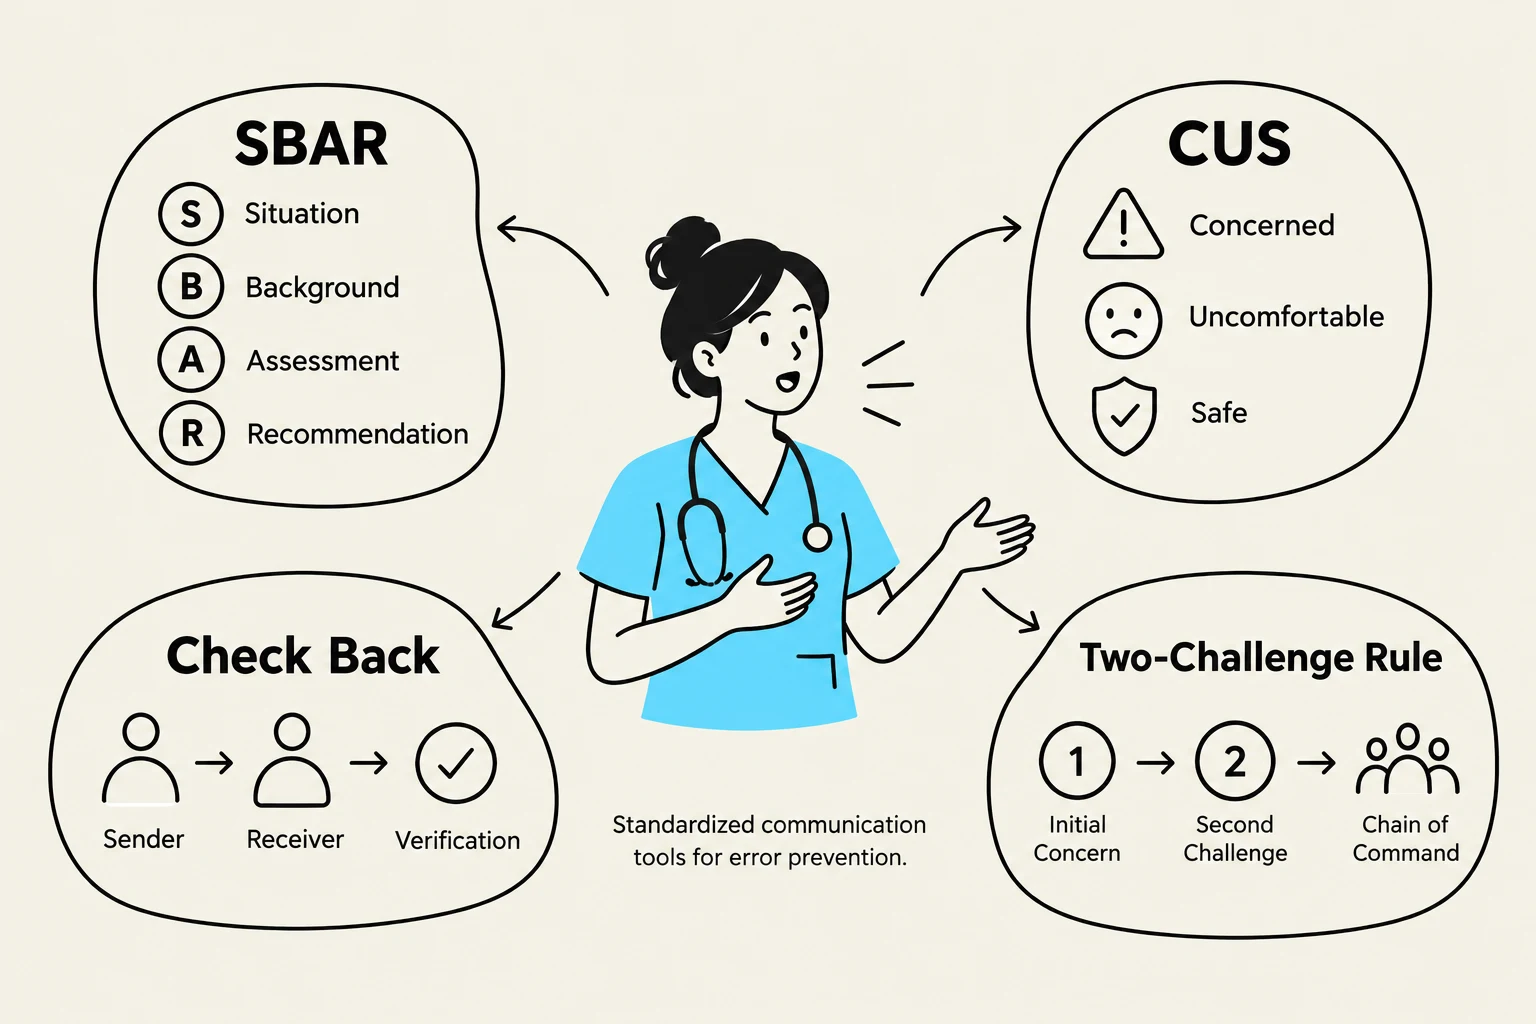
This illustration depicts standardized communication tools for error prevention in healthcare, including SBAR, CUS, Check Back, and the Two-Challenge Rule.
Communication breakdowns are a leading cause of medical errors. To mitigate this, several standardized tools and strategies are used in interprofessional teams:
SBAR: A structured way to communicate information: Situation, Background, Assessment, and Recommendation.
TeamSTEPPS: A systematic approach (Strategies and Tools to Enhance Performance and Patient Safety) designed to improve interprofessional team performance.
CUS Words: A way to escalate a concern using specific keywords: "I am Concerned; I am Uncomfortable; this is not Safe".
Check Backs: A technique where a receiver restates the information provided by the sender to verify understanding.
Call Outs: Shouting out critical information (like a sudden change in vital signs) so the entire team hears it simultaneously.
Two-Challenge Rule: If a nurse identifies a safety concern, they should state it at least twice. If the concern is ignored, they must follow the chain of command to ensure the issue is addressed.
National Patient Safety Goals (NPSG) 2025
Regulatory bodies and organizations like The Joint Commission establish specific goals to address high-risk issues in healthcare. Key focus areas for the 2025 goals include:
Correct Patient Identification: Always use at least two identifiers (e.g., name and date of birth) to ensure the right patient receives the right treatment.
Safe Medication Use: Taking extra care with high-alert medications, such as anticoagulants (blood thinners), which are more likely to cause harm due to complex dosing.
Infection Prevention: Prioritizing hand hygiene to reduce healthcare-associated infections (HAIs).
Fall Prevention: Identifying high-risk patients (e.g., those on diuretics or sedatives) and taking proactive measures to prevent injury.
Pressure Ulcer Prevention: Performing frequent skin assessments to prevent or halt the progression of bed sores.
Clinical Application: If you are caring for an elderly patient who is taking a diuretic and using a walker, your highest priority for safety is fall prevention.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.