This content discusses quality of care, patient safety, and adverse events within the health care system, including definitions of harmful incidents, near misses, and no-harm incidents. It also covers the Patient Restraints Minimization Act, abuse prevention, medication error prevention, and the importance of a patient
In the modern healthcare landscape, the concepts of "quality of care" and "patient safety" are inextricably linked. Quality of care refers to how well healthcare services are provided to patients, aiming to deliver the best and safest possible care every time they interact with the system. Patient safety, as defined by the Canadian Patient Safety Institute (CPSI), is the active pursuit of reducing and mitigating unsafe acts within the healthcare system while utilizing best practices to achieve optimal patient outcomes. For nursing professionals, understanding the intersection of these two concepts is fundamental to providing competent, ethical, and safe care.
Understanding Adverse Events and Risks
An Adverse Event (AE) is defined as an event or circumstance that could have resulted in, or did result in, unnecessary harm to a patient. In Canadian hospitals, statistics show that approximately 1 in 17 hospital stays involves at least one harmful event. These events generally fall into four categories:
Healthcare and medications: Such as medication errors or pressure ulcers.
Infections: Such as post-operative infections.
Procedure-related: Such as bleeding following a surgical procedure.
Patient accidents: Such as falls.
It is vital to distinguish between different types of incidents to improve system responses:
Harmful incident: An event that results in actual harm.
Near Miss: An event that could have resulted in harm but did not.
No-harm incident: An event that occurred but resulted in no harm to the patient.
The impact of these events extends beyond the patient. While patients face direct costs and increased hospital stays (averaging an additional 5 days), healthcare workers often experience significant psychological distress, including shame, guilt, and absenteeism.
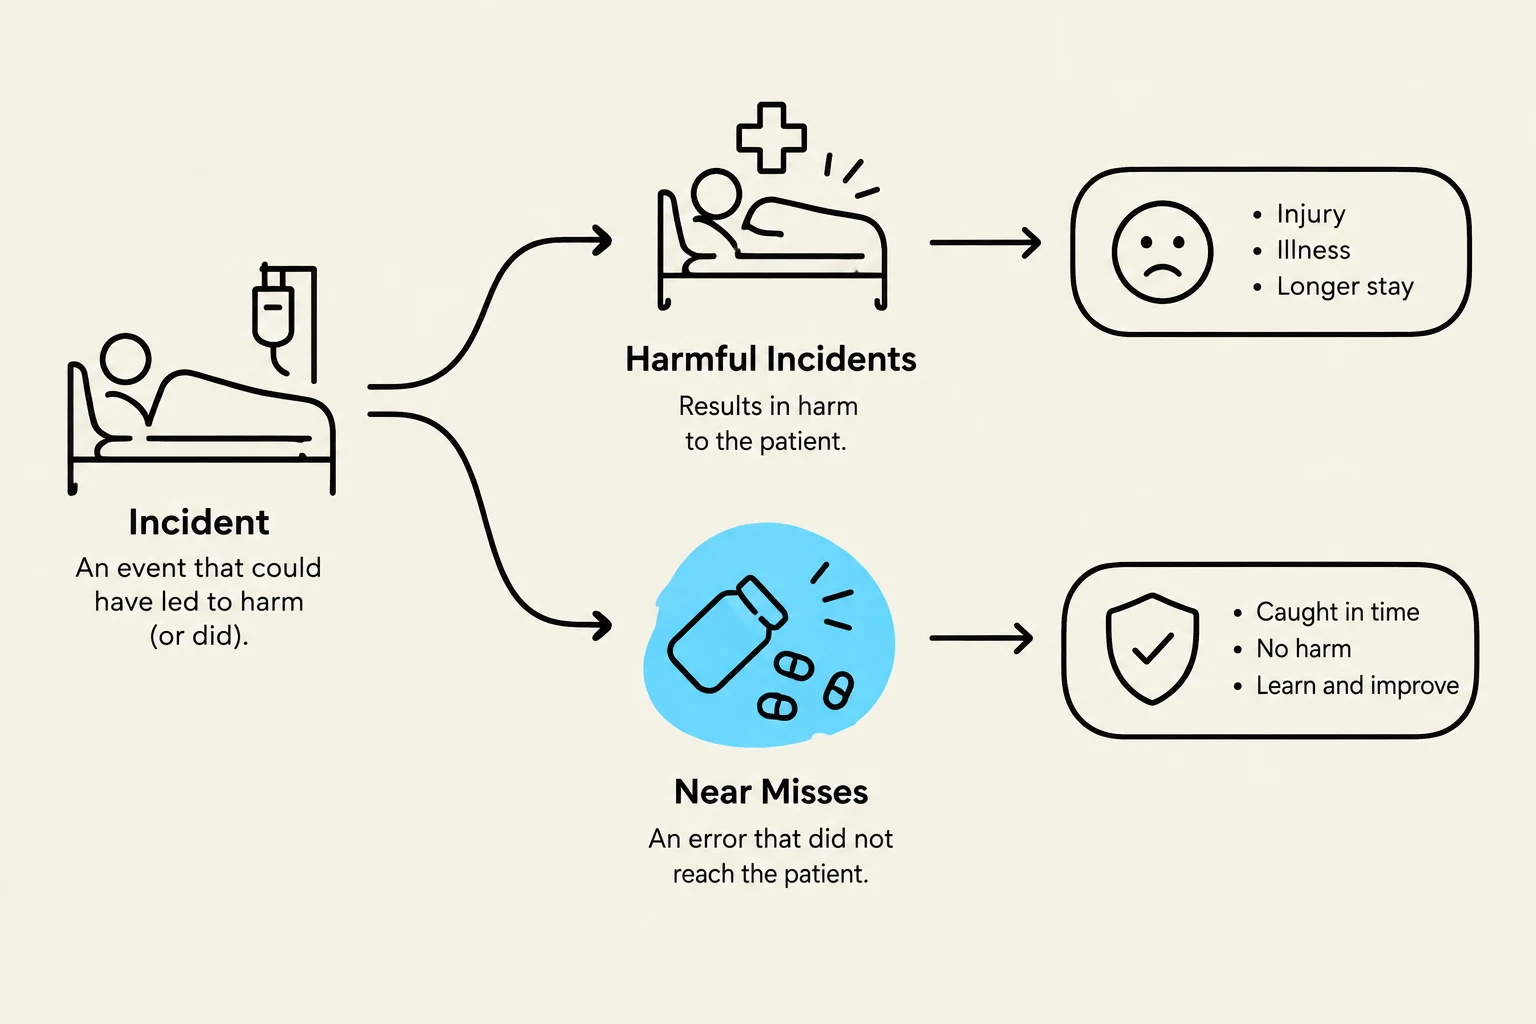
This diagram illustrates the difference between harmful incidents and near misses in a patient care context. Harmful incidents result in patient harm, leading to injury, illness, or longer stays. Near misses, on the other hand, are errors that do not reach the patient, allowing for timely intervention, no harm, and opportunities for learning and improvement.
Exam Tip: When reviewing case studies, always categorize the incident correctly. If a nurse catches a wrong dose before administration, it is a Near Miss. If the dose is given but the patient is fine, it is a No-harm incident. If the patient suffers a reaction, it is a Harmful incident.
Factors Affecting Nursing Safety
Safety is not merely the result of individual performance; it is influenced by complex systems. Nurses face specific risks that can be categorized into environmental, systemic, and human factors.
Systemic and Environmental Risks:
Equipment design flaws: Problems with electronic blood pressure monitors, IV pumps, or mechanical lifts can lead to errors.
Complex systems: The intricate nature of modern healthcare can lead to confusion and errors.
Occupational Health and Safety: Nurses must adhere to policies regarding WHMIS, fire and evacuation plans, and infection prevention (PPE) to ensure their own safety while caring for others.
Human and Communication Factors:
Ineffective Communication: Poor handovers, illegible handwriting, and interruptions are major contributors to error.
Teamwork and Hierarchy: A culture where staff feel unable to challenge superiors due to "professional courtesy" or a rigid hierarchy can suppress vital safety information.
Individual Factors: Fatigue and high workload significantly increase the risk of mistakes.
Professional Standards and Safety Competencies
To mitigate these risks, nursing practice is guided by rigorous standards and competencies.
CNO Standards and Guidelines
The College of Nurses of Ontario (CNO) provides the framework for safe practice through several pillars:
Code of Conduct: This includes six principles, such as respecting client dignity, providing inclusive and culturally safe care, and acting with integrity.
Scope of Practice: Defined by Authority, Competence, and Context.
Quality Assurance (QA): Ensures ongoing competence through knowledge and practice assessments.
CPSI Safety Competencies
The Canadian Patient Safety Institute identifies six core domains that healthcare professionals must master to ensure a robust safety culture:
Patient safety culture.
Teamwork.
Communication.
Safety, Risk, and Quality Improvement.
Optimize Human and System Factors.
Recognize, Respond to, and Disclose Patient Safety Incidents.
Client Abuse Prevention
A critical component of nursing safety is the prevention of client abuse. The CNO defines client abuse as the misuse of power or the betrayal of trust, respect, or intimacy within the therapeutic relationship. Abuse can manifest in several forms: physical, verbal, emotional, sexual, financial, or through neglect.
Nurses have a professional responsibility to prevent and report abuse. The CNO emphasizes the principle of "One is One Too Many" to underscore that even a single instance of abuse is unacceptable.
Managing Restraints and Alternatives
Restraints are measures used to restrict a client's movement or control their behavior. In Ontario, the Patient Restraints Minimization Act, 2001 dictates that restraints must be used as a last resort and represent the least restraint possible.
Types and Risks
Restraints can be Physical, Chemical, or Environmental. While they may be used for protection (preventing self-harm), maintaining treatment (preventing removal of a breathing tube), or enhancing freedom in specific settings, they carry significant risks:
Physical risks: Skin breakdown, incontinence, constipation, loss of bone mass, and muscle atrophy.
Psychological risks: Confusion, agitation, depression, and loss of dignity.
Alternatives to Restraints
Nurses should prioritize non-restrictive interventions to manage patient behavior:
For falls/unsteadiness: Use lower beds, floor mattresses, or regular toileting.
For cognitive impairment: Use diversion activities, soothing music, or alarm devices.
For agitation/tube pulling: Use redirection, gentle touch, or camouflaging tubing.
Clinical Practice Note: When using restraints, the CNO requires nurses to actively involve the patient and their family, obtain consent, and continuously reassess the need for the intervention. Documentation must include the assessment, the intervention used, and the ongoing evaluation.
Strategies for Improvement: The "Just Culture"
To decrease adverse events, healthcare organizations are moving toward a "Just Culture". This approach focuses on understanding the systemic causes of errors rather than simply assigning individual blame. Strategies to improve safety include:
Interprofessional Communication: Utilizing structured tools like SBAR (Situation, Background, Assessment, Recommendation) to ensure clear handovers.
Technology: Using electronic monitoring and improved device design.
Reporting: Encouraging the reporting of both adverse events and near misses without fear of retribution.
Leadership: Implementing organizational protocols and continuous education.
By integrating these competencies and adhering to professional standards, nurses contribute to a safer healthcare environment for both patients and themselves.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.