This guide covers the essential principles and practices of safe medication administration in nursing, including legal responsibilities, medication orders, routes of administration, safety checks, error prevention, and documentation.
Medication administration is a core nursing function that requires a high level of clinical knowledge, precision, and accountability. It is not merely the act of handing a pill to a patient; rather, it is a complex process that involves the application of the nursing process—assessment, diagnosis, planning, implementation, and evaluation—to ensure that every dose is safe, effective, and appropriate for the individual. Because nurses are legally responsible for every drug they administer, they must act as the final check in the healthcare system to prevent errors and protect patient safety.
Legal Framework and Professional Responsibility
The practice of medication administration is governed by a strict hierarchy of regulatory bodies and laws. At the federal level, the Food and Drug Administration (FDA) regulates the safety and effectiveness of drugs sold in the United States. Meanwhile, the Drug Enforcement Administration (DEA) oversees the handling of all controlled substances to prevent abuse.
At the professional level, the Nursing Practice Act (such as the Massachusetts Nursing Practice Act) defines the scope of practice for nurses. For a Registered Nurse (RN), this includes the ultimate responsibility for both direct and indirect patient care.
Nursing Accountability Tip: You have the legal right and the professional obligation to question a medication order if you suspect an error. Furthermore, you have the right to refuse to administer any medication that you believe may harm a patient based on your professional knowledge.
Medication Orders and Reconciliation
A medication order (or prescription) is the provider's communication of therapy. It is a fundamental rule in nursing: no order means no medication administration. Orders may be entered via Computer Provider Order-Entry (CPOE), paper, or verbal orders (though students should never accept verbal orders).
Every valid order must contain seven essential parts:
Patient name and a second identifier
Date and time the order was written
Name of the drug
Dosage
Route of administration
Frequency of administration
Prescriber's signature
Orders can be categorized by their timing: Standing/Routine (carried out until cancelled), PRN (as needed), Single/One-time, or STAT (immediate).
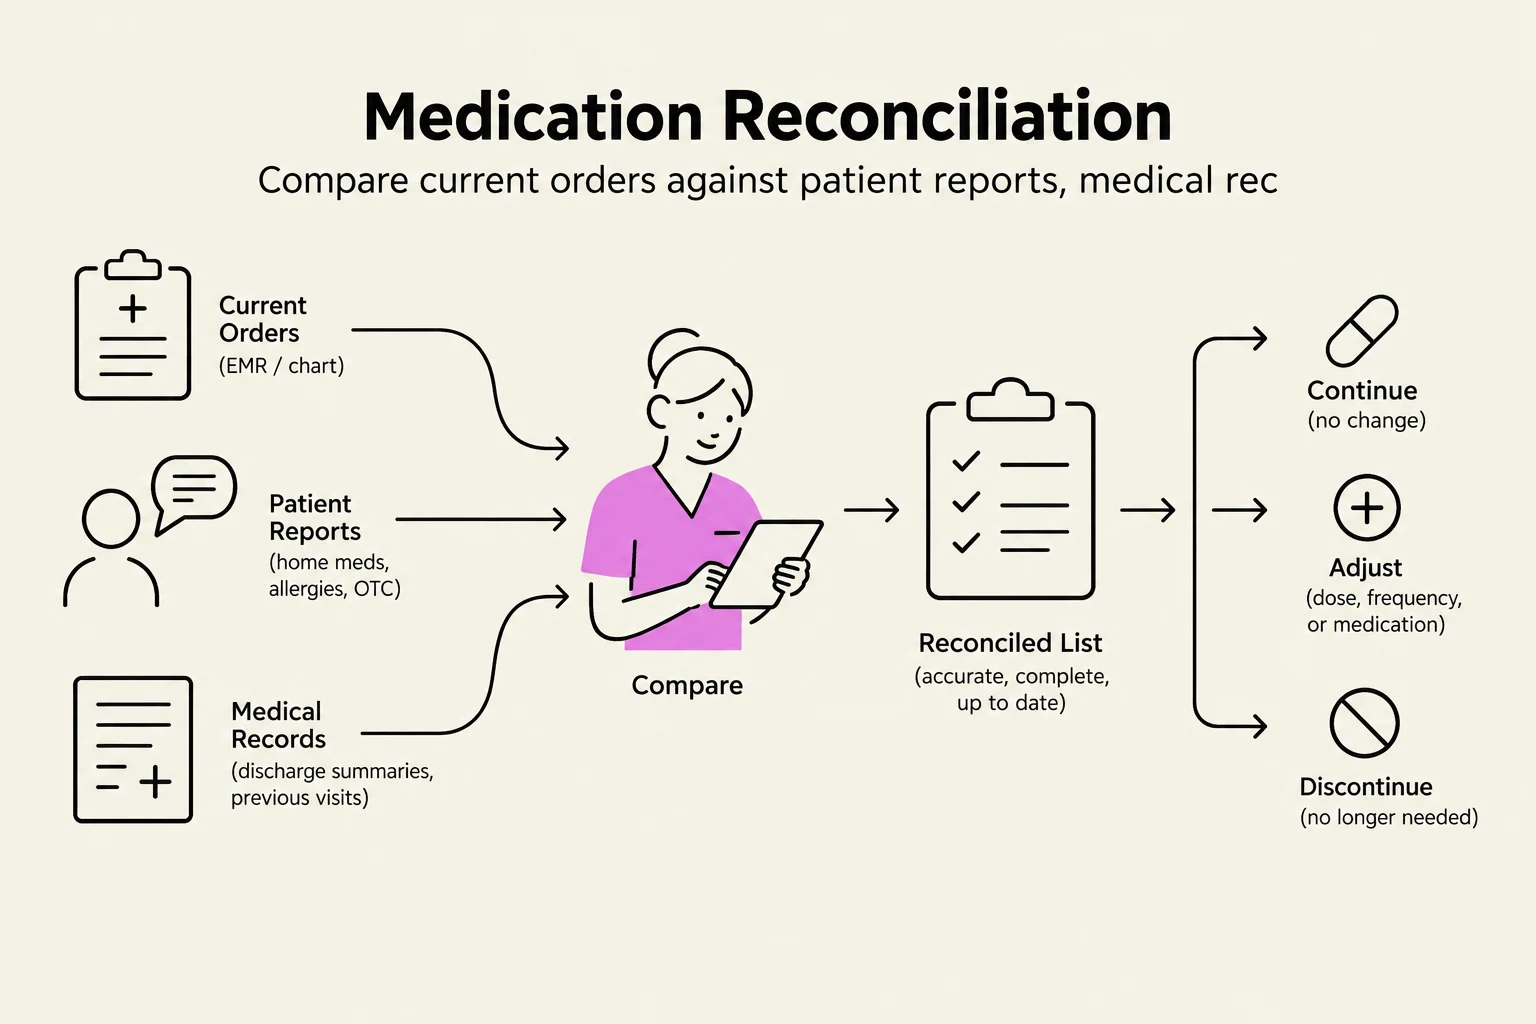
To prevent errors during transitions of care—such as admission, transfer, or discharge—nurses perform Medication Reconciliation. This involves comparing current orders against the patient's reported medications, medical records, and previous prescriptions to reduce the risk of duplication, omission, or dangerous drug interactions.
This diagram illustrates the process of medication reconciliation, which involves comparing current medication orders with patient reports and medical records to ensure accuracy and completeness.
Routes of Administration
The route of administration is determined by the drug's preparation and the desired onset of action. Understanding these routes is vital for selecting the correct equipment and technique.
Enteral (Oral) Routes
The oral route is the most common, convenient, and comfortable, but it generally has a slower onset of action compared to other routes.
Oral (PO): Swallowing tablets, capsules, or liquids.
Sublingual: Placing the drug under the tongue.
Buccal: Placing the drug between the tongue and the cheek.
Enteral: Administering via a feeding tube.
Parenteral (Injection) Routes
Parenteral administration refers to routes "outside the intestines".
Intradermal (ID): Administered into the dermis at a 5–15 degree angle; used for sensitivity tests.
Subcutaneous (SubQ): Administered into the adipose tissue at a 45–90 degree angle.
Intramuscular (IM): Delivered into large muscles at a 90-degree angle for faster absorption than SubQ.
Topical and Other Routes
Transdermal: Patches applied to the skin for systemic absorption.
Inhalation: Using MDIs or nebulizers for rapid absorption through lung tissue.
Instillations: Eye, ear, nasal, vaginal, or rectal applications.
Medication Safety: The Rights and the Checks
To mitigate the risk of a medication error—defined as any preventable event that may lead to inappropriate use or patient harm—nurses must strictly adhere to standardized safety protocols.
The Three Medication Checks
Nurses should perform these checks to ensure accuracy:
Check #1: When pulling the medication from the dispensing system.
Check #2: During preparation (e.g., pouring or drawing up) and comparing it to the eMAR.
Check #3: At the bedside immediately before administration to the patient.
The Rights of Medication Administration
While many lists exist, the essential "rights" include:
Right Medication, Right Patient, Right Dosage, Right Route, Right Time, Right Reason, Right Assessment Data, Right Documentation, Right Response, Right Education, and the Right to Refuse.
Exam Tip: Patient Identification
Always use at least two identifiers before administration. Validate the patient's name (first identifier) and their date of birth or medical record number (second identifier) by checking their bracelet and asking them to state their name if possible.
Error Prevention and Reporting
Errors can occur due to inappropriate prescribing, wrong doses, incorrect routes, or even using deteriorated drugs. To maintain a safe environment, nurses should minimize distractions, finish one medication order before starting another, and never leave prepared medications unattended. Utilizing Bar Code-Enabled Medication Administration (BCMA) is a powerful technological tool to reduce these risks.
Reporting an Error
If an error occurs, do not panic, but act immediately using the "Check, Notify, Write, Complete" protocol:
Check: Assess the patient's condition immediately for adverse effects.
Notify: Inform the nurse manager and the primary healthcare provider.
Write: Document a description of the error and the remedial steps taken in the medical record.
Complete: Fill out the facility's specific incident or unusual occurrence report.
Handling Controlled Substances
Controlled substances are regulated due to their high potential for abuse. They require extra layers of security, including a double-locked system and secure ID codes.
Nurses must perform regular counts (usually every shift). If a portion of a controlled substance must be discarded (a process called "wasting"), it must be done in the presence of a second nurse who acts as a witness.
Documentation and Evaluation
The medication record is a legal document. Every administration must be documented, including the name of the medication, dosage, route, time, the site used for injections, and the name of the nurse administering it. If a patient refuses a medication or if a drug is omitted, this must also be recorded.
Finally, the nursing process is not complete until the nurse evaluates the effect of the medication. This involves:
Clinical Observation: Collecting subjective data (e.g., "How is your pain?") and objective data (e.g., vital signs).
Measurement: Checking drug serum levels (e.g., digoxin or vancomycin).
Monitoring: Using systems like cardiac monitors to watch for adverse reactions.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.