This content provides an overview of seizure disorders, including their etiology, types (tonic-clonic, absence, atonic), diagnostic testing, and essential nursing interventions during and after a seizure. It also covers emergency situations and long-term management strategies such as anticonvulsant medications and the
Seizure disorders represent a significant challenge in neurological nursing, characterized by disturbances in normal brain function due to neurological dysfunction. These disturbances can manifest as uncontrolled body movements, changes in behavior, or alterations in sensation. Because seizures can range from brief moments of "daydreaming" to life-threatening prolonged episodes, understanding their classification and the immediate nursing interventions required is critical for patient safety.
Understanding Seizure Etiology and Types
Seizures are not a single disease but a symptom of underlying neurological issues. They can be classified as either congenital (present from birth) or acquired. The underlying cause often depends on the patient's age:
Infants: Common causes include birth injury, hemorrhage, anoxia, or congenital defects.
Early Childhood: Often triggered by infections or physical trauma.
Older Children: Epilepsy is the most common cause, which is often idiopathic (meaning the cause is unknown).
A specific subset of seizures seen in pediatric populations is febrile seizures. These are often transient and occur in children aged 6 months to 5 years when body temperatures exceed 102.0∘F.
Clinical Classifications of Seizures
Diagram illustrating the tonic and clonic phases of a tonic-clonic seizure, showing muscle contractions and relaxations.
Nurses must be able to distinguish between different seizure types to provide accurate documentation and appropriate care:
Tonic-Clonic (Grand Mal)
This is a generalized seizure that occurs without warning and involves a loss of consciousness. It consists of two distinct phases:
Tonic Phase (10–30 seconds): The entire body contracts, the eyes roll upward, and the patient may experience apnea (cessation of breathing) and cyanosis (bluish skin color) due to the loss of the swallowing reflex.
Clonic Phase (30–50 seconds): This involves violent, rhythmic jerking movements caused by the contraction and relaxation of muscles. Patients may experience foaming at the mouth and incontinence.
Following these phases, the patient enters a postictal state, which can last about 30 minutes or longer. During this time, the patient is typically semiconscious, confused, or sleeps deeply, and they usually have no recollection of the event.
Absence (Petit Mal)
Typically onsetting around age 5 and ceasing by the teenage years, these seizures involve a brief loss of consciousness lasting only 5–10 seconds. They often resemble daydreaming, which can lead to poor academic performance. Physical signs may include lip smacking, eyelid twitching, or slight hand movements.
Atonic ("Drop Attacks")
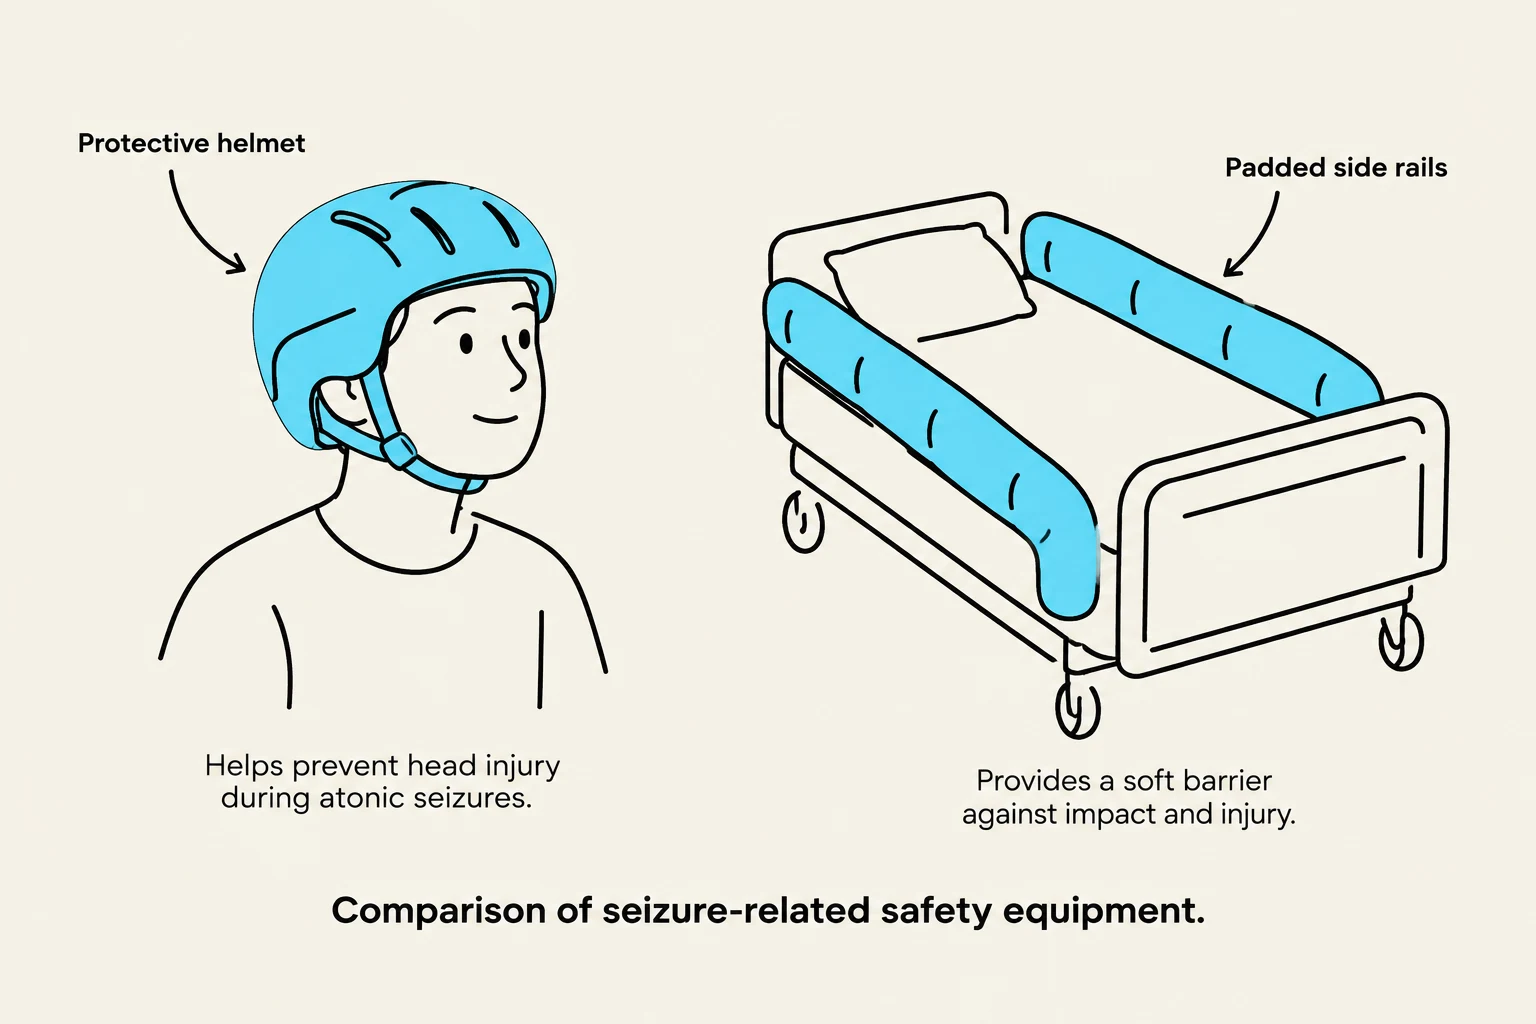
Atonic seizures involve a sudden loss of muscle tone. This often causes the patient to fall suddenly to the ground. Because of the risk of injury, these patients may need to wear protective gear, such as helmets.
Diagnostic Testing
To determine the cause and type of seizure disorder, healthcare providers utilize several diagnostic tools:
EEG (Electroencephalogram): To monitor electrical activity in the brain.
Imaging: CT scans or MRI scans to identify structural abnormalities.
Laboratory Tests: CBC, blood chemistries, lead levels, and toxicology screens to rule out metabolic or toxic causes.
Nursing Management: During the Seizure
The primary goal of nursing care during an active seizure is safety and injury prevention.
Immediate Interventions
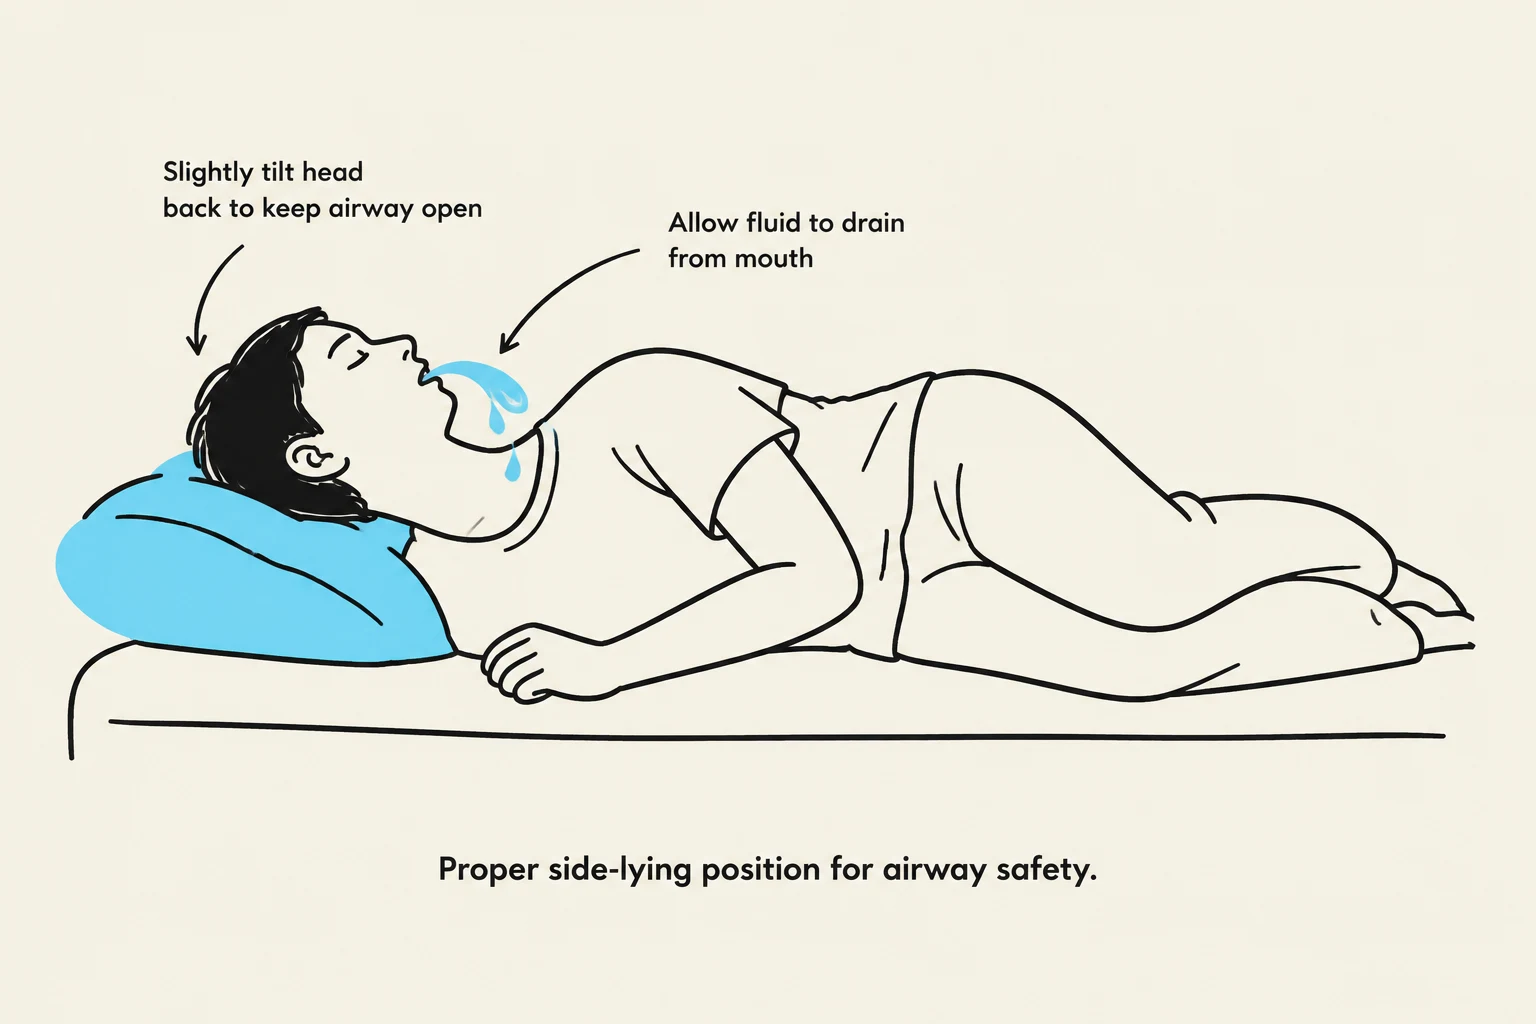
Proper side-lying position for airway safety.
When a seizure begins, the nurse should:
Protect the patient: Move loose objects away from the bed and ensure side rails are up and padded.
Maintain airway safety: Place the patient in a side-lying position to prevent aspiration.
Loosen clothing: Remove or loosen restrictive clothing to assist with breathing.
[!IMPORTANT]
NEVER attempt to restrain a patient during a seizure, and NEVER place anything in the patient's mouth. Restraining can lead to injury, and placing objects in the mouth can obstruct the airway or cause dental damage.
Observation and Documentation
Accurate documentation is essential for the medical team to adjust treatment. The nurse must note:
The exact onset and total duration of the seizure.
Specific body movements (e.g., which limbs were jerking).
Changes in color (cyanosis) or respirations.
Any incontinence or loss of muscle tone.
Ensure that suction equipment and oxygen are readily available at the bedside.
Emergency Situations: When to Call 911
While many seizures are managed in a clinical setting, certain scenarios constitute a medical emergency requiring immediate escalation:
The seizure lasts longer than 5 minutes.
Status epilepticus occurs (seizures lasting >30 minutes without a postictal phase).
The patient stops breathing.
The seizure occurs in water.
The patient is unresponsive to pain or cannot be awakened.
The patient has continuous vomiting for 30 minutes.
The patient's pupils are unequal following the seizure.
It is the patient's first seizure.
Post-Seizure Care and Long-Term Management
Once the seizure has ceased, the focus shifts to recovery and stabilization.
Acute Post-Seizure Care
Reorient the patient: Patients are often confused; provide a calm environment and reorient them to their surroundings.
Assess vitals: Check vital signs and monitor for any injuries sustained during the seizure.
Oxygenation: Administer oxygen if necessary to ensure adequate cerebral oxygenation.
Long-Term Medical Management
Many patients with seizure disorders require lifelong management to prevent recurrence:
Anticonvulsant Medications: Drugs such as Dilantin, Depakene, Tegretol, valproic acid, or clonazepam are commonly used. It is vital to instruct patients to take these medications at the same time every day and to never discontinue them without medical supervision.
Ketogenic Diet: For some patients, a specialized diet high in fat, adequate in protein, and low in carbohydrates may be prescribed to help control seizures.
Patient and Family Education
Comparison of seizure-related safety equipment, including a protective helmet and padded side rails for beds.
Effective education reduces the risk of breakthrough seizures and improves quality of life:
Identify Triggers: Teach patients to avoid known precipitants such as stress and fatigue.
Safety Measures: Encourage the use of a medical alert bracelet. For those at high risk of falling, discuss the use of helmets. For those at risk of drowning, suggest taking showers instead of baths (with the door unlocked).
Medication Awareness: Inform patients that anticonvulsants can interact with oral contraceptives.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.