This content discusses causes, risk factors, expected findings, laboratory tests, diagnostic procedures, nursing care, and client education for various types of vaginal bleeding during pregnancy.
Vaginal bleeding during pregnancy is always considered an abnormal finding that requires immediate medical evaluation. Because bleeding can signal life-threatening complications for both the mother and the fetus, the clinical management strategy is heavily dependent on the gestational age of the pregnancy and the underlying cause. Understanding the distinction between first-trimester and third-trimester bleeding is essential for providing appropriate nursing interventions and ensuring patient safety.
First Trimester Causes
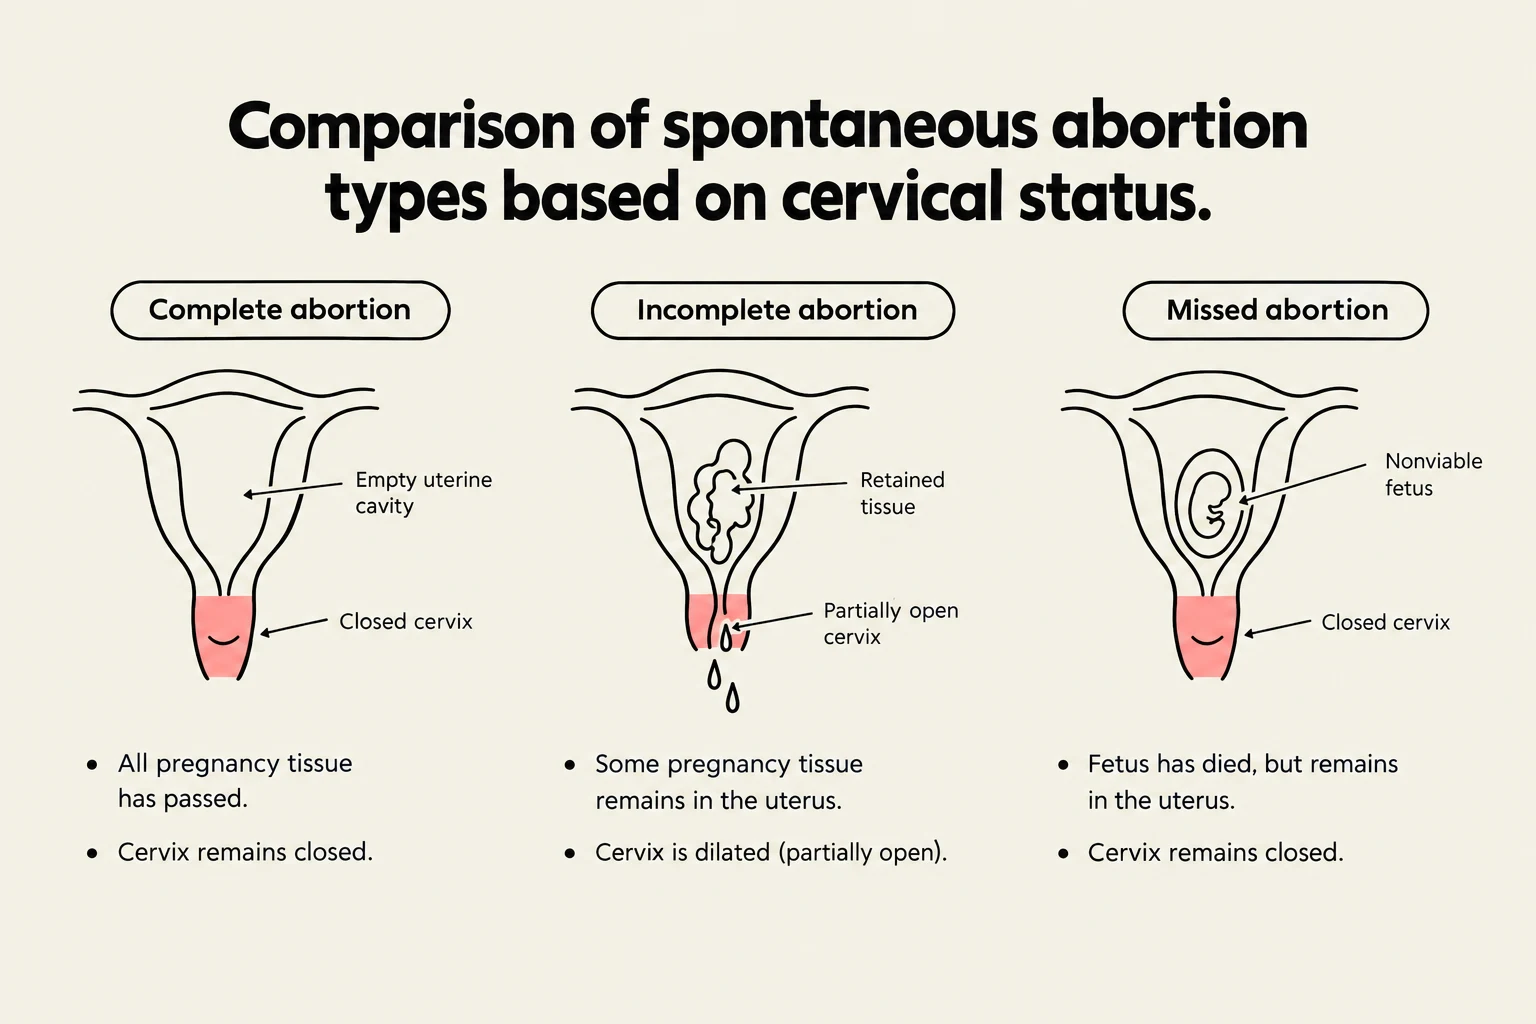
Comparison of spontaneous abortion types based on cervical status, illustrating complete, incomplete, and missed abortions.
Bleeding in the first trimester often relates to the early establishment of the pregnancy or complications in the implantation process.
Spontaneous Abortion
A spontaneous abortion is a pregnancy loss occurring before 20 weeks of gestation. It is classified into several types:
Threatened: Bleeding occurs, but the cervix remains closed and the fetus is still viable.
Inevitable: Bleeding and contractions occur, and the cervix dilates.
Incomplete: Some products of conception are expelled, but some remain in the uterus.
Complete: All products of conception are expelled.
Missed: The fetus has died in utero, but the body has not yet expelled the products of conception.
Nursing care focuses on monitoring the amount of bleeding, providing emotional support to the grieving client, and administering medications such as oxytocin to assist in expulsion or Rho(D) immune globulin if the mother is Rh-negative.
Ectopic Pregnancy
An ectopic pregnancy occurs when the ovum implants outside the uterine cavity, most commonly within the fallopian tubes. This is a surgical emergency if the tube ruptures.
Expected Findings: Unilateral stabbing pelvic pain and referred shoulder pain, which is a classic indicator of a ruptured tube and internal bleeding.
Management: Treatment may include the medication methotrexate or surgical intervention such as a salpingectomy (removal of the fallopian tube).
Nursing Alert: If a client is prescribed methotrexate, they must be educated to avoid folic acid, as it can interfere with the medication's effectiveness in stopping cell growth.
Also known as a hydatidiform mole, this involves an abnormal proliferation of trophoblastic villi that appear as grape-like clusters.
Complete Mole: No fetus is present.
Partial Mole: Abnormal fetal parts may be present.
Expected Findings: Excessive vomiting (due to abnormally high hCG levels) and a uterus that is larger than expected for the gestational age.
Follow-up: Long-term monitoring of serum hCG levels is critical to ensure the condition does not progress to choriocarcinoma (a type of cancer).
Third Trimester Causes
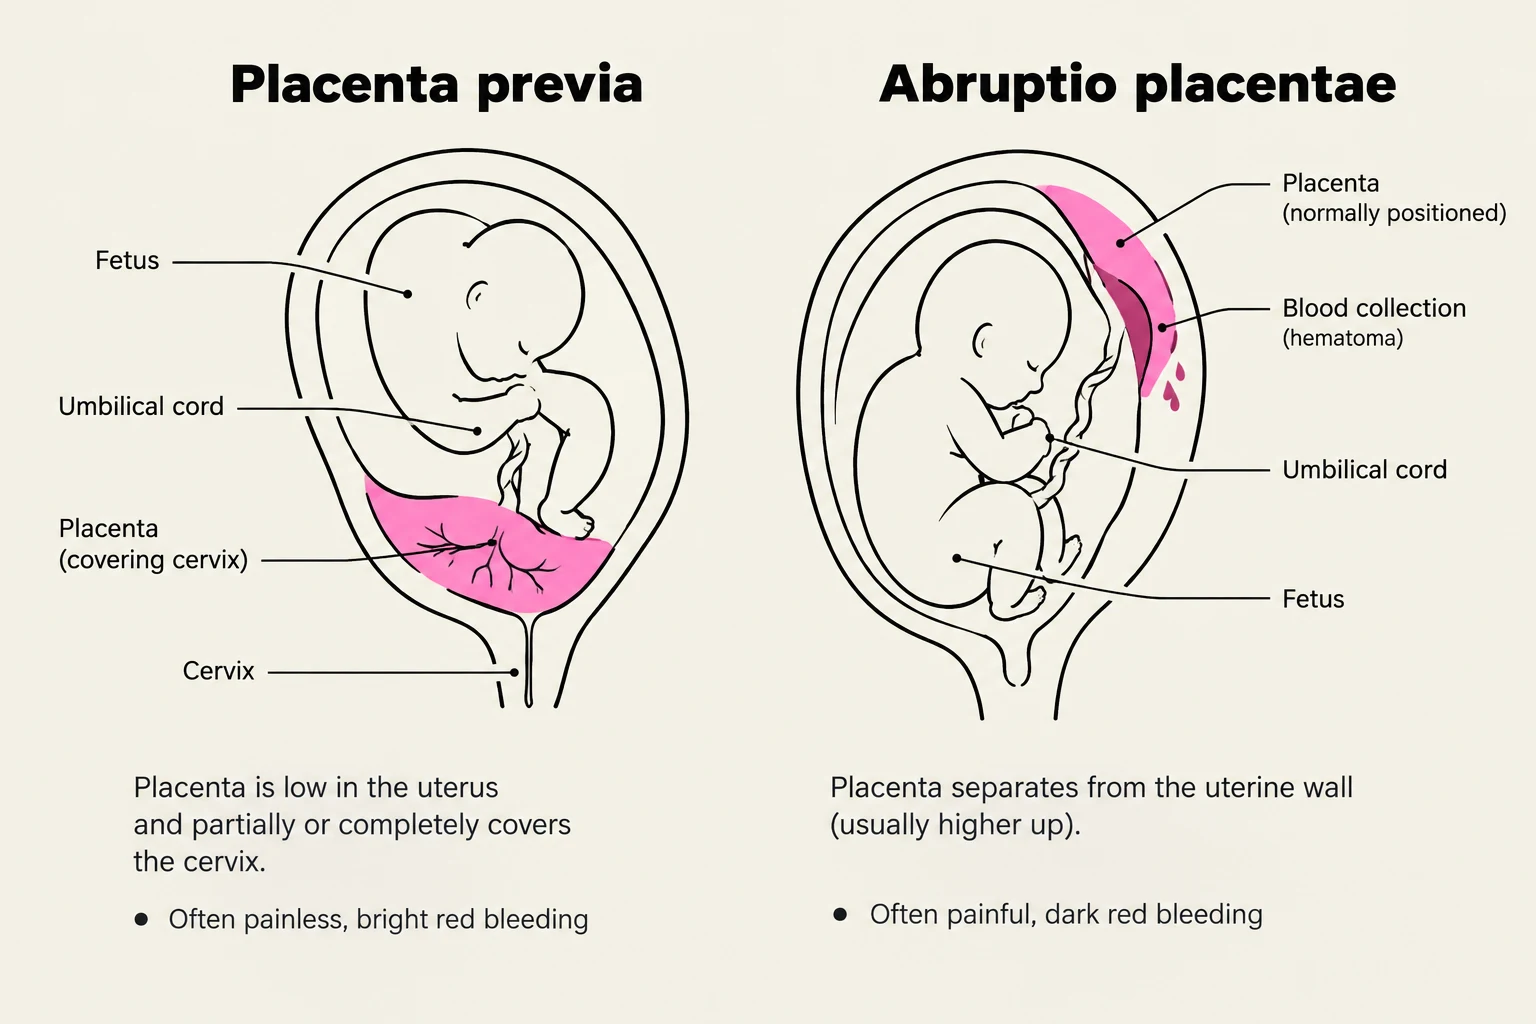
Diagrams illustrating Placenta previa and Abruptio placentae, two conditions affecting pregnancy. Placenta previa shows the placenta covering the cervix, while Abruptio placentae depicts the placenta separating from the uterine wall.
Bleeding in the third trimester is often associated with placental complications and is frequently a medical emergency.
Placenta Previa
In placenta previa, the placenta implants over or near the cervical os.
Expected Findings:Painless, bright red vaginal bleeding and a soft, non-tender uterus.
Crucial Nursing Action:Do NOT perform a vaginal exam on a client suspected of having placenta previa, as this can cause massive hemorrhage.
Management: Includes bed rest and continuous monitoring of fetal well-being.
Abruptio Placentae
This is the premature separation of the placenta from the uterine wall, which can deprive the fetus of oxygen.
Expected Findings:Sudden, intense uterine pain, dark red bleeding, and a boardlike, tender uterus.
Management: This is a medical emergency. Nursing care includes administering oxygen, monitoring for signs of shock, and preparing the client for an emergency delivery.
Vasa Previa
In vasa previa, the fetal umbilical vessels are implanted into the fetal membranes, crossing the internal os. This condition carries a high risk of fetal exsanguination during labor, requiring extremely close monitoring of fetal heart tones.
Diagnostic and Laboratory Evaluation
To determine the cause of bleeding, healthcare providers utilize several diagnostic tools:
Laboratory Tests
hCG Levels: High levels may suggest a hydatidiform mole or multiple pregnancy, while lower-than-expected levels might suggest a miscarriage.
Blood Work: Hemoglobin and hematocrit are monitored to assess blood loss; blood type and Rh factor are checked to determine the need for Rho(D) immune globulin.
Specific Tests: For suspected preterm labor, fetal fibronectin may be tested. For suspected preeclampsia, liver enzymes (AST, LDH) and creatinine are monitored.
Diagnostic Procedures
Ultrasound: Used to visualize the fetus and determine placental location.
Nitrazine/Ferning Tests: Used to confirm the rupture of membranes (PROM) by checking the pH and crystal pattern of vaginal fluid.
Nonstress Test (NST): Used to monitor fetal well-being during episodes of bleeding.
Nursing Care and Client Education
Nursing Interventions
The priority in nursing care is the stabilization of both the mother and the fetus.
Assessment: Monitor vital signs (looking for signs of shock like tachycardia or hypotension), assess the amount and color of bleeding, and monitor fetal heart rates.
Positioning: Encourage the client to remain in a lateral (side-lying) position to optimize placental perfusion.
Safety: In cases of suspected placenta previa, avoid all vaginal examinations.
Medication Administration: Administer medications such as magnesium sulfate (for preeclampsia) or betamethasone (to enhance fetal lung maturity in preterm labor) as ordered.
Client Education
Education should be tailored to the specific complication but generally includes:
Activity Restrictions: Adhering to bed rest with bathroom privileges and avoiding sexual intercourse or anything inserted into the vagina (e.g., tampons).
Symptom Reporting: Instructing the client to immediately report any increase in bleeding, abdominal pain, or changes in fetal movement (kick counts).
Infection Prevention: For clients with ruptured membranes, emphasize hygiene (wiping front to back) and reporting any foul-smelling discharge or fever.
Exam Tip: When distinguishing between Placenta Previa and Abruptio Placentae, remember: Previa is painless and bright red; Abruption is painful and dark red.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.