Nursing Care of Patients with Cardiac Dysrhythmias
A comprehensive guide to understanding and managing cardiac dysrhythmias, covering EKG interpretation, common rhythms, emergency interventions, and psychosocial support for patients.
Managing patients with cardiac dysrhythmias is a critical nursing competency that bridges physiological stability with psychosocial support. For a nurse, success in this area requires more than just recognizing a rhythm on a monitor; it demands rapid clinical assessment, precise EKG interpretation, and the ability to intervene during life-threatening emergencies. Whether you are managing a stable patient with atrial fibrillation or responding to a pulseless ventricular fibrillation, your ability to integrate pharmacological knowledge with technical skills like defibrillation is vital to patient outcomes.
Foundations of EKG Interpretation
Before diagnosing a dysrhythmia, a nurse must master the components of a normal sinus rhythm. Accuracy in EKG interpretation is the foundation of all subsequent nursing actions. When assessing an EKG strip, you should systematically evaluate the following:
P waves: Ensure there is one P wave for every QRS complex.
PR Interval: This should measure between 0.12−0.20 seconds. A PR interval greater than 0.20 seconds indicates a first-degree AV block.
QRS Interval: This should be narrow, measuring between 0.06−0.12 seconds. A wider QRS (greater than 0.12 seconds) may indicate a bundle branch block.
ST Segment: Look for any elevations or inversions, which can indicate myocardial ischemia or injury.
T wave: Typically upright; peaked or flat T waves can indicate electrolyte imbalances.
Diagram illustrating the components of an electrocardiogram (ECG) waveform, including the P wave, QRS complex, ST segment, and PR interval, with explanations of their physiological significance in atrial and ventricular depolarization and repolarization.
Calculating Heart Rate
To determine the heart rate, you can use the large box method or the small box method. For a regular rhythm, you can count the number of large boxes between two R waves and divide 300 by that number. For example, if there are 4 large boxes between R waves:
Heart Rate=4300=75 bpm
Sinus Dysrhythmias
Sinus dysrhythmias originate from the SA node but deviate from the normal rate.
Sinus Bradycardia
This rhythm is characterized by a slow heart rate. Common causes include hypoxia, medications, or physiological triggers like the Valsalva maneuver, gagging, or suctioning. Patients may present with pale, cool skin, hypotension, confusion, or syncope.
Nursing Alert: Treatment is indicated only if the patient is symptomatic.
Management includes administering oxygen and IV Atropine (1 mg every 3−5 minutes, up to a maximum of 3 mg). If Atropine is ineffective, the patient may require temporary or permanent pacing.
Sinus Tachycardia
Sinus tachycardia involves a rapid heart rate often caused by fever, pain, hypovolemia, exercise, or stimulants. Unlike bradycardia, the primary nursing intervention is to treat the underlying cause (e.g., administering fluids for hypovolemia or antipyretics for fever).
Atrial Dysrhythmias
Atrial dysrhythmias originate above the ventricles and often pose a significant risk for thromboembolism (blood clots).
Atrial Fibrillation (Afib) and Atrial Flutter
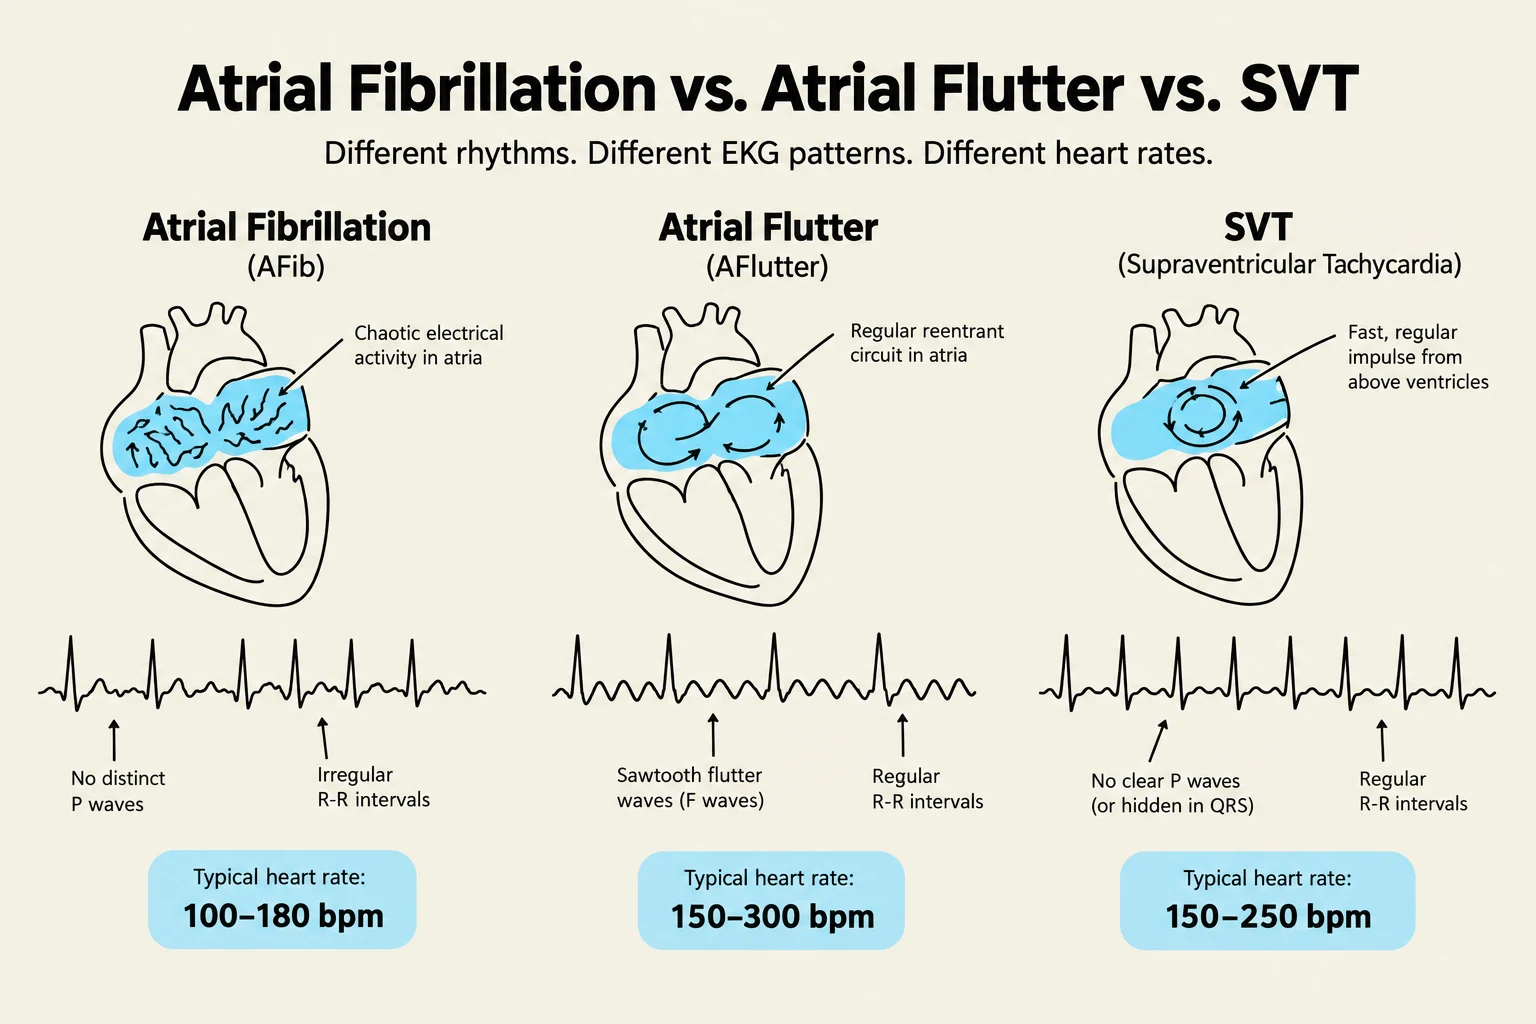
Atrial Fibrillation is characterized by an irregular rhythm and rapid atrial rates between 350−600 bpm. This rhythm significantly decreases cardiac output and carries a high risk for blood clots.
Atrial Flutter presents with a regular rhythm and a characteristic sawtooth-shaped pattern on the EKG, with atrial rates of 240−340 bpm.
For both rhythms, the nursing management strategy depends on the patient's stability:
Unstable Patients ("Edison before Medicine"): Prioritize electrical intervention via synchronized cardioversion (50−100 Joules).
Stable Patients ("Medicine before Edison"): Prioritize pharmacological management using Amiodarone, Beta Blockers, Calcium Channel Blockers, or Digoxin.
Premature Atrial Contractions (PACs) and SVT
PACs are ectopic beats caused by stress, fatigue, or stimulants (tobacco/alcohol). They may be asymptomatic or cause palpitations.
Supraventricular Tachycardia (SVT) is a regular, rapid rhythm (150−200 bpm) with a narrow QRS. If the patient is stable, nurses may assist with vagal maneuvers or administer Adenosine (6 mg IVP, followed by 12 mg if needed).
This illustration compares Atrial Fibrillation (AFib), Atrial Flutter (AFlutter), and Supraventricular Tachycardia (SVT), detailing their distinct EKG patterns, electrical activity in the atria, and typical heart rates.
Ventricular Dysrhythmias: The Lethal Rhythms
Ventricular dysrhythmias are often more dangerous because they originate in the ventricles, directly impacting the heart's ability to pump blood to the body.
Premature Ventricular Contractions (PVCs): These are ectopic beats that may feel like a "skipped beat".
Ventricular Tachycardia (VT): Can be monomorphic (all beats look the same) or polymorphic (beats look different).
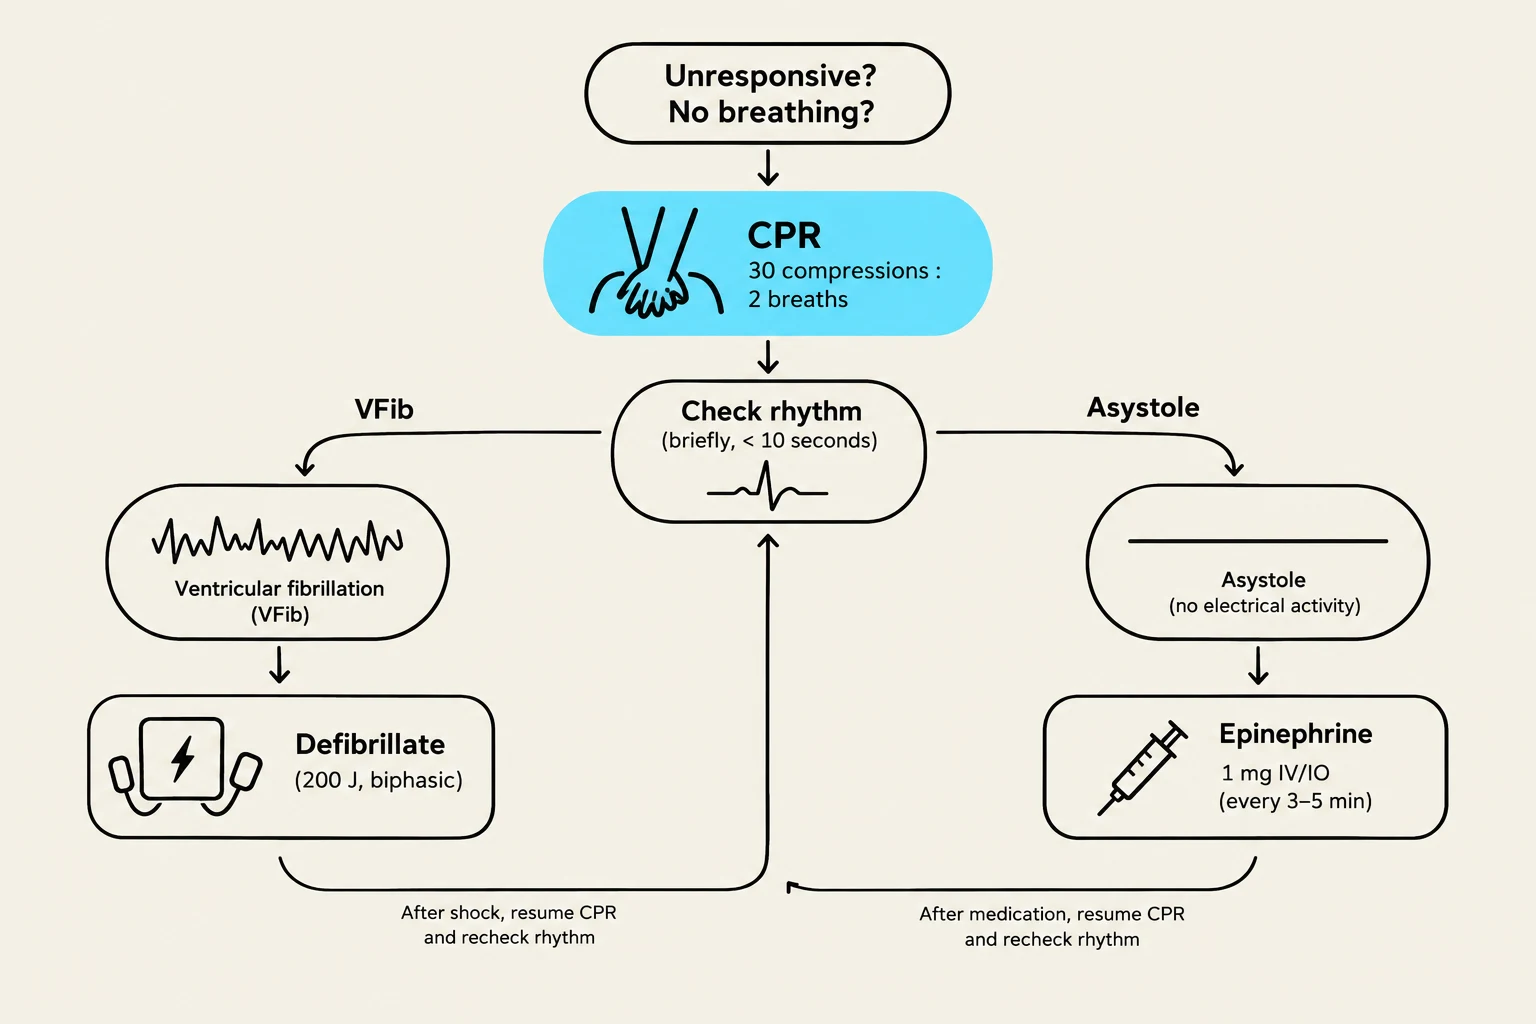
Ventricular Fibrillation (VFib): A lethal rhythm where there is no measurable electrical activity. The patient will be unresponsive and pulseless.
Asystole: The total absence of ventricular activity. This is a lethal rhythm often caused by hypoxia or acidosis.
Emergency Interventions and Pharmacology
When a patient enters a pulseless rhythm, such as VFib or pulseless VT, the nurse must act immediately.
Defibrillation vs. Cardioversion
The most critical distinction in emergency cardiac care is the use of "Sync" mode:
Cardioversion: Used for stable patients with organized rhythms (like Afib or SVT). The machine is in synchronized mode to ensure the shock is delivered on the R wave.
Defibrillation: Used for unstable, pulseless rhythms (VFib/Pulseless VT). The synchronized mode must be OFF.
Energy Settings:
Monophasic Defibrillator: 360 Joules.
Biphasic Defibrillator: 120−200 Joules.
Emergency Pharmacology
During a cardiac arrest (VFib/Pulseless VT), the standard pharmacological interventions include:
Epinephrine: 1 mg administered every 3−5 minutes.
Amiodarone: A 300 mg bolus (followed by 150 mg if needed).
Critical Note on Asystole: If the rhythm is Asystole, focus on high-quality CPR and Epinephrine. Do not shock the patient.
This flowchart outlines the emergency response protocol for an unresponsive individual who is not breathing, detailing steps for CPR, rhythm checks, defibrillation for Ventricular Fibrillation (VFib), and administration of Epinephrine for Asystole.
Psychosocial Integrity and Patient Education
Nursing care extends beyond the monitor. Patients experiencing dysrhythmias often face significant anxiety, fear of death, and lifestyle limitations.
Education should focus on:
Risk Reduction: Discussing the impact of smoking, excessive caffeine, alcohol, and stress on heart rhythm.
Symptom Recognition: Teaching patients to recognize palpitations, dizziness, or shortness of breath.
Self-Care: Encouraging lifestyle modifications to manage underlying causes like hypertension or electrolyte imbalances.
By addressing both the physiological emergency and the psychosocial impact, the nurse provides holistic, high-quality care to the client with cardiovascular disorders.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.