This guide covers the definition and management of high-risk pregnancies, including psychological considerations, infections, metabolic disorders like diabetes, hypertensive disorders, hemorrhagic disorders, and trauma. It details nursing interventions and potential complications for both mother and fetus.
Pregnancy is a physiological process that involves significant metabolic and systemic changes. However, when these changes—or external factors—jeopardize the health of the mother or the newborn, the pregnancy is classified as "high-risk". A high-risk pregnancy is defined as one where the life or health of the mother or newborn is endangered by medical, social, or environmental factors coincident with or unique to pregnancy. This period of risk extends to six weeks postpartum, as many complications only manifest after childbirth.
Psychological Considerations
A high-risk diagnosis can trigger a situational crisis within a family. Parents may experience profound grief over the loss of the "ideal" healthy pregnancy they had envisioned. This often manifests as increased fear and anxiety regarding the unknown. It is critical for nurses to recognize that heightened maternal anxiety can physiologically contribute to preterm birth.
Infections and Sexually Transmitted Infections (STIs)
Infections can have devastating effects on both the mother and the developing fetus.
Common STIs
Gonorrhea: Often asymptomatic but can cause urinary burning or pelvic pain. It poses a risk for salpingitis in the mother and eye infections in the newborn. Newborns are typically treated with Erythromycin eye ointment.
Chlamydia: Frequently asymptomatic but can lead to ectopic pregnancy, premature labor, or premature rupture of membranes. Newborns may develop conjunctivitis or pneumonia.
Human Papilloma Virus (HPV): Characterized by anogenital warts, which may block the birth canal and necessitate a Cesarean section.
Herpes Simplex Virus (HSV): If active lesions are present during labor, a Cesarean section is scheduled to prevent neonatal transmission. Acyclovir is the drug of choice.
Hepatitis B (HBV): A viral liver disease that is often "silent". Infants born to HBV-positive mothers must receive the HBV vaccine and HBIG within the first 12 hours of life.
Vaginal Infections
Candidiasis (Yeast Infection): Common in pregnancy, especially in clients with HIV or gestational diabetes. Note that Fluconazole is contraindicated in pregnancy.
Trichomoniasis: Associated with preterm labor and low birth weight. It is treated with oral Flagyl.
Metabolic Disorders: Diabetes Mellitus
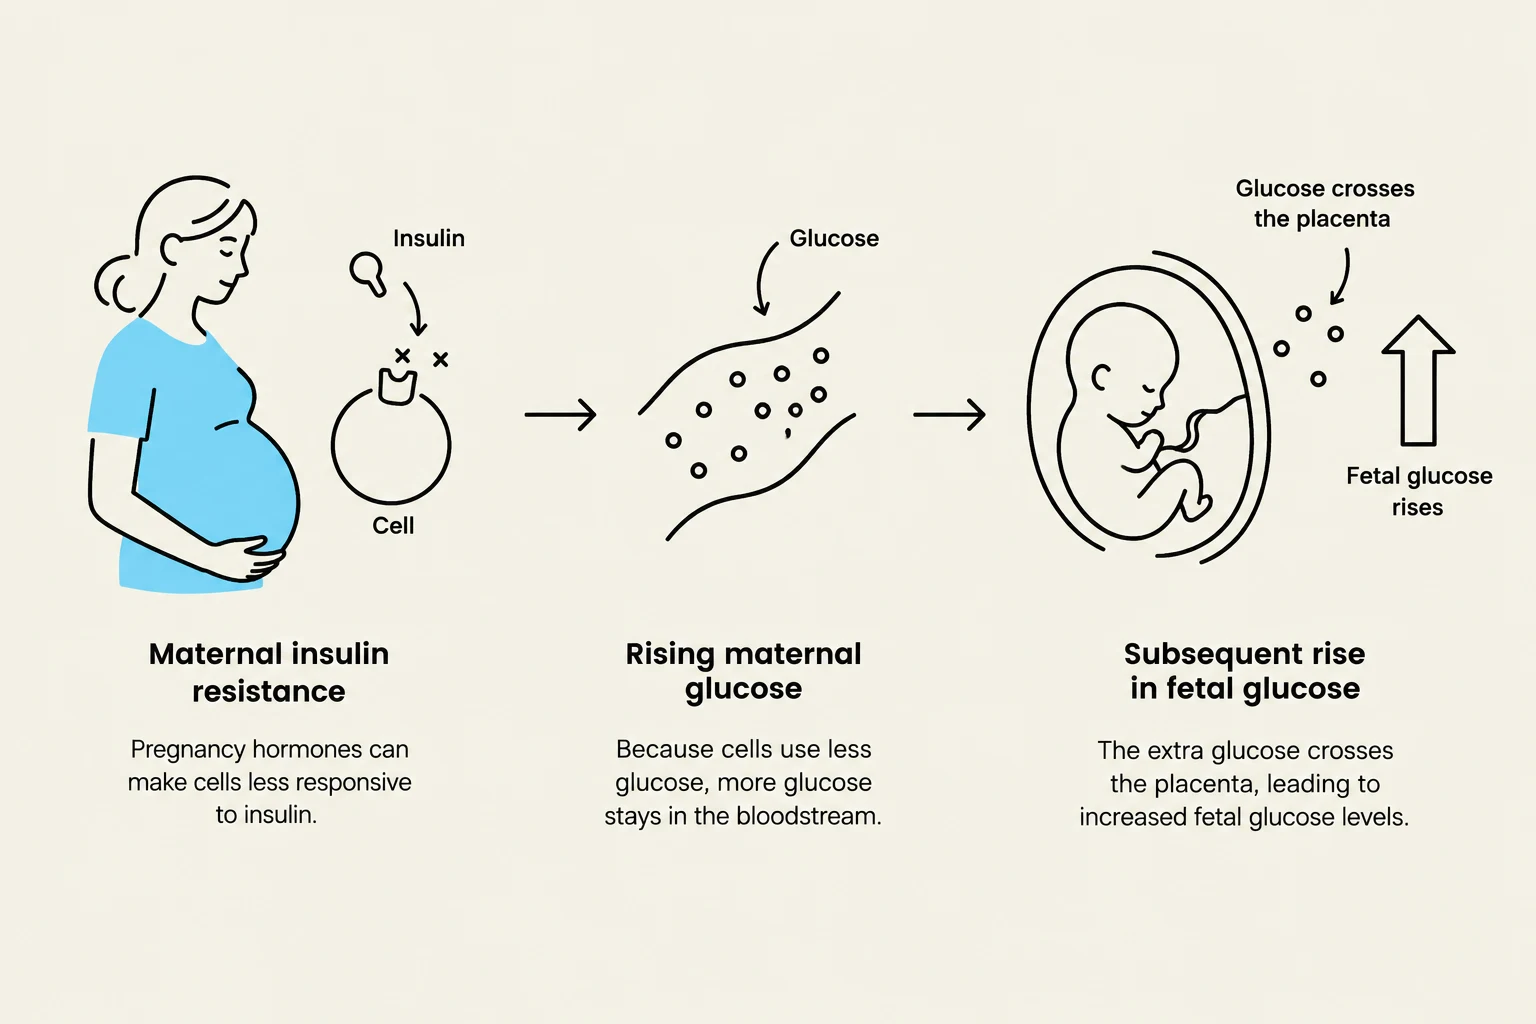
Diabetes management is complex because maternal glucose levels directly influence fetal glucose levels.
Pre-gestational vs. Gestational Diabetes
In pre-gestational diabetes (Type 1 or 2), the mother is already diabetic. These clients are at risk for congenital malformations if hyperglycemia is uncontrolled during the first trimester.
Gestational Diabetes Mellitus (GDM) is defined as glucose intolerance first recognized during pregnancy, typically in the second or third trimester. During this time, hormonal changes increase insulin resistance, raising the body's demand for insulin.
Clinical Note: Screening for GDM
Screening typically occurs between 24–28 weeks gestation using a 1-hour plasma glucose test following a 50-gram glucose load.
Risks to the Fetus:
Macrosomia (large birth size), which can lead to birth injuries.
Hypoglycemia at birth.
Increased risk of CNS defects (e.g., spina bifida) and cardiac defects.
This diagram illustrates the process of maternal insulin resistance leading to rising maternal glucose levels, which then cross the placenta and cause a subsequent rise in fetal glucose.
Hypertensive Disorders of Pregnancy
Hypertension in pregnancy is defined by a systolic BP ≥140 mmHg or a diastolic BP ≥90 mmHg.
Pre-existing Hypertension: Diagnosed before 20 weeks gestation.
Gestational Hypertension: New-onset hypertension after 20 weeks without proteinuria.
Pre-eclampsia: A multisystem, vasospastic disease characterized by hypertension and proteinuria. It can lead to organ dysfunction, such as renal failure or hepatic hematoma.
Eclampsia: The onset of seizures in a woman with pre-eclampsia.
HELLP Syndrome: A severe variation of pre-eclampsia involving Hemolysis, Elevated Liver enzymes, and Low Platelets.
Nursing Care for Severe Pre-eclampsia and Eclampsia
Clients with severe pre-eclampsia require hospitalization and seizure precautions.
Medication: Magnesium sulfate is used to prevent seizures. Nurses must monitor deep tendon reflexes (DTRs); a decrease in DTRs may indicate magnesium toxicity. Calcium gluconate should be available to reverse toxicity.
Seizure Management: If a seizure occurs, maintain the airway, administer oxygen, place the client in the recovery position, and record the duration.
Definitive Cure: Delivery of the placenta is the only definitive cure for eclampsia.
Hemorrhagic Disorders and Placental Variations
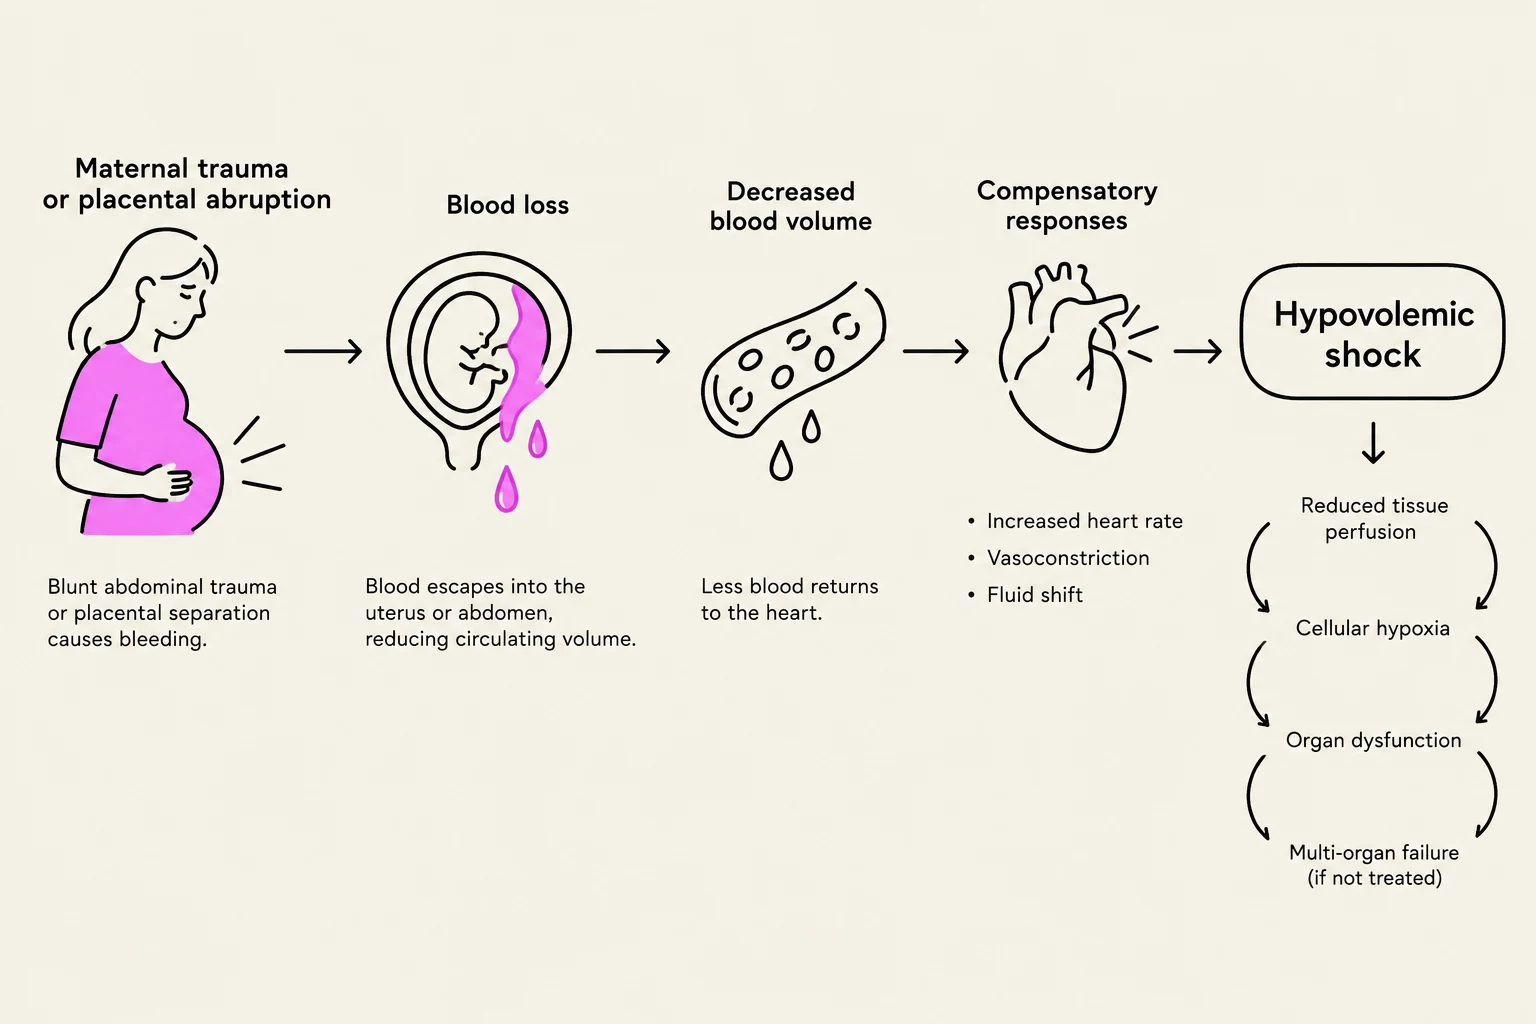
Bleeding during pregnancy is a medical emergency that can lead to hypovolemic shock.
Ectopic Pregnancy: Occurs when a fertilized egg implants outside the uterus.
Placenta Previa: The placenta covers the cervical opening.
Placental Abruption: The premature separation of the placenta from the uterine wall.
Miscarriage Terminology: A "threatened" miscarriage involves scant bleeding and no cervical dilation. An "imminent" miscarriage involves uterine contractions and cervical dilation.
Disseminated Intravascular Coagulation (DIC): A pathological clotting cascade often triggered by placental abruption, which uses up clotting factors and leads to massive bleeding.
This diagram illustrates the progression of hypovolemic shock, starting from maternal trauma or placental abruption leading to blood loss, decreased blood volume, and compensatory responses, ultimately resulting in hypovolemic shock with reduced tissue perfusion, cellular hypoxia, organ dysfunction, and potential multi-organ failure if untreated.
Amniotic Fluid and Fetal Growth
The volume of amniotic fluid is a critical indicator of fetal well-being:
Oligohydramnios: Inadequate amount of amniotic fluid.
Hydramnios (Polyhydramnios): Excessive amount of amniotic fluid.
Intrauterine Growth Restriction (IUGR): Often associated with placental issues or hypertensive disorders, where the fetus does not reach its growth potential.
Trauma and Other Complications
Trauma is the leading cause of non-obstetrical death in pregnant women. Common causes include motor vehicle accidents (MVAs) and intimate partner violence (IPV).
Priority of Care in Trauma
In the event of trauma, the nurse's priority is to resuscitate and stabilize the mother first; fetal needs are addressed only after maternal stability is achieved.
Potential complications of trauma include uterine rupture, preterm labor, and placental abruption. Nurses must perform a rapid assessment of Airway, Breathing, and Circulation (ABCs) and initiate IV access immediately.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.