Comprehensive guide to nursing interventions for managing bowel elimination, including assessment, common alterations (constipation, diarrhea, impaction), ostomy care, nutritional and hydration management, bowel training, and psychosocial support.
Effective bowel elimination is a cornerstone of patient comfort, nutrition, and systemic health. For nurses, managing bowel elimination involves much more than simply monitoring stool frequency; it requires a comprehensive approach that integrates physical assessment, skin protection, nutritional management, and psychosocial support. Whether a patient is dealing with common issues like constipation and diarrhea or managing a permanent surgical diversion like an ostomy, the nursing goal remains the same: to promote predictable elimination patterns while maintaining skin integrity and patient dignity.
Assessment and Common Alterations
Nursing care begins with a thorough assessment of the patient's baseline bowel patterns, including the last bowel movement, stool form, abdominal distention, and the presence of pain or nausea. Nurses must also consider factors that influence elimination, such as age, diet, fluid intake, physical activity, and medications like opioids or anticholinergics.
Common challenges encountered in clinical practice include:
Constipation: Infrequent or difficult stool passage, often requiring interventions like increased fluids, fiber, and scheduled toileting.
Fecal Impaction: Hardened stool retained in the rectum. This can present as constipation or "paradoxical" liquid stool leakage around the mass.
Diarrhea: Frequent, loose stools that pose high risks for dehydration and skin breakdown.
Fecal Incontinence: The involuntary loss of stool, which requires a focus on dignity and identifying reversible causes, such as neurologic impairment or constipation.
Clinical Alert: The Impaction Paradox
If a patient reports constipation but is experiencing small amounts of watery stool leakage, do not assume they have diarrhea. This is often a sign of fecal impaction, where liquid stool seeps around a hardened mass.
Ostomy Care: Assessment and Pouching
For patients with bowel diversions, such as colostomies or ileostomies, nursing care shifts toward managing a surgically created opening. The type of ostomy dictates the expected output: colostomies generally produce thicker stool, while ileostomies produce liquid, enzymatic output.
Ostomy Assessment Priorities
The primary assessment focus is the stoma itself. A healthy stoma should be pink to beefy red and moist. Nurses must immediately report any stoma that appears dusky, pale, black, or dry, as these are signs of compromised blood flow. Additionally, the peristomal skin must be inspected for redness, denudement, or leakage injury.
Pouching and Skin Integrity
Proper pouching is essential to prevent skin breakdown and odor.
Fit: The wafer opening should be cut close to the stoma size to protect the surrounding skin.
Emptying: Empty the pouch when it is one-third to one-half full to prevent weight from pulling the seal away from the skin, which causes leaks.
Cleaning: Use water to clean the skin; avoid oily soaps that can interfere with the wafer's adhesion.
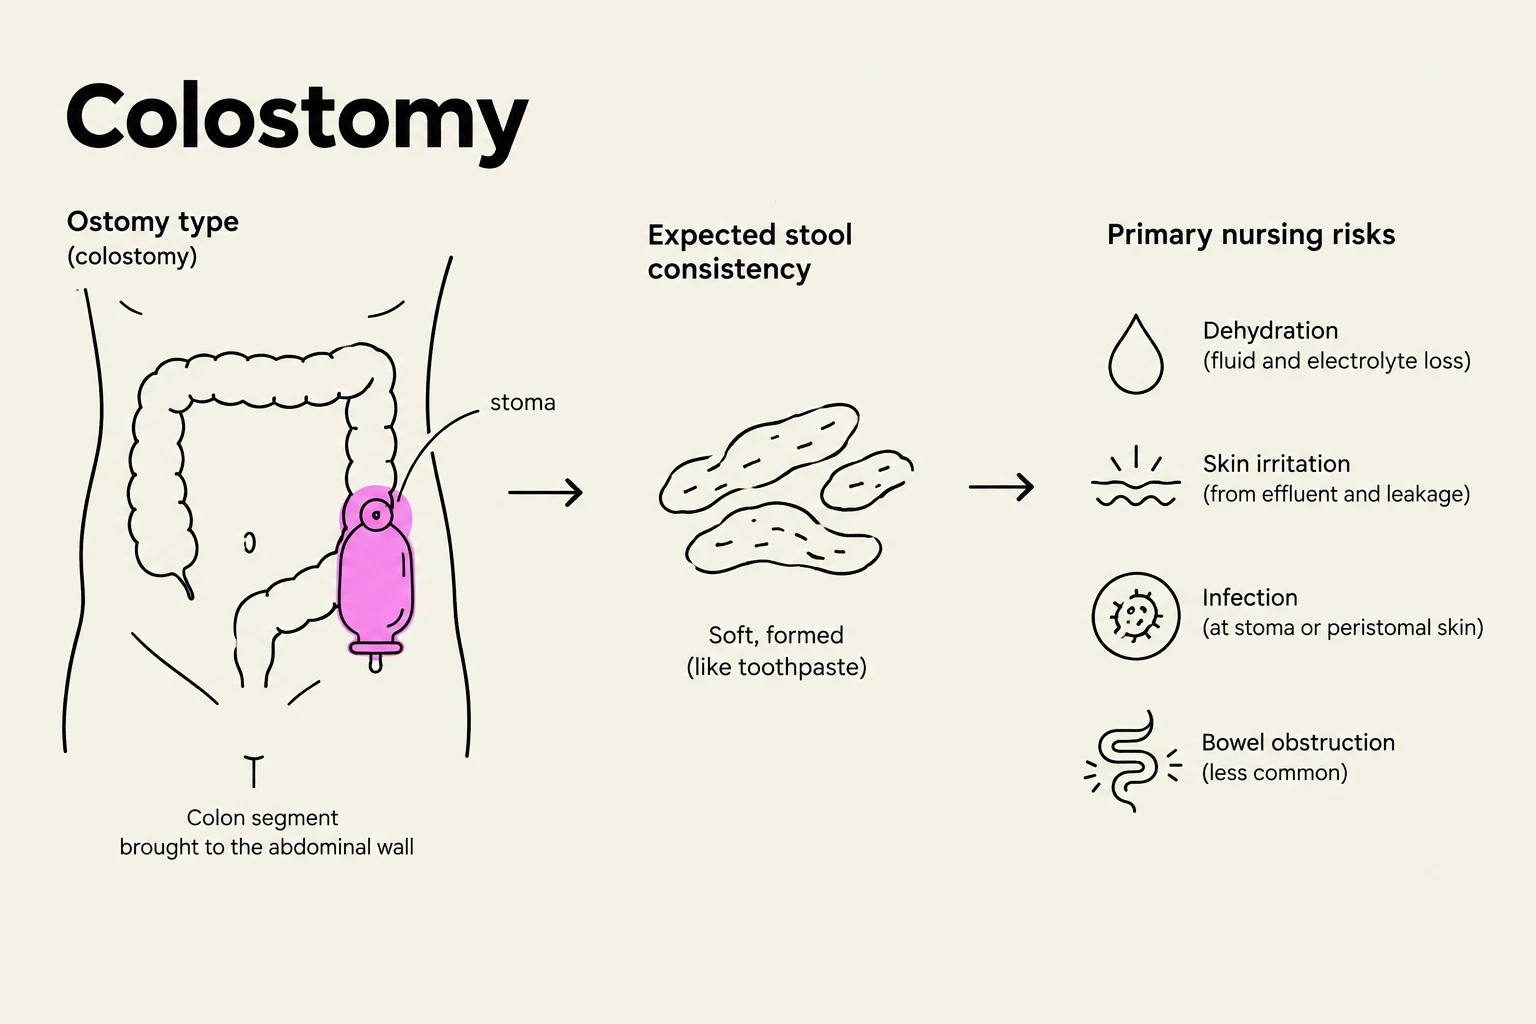
This diagram illustrates a colostomy, showing the ostomy type, expected stool consistency, and primary nursing risks associated with it, including dehydration, skin irritation, infection, and bowel obstruction.
Nutritional and Hydration Management
Bowel alterations can rapidly escalate into systemic problems involving fluid, electrolyte, and nutritional status.
Hydration and Electrolytes
Patients with diarrhea or high-output ileostomies are at significant risk for dehydration and electrolyte imbalances. Nurses should monitor:
Intake and Output (I&O): Tracking total fluids versus losses.
Vital Signs: Watching for tachycardia or hypotension, which may indicate dehydration.
Laboratory Values: Monitoring electrolytes (potassium, sodium, magnesium) and renal function (BUN/creatinine).
Nutritional Considerations
Dietary management is individualized. For ostomy patients, it is often recommended to advance the diet slowly, using small, frequent meals and thorough chewing. Patients should be taught to identify "trigger foods" that increase gas, odor, or diarrhea.
Bowel Training and the Gastrocolic Reflex
For patients with functional constipation or fecal incontinence, nurses can implement bowel training to restore predictable elimination. A key physiological tool in this process is the gastrocolic reflex, which is the stimulation of peristalsis following food intake.
Implementation of Bowel Training:
Timed Toileting: Schedule toileting after meals (e.g., breakfast) to take advantage of the gastrocolic reflex.
Positioning: Encourage an upright sitting position with feet supported and knees slightly elevated.
Consistency: Combine the routine with adequate fluids, fiber, and physical activity.
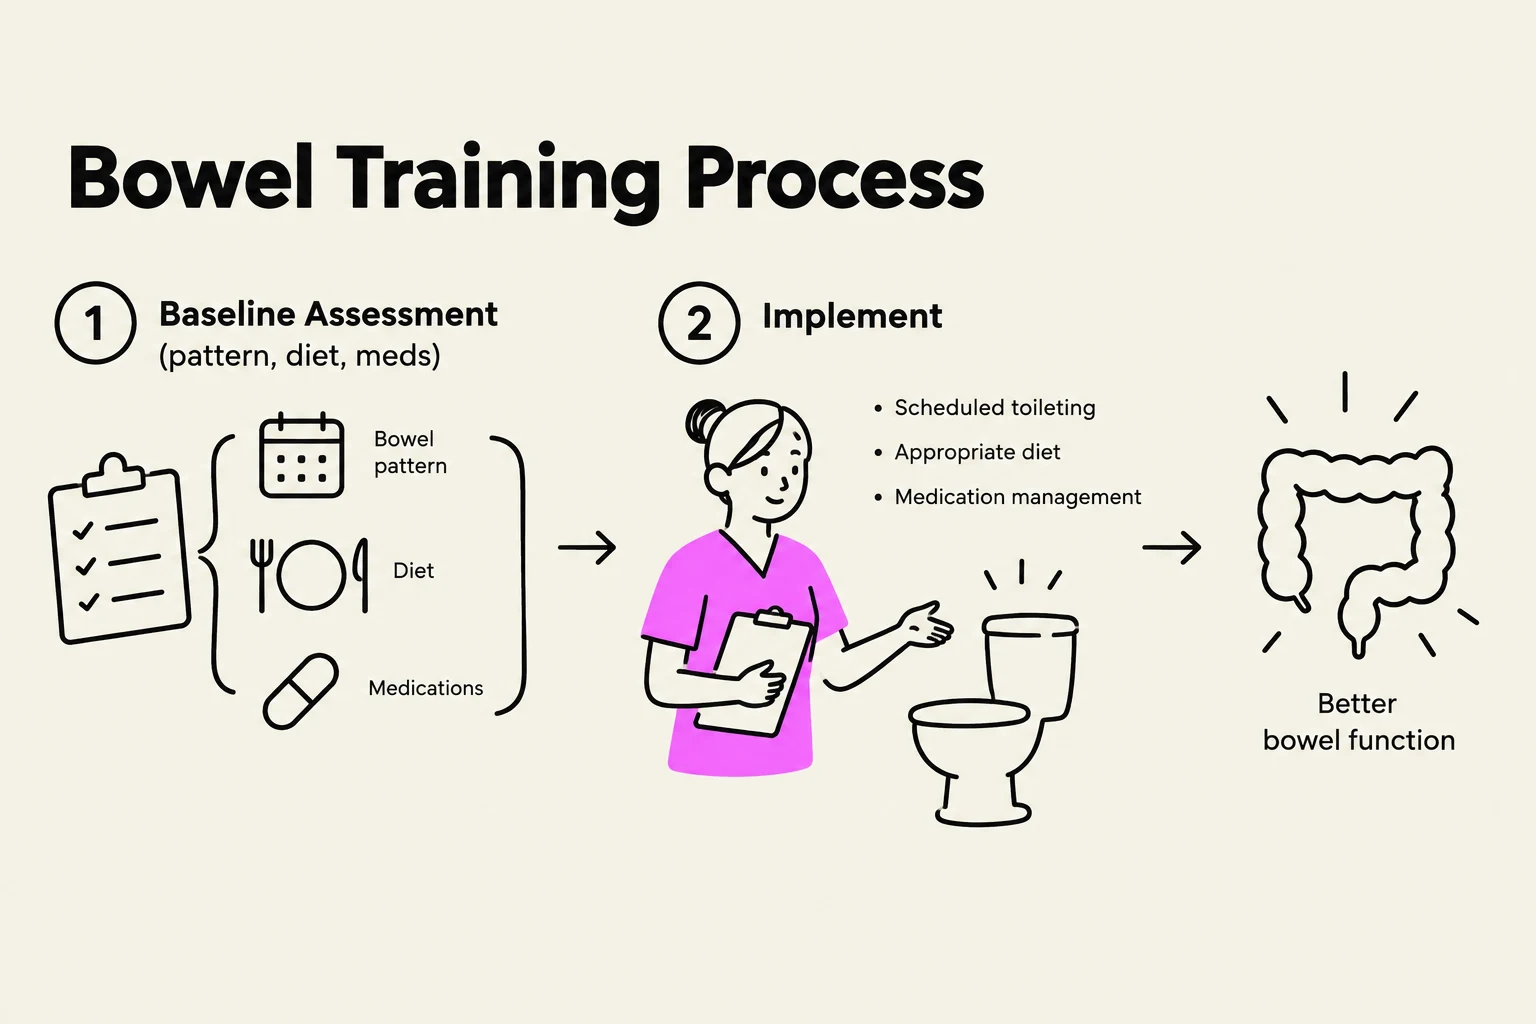
This diagram illustrates the Bowel Training Process, which involves a baseline assessment of bowel patterns, diet, and medications, followed by implementation of scheduled toileting, appropriate diet, and medication management to achieve better bowel function.
Psychosocial Support and Self-Care Teaching
Bowel alterations often impact a patient's body image, leading to anxiety, embarrassment, or social withdrawal. Nursing care must address these psychological needs by using matter-of-fact language, protecting privacy, and involving the patient in their care at their own pace.
Patient Teaching Priorities
The ultimate goal of nursing care is to prepare the patient for independence. Teaching should include:
Self-Care Skills: Demonstrating how to empty and change the pouching system.
Emergency Preparedness: Preparing a kit with emergency supplies.
Red Flags: Teaching the patient when to call the provider, such as sudden changes in stoma color, no output accompanied by pain/distention, or signs of dehydration.
Red Flags: When to Escalate Care
Nurses must use clinical judgment to recognize when a patient's condition requires immediate provider notification.
Symptom
Potential Concern
No stool/gas + severe pain + distention
Suspected bowel obstruction
Dusky, black, or pale stoma
Compromised blood supply
Bloody or black/tarry stool
Gastrointestinal bleeding
Fever + severe abdominal pain
Infection or perforation
Tachycardia + low urine output
Severe dehydration
Exam Tip: Vagal Response
When performing manual disimpaction or administering certain enemas, be alert for a vagal response. This can cause a sudden decline in heart rate (bradycardia), dizziness, or diaphoresis. Always check the patient's pulse if they have cardiac disease.
This diagram illustrates red flags for bowel elimination, categorized by system. It details concerning color changes in a stoma and signs of gastrointestinal obstruction, such as lack of stool or gas, abdominal distention, nausea, vomiting, and pain.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.