A comprehensive guide to nursing interventions throughout the stages of labor and delivery, including initial assessments, labor progress evaluation, delivery assistance, newborn care, and postpartum recovery.
Nursing care during the intrapartum period is a profound responsibility. For the patient and their support system, the labor and birth process is a life-altering event; for the nurse, it is a privilege to provide the clinical expertise and emotional support necessary to ensure the best possible outcomes. Effective nursing care requires a continuous cycle of assessment, intervention, and evaluation, focusing on both the physiological stability of the mother and the well-being of the newborn.
Initial Assessment and Preparation
Before labor progresses, the nurse must establish a baseline by reviewing the patient's prenatal records and gathering a comprehensive health history. Key data points include the patient's obstetrical history, often documented using the GTPAL system, and the identification of high-risk factors such as diabetes, multiples, or placenta previa.
Fetal Heart Rate (FHR): Ensuring the FHR remains within the normal range of 110–160 beats/minute.
Psychosocial Status: Assessing the patient's level of coping and preparation.
Clinical Alert: Always rule out complications like placenta previa before performing a vaginal examination.
Evaluating Labor Progress
As labor advances, nurses must evaluate several metrics to determine how the patient is progressing through the stages of labor.
Uterine Contractions and Cervical Status
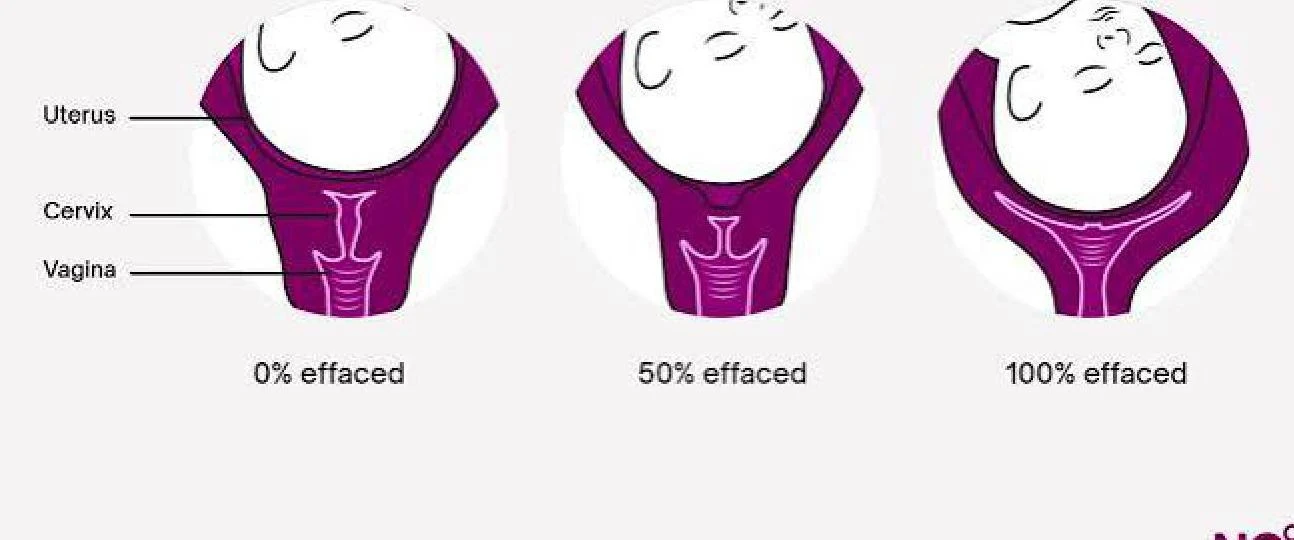
Contractions can be measured via palpation of the fundus or through electronic monitoring using a toco transducer or an IUPC (intrauterine pressure catheter). The nurse also assesses the cervix for dilation (the opening of the cervix, measured from the size of a blueberry to a rockmelon) and effacement (the thinning of the cervix).
Diagram illustrating cervical effacement during labor, showing 0%, 50%, and 100% effacement.
Fetal Station and Membrane Status
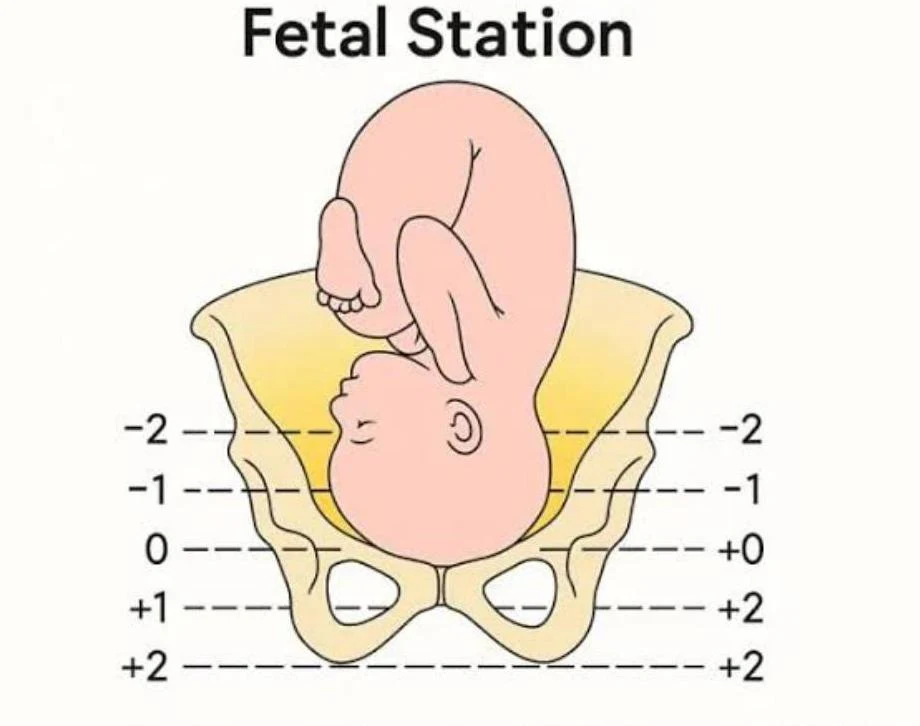
Fetal station refers to the position of the presenting part relative to the maternal pelvic bones. Additionally, the nurse must monitor the status of the membranes. If the membranes have ruptured (ROM), the nurse may use a nitrazine test (which changes color when exposed to amniotic fluid) or visual inspection to confirm.
Illustration showing fetal station, which measures the position of the fetus in the birth canal relative to the ischial spines.
Stages of Labor Interventions
The First and Second Stages
During the First Stage, the focus is on comfort and monitoring. Nurses encourage ambulation, offer hydration (clear liquids or ice chips), and support breathing techniques.
In the Second Stage, the patient begins the descent and birth of the baby. The nurse coaches pushing efforts, assists the provider with positioning, and monitors the FHR closely.
Assisting with Delivery
When the birth is imminent, the nurse assists the healthcare provider by cleansing the perineum and positioning the patient. During the actual delivery, the nurse may ask the mother to "pant" to control the delivery of the head, suction the infant's mouth and then nose, and assist in the delivery of the shoulders.
Umbilical Cord Management
Once the baby is born, the nurse manages the umbilical cord. Evidence-based practice supports delayed cord clamping to benefit the newborn. The nurse should check for two arteries and one vein, then clamp the cord with two clamps and cut between them.
Third Stage: Placental Delivery and Newborn Care
The Third Stage involves the delivery of the placenta and the immediate stabilization of the newborn.
Initial Newborn Care
The nurse's priority is to maintain the infant's respiration and warmth.
Skin-to-Skin Care: If the newborn is term, breathing/crying, and has good muscle tone, they should be placed immediately on the mother's chest for skin-to-skin contact.
Care at the Radiant Warmer: If the infant is not term, is not breathing, or has poor muscle tone, they must be moved to a radiant warmer for drying, stimulation, and potential positive pressure ventilation.
APGAR Scoring
Newborn stability is assessed using the APGAR score at 1 and 5 minutes.
Sign
0
1
2
Heart Rate
Absent
<100
≥100
Respiratory Effort
Absent
Slow/Irregular
Good Cry
Muscle Tone
Limp
Some Flexion
Active Motion
Reflex Irritability
No Response
Grimace
Cry
Color
All Blue
Hands & Feet Blue
All Pink
A healthy newborn typically exhibits an apical heart rate of 110–170 bpm, a respiratory rate of 30–60/min, and active muscle flexion.
Fourth Stage: Postpartum Recovery
The Fourth Stage focuses on maternal recovery and preventing hemorrhage.
Uterine and Perineal Assessment
The nurse must administer oxytocin as directed to promote uterine contractions and prevent uterine atony. Frequent assessments (every 15 minutes during the first hour) are required to monitor:
Fundus: Ensuring it is firm and midline.
Lochia: Assessing the amount and color of vaginal discharge.
Perineum: Checking for lacerations or episiotomies.
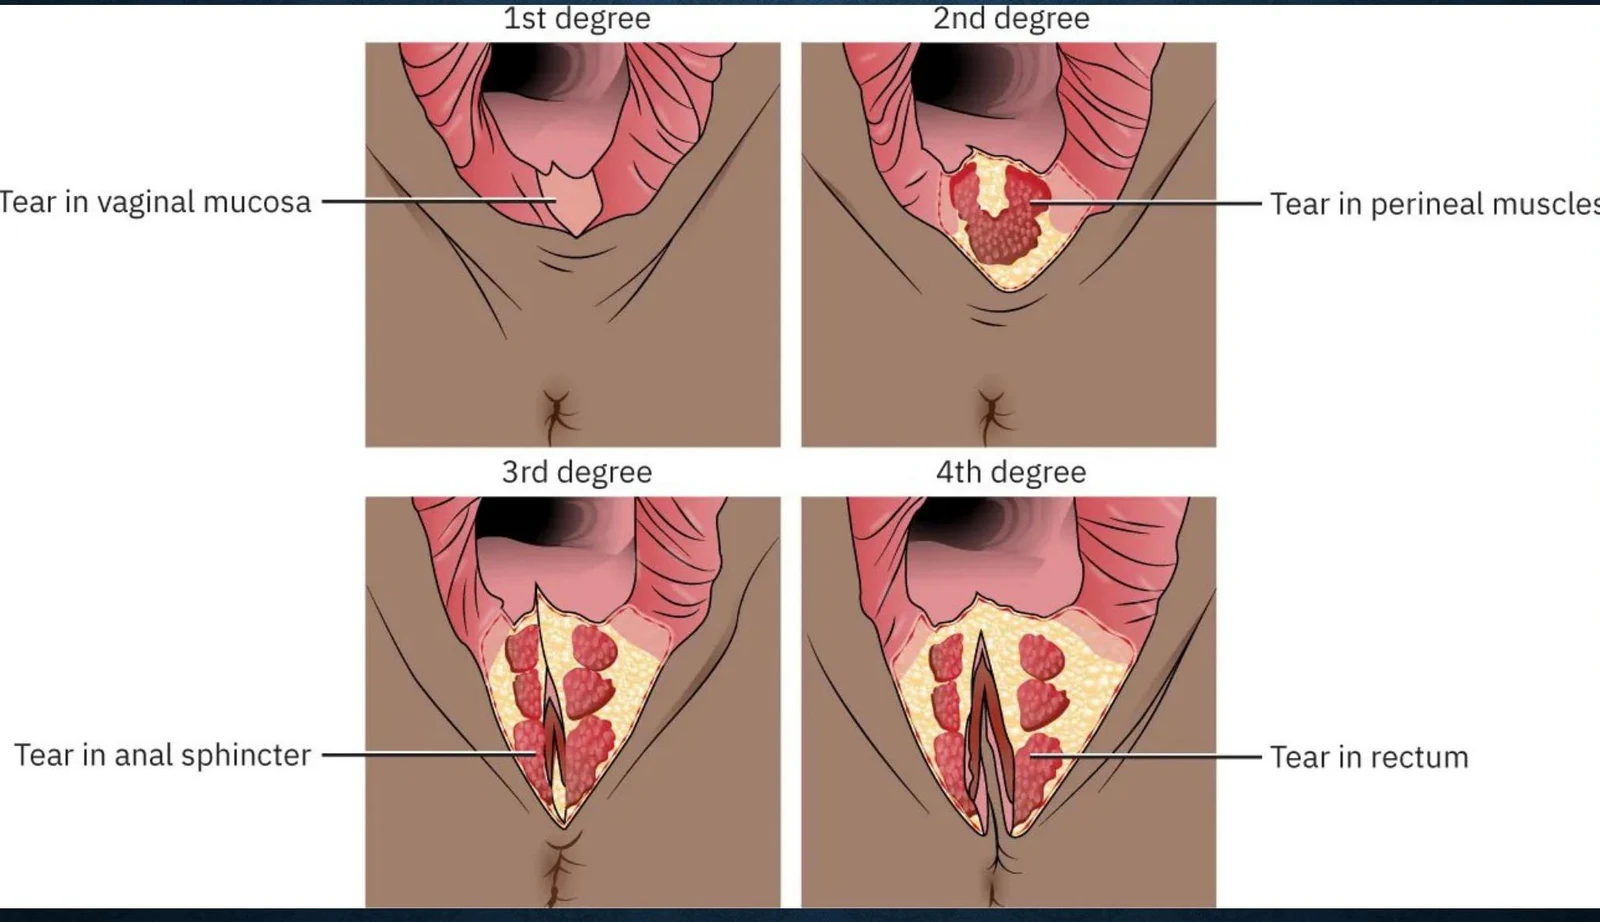
Perineal tears are categorized by severity:
1st Degree: Tear in the vaginal mucosa.
2nd Degree: Tear in the perineal muscles.
3rd Degree: Tear involving the anal sphincter.
4th Degree: Tear extending into the rectum.
Diagram illustrating the four degrees of perineal tears, indicating the extent of tissue damage from mild mucosal tears to tears involving the anal sphincter and rectum.
Special Considerations: Adolescent Nursing Care
When caring for adolescents, nurses must recognize that this population is at a higher risk for complications, including preeclampsia, anemia, and prematurity. Because of these risks, providing kind, supportive, and non-judgmental care is essential to managing their psychological coping and physical safety.
Nursing Tip: For adolescent patients, focus on building rapport and providing culturally competent care to help manage the unique psychosocial stressors they may face.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.