A comprehensive guide to the physiological and psychosocial transitions newborns and parents experience after birth, covering essential clinical assessments, safety protocols, and developmental patterns for high-quality neonatal care.
The period immediately following birth is a time of profound physiological and psychosocial transition. For the newborn, this involves shifting from a life of placental dependence to independent respiratory and thermoregulatory function. For the parents, it marks the beginning of a complex journey of bonding, role attainment, and managing new responsibilities. This article provides a detailed overview of the critical clinical assessments, safety protocols, and developmental patterns essential for providing high-quality neonatal care.
Physiological Transition: Respiration and Thermoregulation
As a newborn is delivered, they must transition from receiving oxygen via the umbilical cord to breathing air. The stimulation of the head during delivery often triggers the first breath, but the full transition occurs once the cord is cut, signaling the body to rely entirely on pulmonary gas exchange. A critical component of this process is the presence of surfactant, which keeps the alveoli open; premature infants may lack sufficient surfactant and may require medical intervention, such as intubation, to receive it.
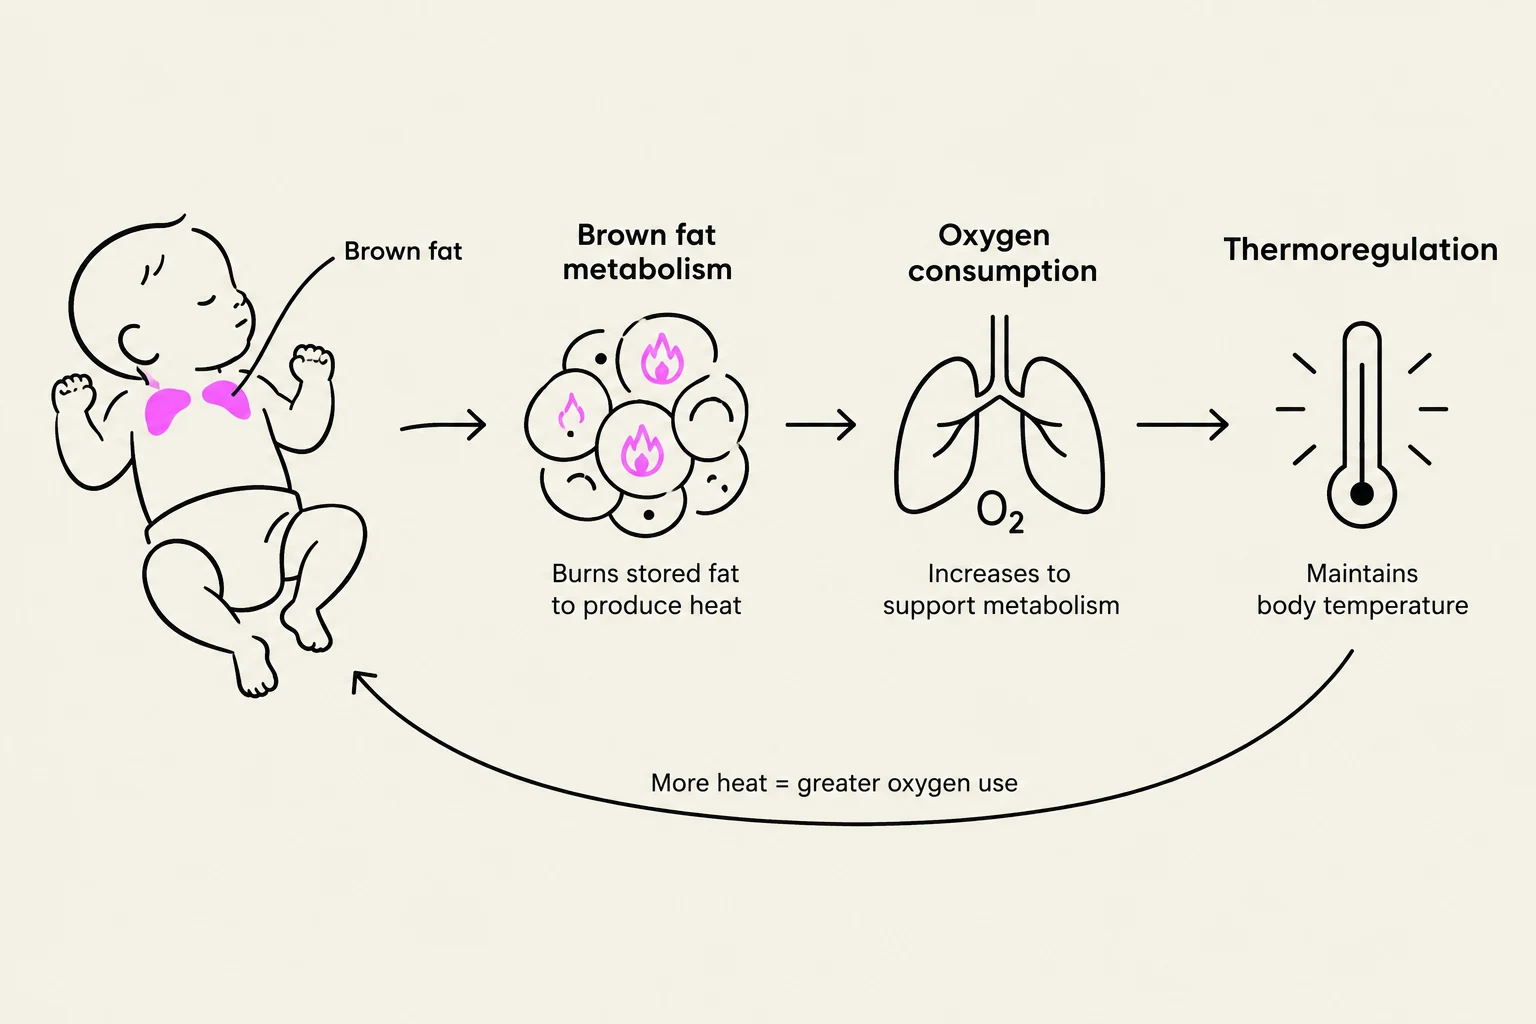
Simultaneously, the newborn must manage their body temperature. Unlike adults, newborns rely on "brown fat" for thermogenesis. When a baby becomes cold, they burn this brown fat for energy, which in turn increases their demand for oxygen.
Clinical Tip: When weighing a newborn, place a warm towel or blanket on the scale first. This prevents the baby from losing heat to the cold surface of the scale, helping to maintain thermoregulation and reducing crying.
This diagram illustrates the process of thermoregulation in infants, where brown fat metabolism increases oxygen consumption to maintain body temperature.
Clinical Assessment and Risk Factors
Nurses must perform systematic assessments to identify potential complications early. One significant concern is hyperbilirubinemia (jaundice), which occurs when the immature liver cannot efficiently excrete bilirubin.
Several factors significantly increase the risk for hemolytic disorders and hyperbilirubinemia:
Cephalohematoma: Often following a vacuum-assisted birth, this can lead to increased bilirubin levels.
Blood Type Incompatibility: For example, a mother with Type O blood and a newborn with Type A blood.
Rh Incompatibility: Identified by a maternal Rh-negative status combined with a positive indirect Coombs test.
Additionally, clinicians must monitor for congenital heart defects using pulse oximetry. A critical finding is a discrepancy in oxygen saturation between the right hand and the foot. If the difference is greater than $3%$, the infant has failed the screen and requires further investigation, such as an echocardiogram.
Nutrition: Breastfeeding and Feeding Patterns
Breastfeeding is highly recommended for the first six months of life because breast milk provides essential immunoglobulins and helps establish a healthy microbiome. Beyond nutrition, the immunological properties of breast milk change based on the mother's environment, allowing the infant to receive antibodies tailored to potential pathogens.
Effective breastfeeding requires a good "latch." If a mother experiences significant pain or if the baby is not satisfied after feeds, a tongue-tie or lip-tie may be present.
Feeding follows specific patterns in the early weeks:
Frequency: Newborns typically feed every 2 to 4 hours.
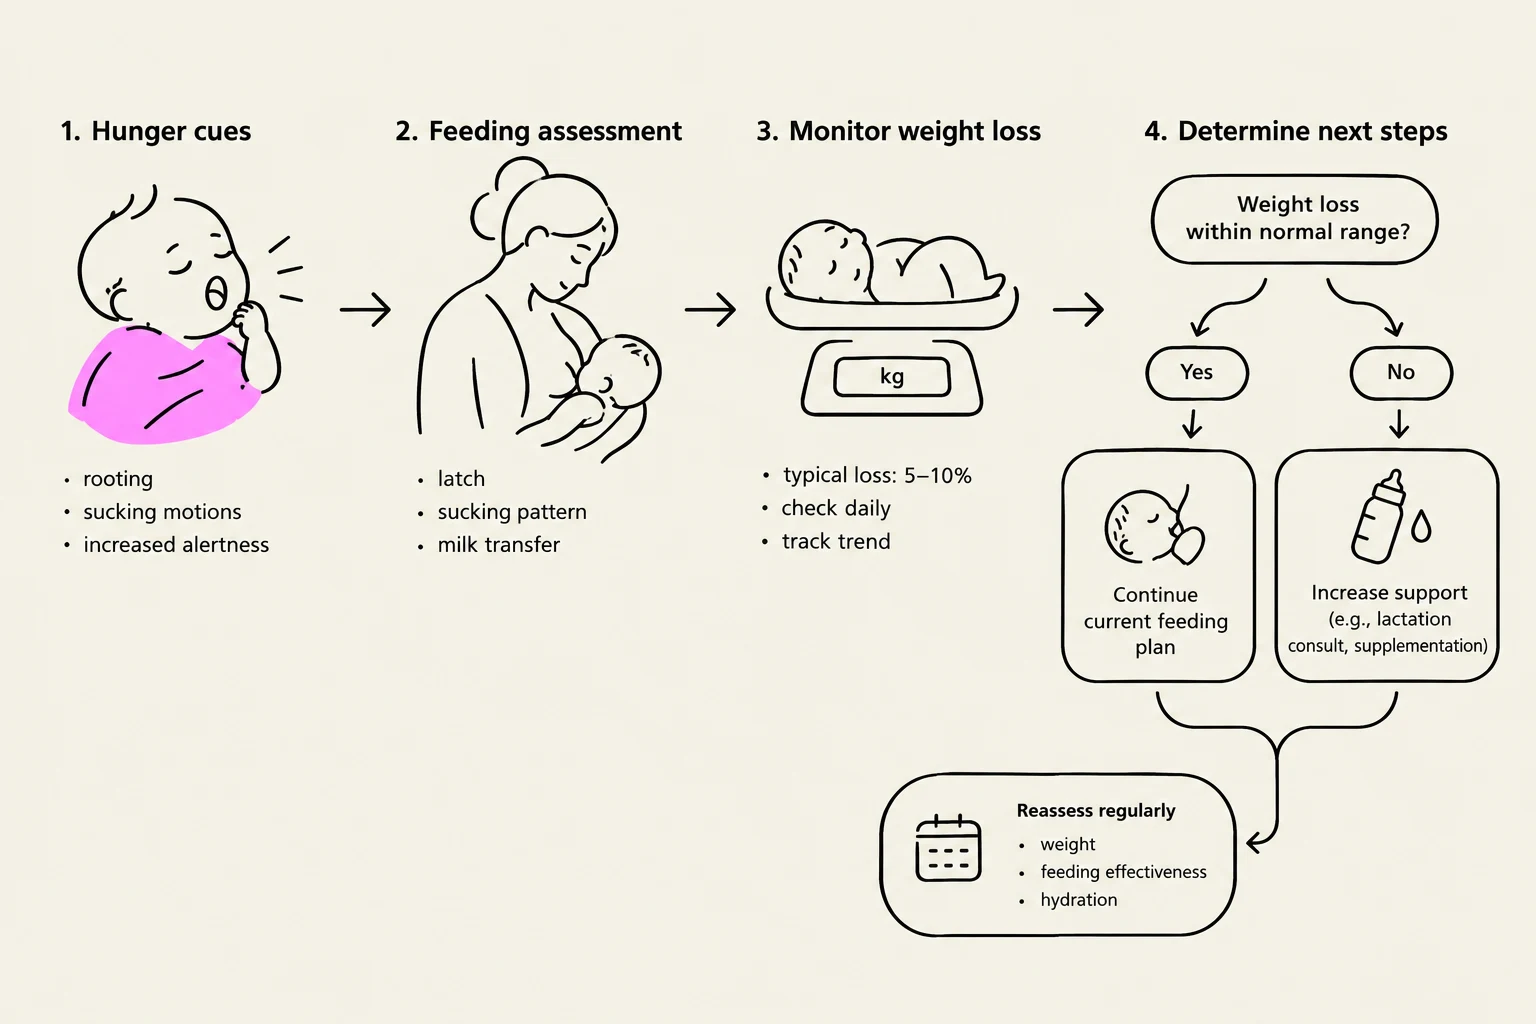
Weight Monitoring: It is normal for a baby to lose up to $10%$ of their birth weight within the first 24 to 48 hours. However, if weight loss exceeds $10%$, "weighted feeds" (weighing the baby before and after eating) are necessary to ensure adequate intake.
Cluster Feeding: Parents may notice periods where the baby wants to feed almost continuously; this is often "cluster feeding," which helps stimulate milk production.
This diagram illustrates the process of assessing infant feeding, starting with recognizing hunger cues, evaluating feeding effectiveness, monitoring weight loss, and determining appropriate next steps, including reassessment.
Safety, Infection Control, and Sleep
Protecting a newborn's developing immune system is a primary nursing priority.
Infection Control and Identification
Hand Hygiene: Strict adherence to handwashing is mandatory for all caregivers.
Vaccination: Caregivers should be up to date on vaccinations like RSV and Flu to prevent transmission to the infant.
Identification: To prevent errors during transport, newborns must wear two matching identification bands (one on the wrist and one on the ankle).
Safe Sleep Practices
To reduce the risk of Sudden Unexpected Infant Death (SUID), caregivers must adhere to strict sleep environments:
Position: Always place the baby on their back on a firm, flat surface.
Environment: The crib should be free of pillows, blankets, stuffed animals, or bumper pads.
Room Sharing: Room sharing with parents is recommended for at least 6 months, but bed sharing is strongly discouraged.
Psychosocial Support and Transition
The transition to parenthood affects the entire family unit. While "postpartum blues" are common, nurses must monitor more closely for postpartum depression and anxiety, which can impact the parent's ability to bond and care for the infant.
Bonding is facilitated through skin-to-skin contact, eye contact, and vocalization. Furthermore, as siblings adjust to a new family member, providing anticipatory guidance can help mitigate jealousy and facilitate a smoother transition for the whole household.
Exam Tip: When assessing a newborn's neurological status, remember that muscle tone should be appropriate for gestational age. A premature infant will naturally exhibit less muscle tone than a full-term infant.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.