What exactly is a "health system"? While many people equate a health system solely with hospitals and doctors, the definition is much broader. According to the World Health Organization (WHO), a health system comprises all activities intended to promote, restore, or maintain health. This includes population and public health, research, health promotion, policy development, financing, and rehabilitation services.
A health system is not just a collection of buildings; it is a reflection of a society's soul. The way a nation organizes its healthcare reveals its underlying political, cultural, demographic, and economic values. It expresses a society's choice between prioritizing individual rights and personal choice versus prioritizing social responsibility and collective goods.
Distinguishing Financing from Delivery
One of the most common mistakes students make when analyzing health systems is conflating how care is paid for with who provides the care. To analyze any system accurately, you must separate these two distinct concepts:
Financing: This describes who pays for the services. This could be the government (via taxation), employers and employees (via insurance funds), or individuals (via out-of-pocket payments).
Delivery: This describes who provides and operates the care. This could be public hospitals owned by the state or private clinics owned by individuals or corporations.
Exam Tip: These two are not mutually exclusive. A service can be privately delivered but publicly funded. For example, a private surgical clinic might perform a surgery that is paid for entirely by the government, meaning the patient pays nothing out-of-pocket.
Public vs. Private and For-Profit vs. Not-for-Profit
The terms "public" and "private" can be applied to either financing or delivery, so always clarify which you are discussing. "Public" refers to anything under the direction of the government, while "private" refers to anything beyond government systems, such as the private market or individual families.
Similarly, when discussing the organizations that deliver care or manage insurance, we distinguish between for-profit and not-for-profit models:
For-profit: These organizations are structured to generate profit for shareholders.
Not-for-profit: These organizations do not distribute profits to owners. This category includes registered charities (such as the Red Cross or the Alberta Cancer Foundation), which benefit the community through fundraising, research, and patient support programs.
The Four Primary Models of Health Care Organization
While most modern nations use a complex mix of different models, scholars generally categorize health systems into four primary frameworks:
1. The Beveridge Model
Named after William Beveridge, this model is the basis for the United Kingdom’s National Health Service (NHS). In this model, the government owns and operates most health care services, and funding comes primarily from general taxation. Because the government is both the payer and the provider, there is usually little to no out-of-pocket cost for covered services.
Examples: United Kingdom, Spain, New Zealand, Cuba.
Trade-offs: While it provides broad access regardless of income, it can face challenges with long wait times, limited capacity, or restrictions on certain drugs and technologies due to strict government budgets.
2. The Bismarck Model
This is an insurance-based model that uses highly regulated, non-profit "sickness funds" to pay for care. Unlike the Beveridge model, the government is not necessarily the sole provider; in fact, private delivery is very common. Funding typically comes from mandatory employer and employee contributions.
Examples: Germany, Belgium, Japan, Switzerland.
Trade-offs: It offers broad coverage and relatively good access, but the fragmented provider system can make coordination and information-sharing difficult.
3. National Health Insurance (NHI)
The NHI model is a hybrid that combines elements of both Beveridge and Bismarck. In this system, the government acts as the sole payer for essential services (like hospital and physician care), but the delivery of those services is handled by private providers.
Examples: Canada, South Korea, Taiwan.
The Canadian Experience: In Canada, the government provides insurance for "medically necessary" services, but "non-essential" services like dental, vision, or certain prescription drugs are often covered by private insurance or out-of-pocket payments.
4. The Out-of-Pocket Model
Often described as "market-driven," this model relies on private individuals and families to pay for their own care. Both the payers and the providers are private and largely independent of the government.
Examples: United States, China.
Trade-offs: While this model can support high levels of investment, research, and innovation, it often results in significant inequalities in access.
Health System Performance and Measurement
How do we know if a system is actually "good"? Simply looking at how much a country spends is not enough. A high-performing system is measured by several key metrics defined by the World Health Organization (WHO):
Safe and effective: Avoiding harm and providing appropriate care.
Timely: Ensuring wait times do not negatively impact patient outcomes.
Equitable: Ensuring all citizens have fair access to needed services.
Integrated: Providing care that supports people throughout all phases of life.
Efficient: Minimizing waste and maximizing the impact of every dollar spent.
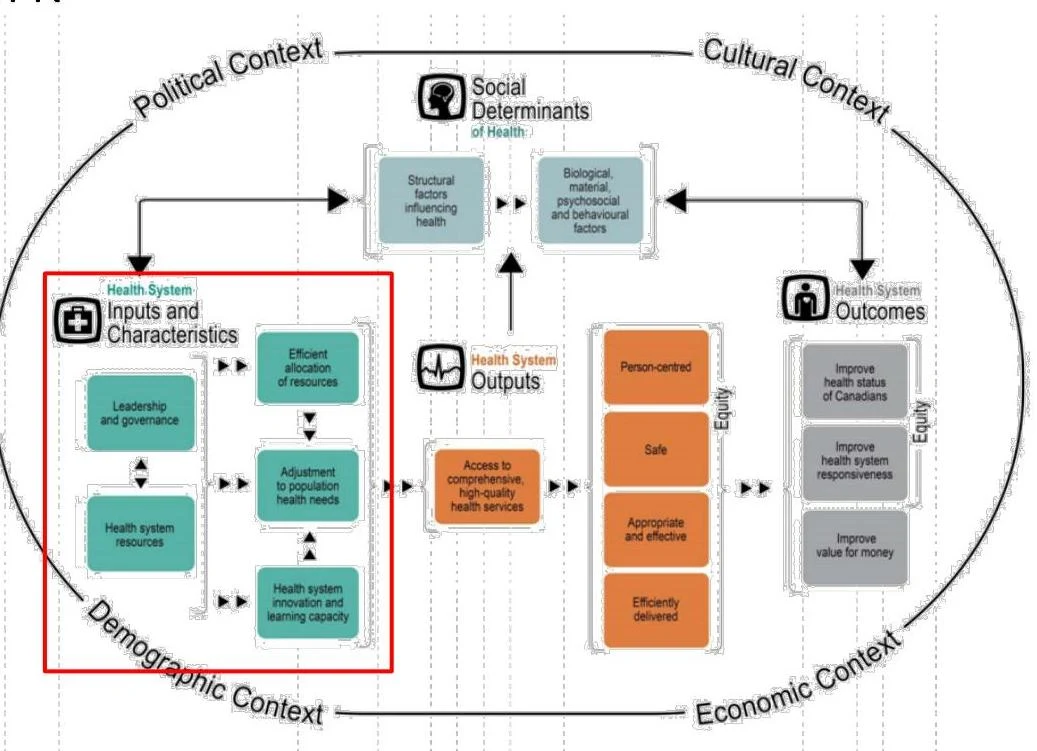
The relationship between inputs and outcomes is complex. A system's performance is driven by inputs—such as funding, staff, facilities, and technology.
A diagram illustrating the determinants of health and health system inputs, outputs, and outcomes within various contexts.
Crucial Concept: Higher spending does not guarantee better access, quality, or health outcomes. It is about how resources are organized and used (efficiency) rather than just the raw amount of money.
Spending vs. Outcomes: The Global Context
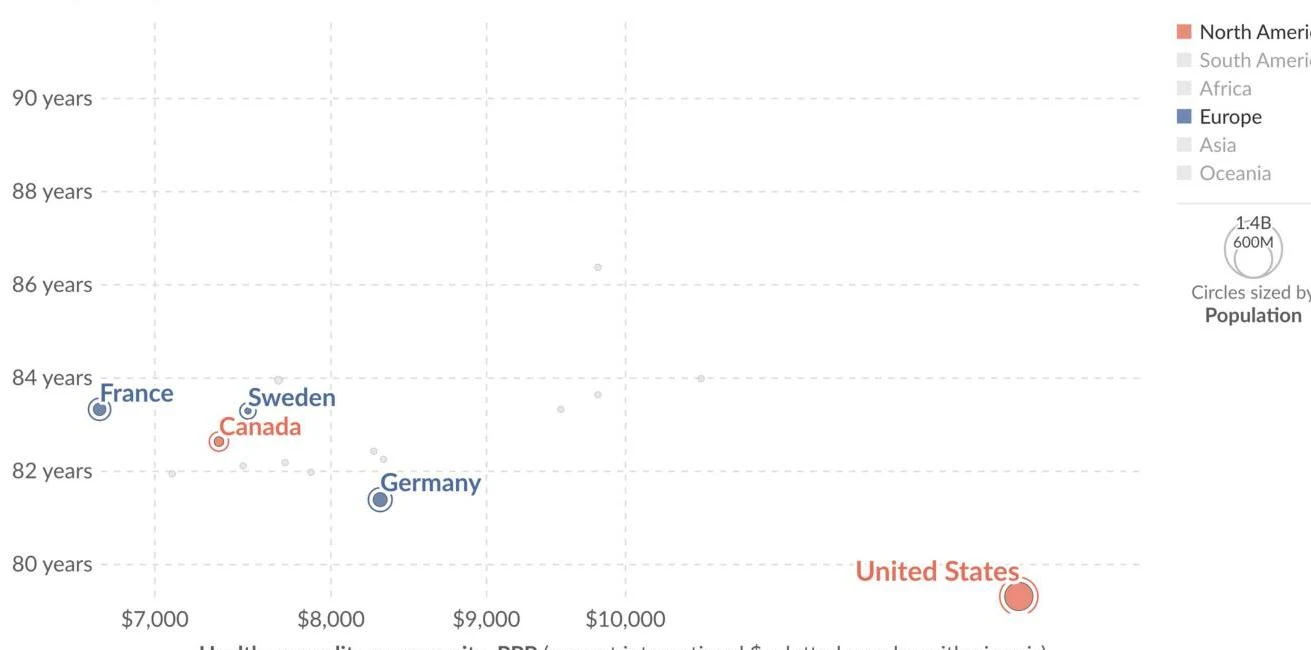
When looking at international data, the correlation between spending and health outcomes is not always linear. For example, while the United States spends substantially more per person than other OECD countries, it does not consistently achieve better population outcomes.
A scatter plot showing life expectancy in years on the y-axis against GDP per capita in international dollars on the x-axis, with circle size representing population.
As shown in the scatter plot above, while there is a general trend, the relationship between expenditure per capita and life expectancy varies significantly across nations. Canada, for instance, sits in the "middle of the pack" regarding spending, often achieving higher life expectancy than countries that spend more.
Case Study: The Canadian System
Canada's system is a prime example of how legislation and societal values shape organization. It is not a single, centrally operated system; rather, it consists of 10 provincial and 3 territorial systems that follow uniform federal guidelines.
Legislative Framework
The division of responsibilities is governed by the Constitution Act (1867), which defines federal and provincial jurisdictions. To ensure a standard level of care across the country, the Canada Health Act (1984) establishes five essential criteria for provincial insurance plans:
Public Administration: Plans must be run on a not-for-profit basis by a public authority.
Comprehensiveness: Must cover all medically necessary hospital and physician services.
Universality: All eligible residents must have access to insured services on uniform terms.
Portability: Coverage must continue when residents are temporarily outside their province or Canada.
Accessibility: Access cannot be obstructed by financial charges or discrimination.
The "Layers" of Canadian Coverage
Because the Canada Health Act only mandates coverage for "medically necessary" services, Canadian healthcare is often viewed in layers:
Layer One (Core Public): Hospitals, physicians, and diagnostics, funded by taxation.
Layer Two (Mixed): Services like prescription drugs, home care, and mental health care, which may use a combination of public taxation and private insurance.
Layer Three (Private): Services like dental care, vision care, and physiotherapy, which are primarily funded through private insurance or out-of-pocket payments.
In provinces like Alberta, the distinction between what is covered and what is not is clearly defined. For example, routine dental care, vision care for certain age groups, and prescription drugs provided outside of a hospital setting are generally not covered by the public plan.
Summary of Key Takeaways
To succeed in studying health systems, always approach a new topic with these three questions in mind:
Is this about financing or delivery? (Who pays vs. who provides)
Is this about public or private? (Government direction vs. everything else)
Is this about for-profit or not-for-profit? (Existence of shareholders)
Ultimately, no single model is perfect. Every system involves trade-offs between coverage, cost, quality, equity, and innovation. A nation's choice of model is a direct expression of its values regarding social justice, fairness, and the role of the state in the lives of its citizens.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.