This article reviews the classification of bacteria, including Gram stain characteristics and oxygen requirements, and explains the diverse mechanisms through which antibiotics exert their effects, such as cell wall impairment, protein synthesis inhibition, DNA/RNA synthesis inhibition, and folic acid synthesis inhibit
Understanding the relationship between bacterial structures and the drugs used to combat them is fundamental to clinical practice. To treat an infection effectively, a clinician must not only identify the pathogen but also understand how the antibiotic interacts with that specific organism. This article reviews the classification of bacteria and the diverse mechanisms through which antibiotics exert their effects.
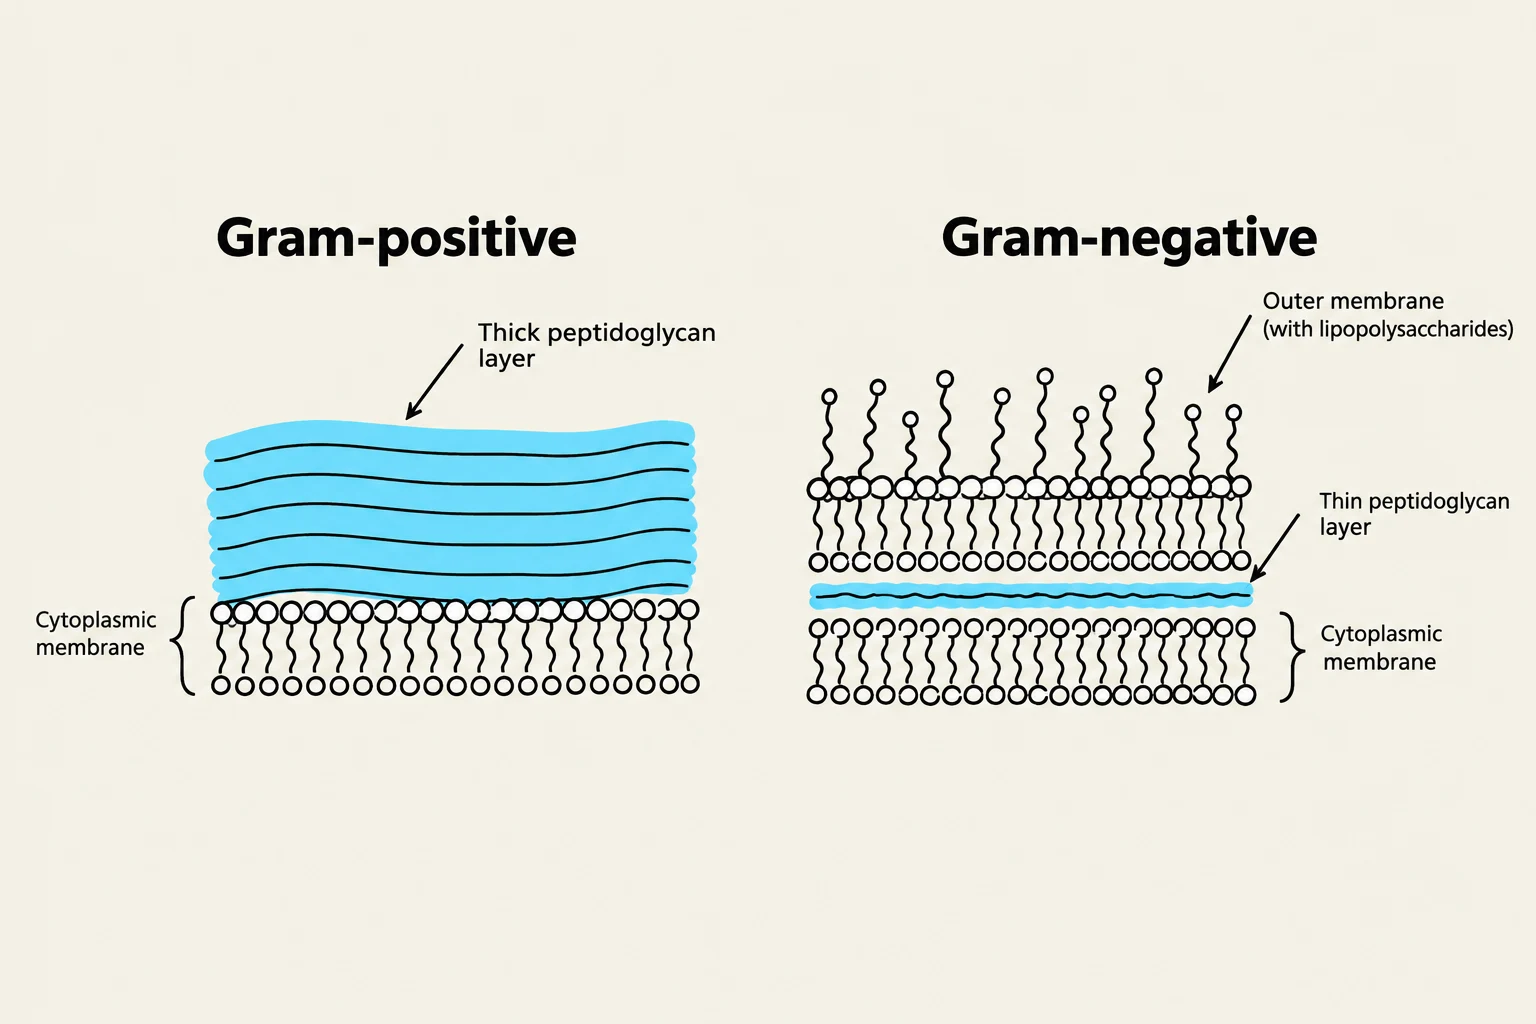
Diagram illustrating the structural differences between Gram-positive and Gram-negative bacteria, highlighting their cell wall composition.
Microbiology Fundamentals: Classifying Bacteria
Before selecting an antibiotic, it is essential to categorize bacteria based on their structure and their relationship with oxygen.
Gram Stain Characteristics
Bacteria are often classified by their reaction to Gram staining, which reveals differences in their cell wall architecture:
Gram-positive (G+): These bacteria lack an outer membrane and stain when exposed to dye. Common examples include Streptococcus groups, Staphylococcus aureus (including MRSA), and Enterococcus faecalis.
Gram-negative (G-): These bacteria possess an outer membrane and do not stain with the dye. They are often more pathogenic and include organisms like E. coli, Klebsiella, Salmonella, and Pseudomonas aeruginosa.
Oxygen Requirements
The environment in which a bacterium thrives dictates how easily it can be treated:
Aerobic bacteria: These survive in oxygen-rich areas. Because these areas typically have better circulation, drug distribution is often more efficient, making them relatively easier to treat.
Anaerobic bacteria: These thrive in oxygen-poor environments. These areas are often poorly circulated, leading to less effective drug distribution and making these infections more difficult to manage. Common anaerobes include Clostridium and Bacteroides fragilis.
Antibiotic Spectrum and Efficacy
Antibiotics are categorized by the range of bacteria they can inhibit, a concept known as "spectrum."
Narrow-spectrum antibiotics: These target a limited number of bacterial types. They are ideal when the specific organism has already been identified via culture or is clinically predictable. Examples include 1st generation Cephalosporins (e.g., Keflex) and Aminoglycosides.
Broad-spectrum antibiotics: These target a wide variety of bacteria simultaneously. They are used when the organism is unknown or when multiple pathogens are suspected. Examples include 2nd through 4th generation Cephalosporins, Beta-lactam Penicillins (e.g., Augmentin), and Carbapenems.
Bactericidal vs. Bacteriostatic
Clinicians must also distinguish between how an antibiotic achieves its goal:
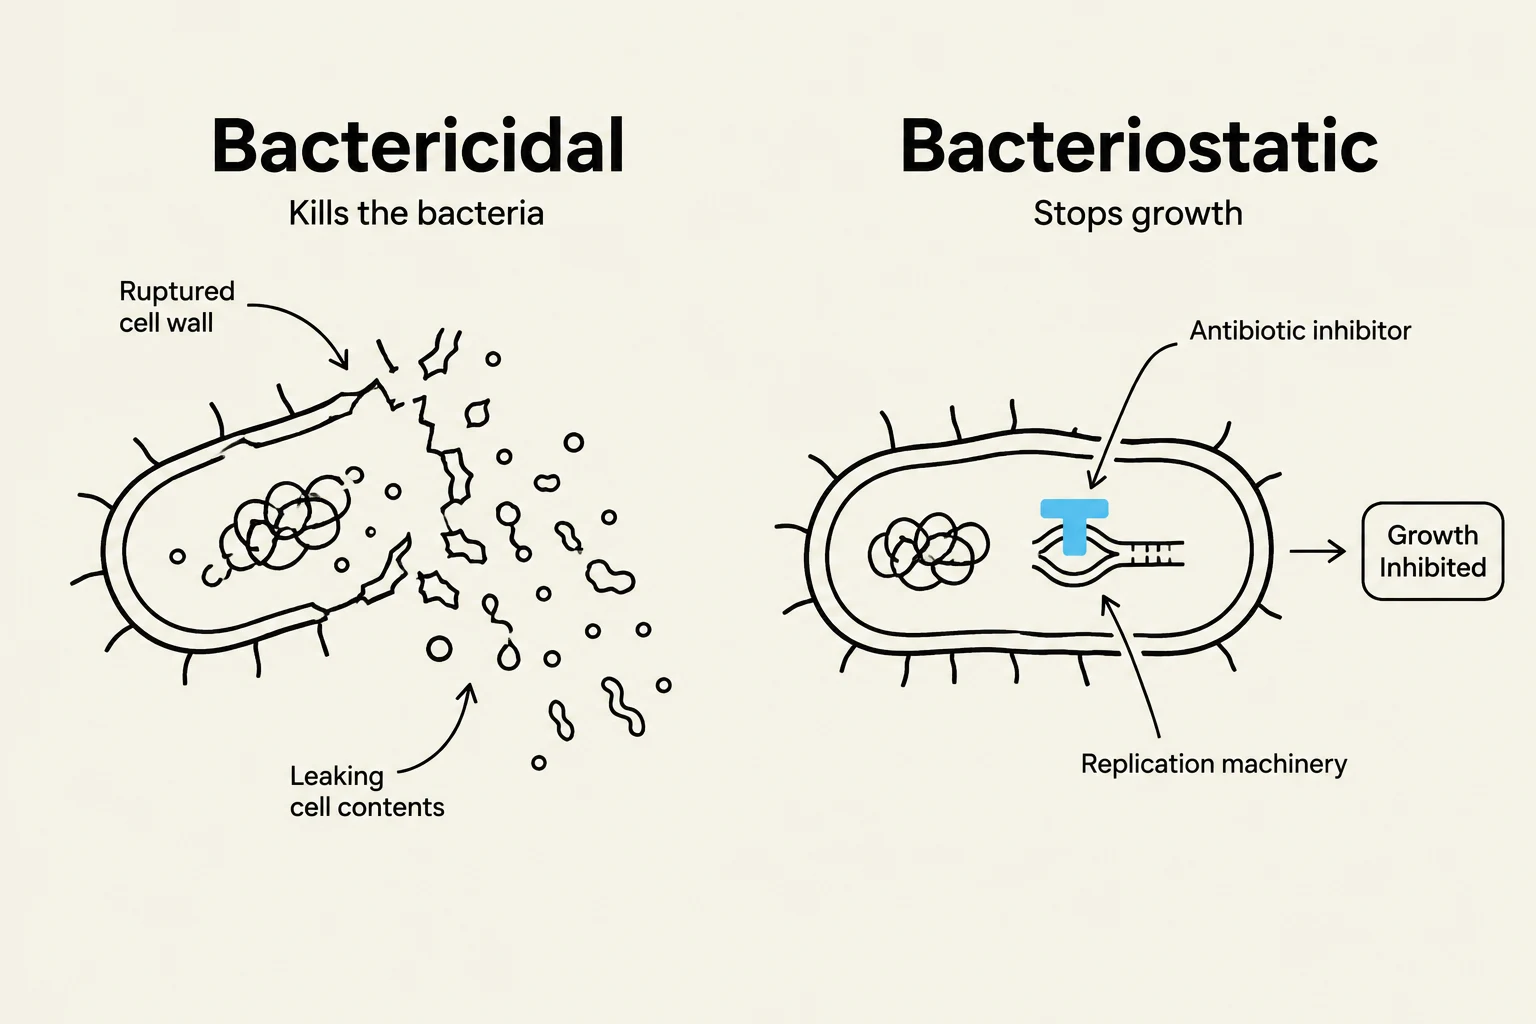
Bactericidal: These antibiotics cause direct bacterial cell death. This includes drugs that impair the cell wall, disrupt the cell membrane, inhibit DNA/RNA synthesis, or inhibit protein synthesis (specifically Aminoglycosides).
Bacteriostatic: These drugs slow the growth or replication of bacteria without killing them immediately. This allows the host's own immune system to eventually eradicate the remaining bacteria. Examples include Clindamycin, Erythromycin, Linezolid, and Tetracyclines.
Exam Tip: If a question asks which protein synthesis inhibitor is bactericidal, the answer is Aminoglycosides. Most other protein synthesis inhibitors are bacteriostatic.
Mechanisms of Action
This diagram illustrates the difference between bactericidal and bacteriostatic agents. Bactericidal agents kill bacteria by rupturing the cell wall and causing cell contents to leak. Bacteriostatic agents inhibit bacterial growth by interfering with replication machinery, as shown by an antibiotic inhibitor blocking the process.
Antibiotics work by attacking specific biological processes that are essential to bacterial survival.
1. Cell Wall Impairment
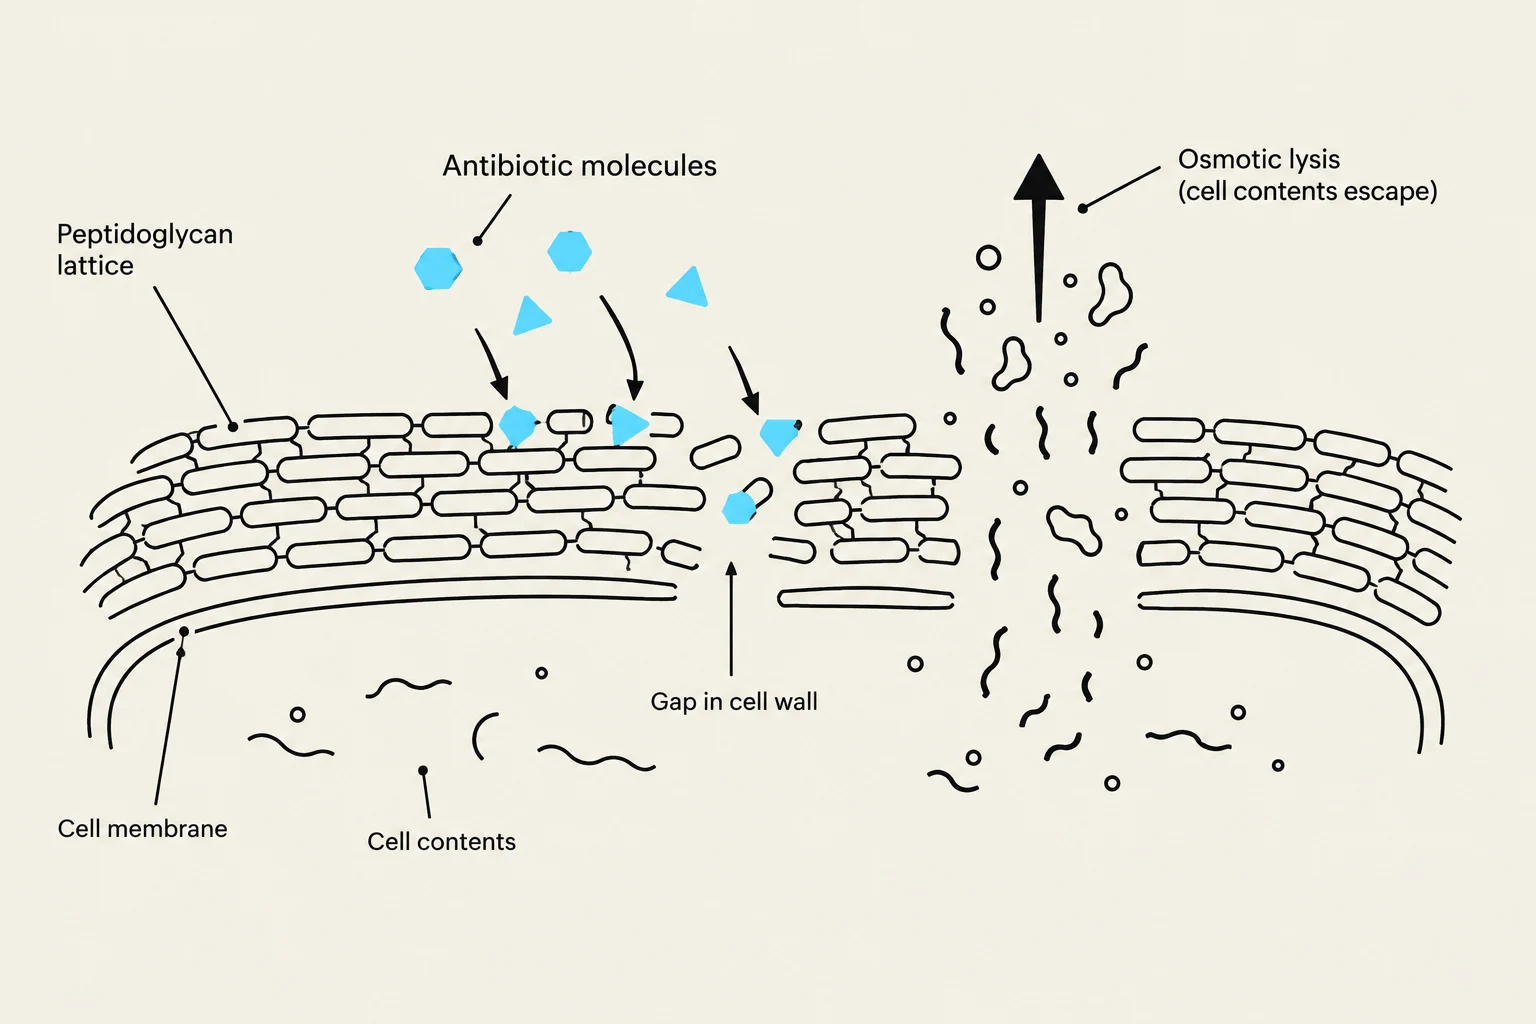
Diagram illustrating how antibiotic molecules disrupt the peptidoglycan lattice of a bacterial cell wall, leading to osmotic lysis as cell contents escape.
By creating holes in the cell wall that enlarge as the cell grows, these drugs eventually cause the bacteria to lyse and die.
Key Agents: Penicillins, Cephalosporins, Carbapenems, Vancomycin, and Monobactams.
Penicillins: These interfere with cell wall synthesis. Natural penicillins are narrow-spectrum and susceptible to penicillinase (an enzyme bacteria use to inactivate the drug), whereas newer generations are broader and more resistant to these enzymes.
Cephalosporins: These are beta-lactam drugs classified into "generations" based on their spectrum; as the generation increases, the spectrum generally becomes broader.
Carbapenems: The broadest spectrum available, used for multi-drug resistant or polymicrobial infections.
Glycopeptides (Vancomycin): Used for Gram-positive infections like MRSA and C. diff.
2. Protein Synthesis Inhibition
These drugs target the bacterial ribosome to prevent the production of essential proteins.
Aminoglycosides (e.g., Gentamicin): Bactericidal; used for aerobic Gram-negative infections. Note: They can cause irreversible ototoxicity and reversible nephrotoxicity.
Macrolides (e.g., Azithromycin): Bacteriostatic; effective against Gram-positive, Gram-negative, and atypical bacteria.
Tetracyclines (e.g., Doxycycline): Bacteriostatic and broad-spectrum. Warning: They should be avoided in children under 8 and pregnant women due to risks of tooth discoloration and skeletal growth depression.
3. DNA or RNA Synthesis Inhibition
These agents generate metabolites that are incorporated into DNA strands, making them prone to breakage.
Fluoroquinolones (e.g., Ciprofloxacin): Bactericidal and broad-spectrum. They are often used for respiratory or urinary tract infections but carry risks of tendon rupture and QTc prolongation.
Metronidazole: Bactericidal; specifically targets anaerobic bacteria and certain parasites by causing DNA strand breakage.
4. Folic Acid Synthesis Inhibition
Bacteria require folic acid to synthesize the nucleic acids that make up their DNA.
Sulfonamides (e.g., Trimethoprim-Sulfamethoxazole): These inhibit folic acid synthesis, preventing bacterial growth (bacteriostatic). A serious adverse effect to monitor is Stevens-Johnson Syndrome (SJS), a medical emergency characterized by a blistering rash.
Clinical Considerations and Stewardship
Pharmacokinetics and Interactions
Effective treatment requires considering how a drug moves through the body. For example, many newer penicillins are unstable in stomach acid and must be given parenterally (IV/IM). Additionally, many antibiotics are excreted by the kidneys, necessitating a check of renal function.
Common Drug Interactions:
Oral Contraceptives: Most antibiotics, including penicillins and tetracyclines, may decrease the effectiveness of oral contraceptives.
Anticoagulants: Many antibiotics can increase the risk of bleeding when taken with anticoagulants.
Specific Incompatibilities: Aminoglycosides and Penicillins can inactivate each other.
Antibiotic Stewardship
Drug resistance occurs through bacterial mutation or gene transfer. To combat this, healthcare providers must practice "Antibiotic Stewardship," which involves:
Obtaining cultures before starting antibiotics.
Avoiding the use of antibiotics for viral infections (e.g., common colds).
Ensuring patient compliance with the full prescribed regimen.
Using evidence-based prescribing to choose the most appropriate dose and spectrum.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.