Metabolic Bone Disorders: Osteoporosis, Rickets, Osteomalacia, and Scurvy
An overview of common metabolic bone disorders including osteoporosis, rickets, osteomalacia, and scurvy. This content details their distinct pathologies, causes, clinical manifestations, and treatment strategies, focusing on bone remodeling, mineralization, and collagen synthesis.
The skeletal system is a dynamic organ system that serves far more than just a structural purpose. Beyond providing a framework for movement and protecting soft tissues, bone acts as a vital reservoir for minerals like calcium and phosphate, maintains mineral homeostasis, and serves as the site for hematopoiesis. Because bone is constantly undergoing a process of remodeling—a cyclical balance between bone deposition and bone resorption—it is highly susceptible to metabolic, nutritional, and hormonal imbalances. When this delicate equilibrium is disrupted, various pathologies arise, ranging from the loss of bone density to the softening of the skeletal matrix.
The Mechanics of Bone Remodeling
To understand bone disorders, one must first understand the cellular "tug-of-war" that maintains bone health. Bone remodeling relies on the tightly coupled activity of two primary cell types: osteoblasts and osteoclasts.
Osteoclasts: These are large, multinucleated cells responsible for osteoclastic resorption. They release enzymes and acids that digest both the organic protein matrix and the inorganic mineral components of the bone, creating tunnel-like spaces in the osteon.
Osteoblasts: These are the "bone-building" cells. They synthesize and secrete collagen fibers to build the organic matrix and facilitate the deposition of calcium and other minerals to harden the bone.
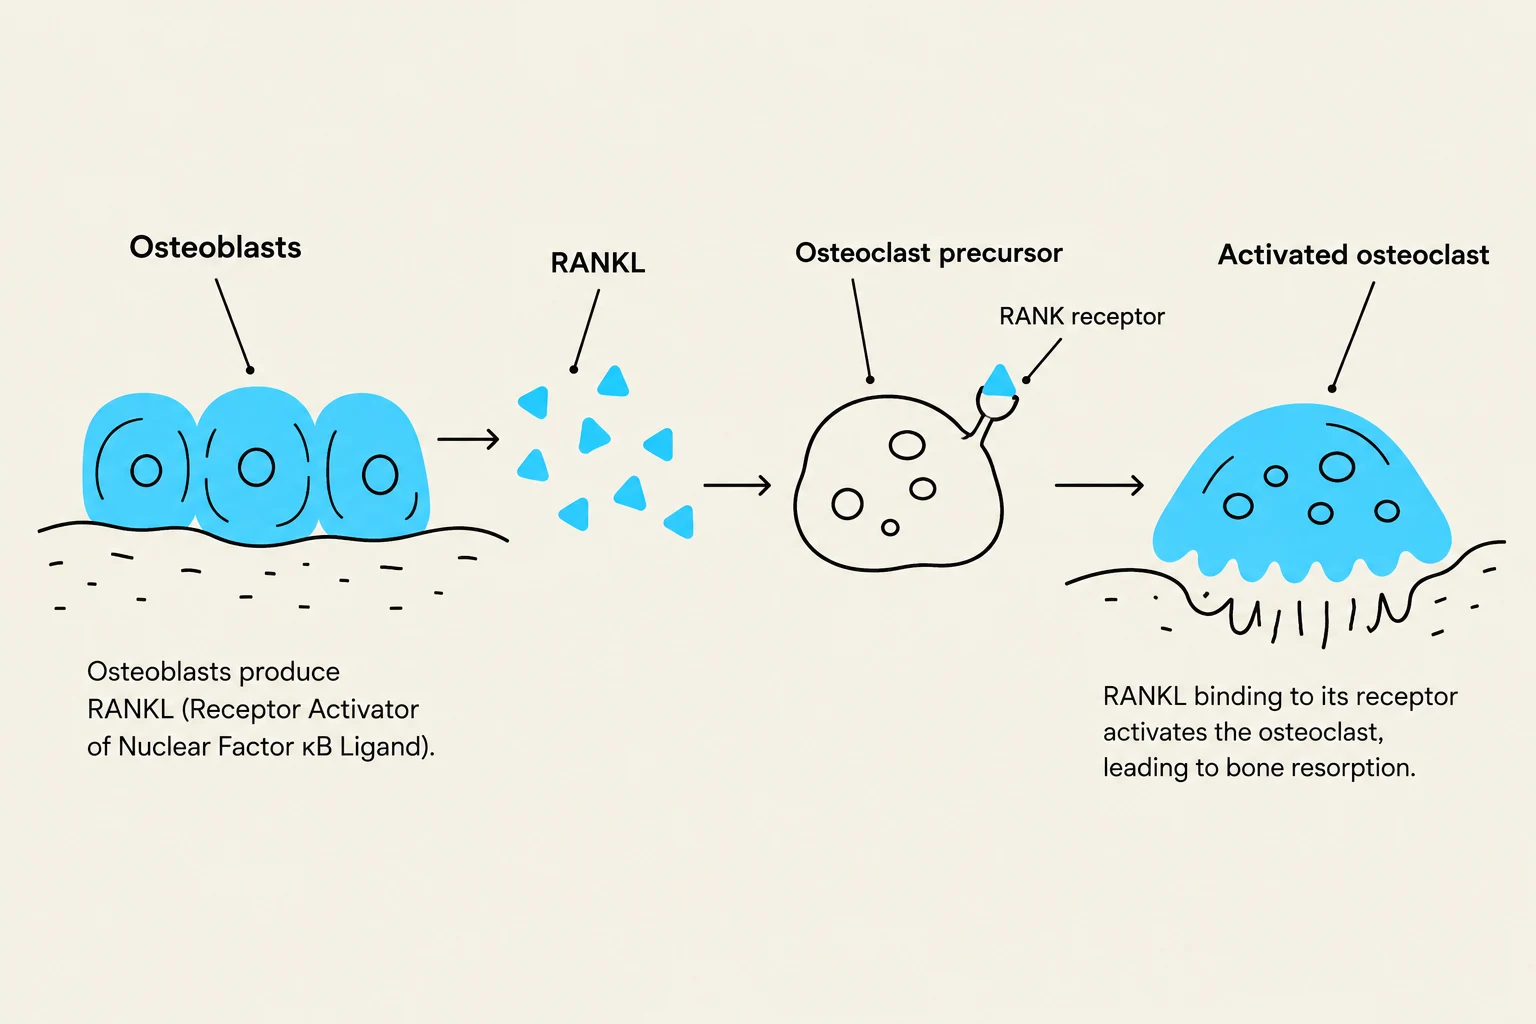
This process is regulated by complex signaling pathways. For instance, osteoblasts produce a protein called RANKL, which binds to RANK receptors on osteoclasts to activate them. Conversely, osteoblasts also produce Osteoprotegerin (OPG), a "decoy" receptor that binds to RANKL and prevents it from activating osteoclasts, thereby inhibiting bone resorption.
This diagram illustrates the process of osteoclast activation, where osteoblasts produce RANKL, which binds to RANK receptors on osteoclast precursors, leading to the activation of osteoclasts and subsequent bone resorption.
Exam Tip: Remember that bone health is a balance. If Resorption>Deposition, bone mass decreases. If Resorption<Deposition, bone mass increases.
Osteoporosis: Loss of Bone Mass
Osteoporosis is a metabolic bone disorder characterized by a decrease in bone tissue, resulting in brittle bones that are highly susceptible to fractures. Unlike some other bone diseases, the bone histology in osteoporosis is often normal, but the bone lacks structural integrity due to a reduction in both the bone matrix and mineralization.
Pathogenesis and Classification
The primary driver of osteoporosis is an imbalance where increased osteoclastic resorption outpaces osteoblastic bone formation. This can be categorized into two types:
Primary Osteoporosis: This includes age-related (senile) osteoporosis and post-menopausal osteoporosis. In post-menopausal women, the decrease in estrogen leads to decreased OPG production, which in turn increases osteoclast activation.
Secondary Osteoporosis: This is caused by external factors such as endocrine disorders (e.g., hyperparathyroidism), gastrointestinal disorders (e.g., malabsorption of Calcium or Vitamin D), or certain drugs like corticosteroids, which increase RANKL and decrease OPG.
Clinical Features and Diagnosis
Patients often present with bone pain, deformities, height loss (sometimes resulting in a "Dowager’s hump"), and fractures, particularly in the vertebrae, femoral neck, and wrist. Diagnosis is primarily achieved by measuring bone mineral density (BMD).
Treatment Strategies
Treatment focuses on both prevention and active intervention:
Prevention: Regular exercise and adequate intake of Calcium and Vitamin D.
Bone formation therapies: Sclerostin inhibitors (e.g., Romosozumab) and intermittent Parathyroid Hormone (PTH) analogues (e.g., teriparatide), which stimulate osteoblasts.
Rickets and Osteomalacia: Mineralization Defects
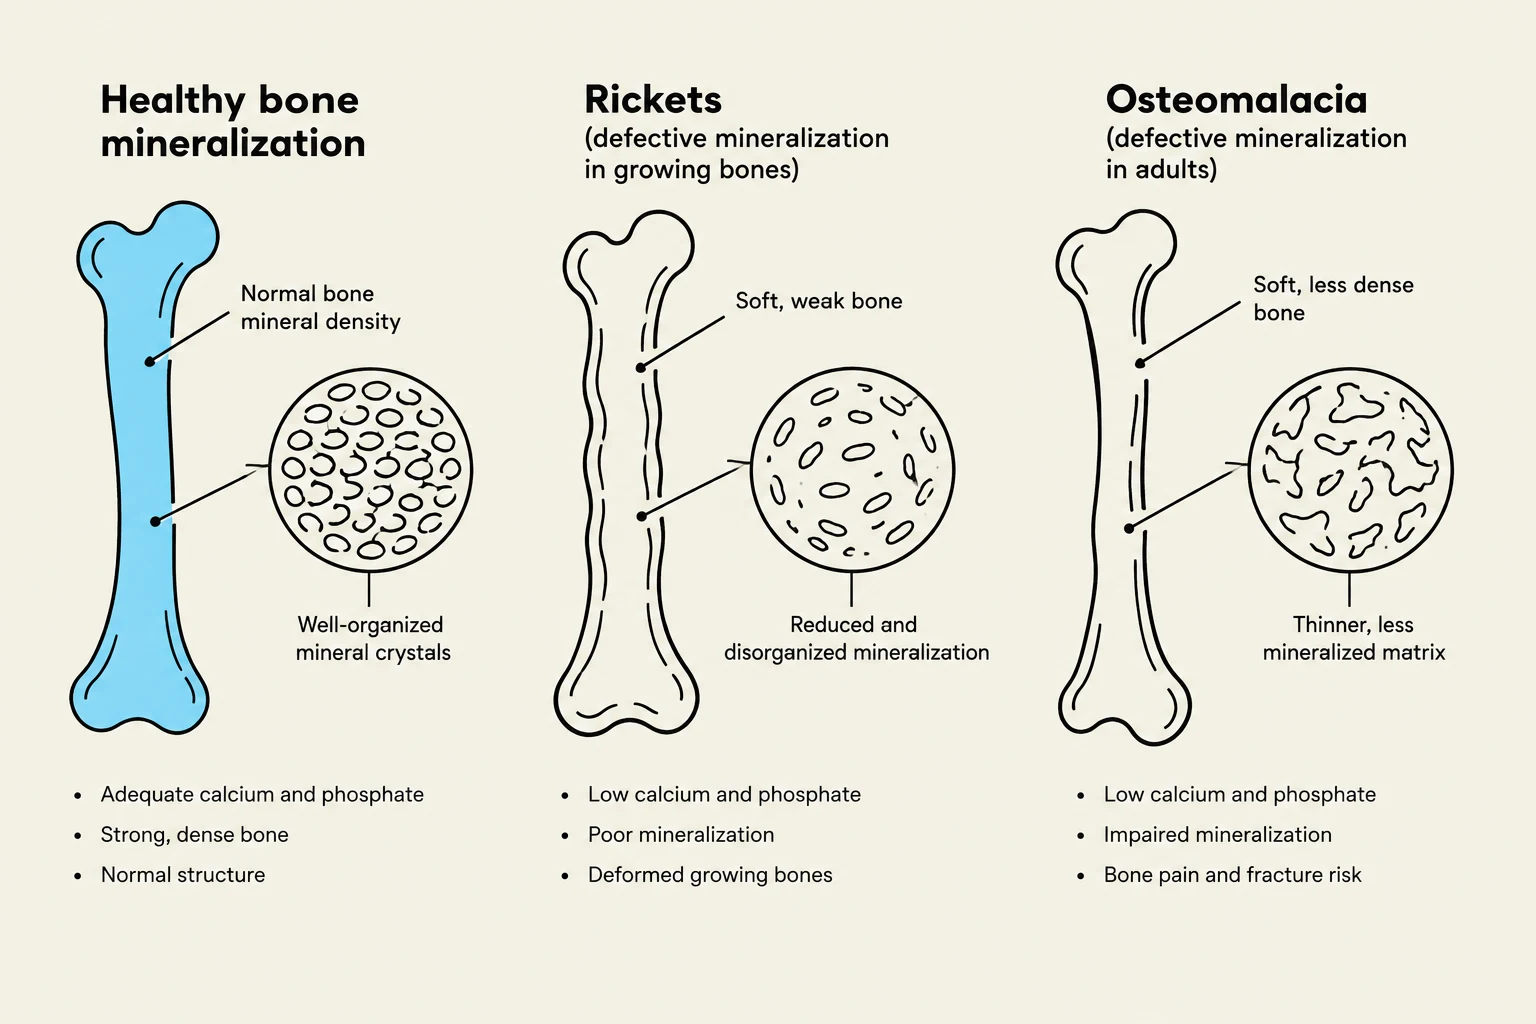
While osteoporosis involves a loss of total bone mass, Rickets and Osteomalacia involve the softening of bone due to inadequate mineralization of the organic matrix. This is most commonly caused by a deficiency in Vitamin D, calcium, or phosphate.
Rickets: This occurs in children and is characterized by impaired calcification of the cartilaginous epiphyseal discs. Clinical features include stunted growth, muscle weakness, and bowed legs.
Osteomalacia: This is the adult equivalent of rickets. It presents with bone pain, skeletal deformities, and pathologic fractures.
Common causes include insufficient UV light exposure (which aids Vitamin D synthesis), dietary deficiencies, or metabolic disorders that affect calcium/phosphate reabsorption.
This illustration compares healthy bone mineralization with rickets and osteomalacia, highlighting the differences in bone structure and mineral density due to calcium and phosphate deficiencies.
Scurvy: A Collagen Production Disorder
Scurvy is a distinct nutritional deficiency caused by a lack of Vitamin C. Unlike the previous conditions which focus on mineral salts, scurvy targets the organic component of the bone: collagen.
Vitamin C is a powerful antioxidant and a necessary cofactor for the production of normal collagen by fibroblasts. Without sufficient Vitamin C, the bone matrix cannot be formed correctly, leading to a loss of tensile strength.
Clinical Manifestations of Scurvy:
Defective bone matrix formation.
Weakened blood vessel walls, leading to hemorrhage, ecchymoses (bruising), and anemia.
Gum disease, including swelling, bleeding, and loosening of teeth.
Treatment is straightforward, involving Vitamin C supplementation and an improved diet rich in fresh fruits and vegetables.
Summary Table of Metabolic Bone Disorders
To help distinguish these conditions for clinical application, refer to the following summary:
Disorder
Primary Defect
Key Nutrient/Factor
Primary Clinical Feature
Osteoporosis
Loss of bone mass (Matrix + Mineral)
Estrogen, Calcium, Vit D
Fragile bones, fractures, height loss
Rickets
Poor mineralization (Childhood)
Vitamin D, Calcium, Phosphate
Bowed legs, stunted growth
Osteomalacia
Poor mineralization (Adult)
Vitamin D, Calcium, Phosphate
Bone pain, pathologic fractures
Scurvy
Defective collagen synthesis
Vitamin C
Bleeding gums, weak blood vessels
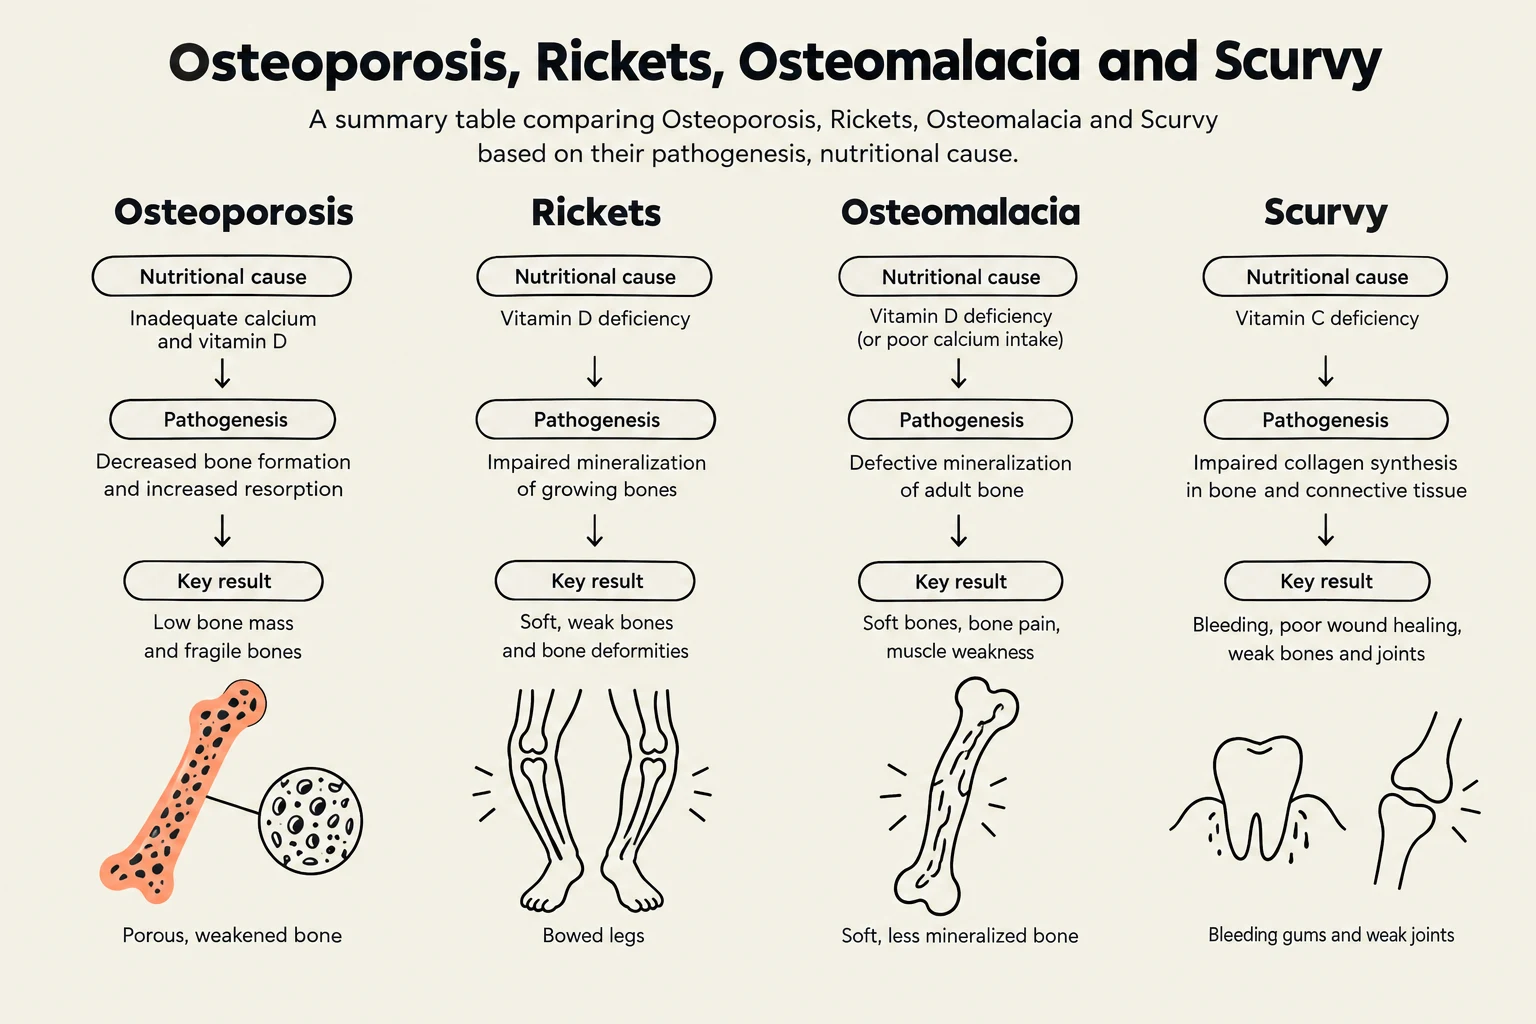
A comparative table outlining the nutritional causes, pathogenesis, and key results of Osteoporosis, Rickets, Osteomalacia, and Scurvy, with accompanying illustrations.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.