Mesenteric Arterial Duplex Ultrasound: Evaluation Criteria and Post-Treatment Monitoring
This guide details the diagnostic criteria for evaluating the superior mesenteric artery (SMA) and inferior mesenteric artery (IMA) using duplex ultrasound. It covers interpretation of velocity and waveform morphology, the postprandial meal challenge, and protocols for post-treatment follow-up and monitoring for in-ste
Mesenteric arterial duplex ultrasound is a critical diagnostic tool used to assess the patency and hemodynamics of the vessels supplying the gastrointestinal tract. Accurate interpretation requires a nuanced understanding of peak systolic velocities (PSV), waveform morphology, and the physiological changes that occur during digestion. This article outlines the diagnostic criteria for the superior mesenteric artery (SMA) and inferior mesenteric artery (IMA), as well as the standardized protocols for post-treatment follow-up.
Superior Mesenteric Artery (SMA) Interpretation
The SMA is a primary vessel for intestinal perfusion, and its evaluation focuses on identifying stenoses or occlusions that could lead to chronic mesenteric ischemia.
Velocity and Morphology
In a healthy, fasting state, the SMA typically exhibits a high-resistance waveform. The standard threshold for identifying significant stenosis is a Peak Systolic Velocity (PSV) of ≥275 cm/s.
When interpreting the waveform, clinicians must pay close attention to the diastolic component. While high resistance is normal during fasting, the presence of significant diastolic flow may indicate:
Proximal arterial stenosis.
The presence of a potential collateral circulation source.
A non-fasting state (the patient may have eaten recently).
Assessing Occlusion and Reconstitution
SMA reconstitution via collateral vessels following proximal occlusion.
If the SMA is completely occluded, the ultrasound technician should look for signs of "reconstitution." This occurs when collateral vessels (such as those from the celiac axis or IMA) bypass the occlusion to supply the distal portion of the SMA. In these instances, the presence of inflow collaterals is considered an abnormal finding, as it indicates the body is compensating for a major proximal blockage.
The Postprandial Meal Challenge
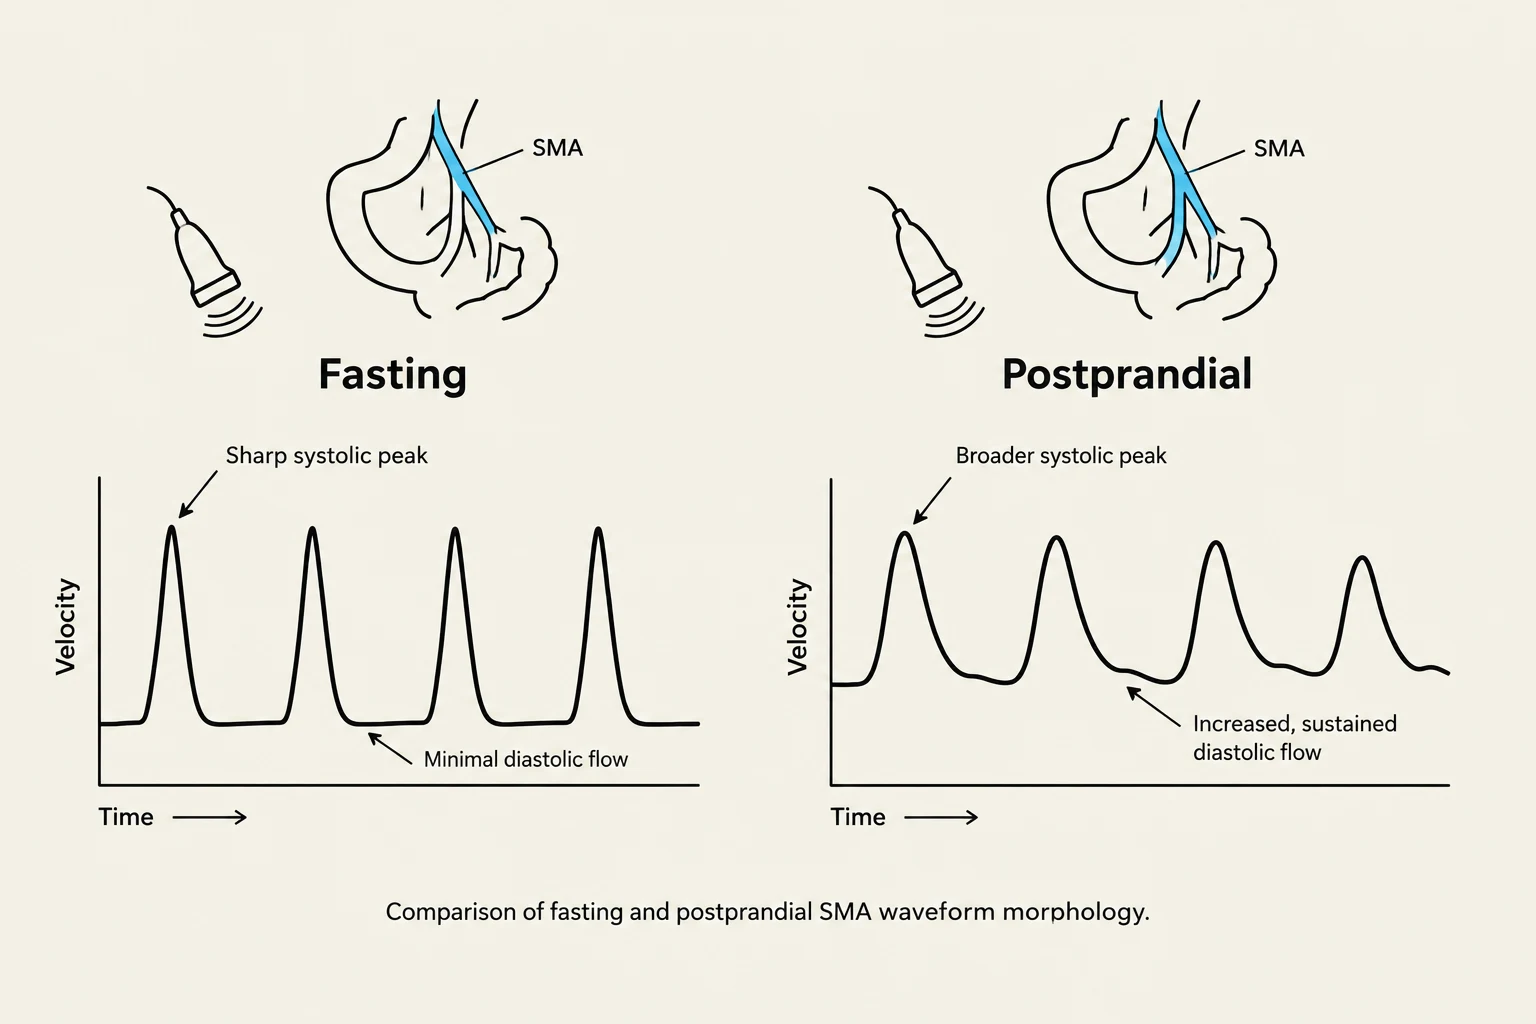
Comparison of fasting and postprandial SMA waveform morphology.
Because mesenteric blood flow is highly dynamic, a single measurement in a fasting state may not capture the full clinical picture. The "meal challenge" is a functional test used to observe the physiological response of the mesenteric vessels.
Under normal conditions, the mesenteric circulation should transition from a high-resistance waveform during fasting to a low-resistance waveform following a meal. This transition occurs because the digestive process requires increased blood flow to the gut. If the vessel fails to show this shift toward low resistance after eating, it may suggest significant underlying atherosclerotic disease or impaired perfusion capacity.
Exam Tip: If you encounter a low-resistance waveform in the SMA during a fasting exam, always check the patient's recent dietary history or look for proximal disease before concluding the vessel is normal.
Inferior Mesenteric Artery (IMA) Interpretation
The IMA is generally smaller and carries less volume than the SMA, but it serves as a vital collateral pathway.
Normal Velocities: The threshold for normal IMA flow is a PSV <200 cm/s.
Collateralization: A notably enlarged IMA is often a sign of compensatory collateralization, suggesting that the SMA or celiac artery may be compromised.
Morphology: Similar to the SMA, a low-resistance waveform in the IMA during fasting may suggest proximal disease or the presence of collateral sources.
Occlusion: If the IMA appears occluded, the sonographer should attempt to follow the vessel distally to document whether it reconstitutes via collateral flow.
Post-Treatment Follow-Up and Monitoring
Patients undergoing vascular interventions—such as endarterectomy, thromboembolectomy, angioplasty, stenting, reimplantation, or bypass grafting—require structured surveillance.
Surveillance Schedule
The Society for Vascular Surgery recommends a standardized follow-up schedule for patients who have undergone surgical or endovascular repair of the celiac, SMA, or IMA. Follow-up imaging should be performed at:
1 month
6 months
12 months
Evaluation Parameters
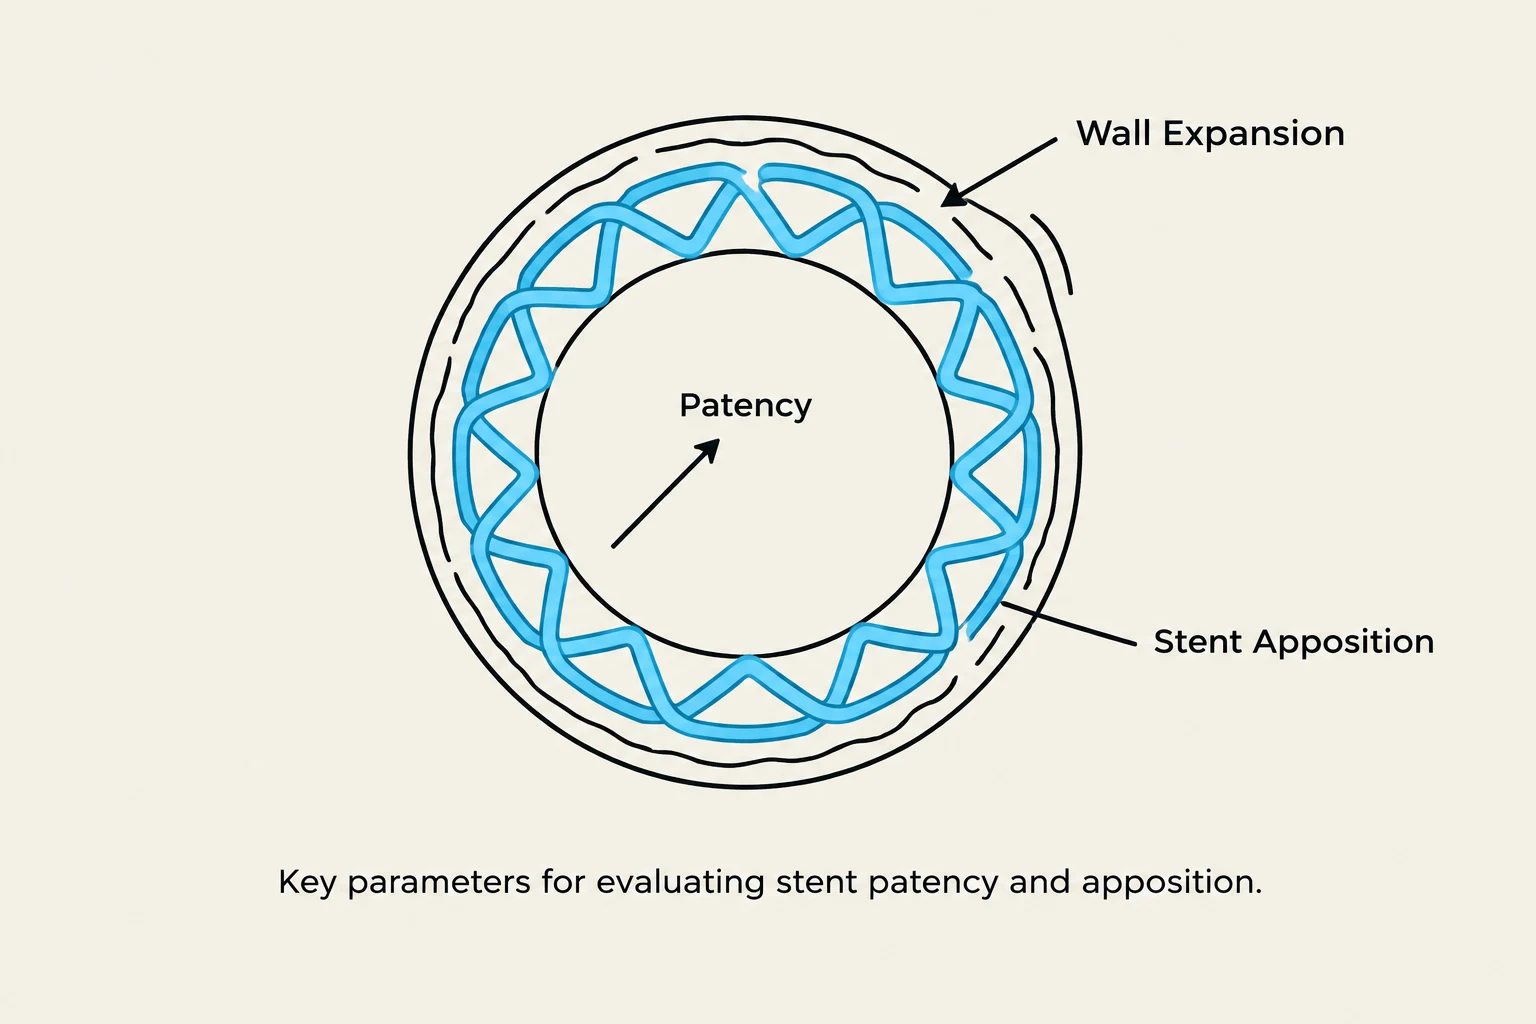
Diagram illustrating key parameters for evaluating stent patency and apposition, including wall expansion and stent apposition.
The criteria for a "successful" follow-up depend on the type of procedure performed:
For Stented Vessels:
Clinicians must evaluate three primary factors:
Patency: Is the lumen open?
Wall Expansion: Has the stent fully expanded against the vessel wall?
Stent Apposition: Is the stent in full contact with the vessel wall?
For Bypass Grafts:
Evaluation is more anatomical, requiring the clinician to assess:
The proximal anastomosis (where the graft meets the native artery).
The body of the graft itself.
The distal anastomosis (where the graft meets the target vessel).
All findings must be compared against the patient's baseline post-operative measurements.
Identifying In-Stent Re-stenosis
When a patient presents with recurrent symptoms of ischemia, or if ultrasound findings appear suspicious, contrast imaging may be necessary to confirm the diagnosis.
In-stent re-stenosis is primarily identified through significant increases in PSV. The diagnostic thresholds are as follows:
Vessel
Re-stenosis Threshold (PSV)
General/SMA
>370 cm/s
SMA Specific
>420 cm/s
IMA
No validated criteria currently exist
Clinical Note: Because there are no validated velocity criteria for in-stent re-stenosis in the IMA, clinicians must rely more heavily on waveform morphology and clinical symptoms in these cases.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.