Explores the human body's defense strategies against microorganisms, detailing the innate and adaptive immune responses, key leukocytes, immune proteins, and the role of dendritic cells. It also discusses the pathogenesis of Mycobacterium tuberculosis and challenges posed by fungi and drug-resistant strains.
The human body is constantly under siege by a diverse array of microorganisms, including bacteria, viruses, and fungi. To survive, we have evolved a sophisticated, multi-layered defense strategy designed to address every stage of microbial pathogenesis, from the initial colonization of tissues to the eventual destruction of human cells. This defense is not a single monolithic wall, but rather a coordinated effort between two primary systems: the rapid-response innate immune system and the highly specialized adaptive immune system.
The Innate Immune Response: The First Line of Defense
The innate immune response is the body's immediate reaction to a perceived threat. It is characterized by its rapid onset—occurring within hours of colonization—and its non-specific nature, meaning it recognizes general patterns common to many pathogens rather than specific individual strains.
Key Leukocytes in Innate Immunity
The primary "soldiers" of this system are leukocytes (white blood cells). When a pathogen enters the body, these cells are recruited to the site of infection through a process involving margination, rolling, firm adhesion, transmigration, and chemotaxis.
Key players include:
Neutrophils: The most abundant leukocyte, making up approximately 65% of the differential count.
Monocytes and Macrophages: Monocytes circulate in the blood, but once they enter tissues, they differentiate into macrophages. Macrophages are critical for phagocytosis, the process of engulfing and digesting microorganisms.
Eosinophils and Mast Cells: These cells play specialized roles in inflammatory responses.
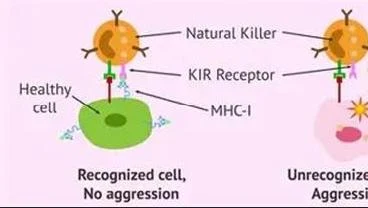
Natural Killer (NK) Cells: These cells provide a unique defense by interacting with healthy cells via KIR receptors and MHC-I to identify and eliminate compromised or infected cells.
Diagram illustrating the interaction between Natural Killer cells and target cells via KIR receptors and MHC-I molecules, differentiating between recognized (non-aggressive) and unrecognized (aggressive) cells.
Innate Proteins and Inflammation
Beyond cells, the innate system utilizes chemical tools. Cytokines (such as TNF-α and IL-6) act as signaling proteins to promote immune activity. Additionally, the complement system consists of a cascade of blood proteins that, when activated, can lead to the formation of a Membrane Attack Complex (MAC), which physically lyses (bursts) bacterial cells.
Exam Tip: Inflammation
Inflammation is an innate localized reaction triggered by pathogen colonization. Its purpose is to contain the spread of the pathogen to the portal of entry and promote its destruction through vascular, metabolic, and cellular changes.
The Bridge: Dendritic Cells
The transition from a general response to a targeted one requires communication. Dendritic cells act as the essential bridge between the innate and adaptive systems. They capture antigens from the site of infection and "traffic" them to the lymphatic organs (such as lymph nodes). By presenting these processed antigens to lymphocytes, dendritic cells initiate the highly specific adaptive attack.
The Adaptive Immune Response: Precision and Memory
While the innate response is fast, it lacks "memory." The adaptive immune response is a more specialized system that develops following the initial innate response. It is characterized by its ability to target specific pathogens and provide long-term immunity.
Cellular Drivers of Adaptive Immunity
The adaptive response relies on two main types of lymphocytes:
B Cells (B Lymphocytes): These cells are responsible for antibody-mediated responses. Once activated by antigens and T cell cytokines, they proliferate and produce antibodies (immunoglobulins) to neutralize pathogens.
T Cells (T Lymphocytes): These cells coordinate the overall immune response and directly target infected cells. They produce immune cytokines (like IFN-γ) that stimulate other cells, including macrophages.
Diagram illustrating the immune response to viral infection, showing T-cell activation and cytotoxic T-lymphocyte killing of infected cells.
Feature
Innate Immunity
Adaptive Immunity
Principal Cells
Macrophages, Neutrophils
T Lymphocytes, B Lymphocytes
Timing
Rapid (hours)
Peaks weeks to months
Specificity
Any pathogen (non-specific)
Only specific pathogens
Memory
No memory
Persistent memory over time
Clinical Application: The Case of Mycobacterium tuberculosis
To understand how these systems interact in a real-world disease, we can look at the pathogenesis of Mycobacterium tuberculosis (TB).
When TB bacilli are inhaled, they are initially engulfed by alveolar macrophages. In a successful defense, the macrophage kills the bacteria within a phagolysosome. However, M. tuberculosis has evolved virulence factors that allow it to inhibit phagolysosome fusion and replicate inside the macrophage, eventually killing the host cell.
Granuloma Formation and Latency
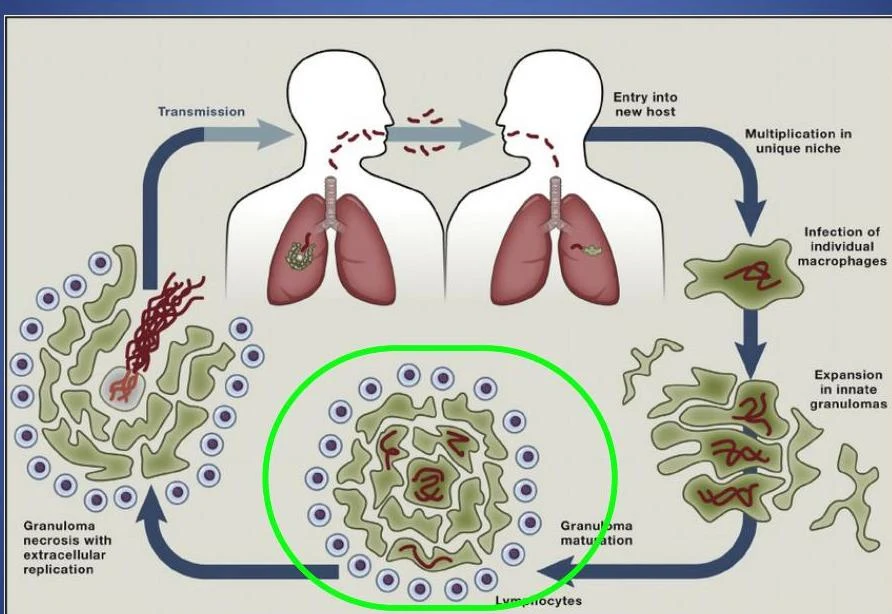
To prevent the spread of these escaped bacteria, the body forms a granuloma—an aggregation of macrophages, matrix, and additional immune cells designed to confine the pathogen.
Latent TB: The bacilli are inactive and contained within granulomas. The patient is typically asymptomatic and not infectious.
Active TB: The bacilli multiply, the granulomas may break down (forming cavitary lesions), and the patient becomes ill and infectious.
This diagram illustrates the transmission and progression of a granulomatous disease, likely tuberculosis, showing the entry into a new host, multiplication within macrophages, granuloma formation and maturation, and eventual necrosis with extracellular replication.
Pathogen Challenges: Fungi and Drug Resistance
The complexity of immunity is further highlighted by other pathogens. For example, Cryptococcus species are encapsulated fungi that pose a significant threat to immunocompromised hosts. Furthermore, the rise of Multidrug-Resistant TB (MDR-TB)—strains resistant to at least isoniazid and rifampin—demonstrates how pathogens can evade even our most advanced medical interventions.
Clinical Note: Testing for TB
The Tuberculin Skin Test (TST) measures the delayed-type hypersensitivity reaction to Purified Protein Derivative (PPD). A positive reaction indicates that the adaptive immune system has "remembered" the TB antigen.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.