Mechanisms of Drug Absorption and Administration Routes
Explores the physiological processes of drug absorption, including transcellular and paracellular pathways, passive diffusion, carrier-mediated transport, and vesicular transport. It also details factors affecting oral absorption and various alternative routes of administration.
When a patient takes medication, the journey from the point of administration to the bloodstream is a complex physiological process. This process is known as absorption. Understanding how drugs move across biological membranes is fundamental to pharmacology, as it determines how much of a drug actually reaches its target and how quickly it begins to work.
Absorption vs. Bioavailability
Before diving into the mechanics, it is crucial to distinguish between two often-confused terms: absorption and bioavailability.
Absorption is the physical process of a drug transferring from its site of administration into the systemic circulation (the bloodstream).
Bioavailability (F) is a quantitative measure of that process. It represents the extent to which a drug can successfully overcome various biological barriers to enter the systemic circulation.
Exam Tip: Think of absorption as the action (the movement) and bioavailability as the result (the amount that actually made it).
Mechanisms of Drug Absorption
To reach the blood, a drug must cross the epithelial layers of the body. This occurs through two primary routes: transcellular (through the cells) and paracellular (between the cells).
1. Transcellular Absorption
In this route, the drug travels directly through the epithelial cells. This can happen via several distinct sub-mechanisms:
Passive Diffusion
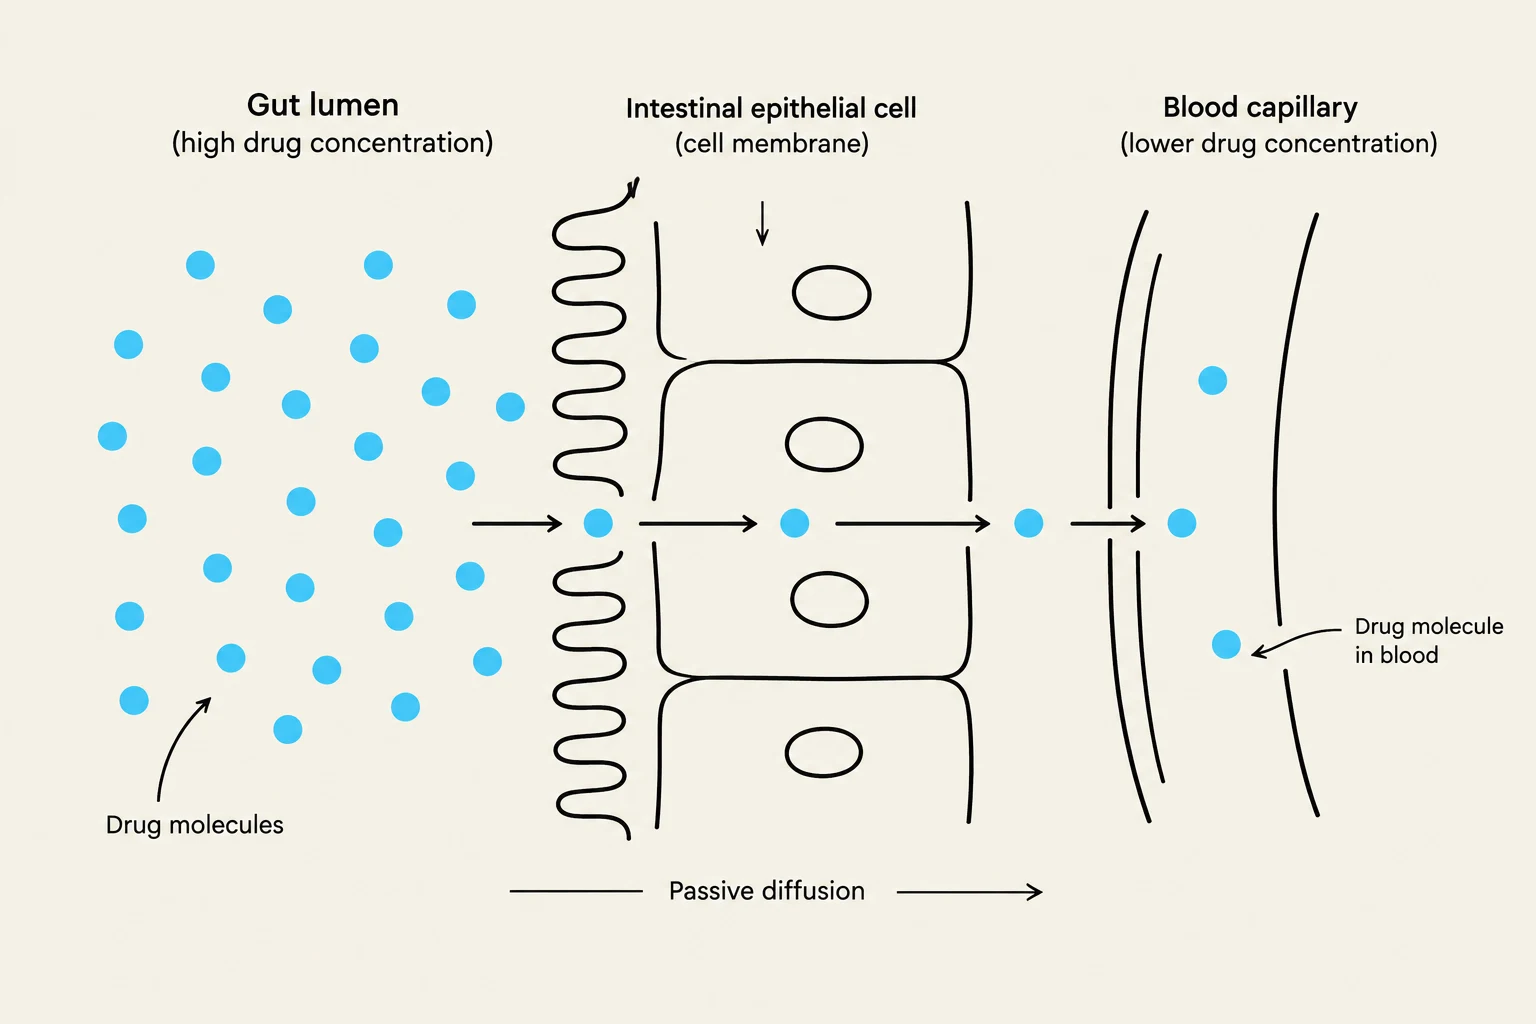
This is the most common method for many drugs. The drug moves from an area of high concentration (such as the gut lumen) to an area of low concentration (the blood). This movement is "passive" because it does not require cellular energy. The rate of this diffusion is influenced by several factors:
Concentration gradient: The difference in drug concentration across the membrane.
Lipophilicity: How well the drug dissolves in fats/lipids. Since cell membranes are phospholipid bilayers, highly lipophilic drugs pass through more easily.
Molecular size and Diffusion constant: Smaller molecules generally move more easily.
Diagram illustrating passive diffusion of drug molecules from the gut lumen, across intestinal epithelial cells, and into a blood capillary.
Carrier-Mediated Transport
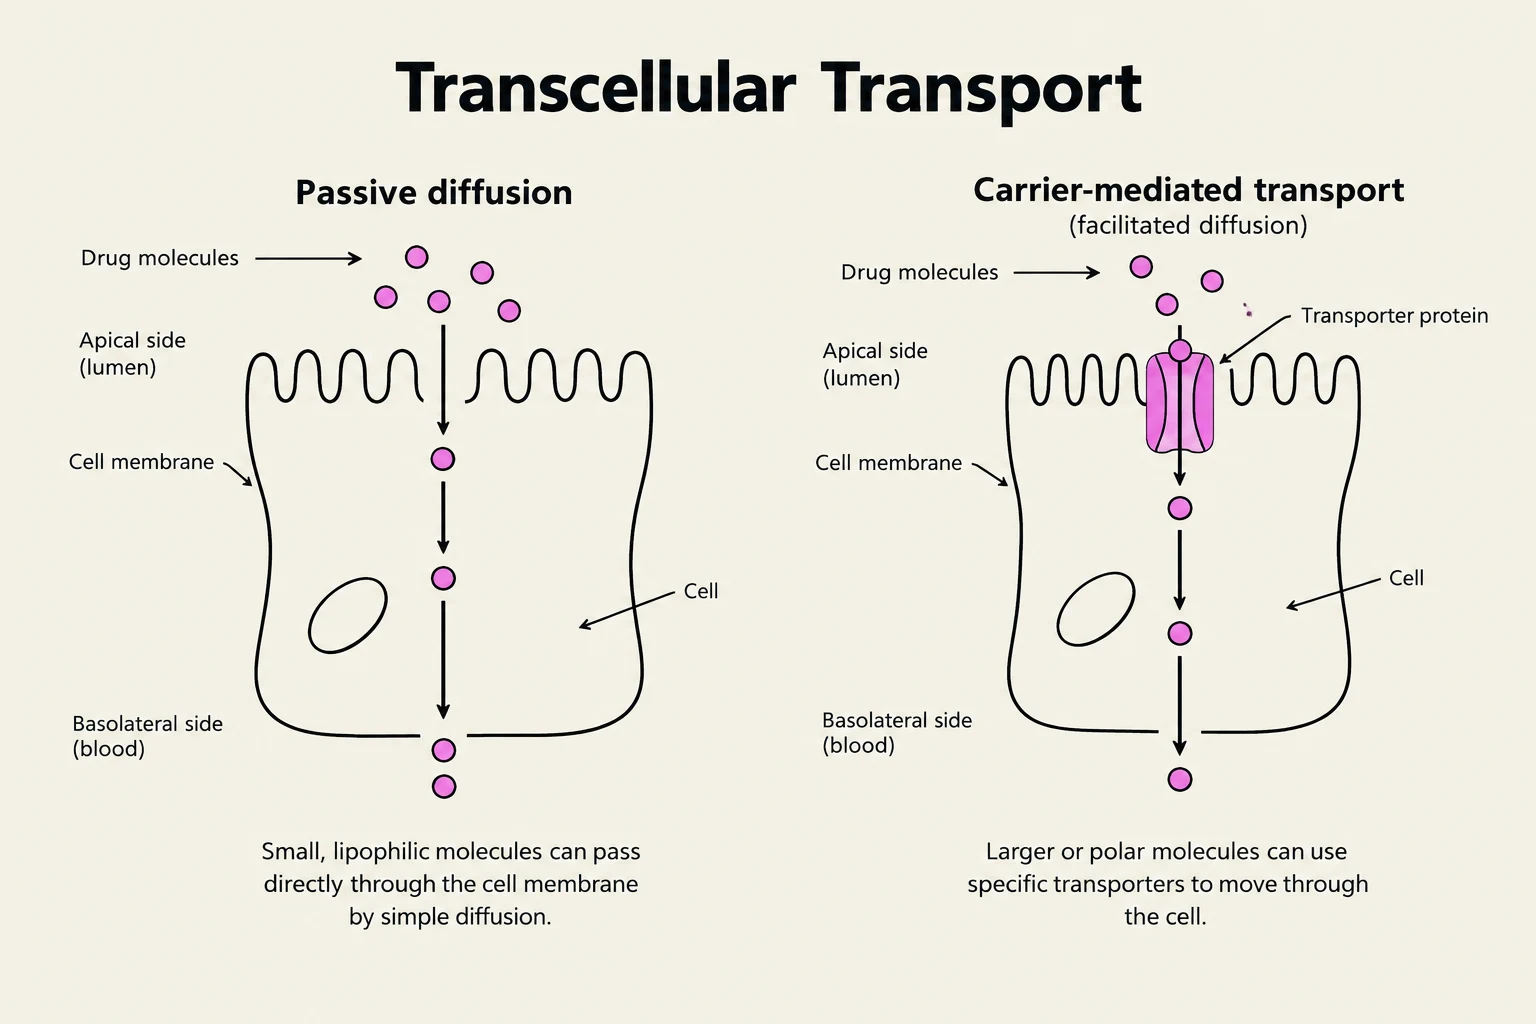
Some drugs are too large or too polar to diffuse passively. Instead, they use specialized membrane proteins called transporters. This can be categorized into three types:
Facilitated Diffusion: Uses a transporter to move drugs down a concentration gradient without using energy.
Active Transport (Absorption): Uses energy (ATP) to pump drugs against a concentration gradient into the blood. An example is the transport of Levodopa.
Active Transport (Efflux): This is a critical concept for drug resistance. Some transporters, like P-glycoprotein (P-gp), use energy to pump drugs out of the cell and back into the intestinal lumen, effectively limiting absorption.
Vesicular Transport (Transcytosis)
For very large molecules, such as certain therapeutic antibodies or the Vitamin B12-intrinsic factor complex, the cell membrane wraps around the drug to form a vesicle, carrying it across the cell.
2. Paracellular Absorption
Rather than going through the cell, some drugs take the "shortcut" by moving through the gaps between adjacent cells, known as tight junctions.
This process is passive, requires no energy, and moves drugs down a concentration gradient. However, because the surface area of these gaps is much smaller than the cell membranes themselves, this route is generally limited to small, hydrophilic (water-loving) molecules.
Diagram illustrating transcellular transport, contrasting passive diffusion with carrier-mediated transport.
Factors Affecting Oral Drug Absorption
The small intestine is the primary site for oral drug absorption due to its massive surface area, rich blood supply, and long residence time. However, several factors can interfere with this process:
Physicochemical Properties: The drug's molecular weight, $pK_a$, and lipophilicity (often measured as Log P values) dictate how easily it crosses membranes.
Patient Factors: Changes in gastrointestinal (GI) motility or the presence of gut wall enzymes can destroy or inactivate drugs before they are absorbed.
Food and Supplements: Certain substances can bind to drugs. For example, calcium or iron supplements can bind to tetracycline antibiotics, making them unavailable for absorption.
Alternative Routes of Administration
When oral absorption is insufficient, or when a faster onset is required, clinicians use alternative routes:
Route
Description
Key Advantage
Sublingual/Buccal
Under the tongue or against the cheek
Rapid onset; bypasses some GI barriers
Rectal
Through the rectum
Useful for children or patients with severe GI issues
Intramuscular (IM)
Injection into muscle
Faster than oral; can use "depot" formulations for prolonged release
Subcutaneous (SC)
Injection under the skin
Good systemic access; rate can be controlled (e.g., insulin)
Percutaneous
Through the skin
Investigated for systemic delivery via the dermis
Pulmonary
Inhalation
Rapid absorption via aerosols or gases
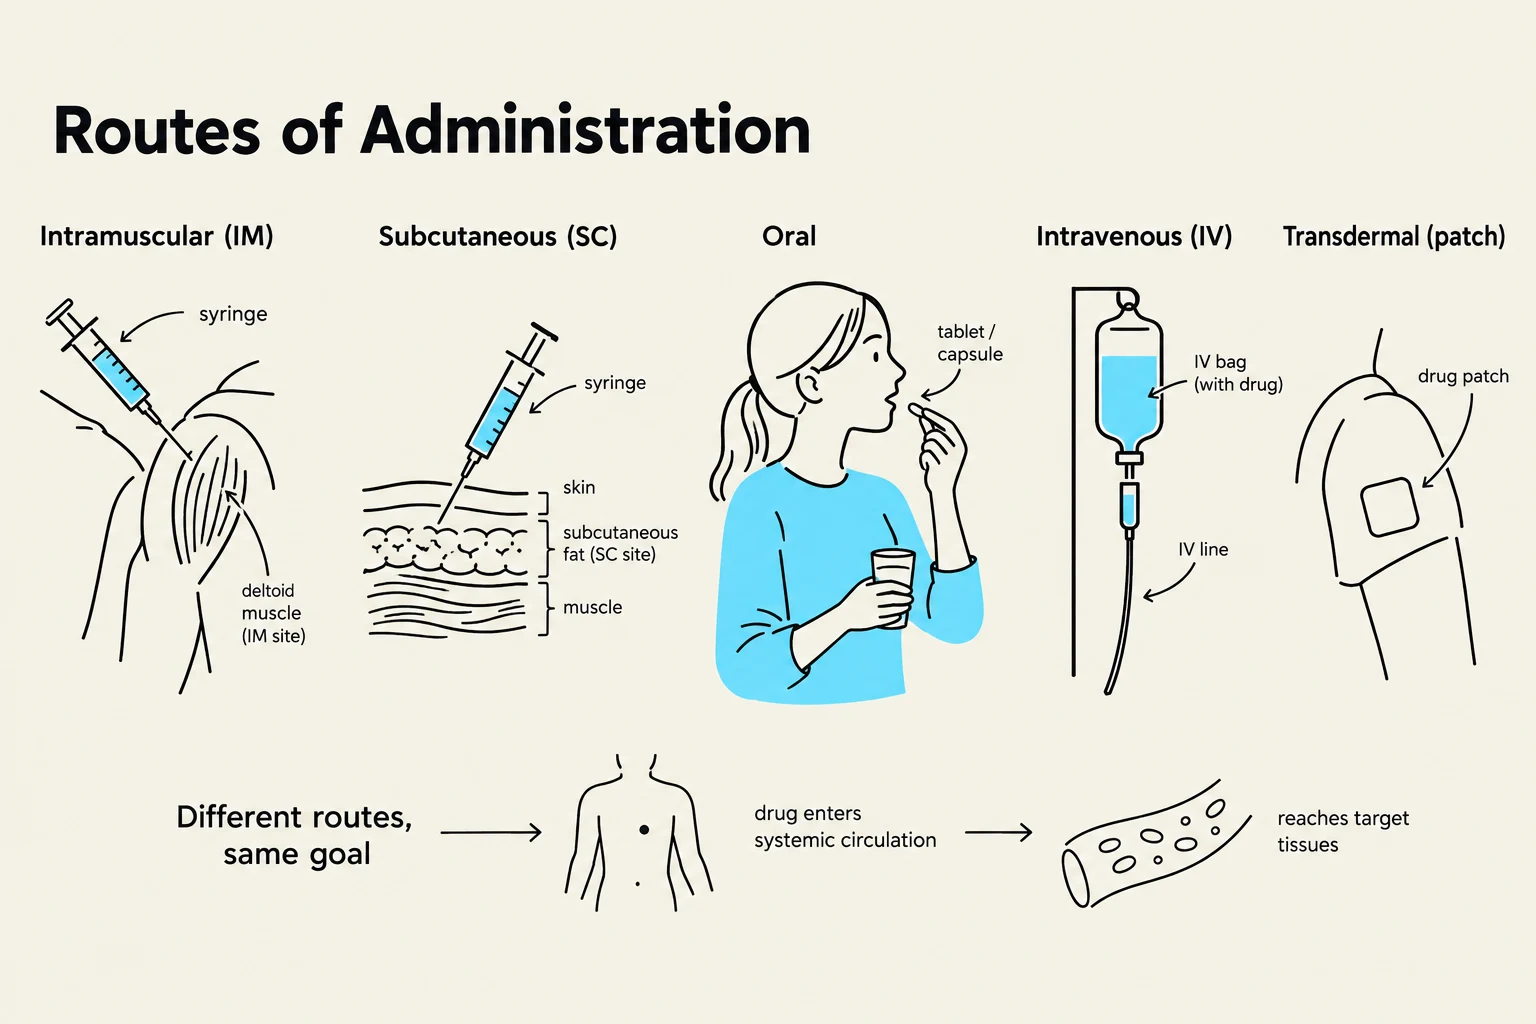
This illustration depicts various routes of drug administration, including intramuscular, subcutaneous, oral, intravenous, and transdermal methods, all aimed at delivering medication to target tissues.
Summary Checklist:
Transcellular: Through the cell (Passive, Carrier-mediated, or Vesicular).
Paracellular: Between the cells (via tight junctions).
P-glycoprotein: An efflux transporter that decreases absorption.
Small Intestine: The "star" of oral absorption.
Bioavailability: The quantitative measure of how much drug reaches the blood.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.