Maxillary and Mandibular Root Morphology in Endodontics
A comprehensive guide to the root and canal morphology of maxillary and mandibular teeth, essential for successful endodontic treatment. Covers variations, classifications, and clinical considerations.
Understanding the internal anatomy of the dentino-pulpar complex is essential for predictable endodontic outcomes. Successful treatment—defined as a healthy, functional tooth in a healthy periapical environment—relies on the clinician's ability to clean, shape, and obturate the entire canal system. Because root and canal configurations vary significantly between the maxillary and mandibular arches, a systematic understanding of tooth-specific morphology is a prerequisite for clinical success.
Maxillary Teeth: Anatomy and Variations
The maxillary arch generally presents with more predictable root numbers in the anterior region, but complexity increases significantly in the posterior teeth due to multiple canals and frequent anatomical variations.
Anterior Maxillary Teeth
The Maxillary Central Incisor is highly predictable, being single-rooted ($100%$) and almost invariably single-canaled ($99.9%$). The Maxillary Lateral Incisor follows a similar pattern but is considered the most variable anterior tooth. It has an average length of 22.0 mm and is the most frequent site for dens invaginatus (a "tooth within a tooth" anomaly). The Maxillary Canine is the longest tooth in the arch, averaging 26.5 mm. While it is single-rooted in over $98%$ of cases, a second canal may be present in $3%$ of teeth.
Maxillary Premolars
The Maxillary First Premolar is notably complex. It frequently presents with two roots ($55.3%$) and two canals (≈85%). Clinicians must always assess for one- and three-root variants. In contrast, the Maxillary Second Premolar is more likely to be single-rooted ($90%$). However, even in single-rooted teeth, two canals are present in $40%$ of cases. The access cavity for the second premolar is typically ovoid and generally easier to access than the first premolar.
Maxillary Molars
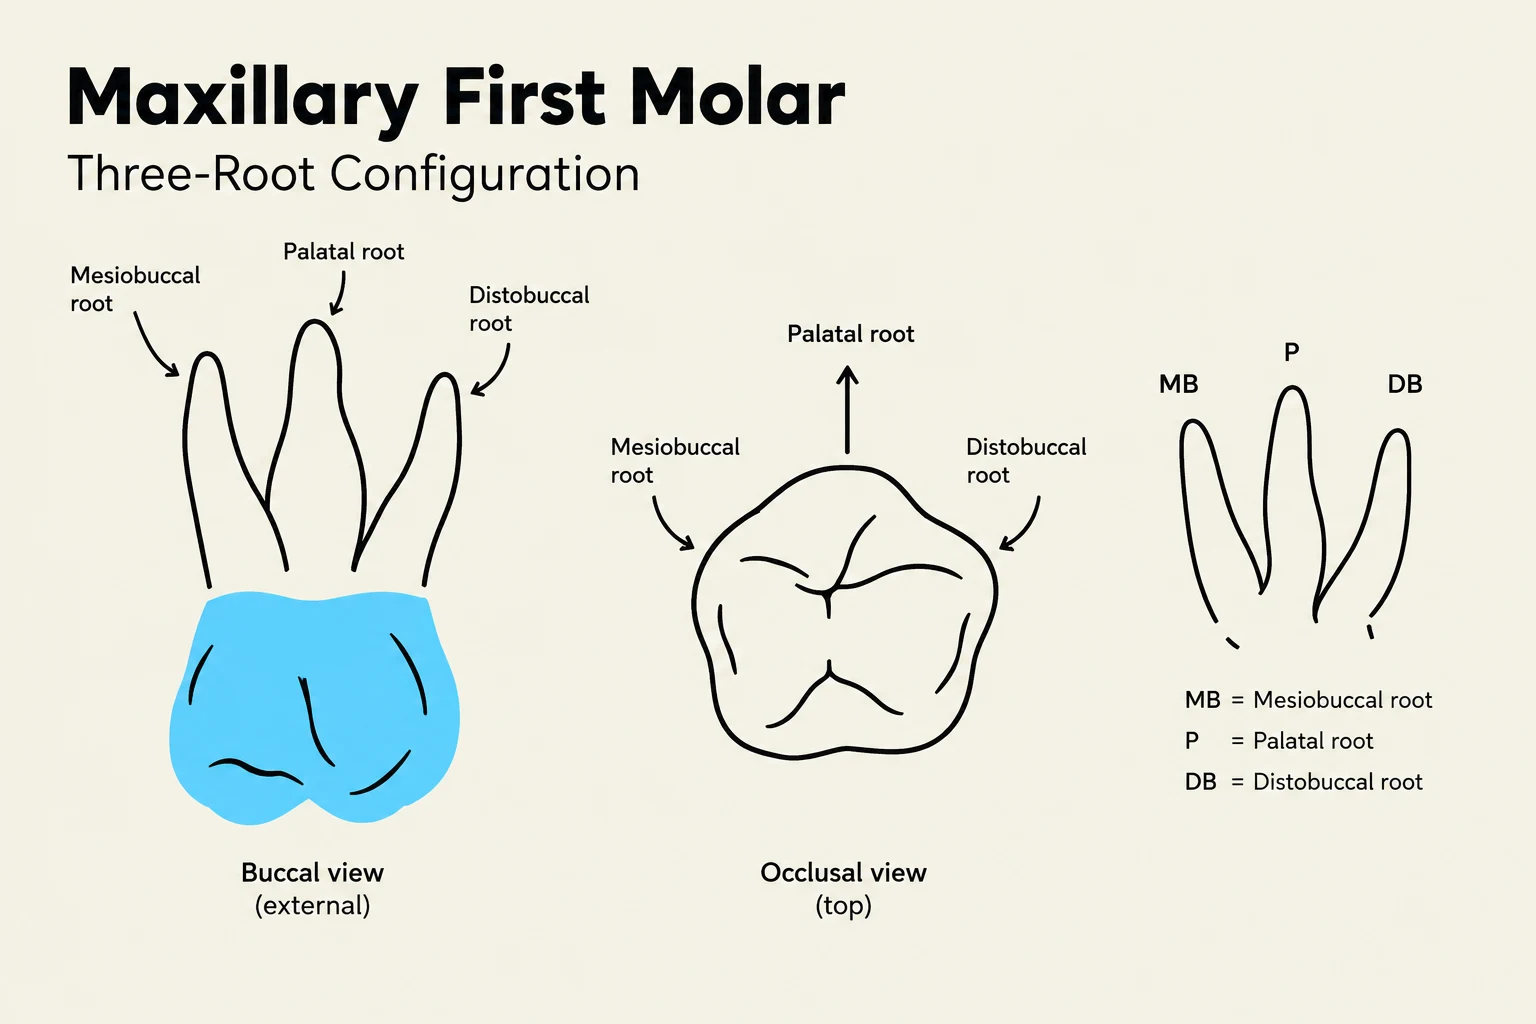
The Maxillary First Molar is characterized by high variability. It typically possesses three roots ($97.7%$). While $40%$ of these teeth have three canals, $60%$ possess four canals. A critical clinical consideration is the MB2 canal (the second mesiobuccal canal), which is present in a significant number of cases—up to $70%$ when viewed via CBCT.
The Maxillary Second Molar often exhibits root fusion, which can complicate treatment. While three roots are most common ($74%$), configurations with two roots ($15%$) or even a single fused root (2–6%) are observed. Canal numbers are also variable, with three canals being the most frequent (≈59%).
Diagram illustrating the three-root configuration of a maxillary first molar, showing buccal (external) and occlusal (top) views, with labels for mesiobuccal, palatal, and distobuccal roots.
Mandibular Teeth: Complexity and Classification
Mandibular teeth often present unique challenges, such as ribbon-shaped roots and C-shaped canal configurations, which require specific clinical approaches.
Mandibular Anterior Teeth
The Mandibular Central Incisor is primarily single-rooted ($99.92%$) with an average length of 20.8 mm. Its canal morphology is best understood through the Vertucci classification:
Type I ($70%$): A single canal from pulp to foramen.
Type II (25–27%): Two separate canals that join into one before reaching the apex.
Type III ($3%$): A single canal that divides and then rejoins.
Type IV (5–15%): Two distinct canals that exit through two separate foramina.
The Mandibular Lateral Incisor is similar but shows a higher prevalence of Type IV morphology ($15%$) compared to the central incisor.
Mandibular Premolars and Canines
The Mandibular Canine has an average length of 25.0 mm and an ovoid access. A significant morphological variation is the ribbon-shaped root, which can mimic the appearance of two separate canals until the dentin fin is removed during instrumentation.
The Mandibular First Premolar is mostly single-rooted ($94%$) and single-canaled ($71.3%$), though approximately $27.9%$ of cases present with two canals.
Mandibular Molars
The Mandibular First Molar typically has two roots ($87%$), though a third root, known as radix entomolaris, occurs in approximately $12%$ of the population. Clinicians should be aware of the middle mesial canal, which is present in 1–15% of these teeth.
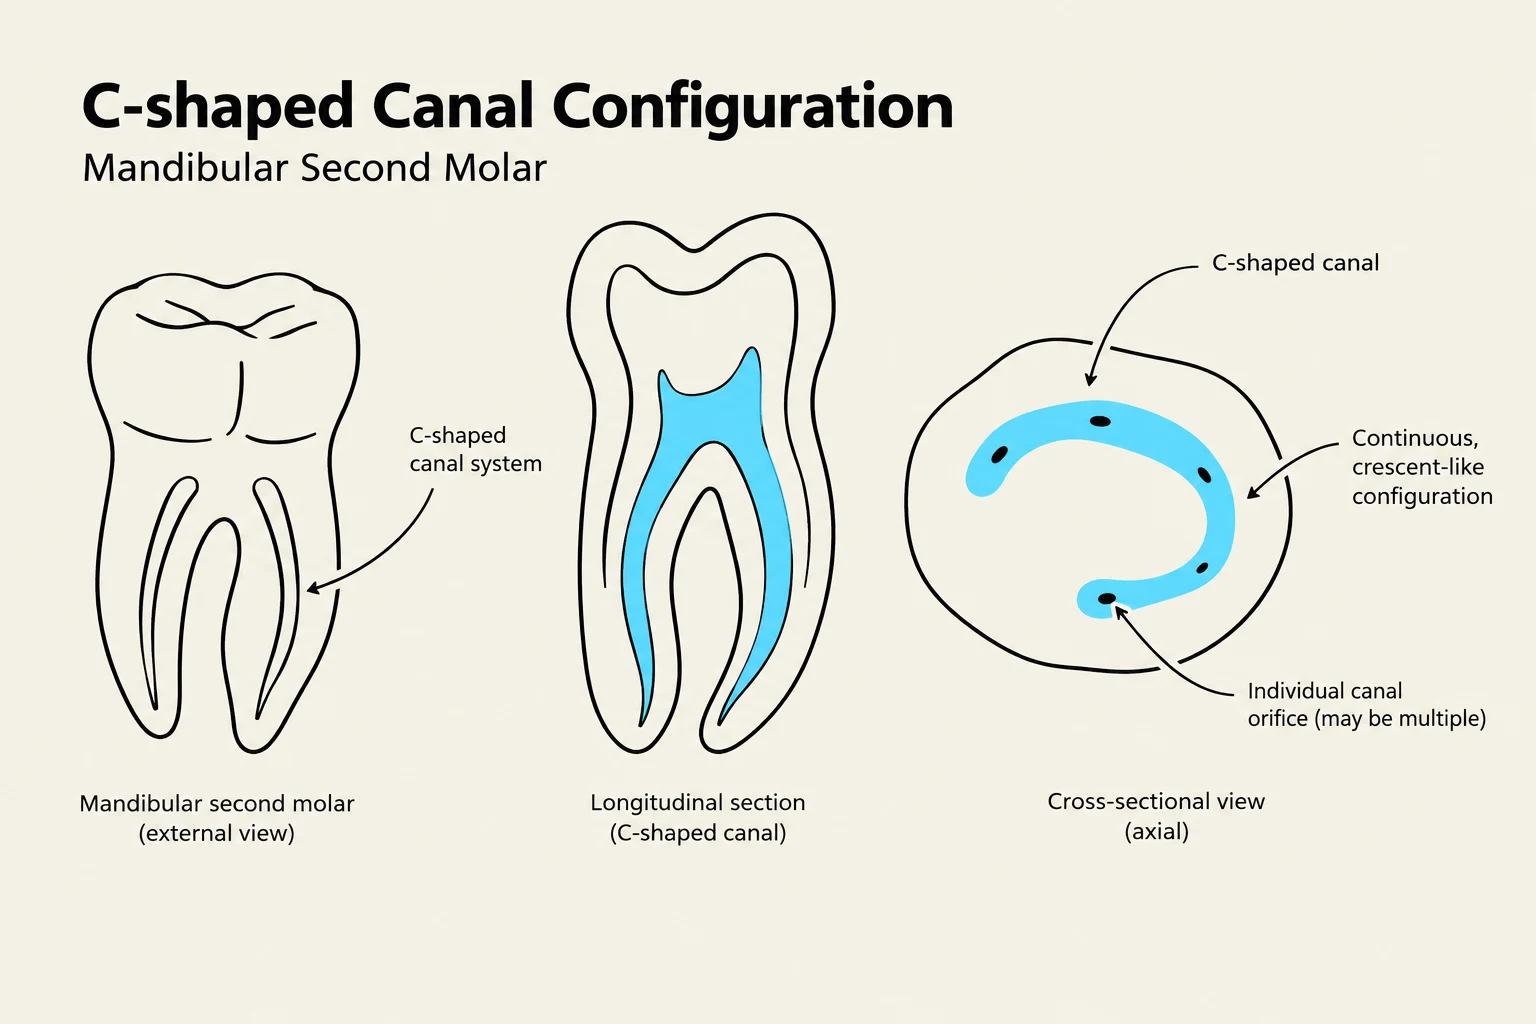
The Mandibular Second Molar is highly variable due to the presence of C-shaped canals. These occur when the mesial and distal roots fuse, creating a continuous, crescent-shaped canal space rather than distinct round canals.
Diagram illustrating the C-shaped canal configuration in a mandibular second molar, showing external, longitudinal, and cross-sectional views.
Clinical Tip: The MB2 and Middle Mesial Canals
When treating maxillary first molars, always search for the MB2 canal using a systematic approach. For mandibular first molars, if a middle mesial canal is suspected, use an ultrasonic tip under magnification to trough the dentin along the developmental groove between the mesial orifices.
Summary of Morphological Data
The following tables summarize the average lengths and canal prevalence for key teeth.
Maxillary Teeth Summary
Tooth
Avg Length (mm)
1 Canal (%)
2 Canals (%)
3 Canals (%)
4 Canals (%)
Central Incisor
22.5
99.9
0.1
-
-
Lateral Incisor
22.0
99.9
0.1
-
-
Canine
26.5
97
3
-
-
1st Premolar
20.6
9
85
6
-
2nd Premolar
21.5
60
40
-
-
1st Molar
20.8
-
-
40
60
2nd Molar
20.0
≈1
≈15
≈60
≈25
Mandibular Teeth Summary
Tooth
Avg Length (mm)
1 Canal (%)
2 Canals (%)
3 Canals (%)
4 Canals (%)
Central Incisor
20.8
70
30
-
-
Lateral Incisor
21.0
55
45
-
-
Canine
25.0
88.2
11.8
-
-
1st Premolar
22.0
71.3
27.9
0.8
-
2nd Premolar
22.3
85
15
-
-
1st Molar
21.0
-
8
56
36
2nd Molar
19.8
-
16.2
72.5
11.3
Exam Note: Vertucci vs. Weine Classifications
Be careful not to confuse the two systems. A "Type III" in the Weine classification describes different anatomy than a "Type III" in the Vertucci classification. Always verify which system is being used when reviewing literature.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.