


Pregnancy is a physiological state that places significant demand on nearly every organ system. When a patient enters pregnancy with a pre-existing medical condition—referred to as a pregestational disease—the clinical stakes are significantly higher. These conditions require intensive, multidisciplinary management because they can jeopardize the health of both the mother and the offspring.
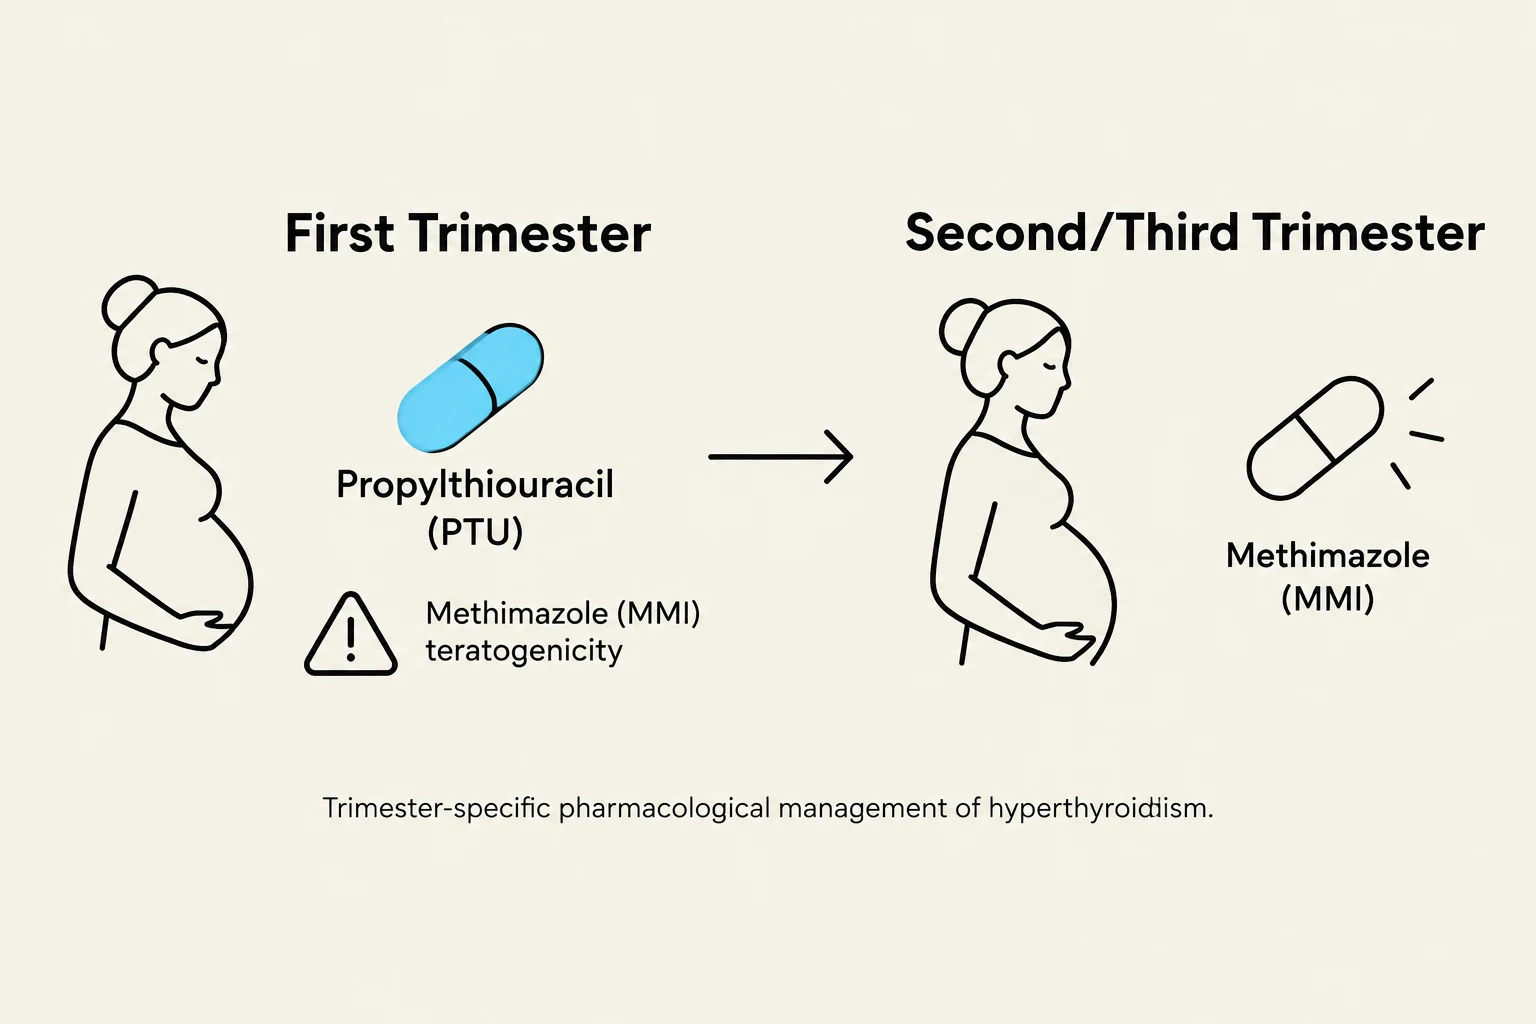
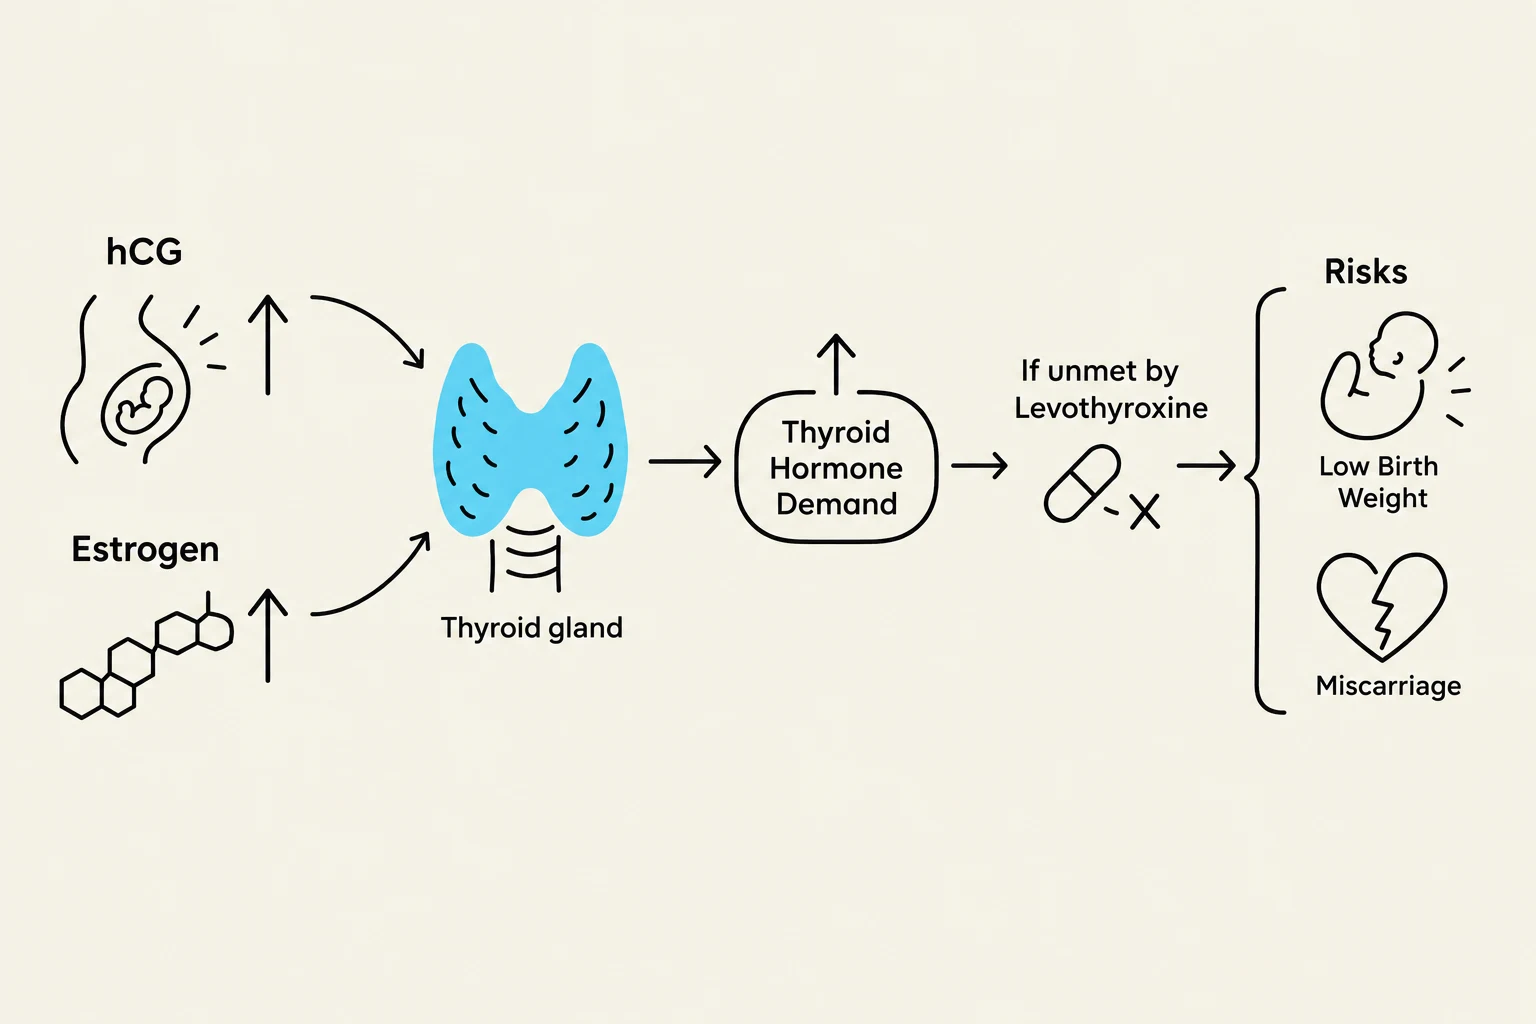
While many conditions like anemia or obesity require careful monitoring, certain diseases such as chronic hypertension, thyroid disorders, and asthma require specific pharmacological adjustments and vigilant screening to prevent life-threatening complications.
Chronic Hypertension in Pregnancy
Chronic hypertension is defined by blood pressure levels established before pregnancy, appearing before the 20th week of gestation, or persisting for more than 12 weeks into the postpartum period.
Clinical Goals and Risks
The primary objective of managing chronic hypertension is twofold:
- Prevent Superimposed Preeclampsia: This is a serious systemic disease characterized by hypertension combined with abnormal renal laboratory findings.
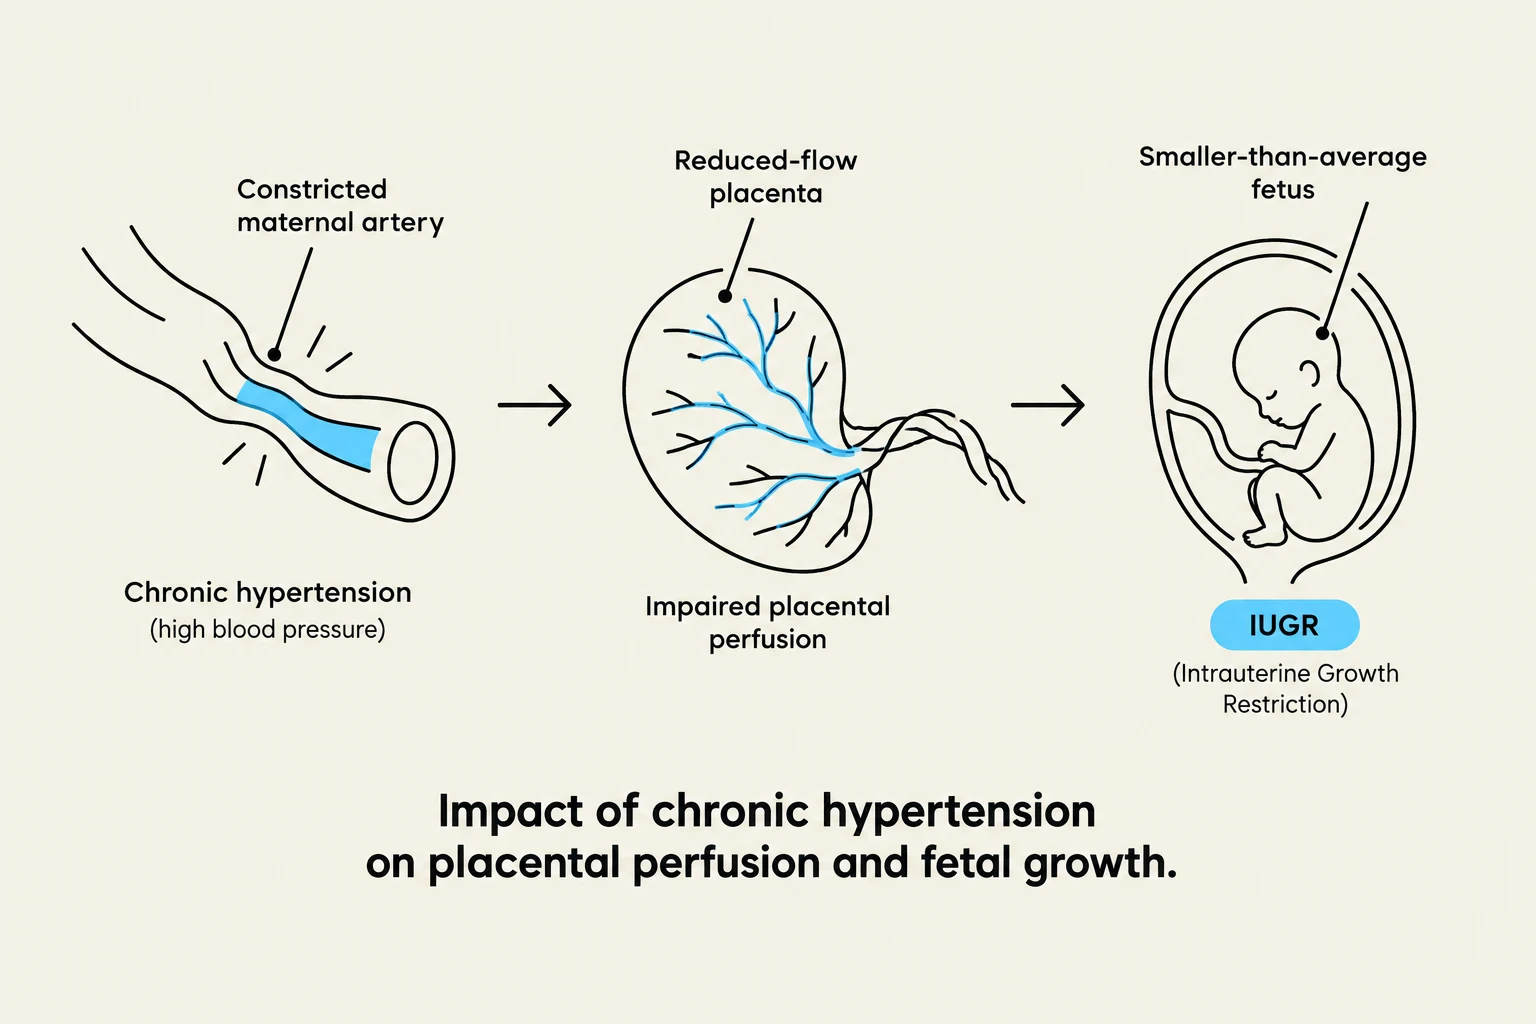
- Maintain Fetal Growth: Chronic hypertension can impair placental perfusion, which is essential for delivering nutrients and oxygen to the developing fetus.
If left unmanaged, the risks to the mother and fetus are severe, including stroke, acute kidney injury (AKI), heart failure, placental abruption, intrauterine growth restriction (IUGR), and preterm birth.
Monitoring and Management
Management involves a proactive approach to prevent these complications:
- Prenatal Visits: Patients typically require biweekly prenatal visits.
- Ultrasounds: Frequent ultrasounds (sometimes as often as biweekly) are necessary to monitor fetal growth and detect signs of impaired perfusion.
- Laboratory Monitoring: Clinicians must regularly check 24-hour urine protein, creatinine, uric acid, and hemoglobin/hematocrit levels.
- Lifestyle Interventions: Management includes stress reduction, home blood pressure monitoring, and dietary sodium restriction (ideally 2–2.4 grams per day).
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated