Lymphatic System Physical Examination and Assessment
This guide details the physical examination of the lymphatic system, focusing on lymph node assessment, drainage patterns, and the interpretation of findings to identify potential pathologies like infection or malignancy. It covers head and neck, supraclavicular, and peripheral lymph node chains, as well as specialized
The lymphatic system plays a critical role in immune surveillance and fluid homeostasis, acting as a filtration network that cleanses lymph before it returns to the venous circulation. During a physical examination, the primary goal is to identify lymphadenopathy—the enlargement of lymph nodes—and use the location, consistency, and mobility of these nodes to localize potential underlying pathology, such as infection or malignancy.
Lymph Node Chains and Drainage Patterns
Understanding the anatomical drainage patterns is essential for clinical reasoning. Because lymph nodes drain specific regions, an enlarged node often serves as a "signpost" for a problem in the area it serves.
Head and Neck Chains
The head and neck contain the most clinically significant groups for routine examination:
Occipital: Located at the base of the skull; often associated with scalp inflammation.
Preauricular/Postauricular: Found in front of or behind the ear; drains the eyelids, conjunctiva, and ear.
Tonsillar (Jugulodigastric): Located at the angle of the mandible; typically responds to pharyngitis or tonsillitis.
Submandibular and Submental: Located under the jaw and chin; drain the teeth, gums, tongue, and lower lip.
Anterior Cervical: Located along the sternocleidomastoid muscle; associated with upper respiratory or pharyngeal disease.
Posterior Cervical: Located along the posterior border of the sternocleidomastoid; enlargement here is a classic association with mononucleosis.
Supraclavicular Nodes: A Critical Landmark
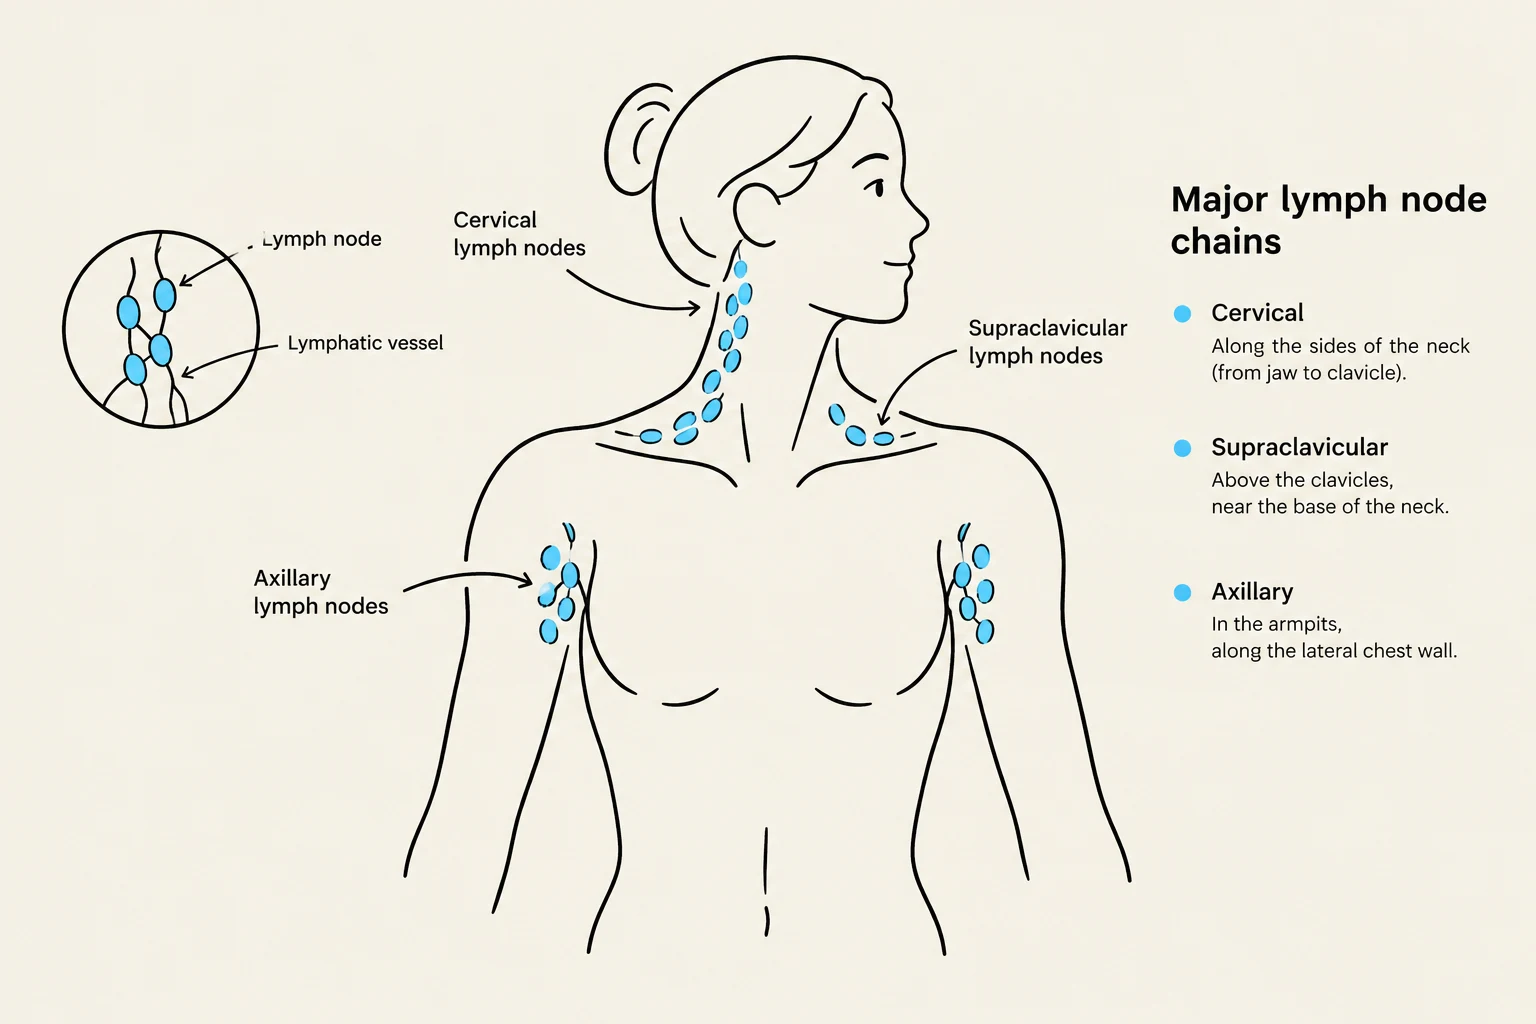
The supraclavicular nodes are located just above the clavicle and drain the thorax and abdomen. These nodes are high-yield for clinicians because their enlargement is rarely benign:
Left-sided (Virchow’s nodes): Highly suspicious for abdominal or gastrointestinal (GI) malignancy.
Right-sided: May reflect disease within the thoracic cavity.
Diagram illustrating the major lymph node chains in the human body, including cervical, supraclavicular, and axillary nodes.
Peripheral Chains
Axillary: Drains the upper limb, breast, and chest wall; common in breast disease or lymphoma.
Epitrochlear: Located at the medial elbow; drains the ulnar forearm and hand. Enlargement in this area is unusual and clinically significant.
Inguinal: Drains the lower abdomen, external genitalia, perineum, and much of the lower limb.
Popliteal: Located behind the knee; drains the lateral foot and posterolateral leg. Like the epitrochlear nodes, enlargement here is unusual.
Lymphadenopathy Assessment Techniques
When a patient presents with palpable nodes, the clinician must move beyond simple detection to a systematic characterization.
The Clinical Approach
History: Inquire about onset, duration, pain, recent infections, dental disease, travel, medications, and systemic "B symptoms" like weight loss or night sweats.
Inspection: Look for asymmetry, skin changes (redness or swelling), or visible masses.
Palpation: Use warm finger pads and a gentle circular motion. It is vital to compare both sides of the body and document the following characteristics:
Size and Number
Consistency (Soft, firm, or hard)
Mobility (Mobile vs. fixed/matted)
Tenderness
Exam Tip: Always examine the body region that drains to the enlarged node. For example, if you find enlarged submandibular nodes, perform a thorough inspection of the teeth, gums, and oral mucosa.
Interpreting Findings
The clinical significance of the findings can be categorized into several patterns:
Pattern
Typical Findings
Clinical Meaning
Normal/Low-risk
Small, soft, mobile nodes; no systemic symptoms
Reassure or observe if a recent self-limited infection is present
Acute Infection
Tender, soft, mobile nodes; possible warmth/erythema
Local bacterial or viral source; treat the cause, not the node
Viral/Generalized
Multiple mobile nodes; fever, fatigue, or rash
Consider EBV/CMV or HIV; test based on exposure
Malignancy Concern
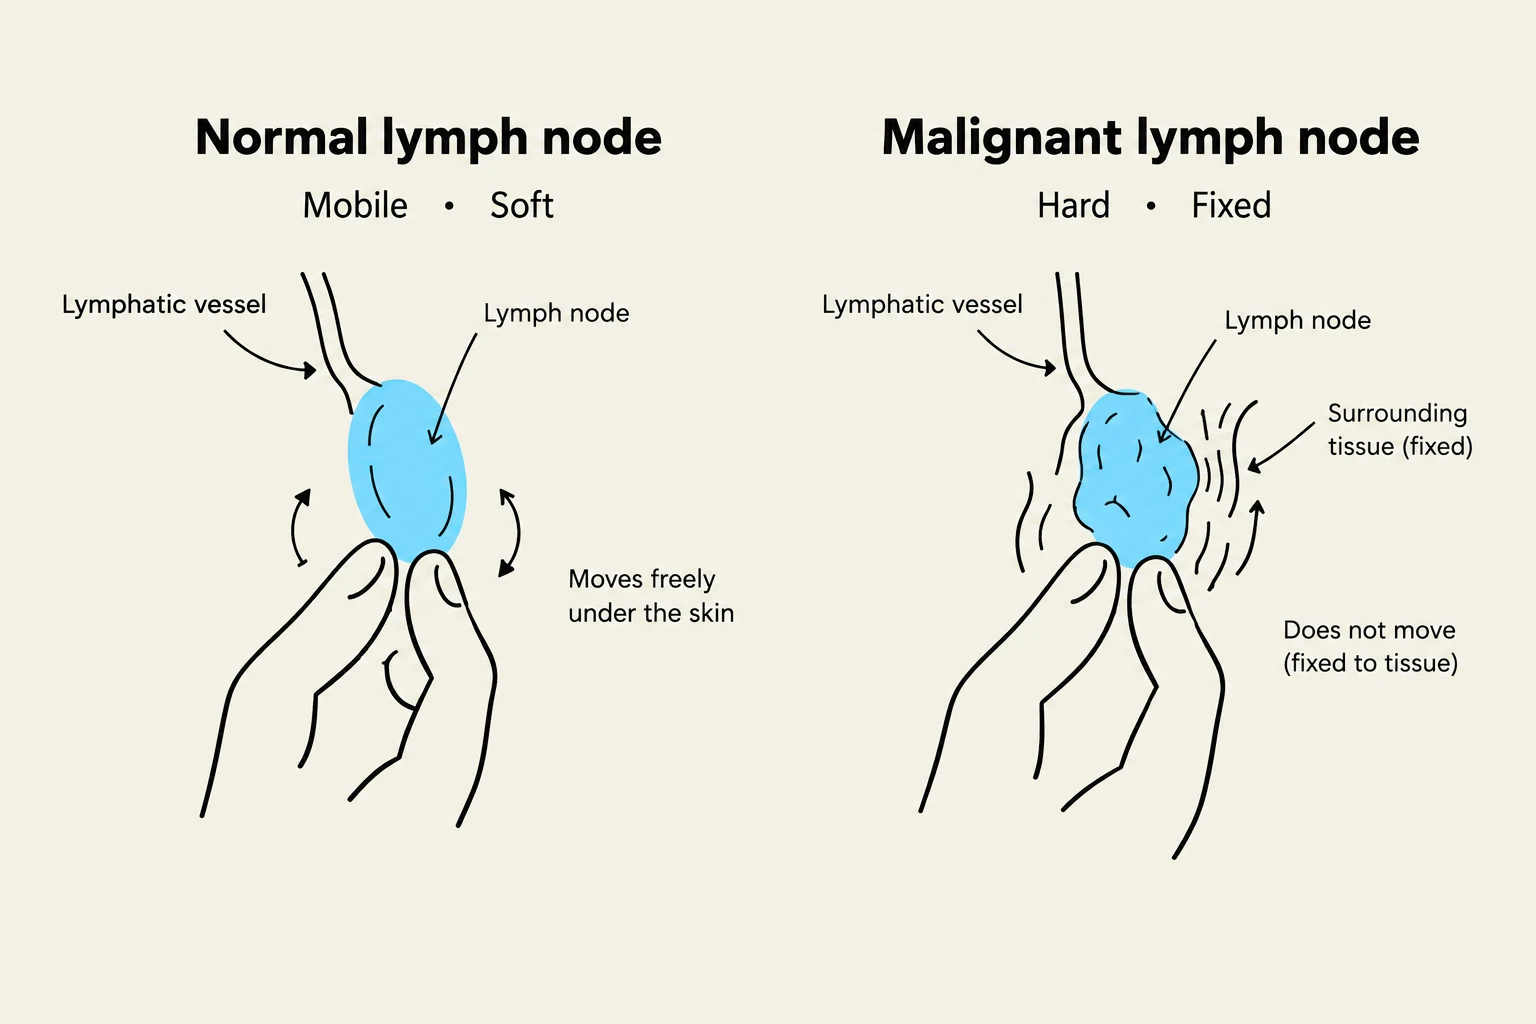
Hard, fixed, matted, painless, or enlarging
Prompt imaging, biopsy, or specialty referral
Comparison of a normal lymph node, which is mobile and soft, with a malignant lymph node, which is hard and fixed to surrounding tissue.
Specialized Lymphatic Findings
Lymphangitis and Lymphedema
Not all lymphatic issues present as discrete nodes.
Lymphangitis: This presents as a tender, erythematous (red) streak extending proximally from a wound toward the regional lymph nodes. This is a sign of a bacterial skin or soft-tissue infection and requires treatment of the underlying infection.
Lymphedema: Characterized by persistent limb swelling, heaviness, and skin thickening. This requires skin care and compression therapy after ruling out acute DVT or infection.
Mononucleosis and Splenomegaly
In cases of generalized lymphadenopathy associated with fever and pharyngitis, mononucleosis (often caused by EBV) is a primary consideration. When managing suspected mononucleosis, clinicians must assess for splenomegaly (enlargement of the spleen).
Clinical Management Note: For patients with mononucleosis, it is critical to restrict contact or collision sports until they are clinically cleared, due to the high risk of splenic rupture.
Red Flags and Management Principles
Recognizing "red flags" is the most important skill in lymphatic assessment to prevent delayed diagnosis of malignancy or systemic disease.
Red Flags Requiring Immediate Investigation
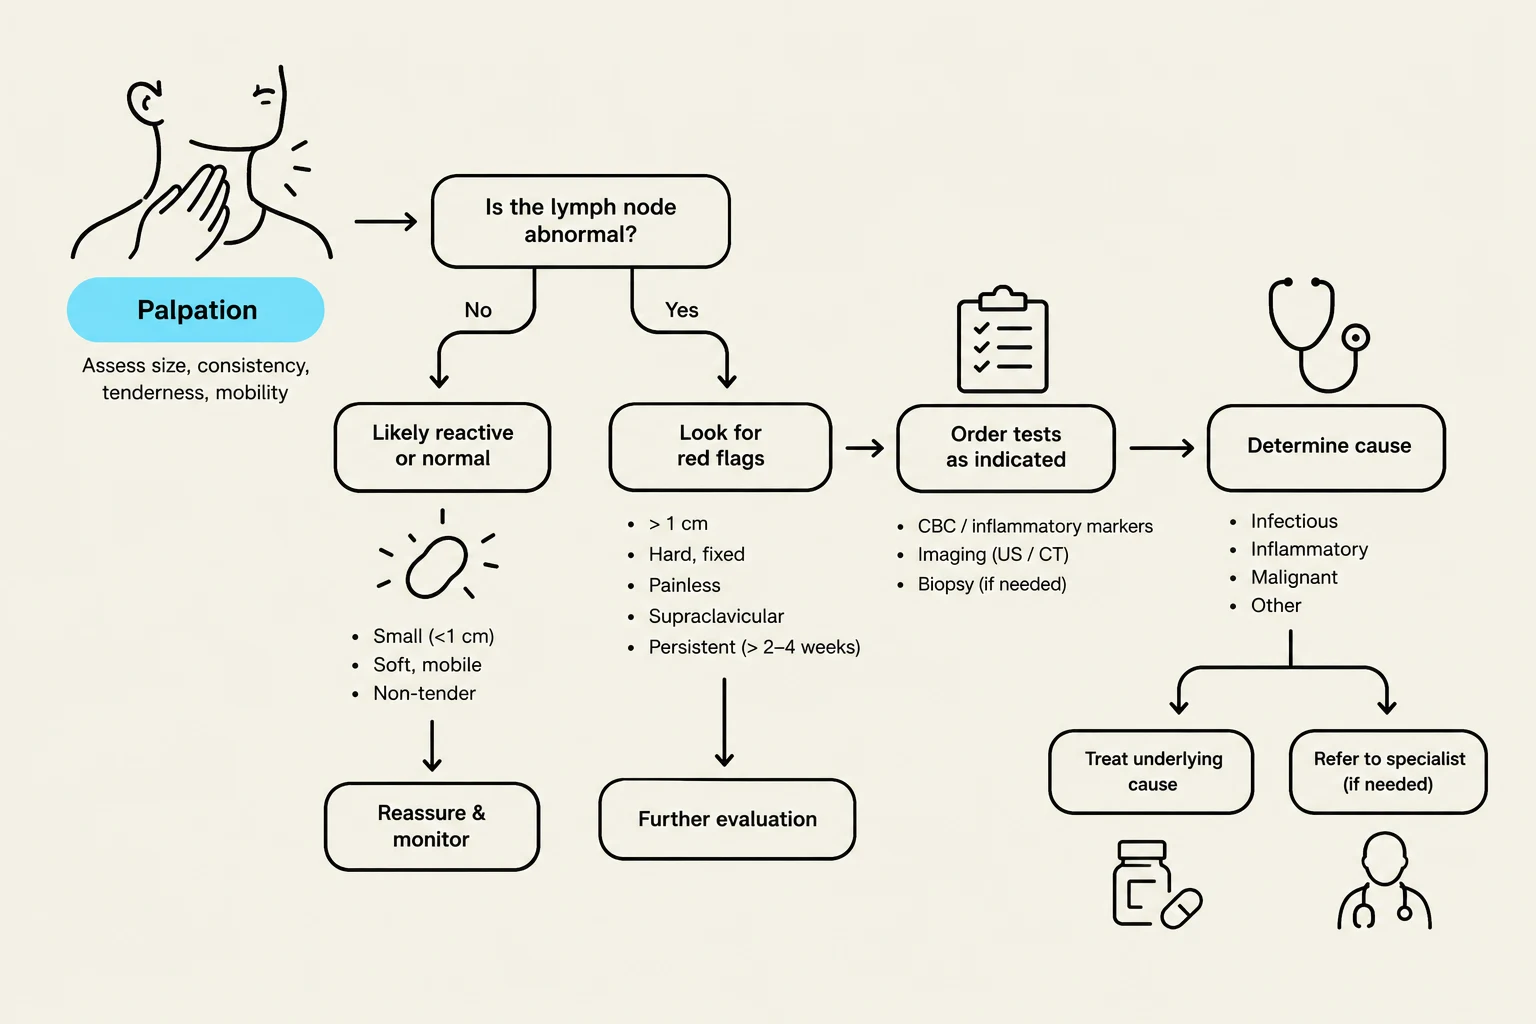
If any of the following are present, immediate investigation via imaging, CBC with differential, or biopsy is warranted:
B Symptoms: Unintentional weight loss, drenching night sweats, unexplained fever, or profound fatigue.
Concerning Node Characteristics: Nodes that are hard, fixed, matted, larger than 1 cm, or rapidly enlarging.
High-Risk Locations: Supraclavicular, epitrochlear, popliteal, or iliac nodes.
Systemic Signs: Hepatosplenomegaly, cytopenias (low blood cell counts), airway compromise, or general systemic toxicity.
Management Principles
Target the Cause: Treatment should focus on the underlying infection or disease rather than the node itself.
Antibiotic Stewardship: Use antibiotics only when there is evidence of bacterial lymphadenitis; viral lymphadenopathy requires only supportive care.
Avoid Steroids: Do not administer empiric corticosteroids if lymphoma is a possibility, as steroids can obscure the diagnostic pathology and make a subsequent biopsy less accurate.
This flowchart outlines the process of assessing lymph nodes, differentiating between normal and abnormal findings, and guiding further evaluation and treatment.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.