Introduction to Pharmacology: Drug Action and Regulation
An overview of pharmacology, covering drug characteristics, nomenclature, regulation, development, pharmacokinetics, pharmacodynamics, and clinical application metrics.
Pharmacology is a multidisciplinary science that integrates knowledge from anatomy, physiology, psychology, chemistry, and microbiology to understand how chemical substances interact with living systems. While the term "drug" refers to any chemical that can affect living processes, in a clinical setting, we focus specifically on those with therapeutic applications. To master this field, one must distinguish between pharmacology (the study of drug interactions), clinical pharmacology (the study of drugs in humans), and therapeutics (the medical use of drugs to diagnose, prevent, or treat disease).
The Nature of Drugs and Ideal Properties
In theory, we strive for an "ideal drug," but in clinical practice, perfection does not exist. Every drug possesses three fundamental characteristics: effectiveness, safety, and selectivity.
Effectiveness: The ability of a drug to elicit the response for which it is given. This is the most important property.
Safety: The degree to which a drug can be administered without causing harm. It is important to note that no drug is truly "safe," as all medications can produce side effects.
Selectivity: The ability of a drug to elicit only the specific response desired. In reality, most drugs cause unintended side effects.
Beyond these "Big Three," an ideal drug would ideally be reversible in action, predictable, easy to administer, chemically stable, low in cost, free from drug interactions, and possess a simple generic name.
Exam Tip: If a question asks if a "perfect" or "completely safe" drug exists, the answer is no. All drugs have the potential for adverse effects or interactions.
Drug Nomenclature and Regulation
Drugs are identified by three distinct types of names:
Chemical Name: A long, complex description using chemical nomenclature (e.g., N-Acetyl-para-aminophenol).
Generic Name: The nonproprietary name assigned by official councils (e.g., Acetaminophen).
Trade Name: The proprietary name created by pharmaceutical companies for marketing (e.g., Tylenol).
The regulation of these substances has evolved from minimal control to extensive oversight through landmark legislation. The Pure Food and Drug Act of 1906 was the first to regulate drugs but was weak, only requiring that drugs be free of adulteration. The Food, Drug and Cosmetic Act of 1938 was passed following a tragedy involving sulfanilamide, requiring that drugs be proven safe before marketing. Later, the Harris-Kefauver Amendments (1962) required drugs to be proven effective, following the thalidomide tragedy. Finally, the Controlled Substance Act of 1970 established schedules for drugs with potential for abuse.
The Development and Testing of New Drugs
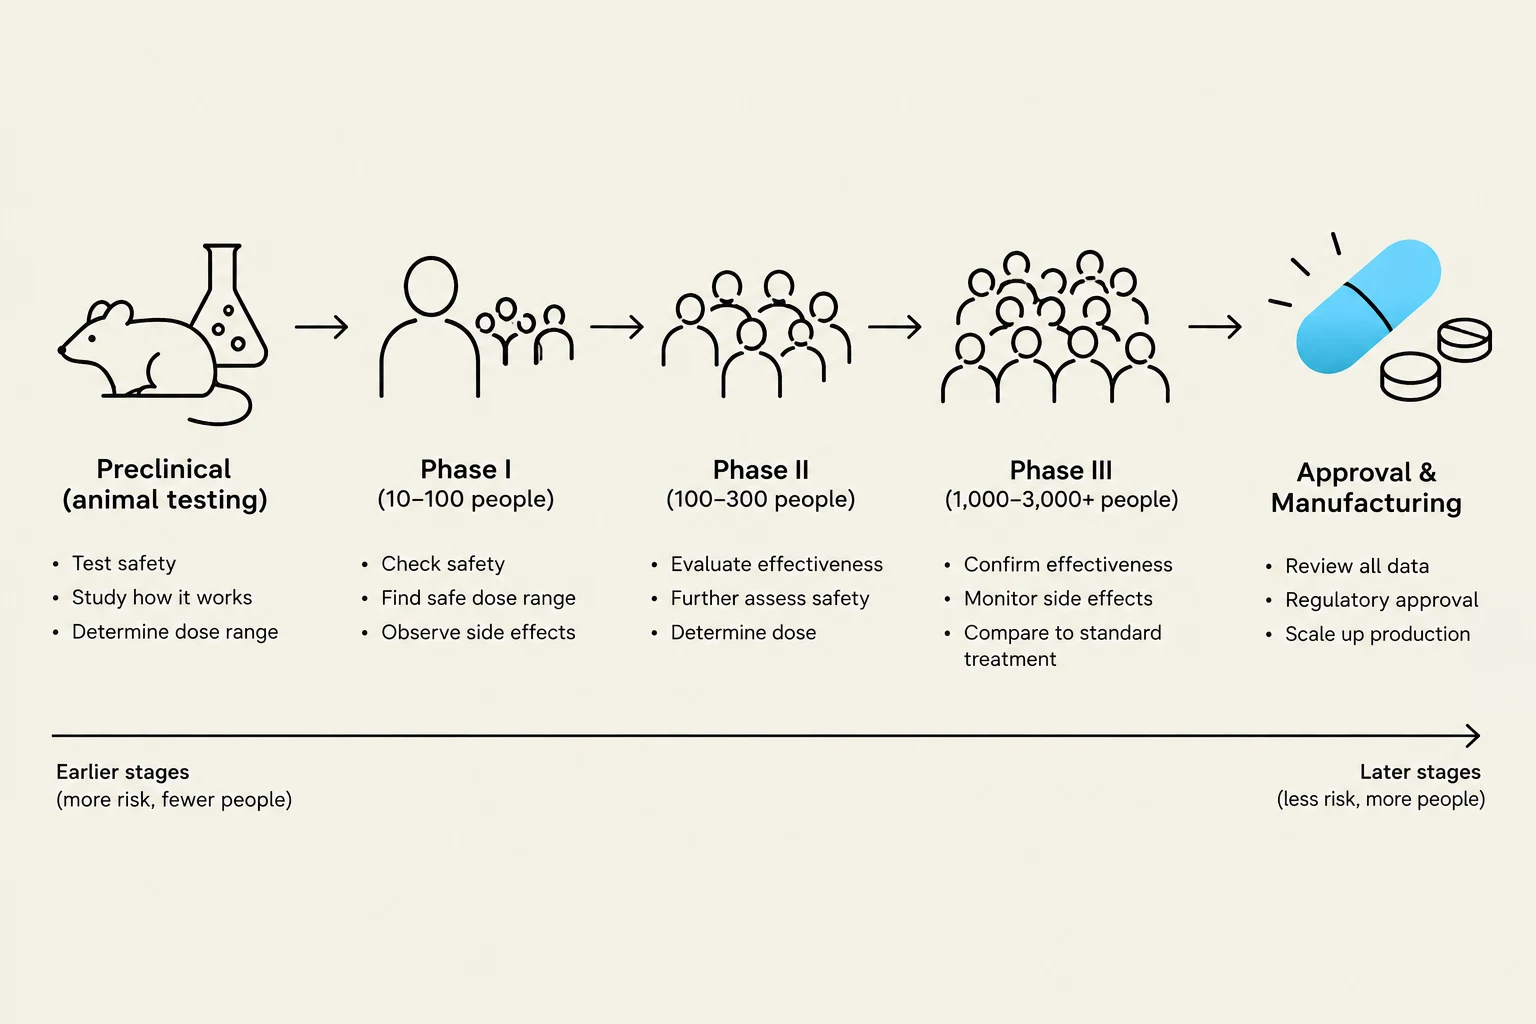
Developing a new drug is a massive undertaking, often costing between $200 million and $800 million and taking 6 to 12 years. The process follows a rigorous path:
Preclinical Testing: Conducted in animals to evaluate toxicity, pharmacokinetics, and potential biological effects.
Clinical Testing (Phases I–IV):
Phase I: Conducted in normal volunteers to evaluate metabolism and effects in humans.
Phases II & III: Tested in much larger groups of patients (500 to 5,000) to determine therapeutic effects, dosage ranges, and safety.
Phase IV: Postmarketing surveillance, where the drug is released for general use and monitored for rare or long-term adverse effects.
To ensure objectivity, researchers use Randomized Controlled Trials (RCTs). These involve a control group (receiving a standard treatment or a placebo) and use randomization to prevent bias. Furthermore, blinding is used to minimize personal bias: in a single-blind study, the subject does not know which treatment they are receiving, while in a double-blind study, neither the subject nor the researcher knows.
This diagram illustrates the typical phases of drug development, from preclinical animal testing through clinical trials (Phases I, II, and III) to final approval and manufacturing.
Pharmacokinetics and Pharmacodynamics
To understand how a drug works, we must look at two distinct processes: Pharmacokinetics (what the body does to the drug) and Pharmacodynamics (what the drug does to the body).
Pharmacokinetics: The Four Processes
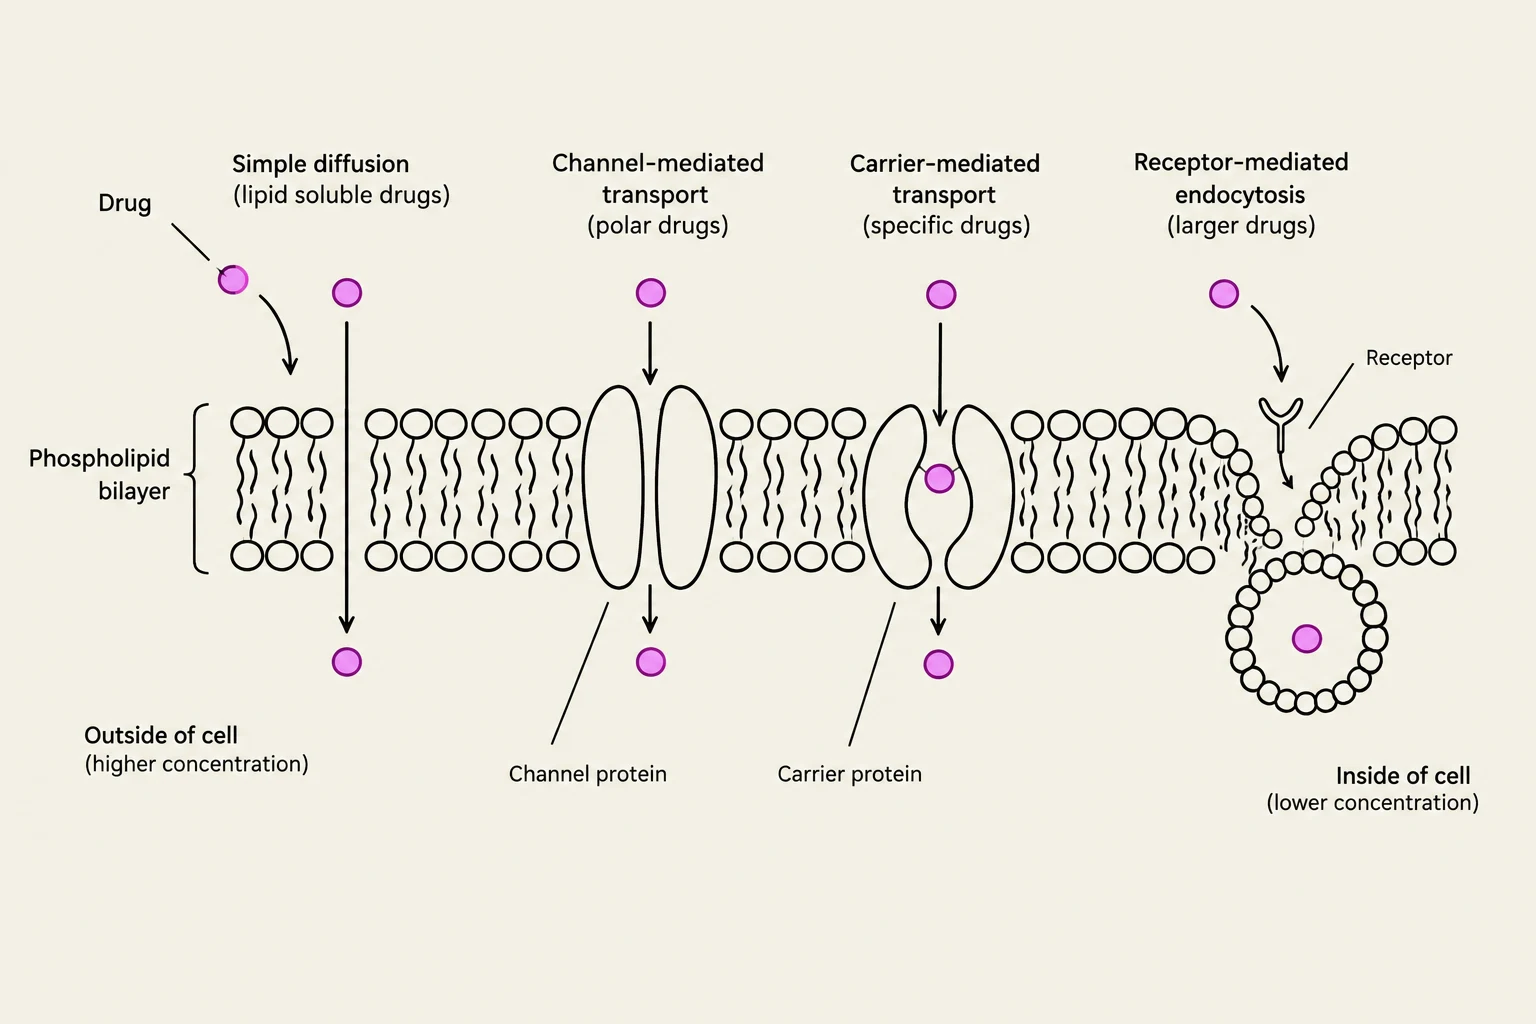
Pharmacokinetics determines how much of an administered dose reaches its site of action. It involves four stages:
Absorption: The movement of a drug from the administration site into the bloodstream. This is influenced by the route (e.g., enteral via the GI tract or parenteral via injection) and the drug's ability to cross the lipid-rich plasma membrane.
Distribution: The movement of the drug from the blood into various tissues, influenced by blood flow and plasma protein binding.
Metabolism (Biotransformation): The chemical alteration of the drug, primarily in the liver, to make it easier to excrete.
Excretion: The removal of the drug or its metabolites from the body, primarily through the kidneys.
Diagram illustrating different mechanisms of drug transport across a cell membrane, including simple diffusion, channel-mediated transport, carrier-mediated transport, and receptor-mediated endocytosis.
Pharmacodynamics: Drug Action
Drugs often act by binding to receptors on the plasma membrane. Based on their activity, drugs are classified as:
Agonist: Activates a receptor to produce a response.
Antagonist: Blocks a receptor, preventing activation.
Partial Agonist: Produces a submaximal response even when all receptors are occupied.
Clinical Application and Safety Metrics
In clinical practice, healthcare providers must manage several variables to ensure drug therapy is effective. The intensity of a drug's response is determined by administration (dosage, route, timing), pharmacokinetics, and pharmacodynamics.
Key Metrics for Dose Management
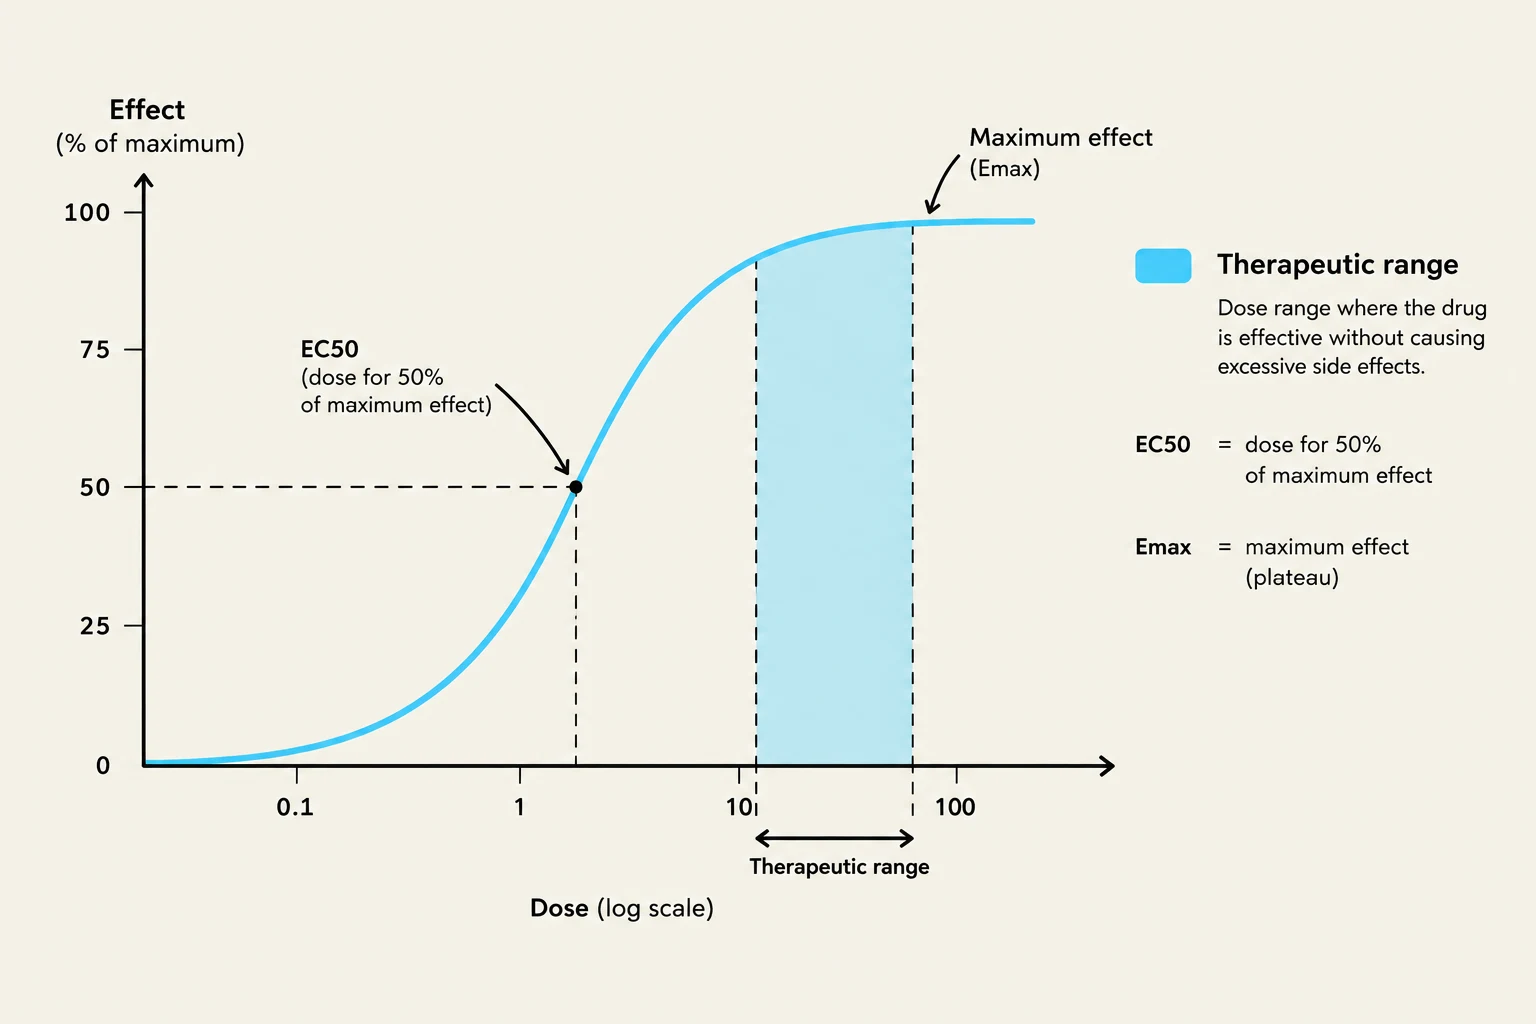
Efficacy: The maximal effect a drug can produce.
Potency: The amount of drug required to produce an effect.
Therapeutic Range: The concentration window between the minimum effective concentration and the toxic concentration.
Therapeutic Drug Index: A ratio used to quantify the safety margin of a drug.
To maintain a steady state in a patient, clinicians calculate the half-life (t1/2), the loading dose (a large initial dose to reach steady state quickly), and the maintenance dose (smaller doses to sustain the steady state).
Patient Care and the "Five Rights"
When administering medication, clinicians must adhere to the Five Rights of Drug Administration to prevent errors:
Correct order
Verify patient identification
Verify drug identification
Verify dosage calculations
Implement special handling
Furthermore, clinicians must be able to distinguish between a correct and a wrong PRN (pro re nata) order. A correct PRN order must be specific (e.g., "1 mg every 2 hours as needed"), whereas a vague order (e.g., "5 mg as needed") is incorrect because it lacks a defined frequency or limit.
Clinical Note: Managing toxicity is a critical aspect of patient care. Recognizing the early signs of toxicity can prevent irreversible injury or death.
This graph illustrates the dose-response relationship of a drug, showing how increasing the dose affects the drug's efficacy. It defines key parameters like EC50 (the dose required to achieve 50% of the maximum effect) and Emax (the maximum effect achievable). The therapeutic range, where the drug is effective without causing excessive side effects, is also highlighted.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.