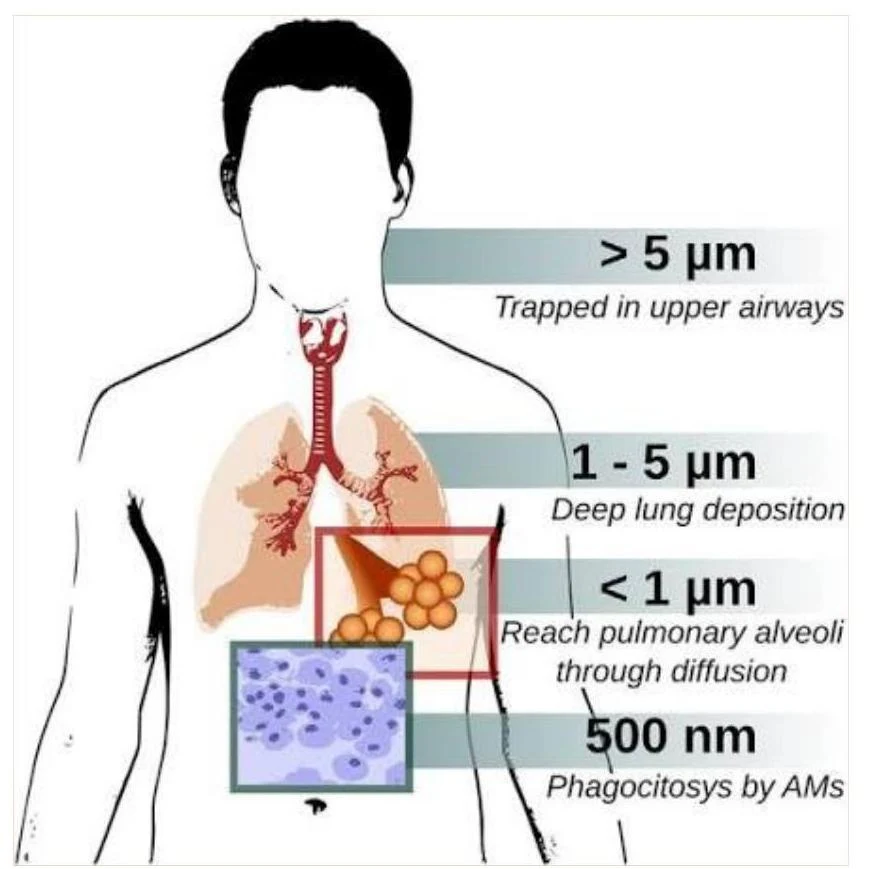
To reach the lower airways and alveolar regions for maximum therapeutic effect, a commonly cited respirable range is approximately 1–5 μm.
Exam Tip: If a question asks which mechanism is responsible for the deposition of very small particles (<1 μm), the answer is diffusion (Brownian motion). For larger particles that hit the throat, the answer is inertial impaction.
Delivery Devices and Mechanisms
Different technologies utilize different physical principles to aerosolize medication. Choosing the right device often depends on the patient's inspiratory capacity and the specific drug formulation.
Metered-Dose Inhalers (pMDI)
pMDIs are propellant-driven devices. They use a pressurized canister containing a liquid propellant (often hydrofluoroalkanes like HFA-134a) and the drug concentrate. When the actuator is pressed, the valve opens, and the propellant forces the medication through the nozzle as a high-velocity spray.
- Technique: Requires the patient to coordinate a slow, steady inhalation with the actuation of the device.
- Enhancement: Using a spacer is frequently recommended to improve coordination and ensure more drug reaches the lungs rather than the mouth.
Dry Powder Inhalers (DPI)
Unlike pMDIs, DPIs are breath-powered and do not use propellants. The medication is delivered as a dry powder that is aerosolized by the patient's own inspiratory flow.
- Technique: Patients must inhale quickly, forcefully, and deeply to disperse the powder.
- Caution: It is critical to protect the powder from moisture; patients should never exhale into the mouthpiece.
Soft-Mist Inhalers (SMI)
SMIs, such as the Respimat® system, utilize a mechanical spring rather than a propellant to generate a mist. When the button is pressed, the spring forces the liquid through a "uniblock" capillary system, where colliding jets of liquid create a slow-moving, fine mist.
- Advantages: The slow-moving mist is easier to inhale, requires less patient effort, and can reduce drug deposition in the throat, thereby decreasing side effects.
Nebulizers
Nebulizers convert liquid medication into an aerosol over a period of multiple breaths. These are often used for patients who cannot perform the forceful inhalation required for DPIs or the coordination required for pMDIs. Regular cleaning and maintenance are essential to prevent microbial contamination.
Therapeutic Applications
Inhalation aerosols are categorized by their pharmacological action and the diseases they treat:
| Drug Class | Examples | Clinical Use |
|---|
| Beta-adrenergic agonists / Sympathomimetics | Albuterol, Salmeterol, Terbutaline | Relief or prevention of bronchospasm |
| Anticholinergic bronchodilators | Ipratropium bromide | Bronchospasm relief |
| Adrenocortical (Corticosteroids) | Beclomethasone, Triamcinolone | Chronic asthma/inflammation control |
| Mast Cell Stabilizers | Cromolyn sodium | Antiallergic effects to prevent bronchospasm |
Manufacturing and Quality Control
The manufacturing of aerosols involves specialized packaging processes to ensure stability and dose accuracy.
Packaging Processes
- Cold Fill Process: The drug and propellant are placed in the container at very low temperatures (−30 to −40∘F) and then sealed.
- Pressure Fill Process: The container is filled under pressure.
Quality Control Standards
Because the efficacy of these drugs is so dependent on delivery, quality control focuses heavily on two metrics:
- Delivered-dose uniformity: Ensuring every time the device is actuated, the patient receives the same amount of medication.
- Aerodynamic particle size distribution: Characterizing the size of the particles produced. This is often measured using cascade impaction, a method that uses successive stages of collectors to separate particles by size.
Other essential tests include propellant pressure, flammability, stability, and microbial quality.
Patient Counseling Essentials
Even the most advanced delivery system will fail if the patient uses it incorrectly. Healthcare providers must provide specific instructions based on the device type:
- For pMDIs: Instruct the patient to shake the device immediately before use and to inhale slowly while actuating.
- For DPIs: Instruct the patient to exhale away from the device first, then inhale quickly and deeply.
- For SMIs: Ensure the patient understands the priming steps and to inhale slowly and deeply as the mist is released.
- For Inhaled Corticosteroids: This is a critical safety point—patients must rinse their mouth and spit after use to prevent local side effects like oral candidiasis (thrush).
Clinical Pearl: Always use the "teach-back" method. Ask the patient to demonstrate their technique to ensure they have mastered the specific requirements of their device.