Immunosuppressants and Disease-Modifying Antirheumatic Drugs (DMARDs)
An overview of immunosuppressants and DMARDs, detailing their mechanisms of action, classifications, clinical uses in managing organ rejection and autoimmune diseases like rheumatoid arthritis, and associated nursing care considerations.
The human immune system is a sophisticated defense mechanism designed to distinguish "self" from "nonself". Its primary goal is to protect the body from foreign antigens, such as bacteria and viruses, and even to identify and destroy cancer cells. However, when this system malfunctions, it can lead to two significant clinical challenges: organ rejection, where the immune system attacks a transplanted organ, and autoimmune diseases, where the immune system mistakenly attacks the body's own healthy tissues.
To manage these conditions, clinicians use immunosuppressants and Disease-Modifying Antirheumatic Drugs (DMARDs). These medications work by decreasing or preventing an immune response, effectively placing the patient in a pharmacologically immunocompromised state.
Understanding the Immune Response
To understand how these drugs work, we must first look at the two main pillars of the immune system:
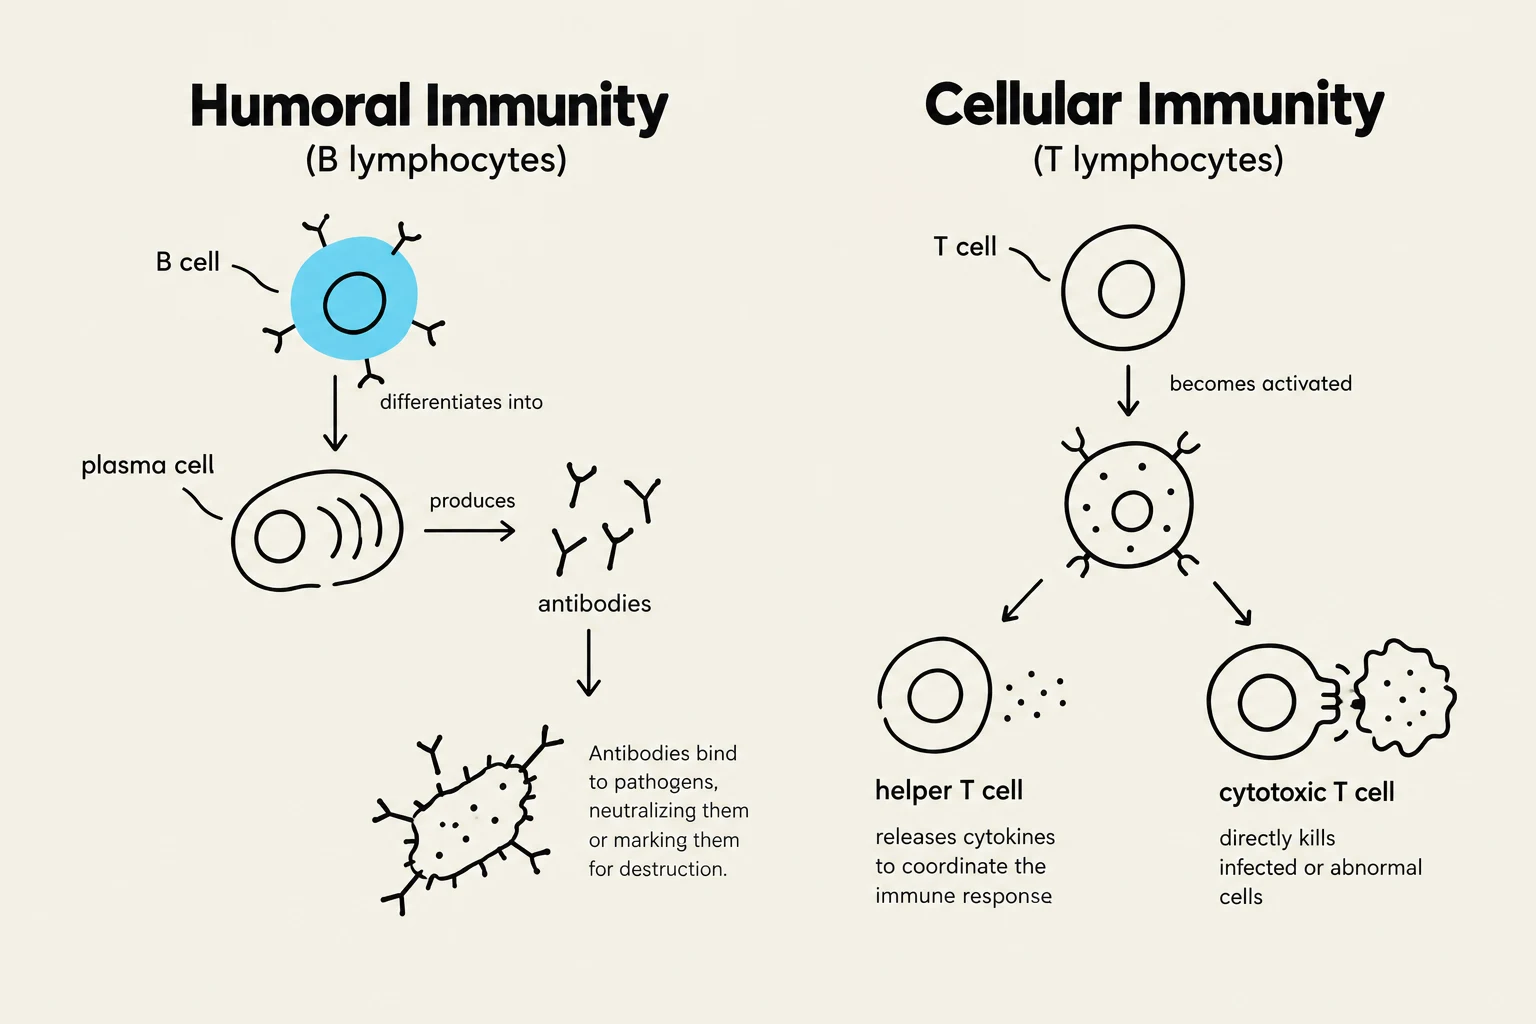
Humoral Immunity: This is mediated by B lymphocytes (B cells), which are responsible for producing antibodies to fight pathogens.
Cellular Immunity: This is mediated by T lymphocytes (T cells), which play a direct role in the immune response and are often the targets of immunosuppressive therapy.
This diagram illustrates two types of immunity: humoral immunity involving B lymphocytes and antibodies, and cellular immunity involving T lymphocytes, including helper T cells and cytotoxic T cells.
When the immune system is hyperactive or misdirected, it can cause systemic inflammation. In the context of transplantation, the immune system identifies the new organ as "nonself," triggering a rejection response. In autoimmune diseases like rheumatoid arthritis, systemic lupus erythematosus (SLE), or multiple sclerosis (MS), the immune system attacks the body's own cells.
Major Classes of Immunosuppressants
Immunosuppressants are categorized by their mechanism of action. Because they often target T-lymphocyte cell lines to prevent them from participating in an immune response, the choice of drug depends on the specific clinical goal.
Glucocorticoids
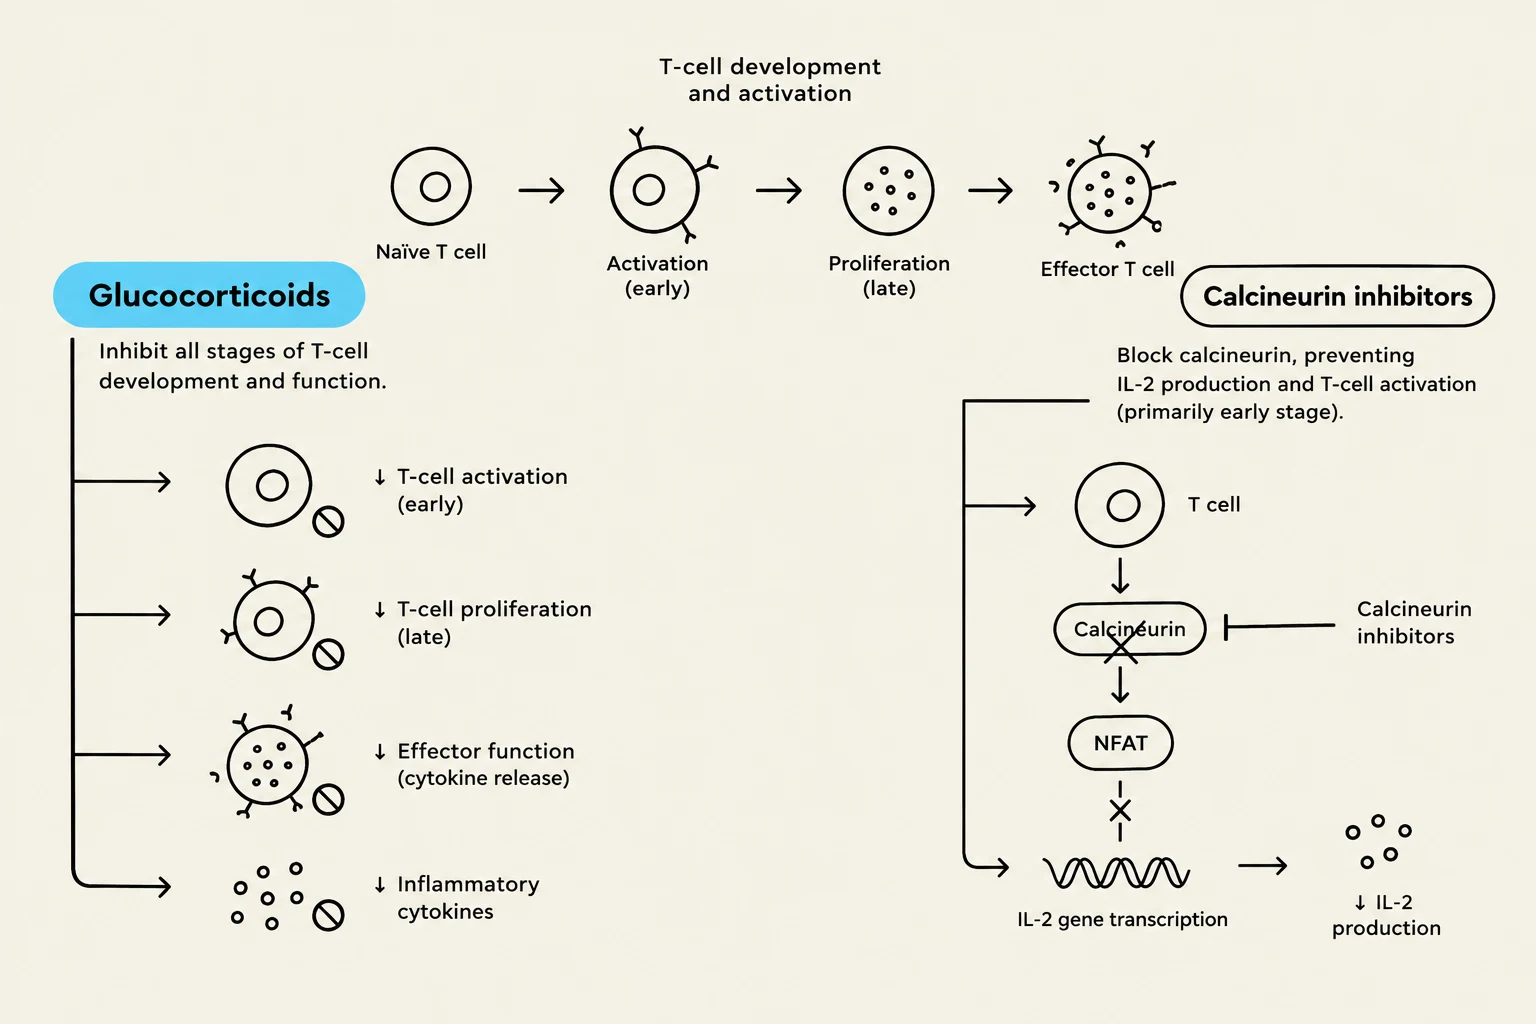
These drugs inhibit all stages of T-cell activation. They are versatile and used for induction therapy, maintenance of immunosuppression, and managing acute rejection episodes.
Calcineurin Inhibitors
These agents work by inhibiting the phosphate required for the production of interleukin-2, a key signaling molecule in the immune cascade.
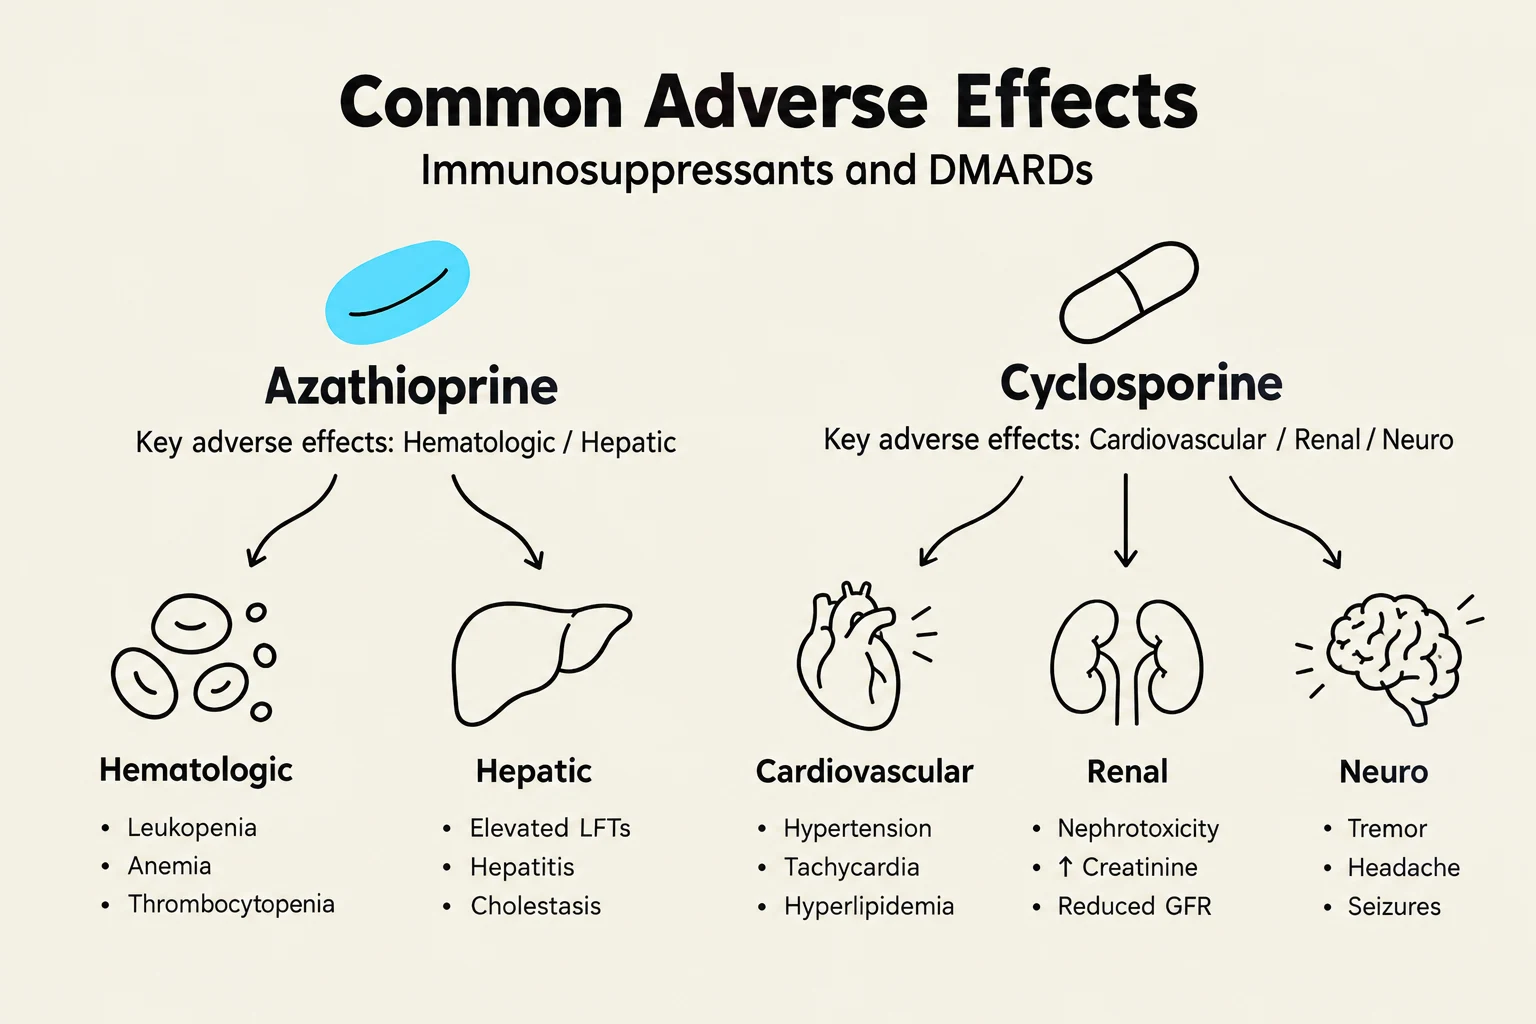
Cyclosporine (Sandimmune): Used to prevent organ rejection and treat autoimmune disorders. It carries significant black box warnings, including renal impairment (structural kidney damage), liver injury, and an increased risk of serious infections.
Tacrolimus (Prograf): Another major agent in this class used for organ transplant maintenance.
Antimetabolites
These drugs inhibit cell proliferation, preventing the rapid multiplication of immune cells.
Azathioprine (Imuran): Often used for the prophylaxis of organ rejection in conjunction with other drugs like cyclosporine. It carries a black box warning for bone marrow suppression and an increased risk of malignancies like lymphoma.
Mycophenolate mofetil (CellCept/Myfortic): Indicated for both the prevention and treatment of organ rejection. Note that CellCept and Myfortic are different dosage forms and are not interchangeable. It carries a black box warning regarding risks to pregnancy, including congenital malformations.
Biologics
Biologics are specialized drugs that inhibit specific functions, such as cytotoxic T killer cell function.
Basiliximab (Simulect): Used in transplant protocols.
Fingolimod (Gilenya): Used in the management of certain autoimmune conditions.
This diagram illustrates the mechanisms of action for Glucocorticoids and Calcineurin inhibitors on T-cell development, activation, and function, including their effects on IL-2 production and gene transcription.
Disease-Modifying Antirheumatic Drugs (DMARDs)
While immunosuppressants are often associated with transplant medicine, DMARDs are specifically used to modify the course of autoimmune diseases, most notably Rheumatoid Arthritis (RA).
Unlike NSAIDs, which provide rapid symptom relief, DMARDs have a slow onset of action, often taking several weeks to become effective. They work by inhibiting the movement of various cells into inflamed, damaged areas like joints.
Nonbiologic DMARDs
These are traditional, "slow-acting" antirheumatic drugs:
Methotrexate: An anticancer drug used at much lower doses for RA. It requires weekly dosing and can cause bone marrow suppression; patients are often advised to take folic acid supplements to mitigate this.
Hydroxychloroquine: An antimalarial drug used for RA and SLE. Because it can cause retinal damage, patients require baseline eye exams and follow-ups every six months.
Sulfasalazine and Leflunomide: Other common nonbiologic options.
Biologic DMARDs
These are more targeted therapies that include various monoclonal antibodies and receptor antagonists:
Etanercept (Enbrel): Used for RA and psoriasis. Patients must be screened for latex allergies, as some forms may contain latex. It also carries a risk of reactivating hepatitis or tuberculosis.
Other examples: Adalimumab, Infliximab, and Rituximab.
Clinical Implications and Nursing Care
Because these drugs suppress the body's ability to fight off pathogens, all patients on this therapy have a heightened susceptibility to opportunistic infections.
Exam Tip: Infection Prevention
Patients must be educated to avoid crowds and people with active infections (like colds). They should immediately report "red flag" symptoms: fever (100.5°F/38.1°C or higher), sore throat, chills, fatigue, or white patches in the mouth.
Nursing Assessment and Monitoring
Before and during therapy, healthcare providers must perform thorough assessments:
Baseline Studies: Renal, liver, and cardiovascular function; respiratory assessment; and baseline laboratory values (Hemoglobin, Hematocrit, WBC count, and Platelets).
Ongoing Monitoring: WBC counts must be monitored closely; if they drop below the normal range, the prescriber must be contacted.
Oral Health: Assess the oral cavity frequently for white patches (candidiasis), as oral antifungal drugs are often prescribed alongside immunosuppressants.
Administration Considerations
Gastrointestinal Upset: Oral immunosuppressants should be taken with food to minimize GI distress.
Drug Interactions: Many of these drugs interact with other medications and substances, such as grapefruit juice.
Special Instructions: When administering oral Cyclosporine solution, do not use Styrofoam containers, as the drug adheres to the walls of the container.
This diagram illustrates common adverse effects associated with immunosuppressants and DMARDs, specifically Azathioprine and Cyclosporine. It categorizes these effects into hematologic, hepatic, cardiovascular, renal, and neurological systems, providing examples for each.
For transplant recipients, it is vital to emphasize that immunosuppressive therapy is typically a lifelong commitment.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.