A comprehensive overview of the liver's anatomy, dual blood supply, microarchitecture, and its critical role in drug metabolism and anesthetic management. Covers Couinaud segments, hepatic arterial buffer response, acinus of Rappaport, and biliary system implications.
The liver is the body's largest solid organ, weighing approximately 1,200–1,500 g, or roughly 2% of total body weight. For the anesthesia provider, the liver represents a complex intersection of hemodynamic regulation, metabolic processing, and surgical precision. Understanding its unique dual blood supply, its functional microarchitecture, and its role in drug biotransformation is essential for managing patients undergoing hepatic resection, transplant, or even routine laparoscopic procedures.
Hepatic Anatomy and Segmental Organization
The liver is situated in the right upper quadrant, protected by ribs 7–11. While morphologic lobes (right, left, caudate, and quadrate) are traditionally defined by the falciform ligament, this division is considered surgically irrelevant. Instead, modern hepatic surgery relies on the Couinaud segments.
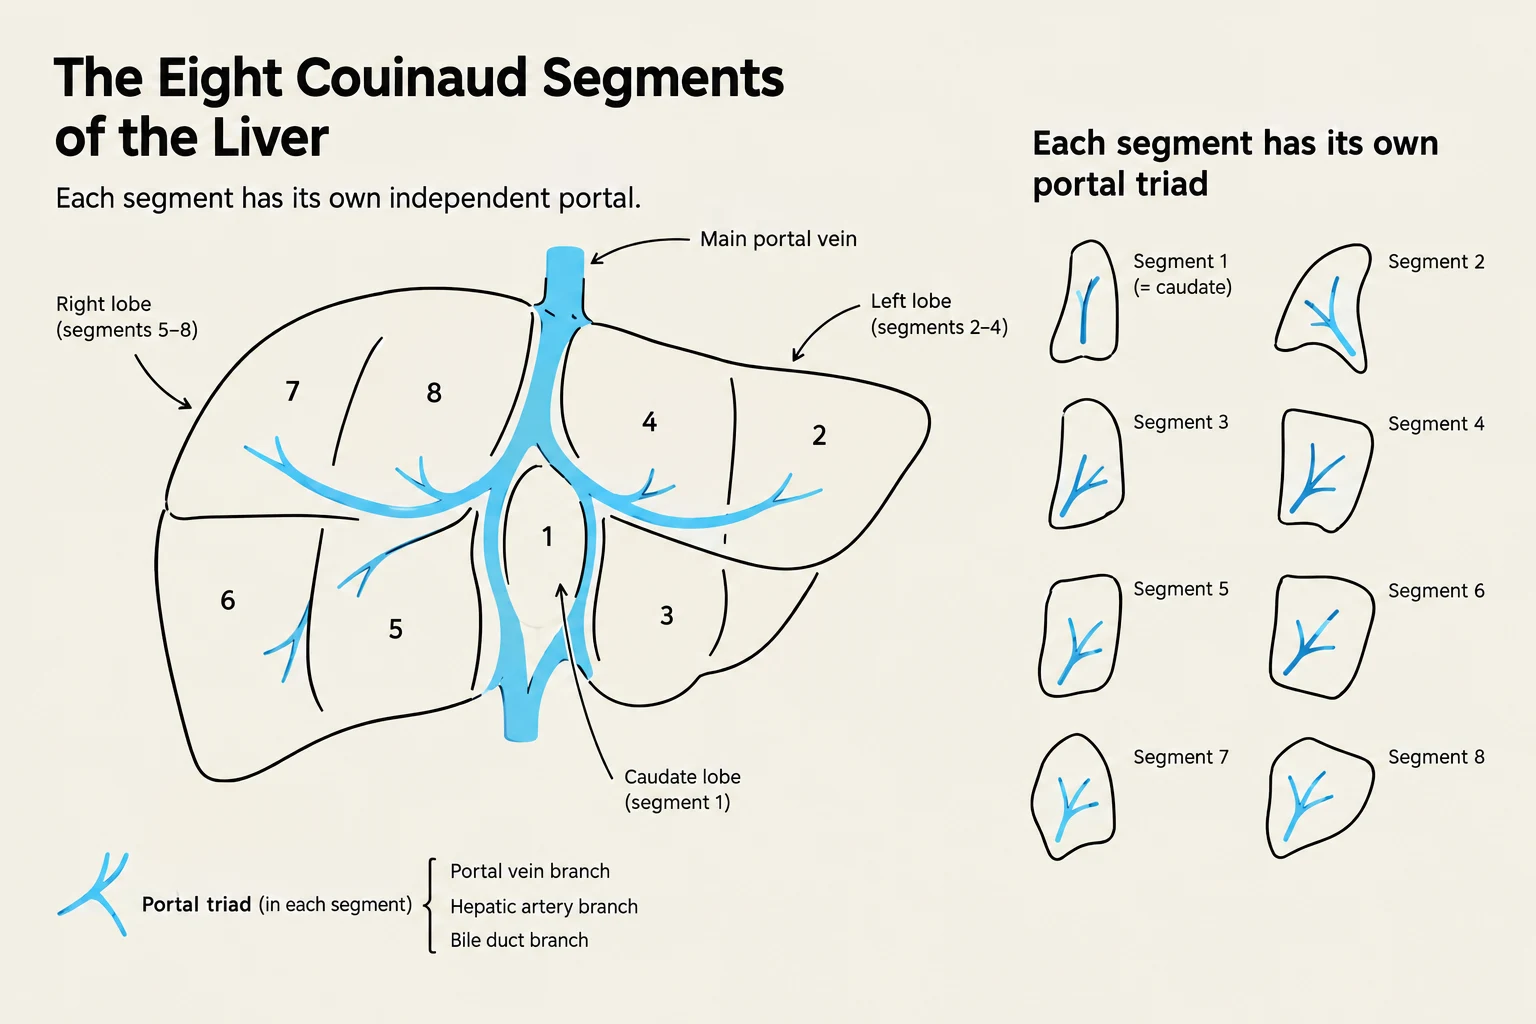
The liver is organized into eight functionally independent segments. Each segment possesses its own dedicated portal triad inflow and hepatic venous outflow, allowing a surgeon to resect a specific segment without devascularizing adjacent tissue. The segments are divided vertically by the three hepatic veins and horizontally by the right and left portal pedicles.
Diagram illustrating the eight Couinaud segments of the liver, with each segment depicted as having its own portal triad.
The numbering follows a clockwise pattern on the anterior view:
Segment I: The caudate lobe, which has independent inflow and outflow from the rest of the liver.
Segments II and III: The left lateral section.
Segment IV (a and b): The left medial section (quadrate lobe).
Segments V and VIII: The right anterior section.
Segments VI and VII: The right posterior section.
Anatomically, the liver is encased in Glisson's capsule. While the liver parenchyma itself is insensate, the capsule transmits pain via stretch. Consequently, acute congestion or a hematoma that distends the capsule will produce right upper quadrant or right shoulder-tip pain.
Dual Blood Supply and the Hepatic Arterial Buffer Response
The liver receives approximately 25% of the total cardiac output (~1,500 mL/min) through a unique dual inflow system:
Portal Vein: Provides 75% of the total blood volume but only 50% of the oxygen supply. It is formed by the splenic and superior mesenteric veins and contains partially deoxygenated blood.
Hepatic Artery: A branch of the celiac trunk that provides the remaining 25% of volume and 50% of the oxygen. Crucially, the hepatic artery is the sole blood supply to the biliary tree.
Because the liver cannot regulate portal flow (which is set by splanchnic arteriolar tone), it relies on the Hepatic Arterial Buffer Response (HABR) to maintain oxygenation. This mechanism uses "adenosine washout" to regulate inflow: when portal flow decreases, adenosine accumulates in the space of Mall, causing the hepatic artery to dilate.
Anesthesia Alert: The HABR is a fragile defense. It can be abolished by volatile anesthetics (most notably halothane), hypocapnia, hypovolemia, and increased intra-abdominal pressure from pneumoperitoneum. Any anesthetic that lowers cardiac output or raises abdominal pressure threatens hepatic oxygen delivery twice over.
Microanatomy: The Acinus of Rappaport
While the classic hexagonal lobule describes structural architecture, the acinus of Rappaport is the superior model for understanding physiology and injury. The acinus divides the parenchyma into three functional zones based on their distance from the blood inflow:
Zone 1 (Periportal): Located closest to the portal triad, this zone has the highest oxygen tension (PO2 60–70 mmHg). It is responsible for gluconeogenesis, protein synthesis, and the urea cycle. It is the most resistant to hypoxia but the first to encounter incoming toxins.
Zone 2 (Midzonal): A transitional zone with intermediate oxygen tension.
Zone 3 (Pericentral): Located around the central vein, this zone has the lowest oxygen tension (PO2 25–35 mmHg). It is the primary site for glycolysis, lipogenesis, and CYP450 biotransformation. Because it is the last to receive oxygen, it is the most susceptible to ischemic necrosis and drug-induced toxicity (e.g., acetaminophen).
At the cellular level, the liver contains Kupffer cells (resident macrophages that clear bacteria and endotoxins) and Stellate (Ito) cells (which store vitamin A and drive fibrosis when activated). The space of Disse sits between the sinusoidal endothelium and the hepatocytes, serving as the site where hepatic lymph is formed.
The Biliary System and Anesthetic Implications
Bile flows from the canaliculi through the hepatic ducts to the common bile duct, which enters the duodenum via the sphincter of Oddi. The enterohepatic circulation is highly efficient, recycling about 95% of bile salts.
Obstruction of the biliary system leads to conjugated hyperbilirubinemia and the malabsorption of fat-soluble vitamins (A, D, E, and K). A deficiency in vitamin K can lead to a vitamin K-dependent coagulopathy.
Clinical Pearl: Opioids, specifically morphine and fentanyl, can increase the pressure of the sphincter of Oddi. If biliary spasm occurs, it can be treated with glucagon (1–2 mg), naloxone, nitroglycerin, or atropine.
Summary of Hepatic Pharmacology
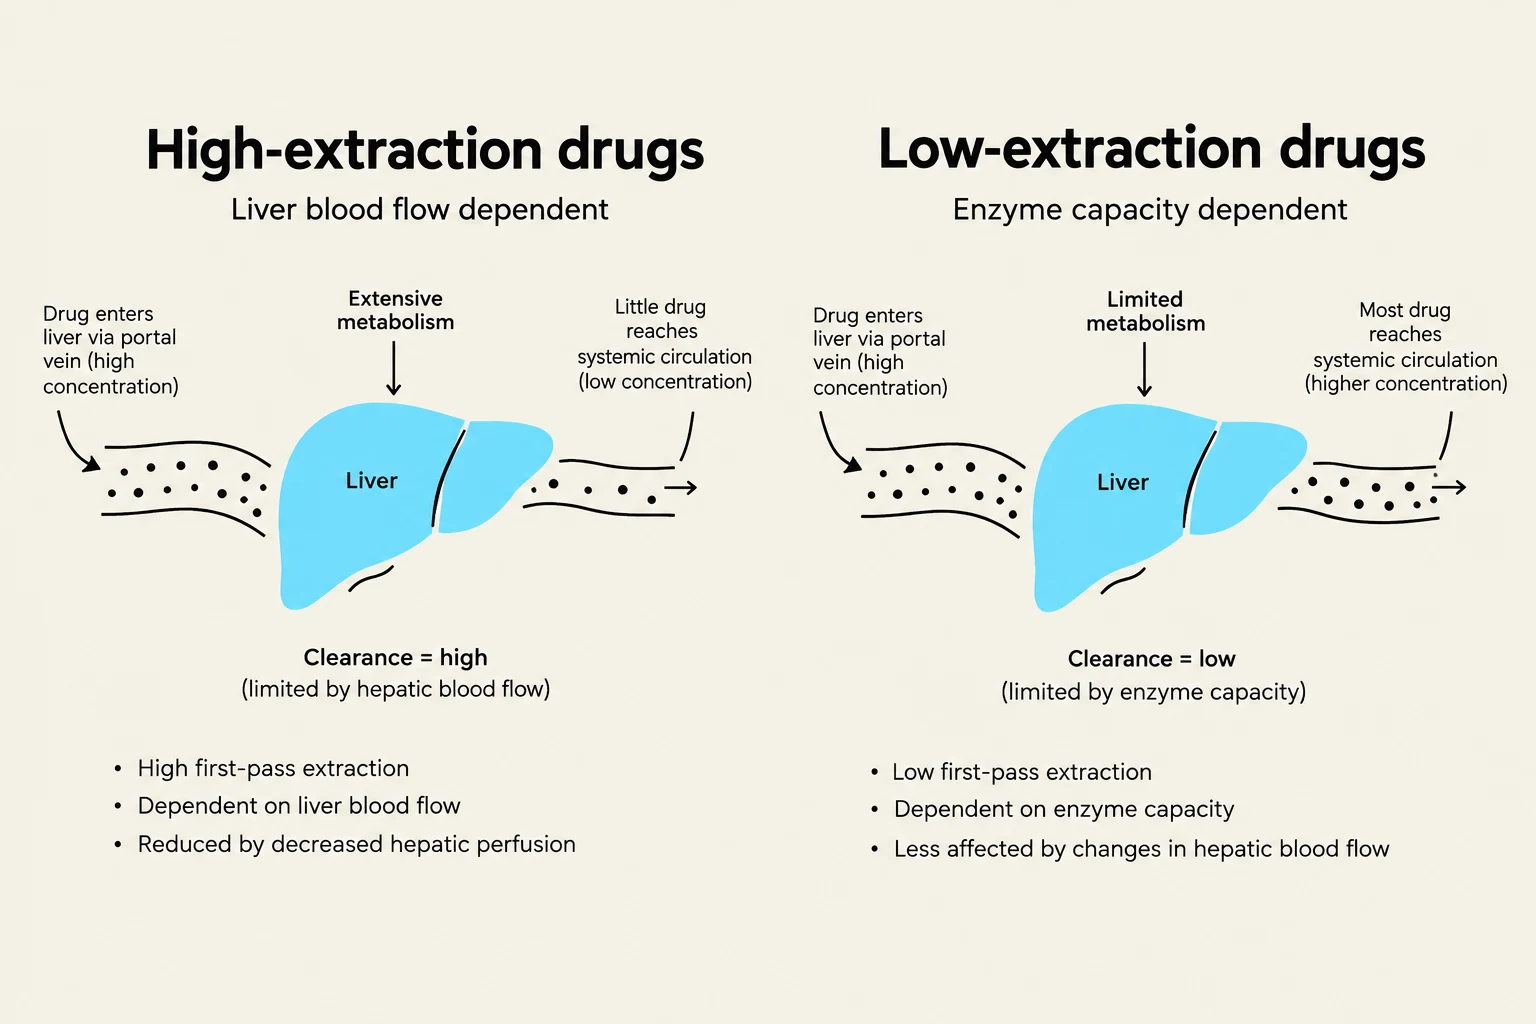
The liver's ability to clear drugs is categorized by the extraction ratio (ER):
Extraction Ratio
Mechanism
Examples
Anesthetic Sensitivity
High (> 0.7)
Flow-limited
Propofol, Fentanyl, Lidocaine
Sensitive to changes in cardiac output and hepatic blood flow.
Low (< 0.3)
Capacity-limited
Diazepam, Rocuronium, Warfarin
Sensitive to enzyme induction/inhibition and protein binding.
In patients with liver disease, several factors complicate drug administration. Hypoalbuminemia increases the free (active) fraction of highly protein-bound drugs like diazepam. Furthermore, because Phase I metabolism (oxidation via CYP450) is lost more severely than Phase II (conjugation) in cirrhosis, clinicians often prefer drugs that undergo Phase II metabolism, such as lorazepam or oxazepam.
Diagram illustrating the difference between high-extraction and low-extraction drugs based on liver blood flow and enzyme capacity.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.