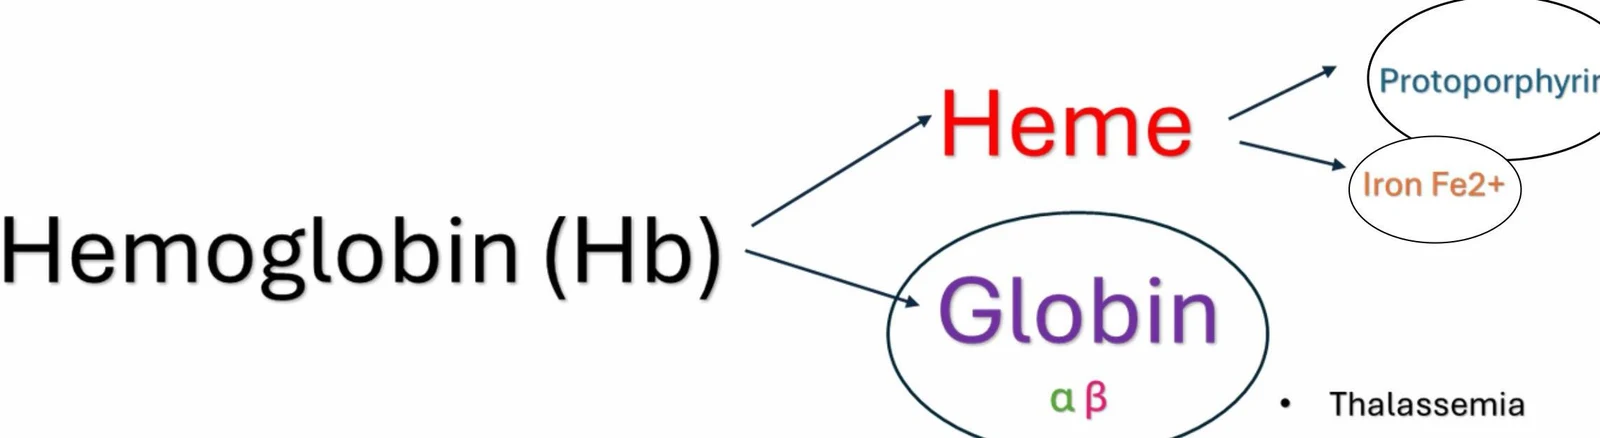
If iron is not immediately used for heme synthesis, it is diverted to storage pools:
- Ferritin: A readily available storage form found in the liver, bone marrow, and spleen.
- Hemosiderin: A less readily available storage form, visible under a microscope using Prussian blue stain.
Globin Chains and Assembly
Globin chains are proteins synthesized on ribosomes in the cytoplasm. These chains are coded by specific chromosomes: Chromosome 16 for alpha and zeta chains, and Chromosome 11 for beta, gamma, delta, and epsilon chains.
The assembly of a hemoglobin molecule follows four structural levels:
- Primary: The specific sequence of amino acids.
- Secondary: The twisting of amino acid chains into helices.
- Tertiary: The bending of these helices into a "pretzel" formation.
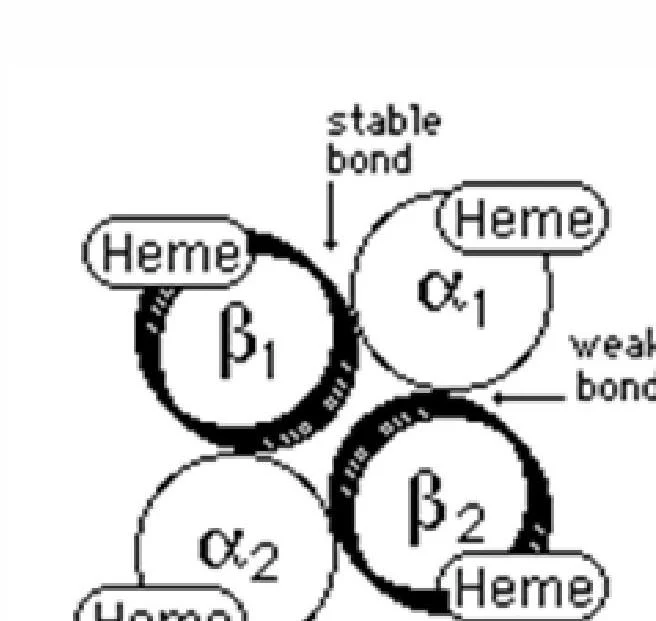
- Quaternary: The final assembly of four 3-dimensional chains into a tetramer.
In a healthy adult, the most common form is HbA1 (α2β2), which makes up over 95% of total hemoglobin.
Hemoglobinopathies: When Synthesis Goes Wrong
Errors in the genetic coding of globin chains or the substitution of amino acids result in hemoglobinopathies.
Hemoglobin S and Sickle Cell Anemia
One of the most well-known abnormalities is Hemoglobin S (HbS). This occurs due to a single amino acid substitution: at the 6th position of the beta chain, glutamic acid is replaced by valine. This structural change causes the hemoglobin to polymerize under certain conditions, distorting the red blood cell into a characteristic crescent or "sickle" shape.
Thalassemias
While hemoglobinopathies often involve qualitative changes (wrong amino acid), thalassemias involve quantitative changes—specifically, a reduced rate of synthesis of one of the globin chains (such as alpha or beta thalassemia).
Glycosylated Hemoglobin and Diabetes
Beyond genetic structural defects, hemoglobin can be altered by metabolic factors in the blood. The most clinically significant form is HbA1c (glycosylated hemoglobin).
When glucose levels in the blood are high, glucose molecules attach to the end of the valine residue on the hemoglobin molecule. This attachment is permanent for the life of the red blood cell. Consequently, HbA1c serves as a vital tool for monitoring glucose level stability in patients with diabetes mellitus.
Clinical Note: While a normal HbA1c range is typically 4%–6%, a reference interval for diabetics may be around 7.5%.
Red Blood Cell Aging and Destruction
Red blood cells have a finite lifespan. As they age, they undergo cellular senescence, characterized by a decline in cellular enzymes and decreased deformability. A key marker of an aging or dying cell is the exposure of phosphatidylserine (PS) on the outer cell membrane, which signals macrophages to consume the cell.
Extravascular Hemolysis (90% of destruction)
Most hemoglobin destruction is extravascular, meaning it is mediated by macrophages in the spleen, liver (Kupffer cells), or bone marrow.
Inside the macrophage, heme is broken down:
- Heme oxygenase converts protoporphyrin into biliverdin.
- Biliverdin is reduced to bilirubin (a yellow molecule).
- Unconjugated (indirect) bilirubin is hydrophobic and must bind to albumin to travel to the liver.
- In the liver, it is conjugated with glucuronic acid to become conjugated (direct) bilirubin, which is water-soluble and can be excreted.
Intravascular Hemolysis (10% of destruction)
In intravascular hemolysis, red blood cells rupture directly within the blood vessels. This releases "free" hemoglobin into the plasma, which can cause oxidative damage to tissues, particularly the kidneys.
To prevent this damage, the body utilizes a salvage system:
- Haptoglobin: The first line of defense. It binds to free hemoglobin dimers, forming a complex that is then cleared by macrophages. A decreased haptoglobin level is a hallmark indicator of intravascular hemolysis.
- Hemopexin: If hemoglobin becomes oxidized into methemoglobin, hemopexin binds to the metheme to salvage the iron.
- Methemalbumin: If these systems are saturated, metheme binds to albumin as a temporary carrier until it can be processed by the liver.
Exam Tip: If a patient presents with low haptoglobin, high LDH, and the presence of schistocytes (fragmented cells), suspect intravascular hemolysis.
| Feature | Extravascular Hemolysis | Intravascular Hemolysis |
|---|
| Primary Site | Spleen, Liver, Bone Marrow | Within blood vessels |
| Haptoglobin | Normal or Increased | Decreased |
| RBC Morphology | Spherocytes often present | Schistocytes (fragments) often present |
| Urine Findings | Normal | Hemoglobinuria / Methemoglobinuria |