Headache Differentials: SNOOP Mnemonic and Primary vs. Secondary Headaches
This guide explains how to differentiate between primary and secondary headaches using the SNOOP mnemonic to identify red flags. It covers common primary headaches like migraine, cluster, and tension-type headaches, as well as critical secondary differentials such as Giant Cell Arteritis (GCA).
Headache is one of the most common presentations in clinical practice, ranging from the benign nuisance of a tension headache to the life-threatening emergency of a subarachnoid hemorrhage. For a clinician, the primary challenge is not merely identifying the type of pain, but more importantly, distinguishing between primary headaches (where the headache itself is the disease) and secondary headaches (where the headache is a symptom of an underlying pathology).
To navigate this complexity, clinicians rely on structured history-taking and specific mnemonic tools to identify "red flags" that necessitate urgent neuroimaging or intervention.
The SNOOP Mnemonic: Identifying Red Flags
The SNOOP mnemonic for identifying secondary headache red flags.
When a patient presents with a headache, your first priority is to rule out secondary causes. The SNOOP mnemonic is a widely recognized tool used to screen for clinical features that suggest a secondary headache caused by serious underlying conditions like tumors, infections, or vascular accidents.
Letter
Feature
Potential Underlying Cause
S
Systemic symptoms/signs
Fever, weight loss, or malignancy
N
Neurological symptoms
Confusion, seizures, focal deficits, or papilledema
New headaches in patients >50 (suggests GCA or tumor)
P
Pattern change/Progression
Change in frequency, severity, or headache character
Exam Tip: If a patient describes the "worst headache of my life" that reached peak intensity within seconds, this is a classic "Thunderclap" onset. You must prioritize ruling out a subarachnoid hemorrhage immediately.
Differentiating Primary Headaches
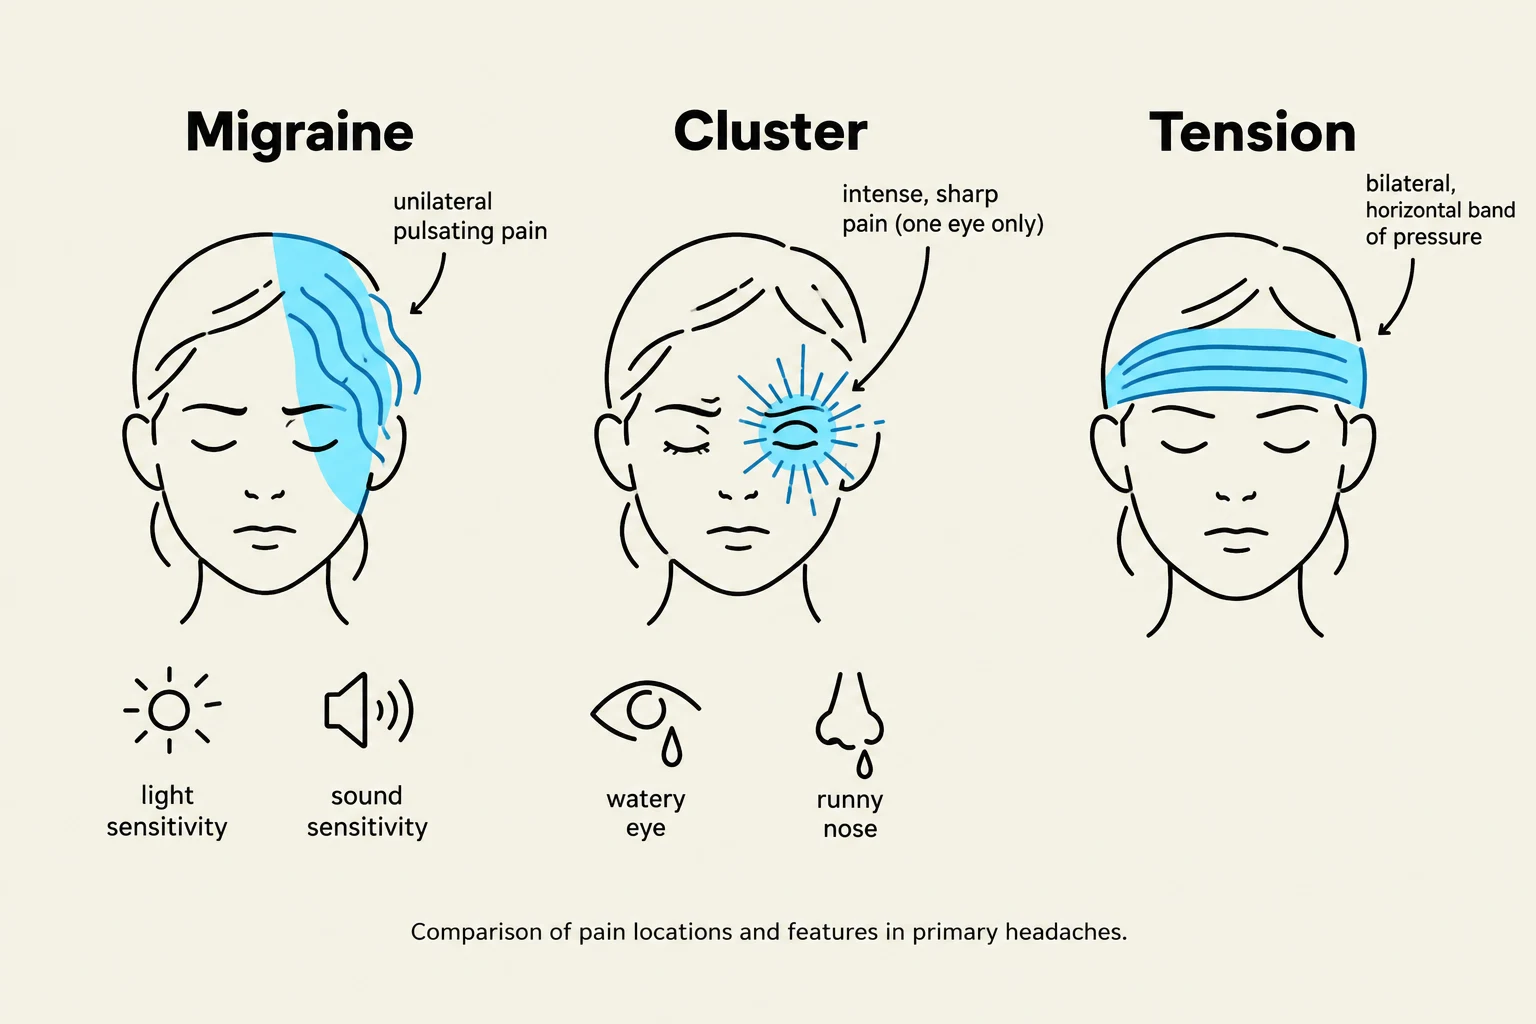
Comparison of pain locations and features in primary headaches.
Once red flags are addressed, you can begin to categorize the headache into primary types. The three most common differentials encountered in clinical practice are Migraine, Cluster Headache, and Tension-type Headache.
1. Migraine
Migraine is a neurovascular disorder characterized by moderate-to-severe pulsating pain. Key features include:
Unilateral location: Often affects one side of the head.
Associated symptoms: Nausea, vomiting, photophobia (sensitivity to light), and phonophobia (sensitivity to sound).
Aura: About 25% of patients experience visual or sensory disturbances (auras) prior to the pain.
Duration: Typically lasts 4 to 72 hours if untreated.
2. Cluster Headache
Cluster headaches are part of the "Trigeminal Autonomic Cephalalgias" group. They are significantly more intense than migraines and follow a distinct pattern:
Unilateral and Periorbital: The pain is strictly one-sided and centered around the eye.
Autonomic symptoms: Unlike migraines, cluster headaches are accompanied by ipsilateral (same side) autonomic signs such as lacrimation (tearing), rhinorrhea (runny nose), or ptosis (drooping eyelid).
Circadian rhythm: They often occur in "clusters" of attacks at the same time of day, frequently waking the patient from sleep.
3. Tension-Type Headache
The most common primary headache, usually characterized by a "band-like" pressure around the head. It is typically bilateral and lacks the debilitating nausea or autonomic symptoms seen in the other two types.
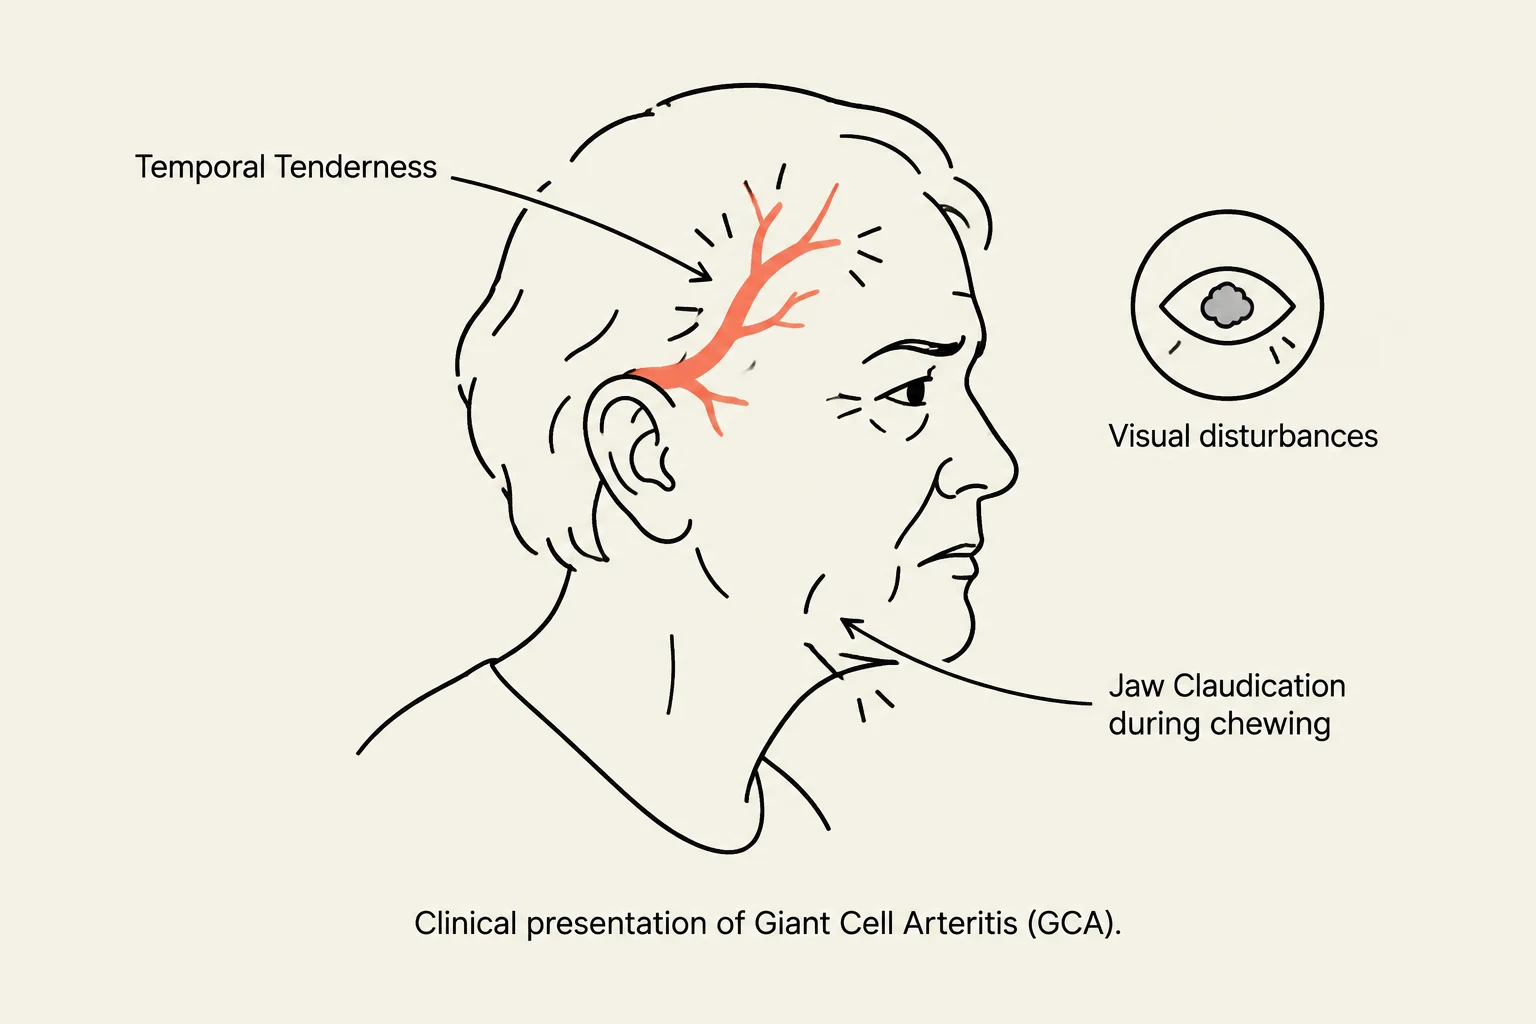
Clinical presentation of Giant Cell Arteritis (GCA), including temporal tenderness, visual disturbances, and jaw claudication during chewing.
While migraine and cluster headaches are primary, Giant Cell Arteritis (GCA), also known as temporal arteritis, is a critical secondary headache differential that must be identified, especially in older populations.
GCA is an inflammation of the lining of the arteries, most commonly those in the head. It is a medical emergency because it can lead to permanent blindness if not treated promptly with corticosteroids.
Clinical Clues for GCA:
Age: Almost exclusively seen in patients over 50.
Temporal Tenderness: Pain or tenderness when touching the temples.
Jaw Claudication: Pain in the jaw when chewing food.
Visual Disturbances: Sudden blurring or loss of vision.
Systemic signs: Fever, malaise, or an elevated ESR (Erythrocyte Sedimentation Rate) in blood tests.
Summary Table for Rapid Differential
To assist in your clinical reasoning, use the following comparison:
Feature
Migraine
Cluster
GCA
Pain Quality
Pulsating/Throbbing
Sharp/Stabbing/Boring
Constant/Aching
Location
Unilateral (usually)
Periorbital (strictly)
Temporal/Temple
Autonomic Signs
No
Yes (Tearing, Red eye)
No
Nausea/Vomiting
Common
Rare
No
Key Risk Factor
Family history/Hormones
Male gender/Smoking
Age > 50
Clinical Pearl: Always ask about "new" headaches in an elderly patient. A new-onset headache in a 65-year-old is GCA or malignancy until proven otherwise.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.