An overview of head and neck cancers, including their pathophysiology, risk factors, clinical manifestations, diagnostic studies, staging, and interprofessional care. It also covers postoperative management, complications, communication and rehabilitation, and psychosocial aspects.
Head and neck cancers represent a diverse group of malignancies that primarily involve the squamous cells found in the mucosal surfaces of the upper respiratory and digestive tracts. These cancers can affect various structures, including the nasal cavity, paranasal sinuses, nasopharynx, oropharynx, larynx, oral cavity, and salivary glands. Because these structures are vital for breathing, swallowing, and communicating, the management of these cancers requires a highly coordinated, interprofessional approach to address both the physical disease and the profound psychosocial impacts on the patient.
Pathophysiology and Risk Factors
The most common type of head and neck cancer is squamous cell carcinoma. This malignancy arises from the squamous cells that line the mucosal surfaces of the head and neck.
Understanding the etiology is critical for prevention and patient education. Smoking is a primary driver, accounting for approximately 85% of cases. Other significant risk factors include:
Human Papillomavirus (HPV)
Excessive alcohol consumption
Exposure to sun, asbestos, or industrial carcinogens
Marijuana use and radiation to the head and neck
Poor oral hygiene
During physical assessments, clinicians look for specific precancerous or early signs of malignancy in the oral mucosa, such as leukoplakia (white patches) or erythroplakia (red patches).
Diagrams illustrating the anatomy of the head and neck, highlighting structures at risk for squamous cell carcinoma.
Clinical Manifestations and Diagnosis
Symptoms of head and neck cancer vary significantly depending on the anatomical location of the tumor.
Pharyngeal involvement: Patients may report a lump in the throat or a persistent sore throat.
Laryngeal involvement: Common signs include a change in voice or hoarseness lasting longer than two weeks.
General/Late signs: Ear pain, ringing in the ears (tinnitus), swelling or a lump in the neck, constant cough, or coughing up blood. As the disease progresses, patients may experience unintentional weight loss, difficulty chewing, swallowing, or moving the tongue/jaw, and potentially life-threatening airway obstruction.
Diagnostic Studies
To confirm a diagnosis, healthcare providers utilize several diagnostic tools:
Physical Assessment: A thorough inspection of the ears, nose, throat, mouth, and neck to identify thickening of the mucosa, lymph nodes, or suspicious patches.
Endoscopic Inspection:Pharyngoscopy and laryngoscopy are used for direct visual inspection and to obtain biopsies for definitive diagnosis.
Imaging: CT scans, MRI, and PET scans are utilized to determine the extent of the disease.
Staging and Treatment Modalities
Once diagnosed, the cancer is staged using the TNM system. This system categorizes the cancer based on the size of the tumor (T), the number and location of involved lymph nodes (N), and the extent of distant metastasis (M).
Interprofessional Care
Treatment is highly individualized and often involves a combination of therapies:
Surgery: Often the first-line treatment, surgery may require reconstruction to restore both structure and function.
Radiation Therapy: Can be delivered via external beams or internal implants. In early-stage cancers, radiation is often used to preserve the patient's voice.
Chemotherapy and Targeted Therapy: These are typically reserved for more advanced stages (Stages III or IV) and are often used in combination with radiation.
Nutrition Therapy: Because surgery and radiation can impair swallowing, patients may require gastrostomy tubes and enteral feedings.
Nursing Alert: Risk for Aspiration
Patients undergoing treatment for head and neck cancer are at a significantly increased risk for aspiration due to impaired swallowing mechanisms. Continuous monitoring of nutritional tolerance and the risk of aspiration is a priority.
Postoperative Management and Complications
Surgical interventions, particularly those involving the neck and airway, require intensive postoperative monitoring.
Surgical Reconstruction and Skin Flaps
When large sections of tissue are removed, surgeons may use skin flaps for reconstruction. These flaps require meticulous nursing care:
They are typically not covered with dressings to allow for better visualization.
Nurses must avoid applying excess pressure to the tissue.
Hourly checks are mandatory, and a Doppler ultrasound may be used to verify the presence of a pulse in the flap.
Airway and Stoma Care
For patients with a tracheostomy, maintaining a patent airway is the highest priority.
Tracheostomy care: Includes frequent suctioning and cleaning the stoma daily.
Patient Education: Patients should be taught to cover the stoma when coughing or during activities that might cause inhalation of foreign materials. They should also use a plastic collar when showering and avoid swimming.
Radiation Side Effects
Radiation therapy introduces specific physiological challenges:
Xerostomia: Chronic dry mouth due to salivary gland damage.
Oral Mucositis: Inflammation and ulceration of the oral mucosa.
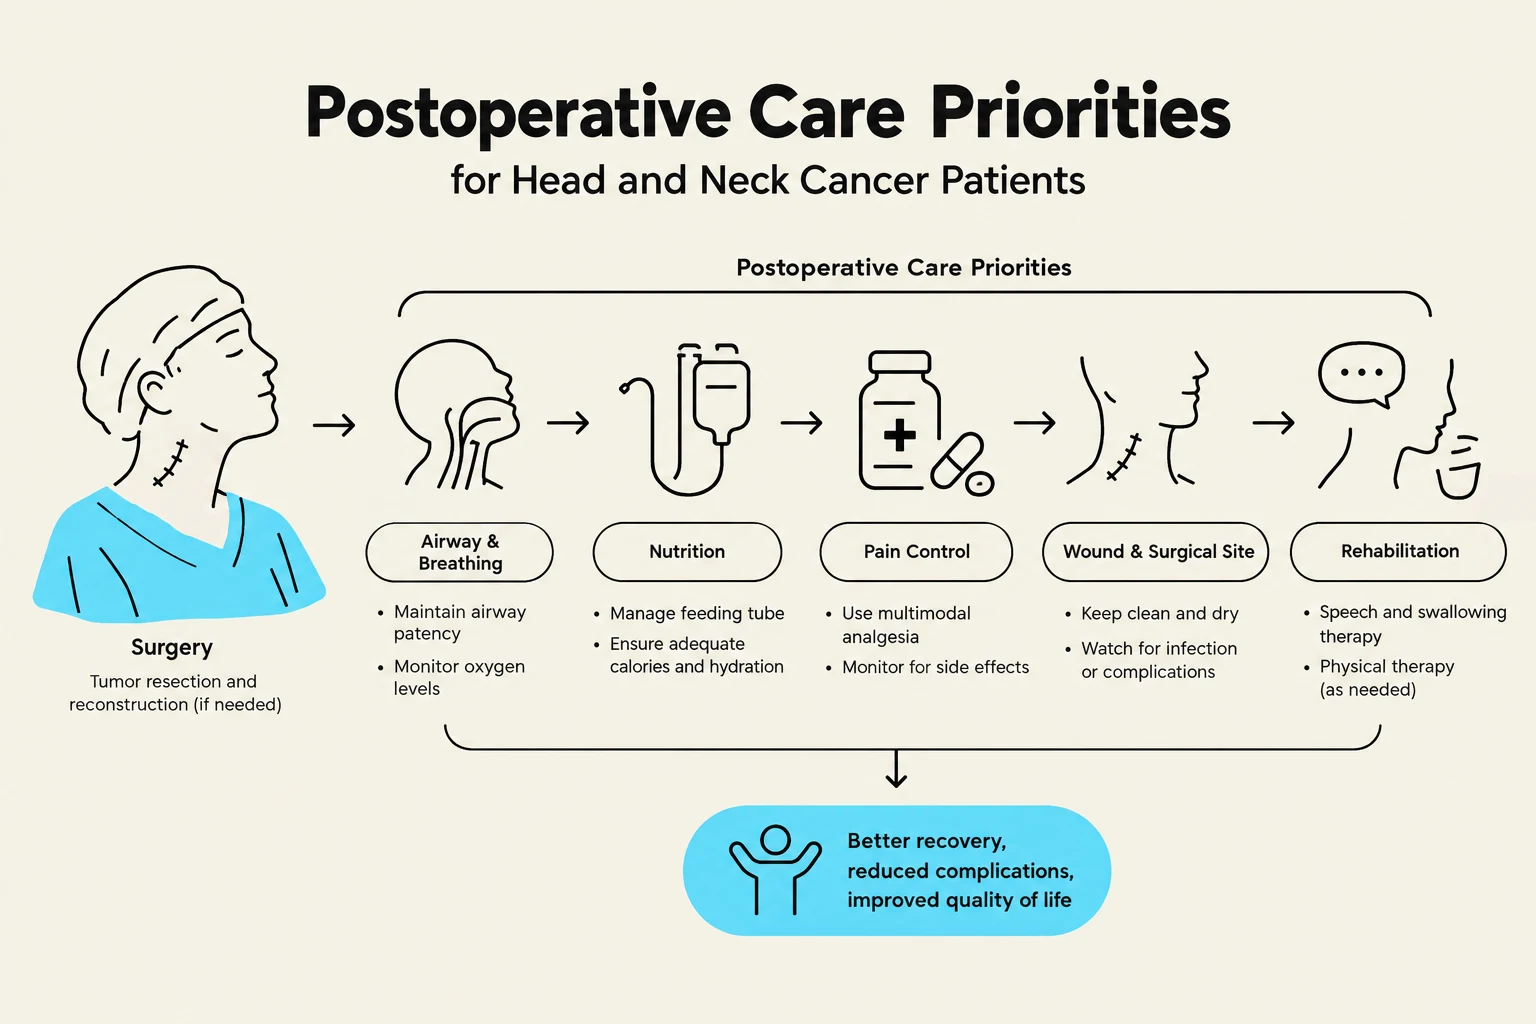
This diagram outlines the postoperative care priorities for head and neck cancer patients, including airway and breathing management, nutrition, pain control, wound care, and rehabilitation, all contributing to better recovery.
Communication and Rehabilitation
Loss of voice or altered speech is a common and distressing consequence of head and neck cancer treatment. Speech therapy plays a vital role in both preoperative planning and postoperative restoration.
Patients may utilize several methods to regain communication:
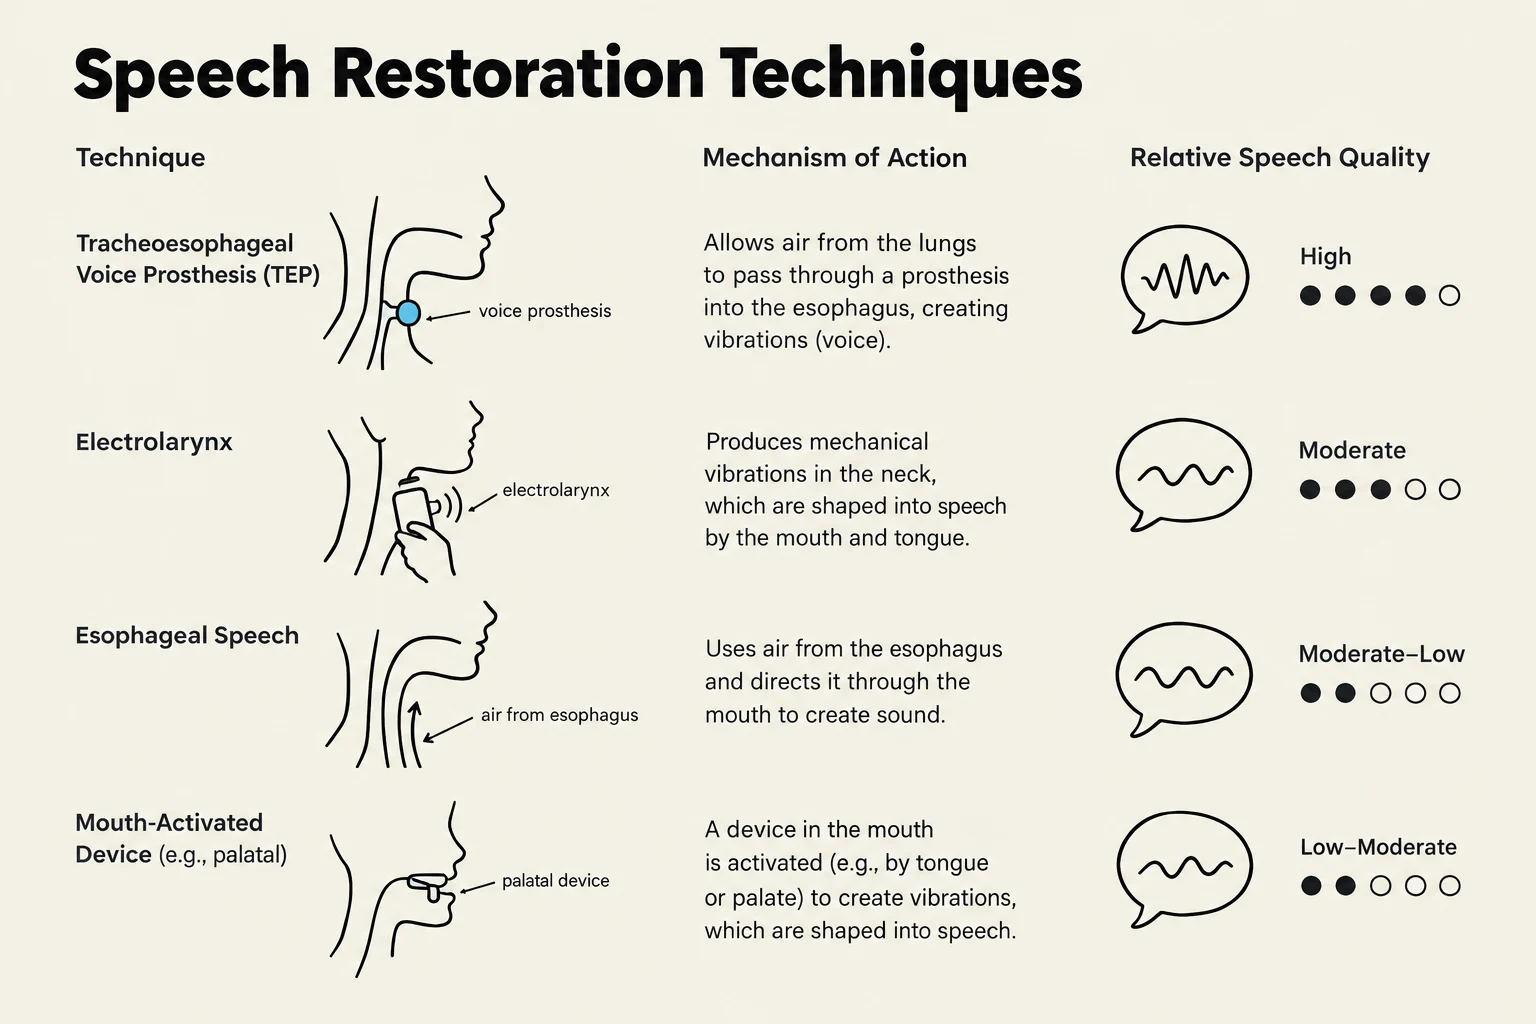
Electrolarynx: A hand-held, battery-powered device that uses sound waves to create speech; the resulting sound has a mechanical quality.
Transesophageal Puncture (TEP): A fistula is created in the tracheoesophageal wall. The patient manually blocks the stoma with a finger to speak, which provides the best speech quality.
Esophageal Speech: A technique that can be difficult to learn and often results in reduced voice quality.
This chart illustrates four speech restoration techniques: Tracheoesophageal Voice Prosthesis (TEP), Electrolarynx, Esophageal Speech, and Mouth-Activated Device. It details the mechanism of action for each and provides a relative speech quality rating.
Psychosocial and Ambulatory Care
The impact of head and neck cancer extends far beyond physical symptoms. Patients often face significant challenges regarding body image, sexuality, and the potential loss of employment.
Discharge Planning and Safety
As patients transition to home care, several safety measures are essential:
Medic Alert: Patients should wear a Medic Alert tag identifying them as a "neck breather".
Home Safety: Because cancer or treatment may result in a loss of smell, patients must be educated on the importance of having working smoke and carbon monoxide detectors.
Continued Support: Encouraging the use of support groups and coordinating with dieticians can help patients manage long-term nutritional and emotional needs.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.