An overview of key genes that significantly impact clinical medicine, including those related to cancer, cardiovascular and metabolic disorders, monogenic diseases, pharmacogenomics, and gene therapy.
In the vast landscape of the human genome, a small number of high-impact genes account for a disproportionate share of what clinicians diagnose, screen for, and treat. While the genome contains tens of thousands of genes, understanding a select group of "driver" genes is fundamental to modern practice. These genes are not merely biological curiosities; they are the foundation of precision oncology, the targets of life-saving gene therapies, and the guides for personalized drug dosing.
By categorizing these genes into functional groups—such as tumor suppressors, oncogenes, and pharmacogenomic drivers—we can better understand how a single molecular error can manifest as a systemic disease or, conversely, how a specific genetic profile can dictate a patient's response to a drug.
Tumor Suppressor Genes: The Biological Brakes
Tumor suppressor genes function as the cell's natural defense system, acting as "brakes" to repair DNA damage or restrain uncontrolled cell division. In a healthy cell, these genes ensure genomic stability. However, when both copies of a tumor suppressor gene are lost or inactivated, the "brakes" fail, allowing for the rapid, uncontrolled proliferation characteristic of malignancy.
DNA Repair and the BRCA Pathway
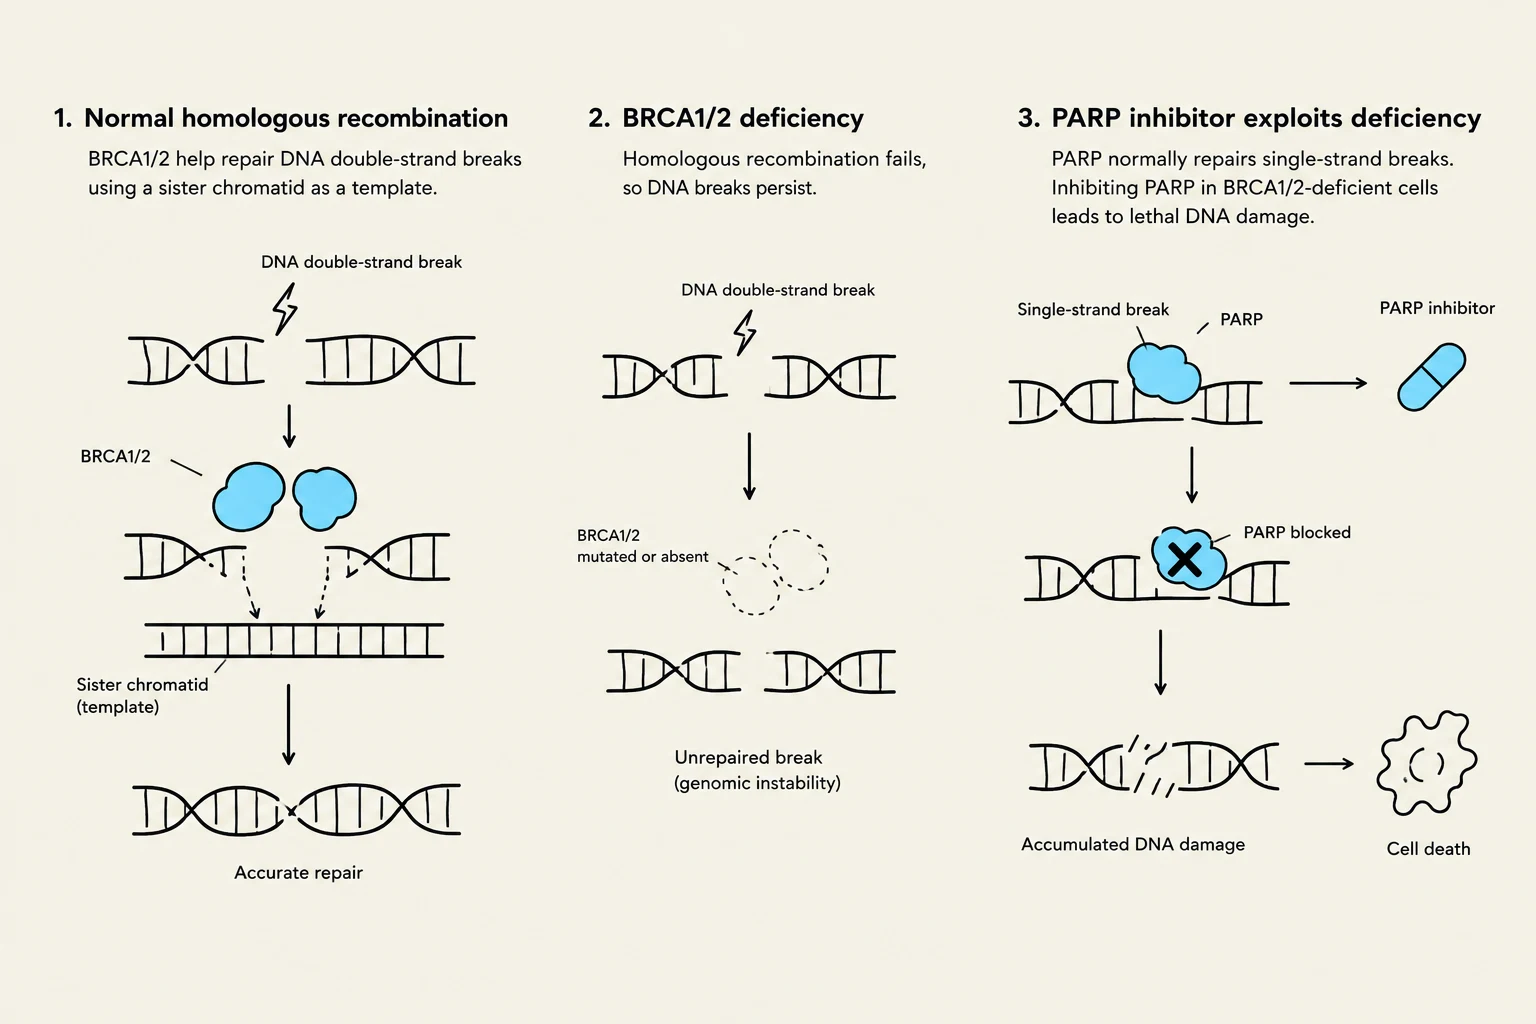
Two of the most clinically significant tumor suppressors are BRCA1 and BRCA2. These genes are essential for repairing double-strand DNA breaks through a high-fidelity process known as homologous recombination.
Mutations in these genes significantly increase the lifetime risk of breast and ovarian cancers, as well as prostate and pancreatic cancers. Beyond diagnosis, these mutations are predictive of treatment success: patients with BRCA deficiencies often respond exceptionally well to PARP inhibitors, which selectively target and kill cells that lack these repair mechanisms.
This diagram illustrates three scenarios related to DNA repair mechanisms: normal homologous recombination, BRCA1/2 deficiency, and the exploitation of this deficiency by PARP inhibitors, leading to cell death.
The Guardians and Regulators of the Cell Cycle
Other tumor suppressors manage the cell cycle through different regulatory mechanisms:
TP53: Often called the "guardian of the genome," TP53 monitors DNA integrity. If damage is detected, it either halts the cell cycle to allow for repair or triggers apoptosis (programmed cell death) if the damage is irreparable. It is the most frequently mutated gene across all human cancers. Inherited mutations in TP53 lead to Li-Fraumeni syndrome, a condition characterized by a high predisposition to multiple types of cancer.
APC: This gene regulates intestinal cell growth by degrading the protein beta-catenin. Inherited loss of APC leads to familial adenomatous polyposis (FAP), a condition where hundreds to thousands of colon polyps develop during adolescence, making colorectal cancer almost certain without preventive surgery.
RB1: As the first identified tumor suppressor, RB1 blocks progression through the cell cycle. Its inactivation is the cause of retinoblastoma, a cancer of the eye in children.
MLH1: This gene is a vital component of the DNA mismatch-repair pathway. Mutations in MLH1 (and related genes) cause Lynch syndrome, the most common inherited colorectal cancer syndrome. Interestingly, tumors with these mismatch-repair deficiencies are often highly responsive to immune checkpoint inhibitors.
Exam Tip: Remember the "Two-Hit Hypothesis" in the context of tumor suppressors like RB1 and APC. For a tumor to develop, both alleles of the gene must typically be inactivated—one through inheritance and one through a somatic mutation.
Oncogenes and Targeted Cancer Therapy
While tumor suppressors are "brakes" that need to be fixed, oncogenes are more like "accelerators" that have become stuck in the "ON" position. When these genes are inappropriately activated, they drive continuous cell growth and survival.
Modern oncology has shifted from broad-spectrum chemotherapy toward targeted cancer therapy, where drugs are designed to specifically inhibit the activity of these activated oncogenes.
Key Drivers in Clinical Practice
EGFR: This growth-factor receptor drives many cases of non-small-cell lung cancer. Because of this, EGFR testing is now a clinical standard; identifying these mutations allows clinicians to prescribe specific drugs like erlotinib or osimertinib.
ERBB2 (HER2): Overexpressed in 15–20% of breast cancers, HER2 drives aggressive tumor growth. The development of the antibody trastuzumab (Herceptin) transformed HER2-positive breast cancer from a poor-prognosis disease into one of the most treatable forms of cancer.
KRAS: For a long time, KRAS was considered "undruggable" because its protein structure lacked a clear binding pocket for drugs. However, the recent approval of drugs like sotorasib and adagrasib, which target the KRAS-G12C mutation, has proven that even the most difficult oncogenic drivers can eventually be targeted.
This diagram illustrates two pathways leading to cancer: loss of tumor suppressor gene function and gain of oncogene function, both resulting in uncontrolled cell growth.
Cardiovascular, Metabolic, and Monogenic Disorders
Beyond cancer, genetics plays a massive role in chronic disease and classic Mendelian (monogenic) disorders.
Cardiovascular and Metabolic Risk
Genetic variations can dictate a patient's baseline risk for heart disease. For example, LDLR mutations cause familial hypercholesterolemia, leading to extremely high LDL ("bad") cholesterol from birth. Conversely, variations in PCSK9 can be used to create new treatments; because PCSK9 normally degrades LDL receptors, inhibiting it can lower cholesterol levels significantly.
Other critical genes include:
APOE: The APOE4 variant is the strongest common genetic risk factor for late-onset Alzheimer's disease.
F5 (Factor V Leiden): This is the most common inherited clotting disorder, increasing the risk of deep vein thrombosis.
Classic Monogenic Disorders
These are diseases caused by a single mutated gene, following predictable inheritance patterns:
CFTR: Mutations cause cystic fibrosis, affecting salt and water movement across membranes.
HBB: Mutations cause sickle cell disease and beta-thalassemia. This gene is also the target of the first approved CRISPR-based gene-editing therapy.
DMD: Mutations in this (the largest human gene) cause Duchenne muscular dystrophy.
FMR1 & HTT: These are classic examples of "trinucleotide repeat" diseases, causing Fragile X syndrome and Huntington's disease, respectively.
Pharmacogenomics and the Future of Gene Therapy
The final frontier of clinical genetics lies in how we prescribe drugs and how we fix broken genes.
Pharmacogenomics: Tailoring the Dose
CYP2D6 is a quintessential pharmacogenomic gene. It encodes a liver enzyme responsible for metabolizing approximately 20% of commonly prescribed drugs, including many antidepressants and opioids. Depending on a patient's genotype, they may be classified as:
Poor metabolizers: Risk of drug toxicity due to accumulation.
Ultra-rapid metabolizers: Risk of treatment failure (or toxicity if the drug is a prodrug, like codeine).
Gene Therapy: The Ultimate Cure
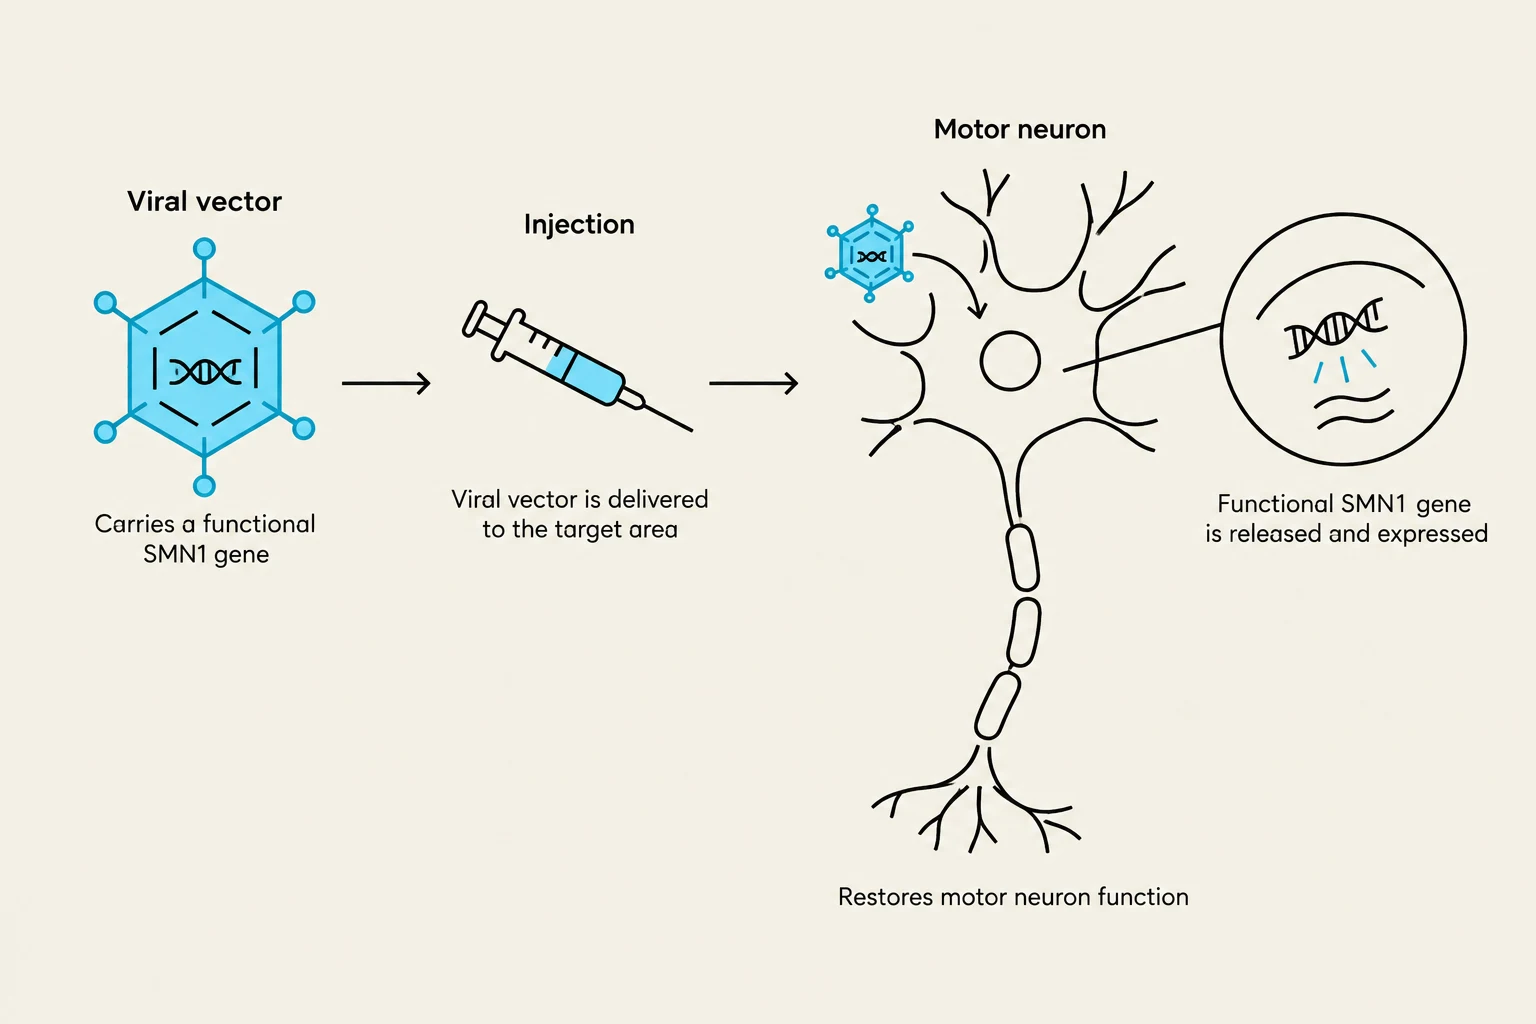
While many treatments manage symptoms or inhibit drivers, gene therapy aims to correct the underlying cause. The success of Zolgensma for Spinal Muscular Atrophy (SMA)—caused by mutations in SMN1—is a landmark achievement. By delivering a functional copy of the SMN1 gene via a viral vector, clinicians can turn a historically fatal infant diagnosis into a treatable condition.
Diagram illustrating the process of delivering a functional SMN1 gene via a viral vector to a motor neuron to restore its function.
Summary Table: Key Clinical Genes
Gene
Primary Clinical Association
Therapeutic Impact
BRCA1/2
Breast/Ovarian Cancer
Predicts PARP inhibitor response
TP53
Most human cancers
Marker for Li-Fraumeni syndrome
EGFR
Non-small-cell lung cancer
Targeted by erlotinib/osimertinib
CFTR
Cystic Fibrosis
Target for CFTR modulators
SMN1
Spinal Muscular Atrophy
Target for Zolgensma gene therapy
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.