Gastrointestinal Medications and Nursing Management
An overview of gastrointestinal disorders, their pharmacological treatments, and essential nursing care. Covers acid management, H. pylori infections, intestinal and rectal disorders, obesity, bariatric surgery, and critical complications.
The gastrointestinal (GI) system is a complex network responsible for digestion, absorption, and elimination. When this system is compromised by inflammation, infection, or structural changes, patients often require a combination of pharmacological interventions and specialized nursing care. For nurses, managing GI disorders requires a deep understanding of how medications interact with gastric acid, how to monitor for life-threatening complications like perforation or peritonitis, and how to support patients undergoing significant lifestyle changes, such as bariatric surgery.
Oral and Esophageal Disorders: Acid Management
Many GI issues stem from an imbalance in gastric acid. Medications used to treat these conditions generally fall into three categories: neutralizing acid, blocking acid production, or protecting the lining of the stomach.
Antacids and H2-Receptor Antagonists
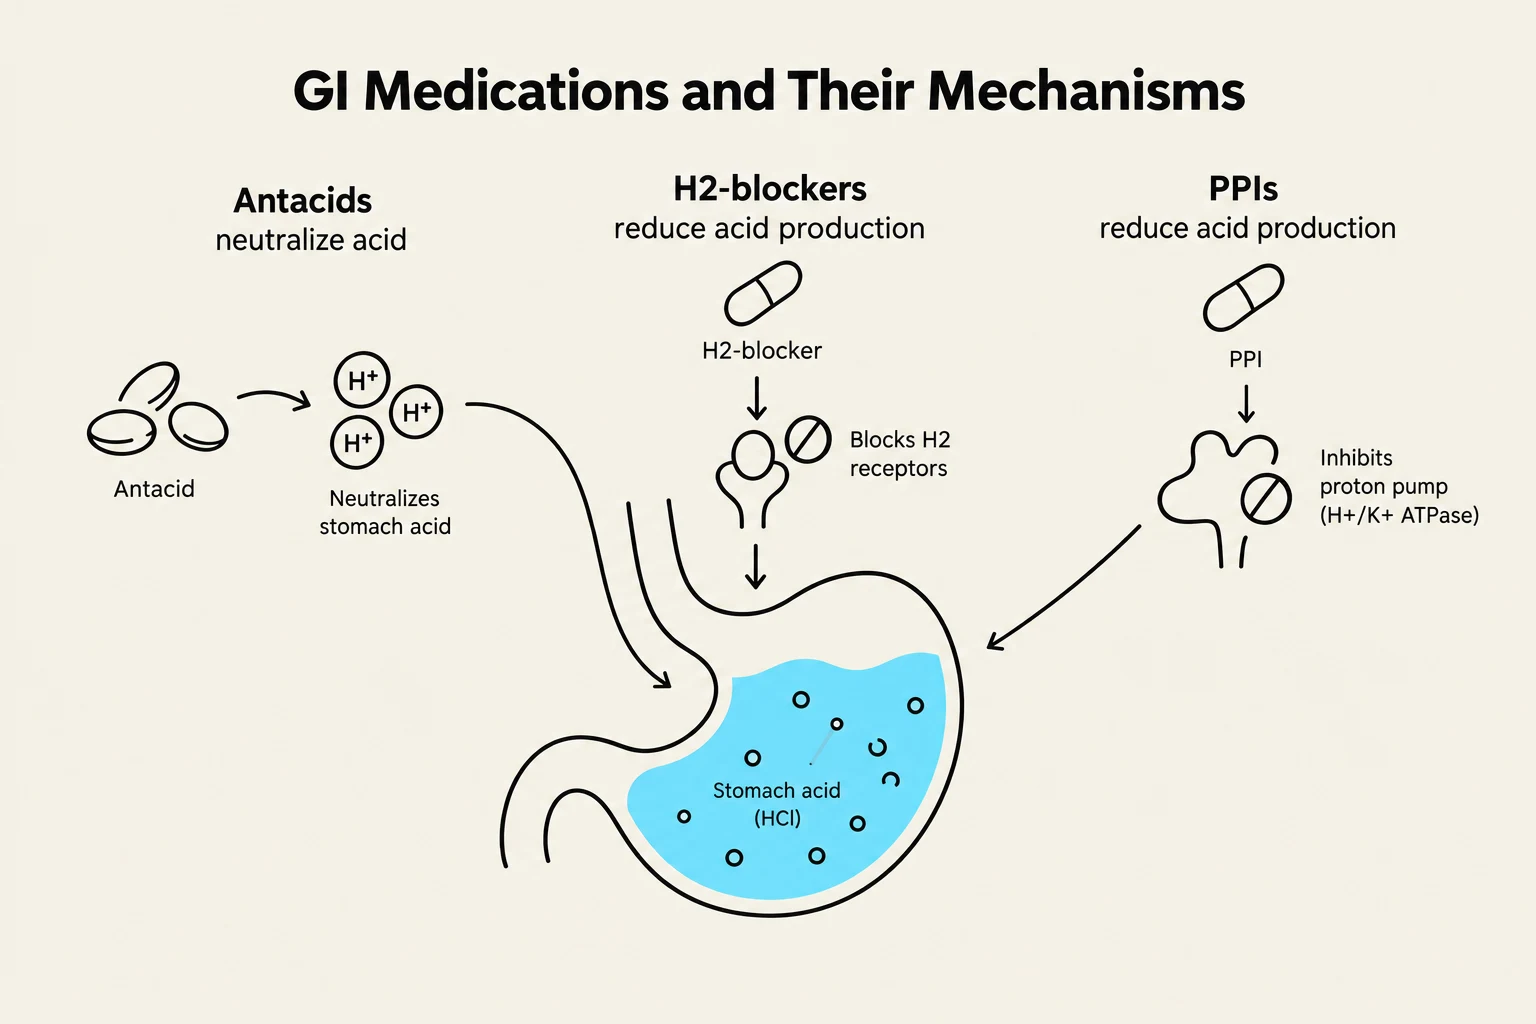
Antacids (e.g., Mylanta, Tums) are mixtures of calcium, aluminum, magnesium hydroxide, or similar bases that act as buffers to neutralize existing gastric acid. Because they can interfere with the absorption of other drugs, they should be taken one hour before or two hours after other medications. A key nursing consideration is the side effect profile: aluminum-based antacids can cause constipation, while magnesium-based ones may cause diarrhea.
H2-Receptor Antagonists (e.g., Famotidine/Pepcid, Cimetidine/Tagamet) work differently by blocking the action of histamine at the receptors, thereby decreasing the total amount of hydrochloric acid produced. These are often used for heartburn, gastritis, and ulcers not caused by H. pylori.
Proton Pump Inhibitors (PPIs) and Prokinetics
Proton Pump Inhibitors (PPIs) (e.g., Omeprazole/Prilosec, Pantoprazole/Protonix) are more potent than H2-blockers because they decrease gastric acid secretion at the source. They should be taken before meals.
Prokinetic agents, such as Metoclopramide (Reglan), increase gastric emptying by contracting the gastric muscle. These are often administered before meals or used as post-operative antiemetics.
Exam Tip: When administering PPIs, remember they are typically not to be crushed. Additionally, if a patient is undergoing a Urea Breath Test for H. pylori, PPIs must be discontinued 2 weeks prior to the test to ensure accuracy.
Mucosal Protection and Prostaglandins
For patients with peptic ulcers, Mucosal Barrier Fortifiers like Sucralfate (Carafate) are used to bind bile acids and pepsins, creating a protective coating over the ulcer. It is vital to give this medication 1 hour before meals and at bedtime, and not within 30 minutes of an antacid, as the antacid might prevent the coating from adhering.
Prostaglandins (e.g., Misoprostol/Cytotec) decrease gastric secretions while protecting the mucosa. However, they are contraindicated in pregnant women due to the risk of causing uterine contractions.
Diagram illustrating the mechanisms of action for antacids, H2-blockers, and proton pump inhibitors (PPIs) in managing stomach acid.
Managing Helicobacter pylori and Infection
Helicobacter pylori is a major cause of gastritis and peptic ulcers. Treatment typically requires Triple Therapy, which involves a PPI combined with two antibiotics.
Commonly used Antimicrobials include:
Metronidazole (Flagyl)
Clarithromycin (Biaxin)
Amoxicillin (Amoxil)
Tetracycline
Patients must complete the full 14-day course of antibiotics to ensure eradication. Common side effects include nausea, vomiting, and diarrhea.
Intestinal and Rectal Disorders
Diarrhea and Constipation
Management of bowel habits involves a variety of pharmacological classes:
Anti-Diarrheals: Loperamide (Imodium) is the drug of choice due to fewer adverse effects. Lomotil is an opioid-related medication that carries a risk of dependence. Note that loperamide is contraindicated in cases of pseudomembranous colitis or abdominal pain of unknown origin.
Laxatives and Stool Softeners: This category includes Bulk-forming (Metamucil), Saline agents (Milk of Magnesia), Stimulants (Dulcolax), and Osmotic agents (Polyethylene glycol).
Inflammatory Bowel Disease (IBD)
IBD includes Crohn’s Disease and Ulcerative Colitis (UC). Both require long-term management to induce remission.
Sulfasalazine (Azulfidine): Used specifically for Ulcerative Colitis. It should be taken after meals with 8 oz of water to prevent kidney stones.
Corticosteroids: (e.g., Prednisone) Used for gastritis and diverticular disease. Crucial Nursing Action: Never stop corticosteroids abruptly; they must be tapered to avoid complications.
Immunomodulators: (e.g., Azathioprine, Methotrexate) These help reduce inflammation and can decrease the long-term need for corticosteroids in IBD patients.
Obesity and Bariatric Surgery
For patients with obesity, management ranges from lifestyle modifications to surgical intervention.
Orlistat is a weight-reduction medication that works by diminishing the intestinal absorption of fats. Common side effects include oily stools, gas, and fecal incontinence.
Bariatric Surgery and Dumping Syndrome
Surgical options include Gastric Banding, Roux-en-Y Bypass, Sleeve Gastrectomy, and the Orbera gastric balloon. A significant complication of these surgeries is Dumping Syndrome, where food moves too rapidly from the stomach into the small intestine.
To manage and prevent Dumping Syndrome, patients should:
Assume a low Fowler’s position after meals and lie down for 20–30 minutes.
Avoid fluids during meals.
Eat small, frequent meals consisting of more "dry" items than liquids.
Keep carbohydrate intake low.
Critical Nursing Priorities and Complications
Nurses must be vigilant for life-threatening GI complications:
Peritonitis: Acute inflammation of the peritoneum. Signs include a "board-like" rigid abdomen, rebound tenderness, and high fever. This is a medical emergency requiring IV fluids, antibiotics, and often surgery.
Fecal Impaction: Severe constipation where hardened stool is stuck in the rectum.
Intestinal Obstruction: Can be mechanical or non-mechanical. Symptoms include crampy, wavelike pain and vomiting that may contain feces.
Hemorrhoids: Swollen veins in the rectum caused by increased abdominal pressure. Management includes Preparation H, Tucks medicated pads, and sitz baths.
Nursing Alert: When managing a patient post-esophageal reconstruction, DO NOT manipulate the Nasogastric Tube (NGT), as this can cause serious complications.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.