Foundations of Pathophysiology and Clinical Assessment
Explores cellular adaptation, lifespan pharmacology, anthropometric profiling, and the pathogenesis of cardiovascular disease, integrating microscopic mechanisms with macroscopic clinical assessment.
Understanding the progression of human disease requires a multi-scalar approach, moving from the microscopic mechanisms of cellular adaptation to the macroscopic assessment of a patient's physical profile and cardiovascular health. By integrating these layers, clinicians can move beyond merely treating symptoms to understanding the underlying drivers of pathology, such as the transition from metabolic dysfunction to acute myocardial necrosis.
Cellular Adaptation and Regenerative Capacity
Cells are not static; they are dynamic entities that attempt to maintain homeostasis when confronted with environmental stressors or injurious stimuli. This process, known as cellular adaptation, involves structural or functional modifications to ensure survival. These adaptations are categorized by how they alter the tissue:
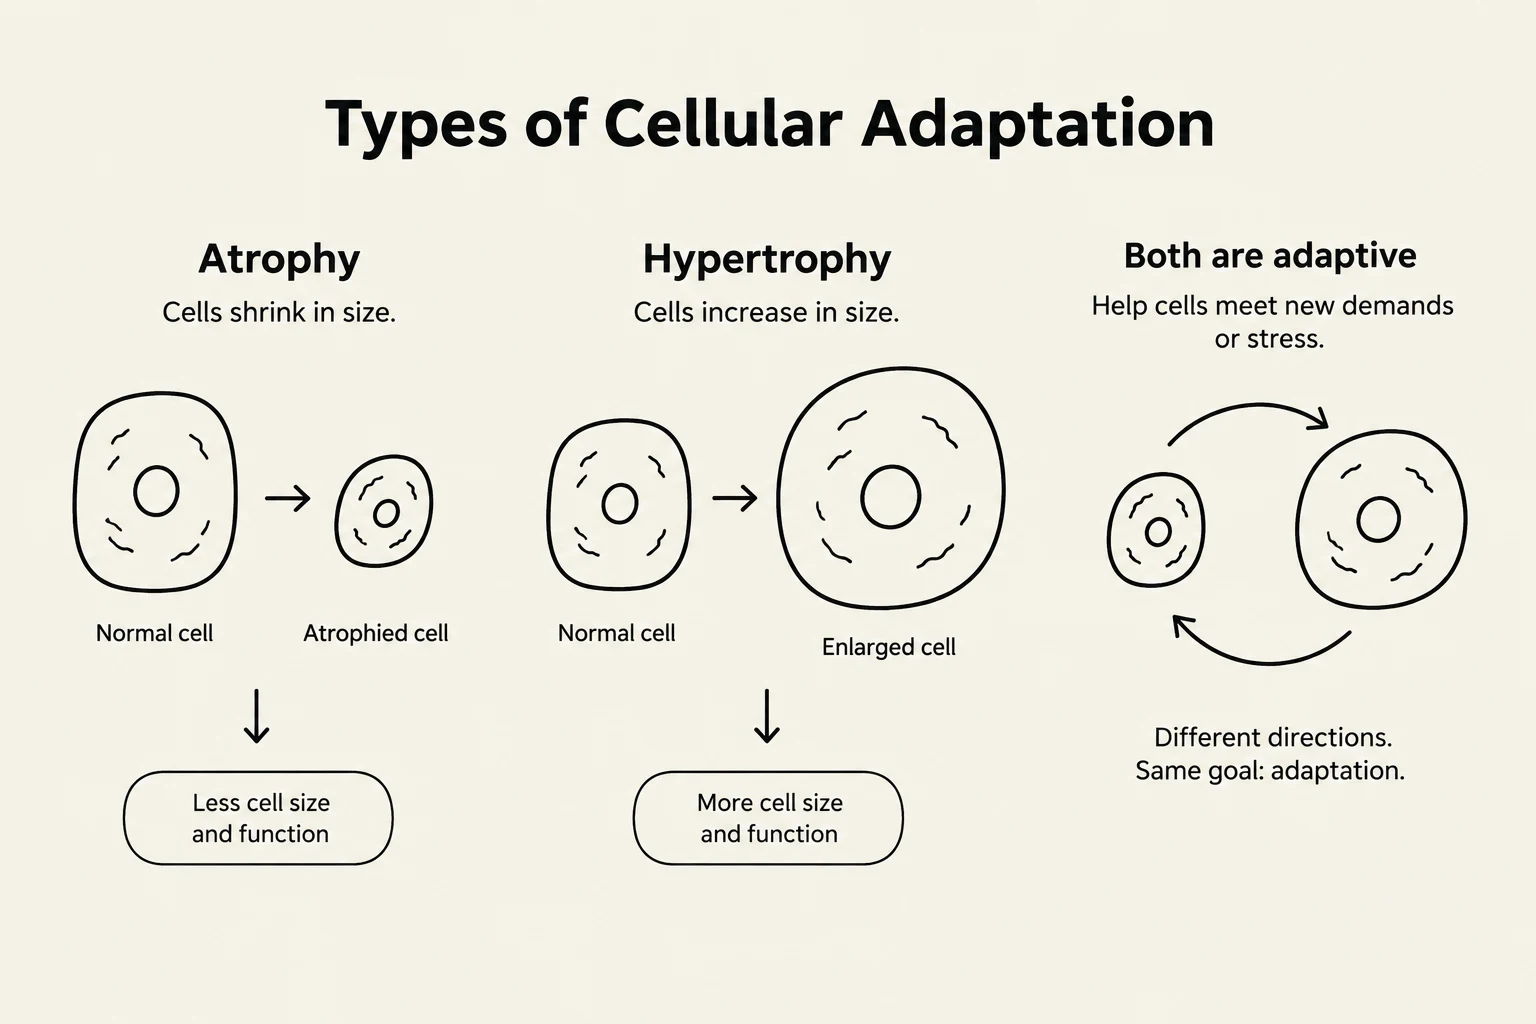
Atrophy: A decrease in cell size, leading to a reduction in the total mass of the organ. This can be physiological (normal aging) or pathological (muscle wasting due to a fracture).
Hypertrophy: An increase in cell size, which increases the total tissue mass. A classic pathological example is myocardial hypertrophy, where the heart muscle thickens to compensate for the high pressure of systemic hypertension.
Hyperplasia: An increase in the total number of cells within a tissue. This occurs in tissues capable of mitosis, such as the prostate or the uterine endometrium.
Exam Tip: Always distinguish between hypertrophy (larger cells) and hyperplasia (more cells). In the heart, because myocytes cannot divide, the response to stress is almost exclusively hypertrophy.
The clinical outcome of an injury is heavily dictated by the regenerative capacity of the specific cell type involved:
Labile Cells: These cells divide continually throughout life (e.g., skin and GI tract linings), allowing for rapid replacement.
Stable Cells: These have a low baseline division rate but can rapidly enter the cell cycle if injured (e.g., hepatocytes in the liver).
Permanent Cells: These cells are incapable of mitotic division in postnatal life (e.g., neurons and cardiac myocytes).
Because permanent cells cannot regenerate, any injury that leads to cell death (necrosis) results in the replacement of functional tissue with non-functional fibrous scar tissue. This is why a myocardial infarction leads to permanent deficits in heart function.
This diagram illustrates cellular adaptation, specifically atrophy (cells shrinking) and hypertrophy (cells increasing in size), as ways cells respond to new demands or stress.
Lifespan Pharmacology and Clinical Safety
A "one-size-fits-all" approach to medication is clinically unsafe because human physiology shifts dramatically across the lifespan. Pharmacokinetics (how the body handles a drug) and pharmacodynamics (the drug's effect on the body) are influenced by age-related changes in organ function and body composition.
Developmental Variations
Neonates/Infants: These patients have higher body water percentages, meaning water-soluble drugs require higher proportional doses. They also face unpredictable absorption and higher levels of "free" active drug due to lower plasma albumin levels.
The Elderly: Aging typically involves a decline in renal and hepatic clearance, which increases the drug's half-life and the risk of toxicity. Furthermore, reduced plasma albumin in the elderly increases the concentration of unbound, active drug.
Adverse Drug Reactions (ADRs) and Polypharmacy
Clinicians must be vigilant for Adverse Drug Reactions (ADRs), which are classified into four types:
Type A (Augmented): Predictable, dose-dependent effects (e.g., excessive bleeding from an anticoagulant).
Type B (Bizarre): Unpredictable, idiosyncratic reactions (e.g., anaphylaxis).
Type C (Chronic): Resulting from long-term cumulative use.
Type D (Delayed): Manifesting long after treatment has ceased (e.g., teratogenicity).
In elderly populations, polypharmacy—the concurrent use of multiple medications—exponentially increases the risk of drug-drug interactions (DIs). While some interactions are intentional (e.g., adding adrenaline to lignocaine to slow its absorption and localize its effect), unintended interactions can lead to a "prescribing cascade" where side effects are mistaken for new medical conditions.
Anthropometric Profiling and Metabolic Risk
Anthropometry provides a non-invasive way to identify metabolic risks before clinical symptoms appear. While the Body Mass Index (BMI) is the global standard, it is a limited metric because it cannot distinguish between lean muscle mass and adipose tissue.
The calculation for BMI is:
BMI=Height (m)2Weight (kg)
Clinicians must also consider ethnic variations; for example, Asian populations often exhibit metabolic risks at lower BMI thresholds than European populations.
Fat Distribution: Android vs. Gynoid
A superior predictor of cardiovascular risk is the Waist-to-Hip Ratio (WHR), which identifies regional adiposity:
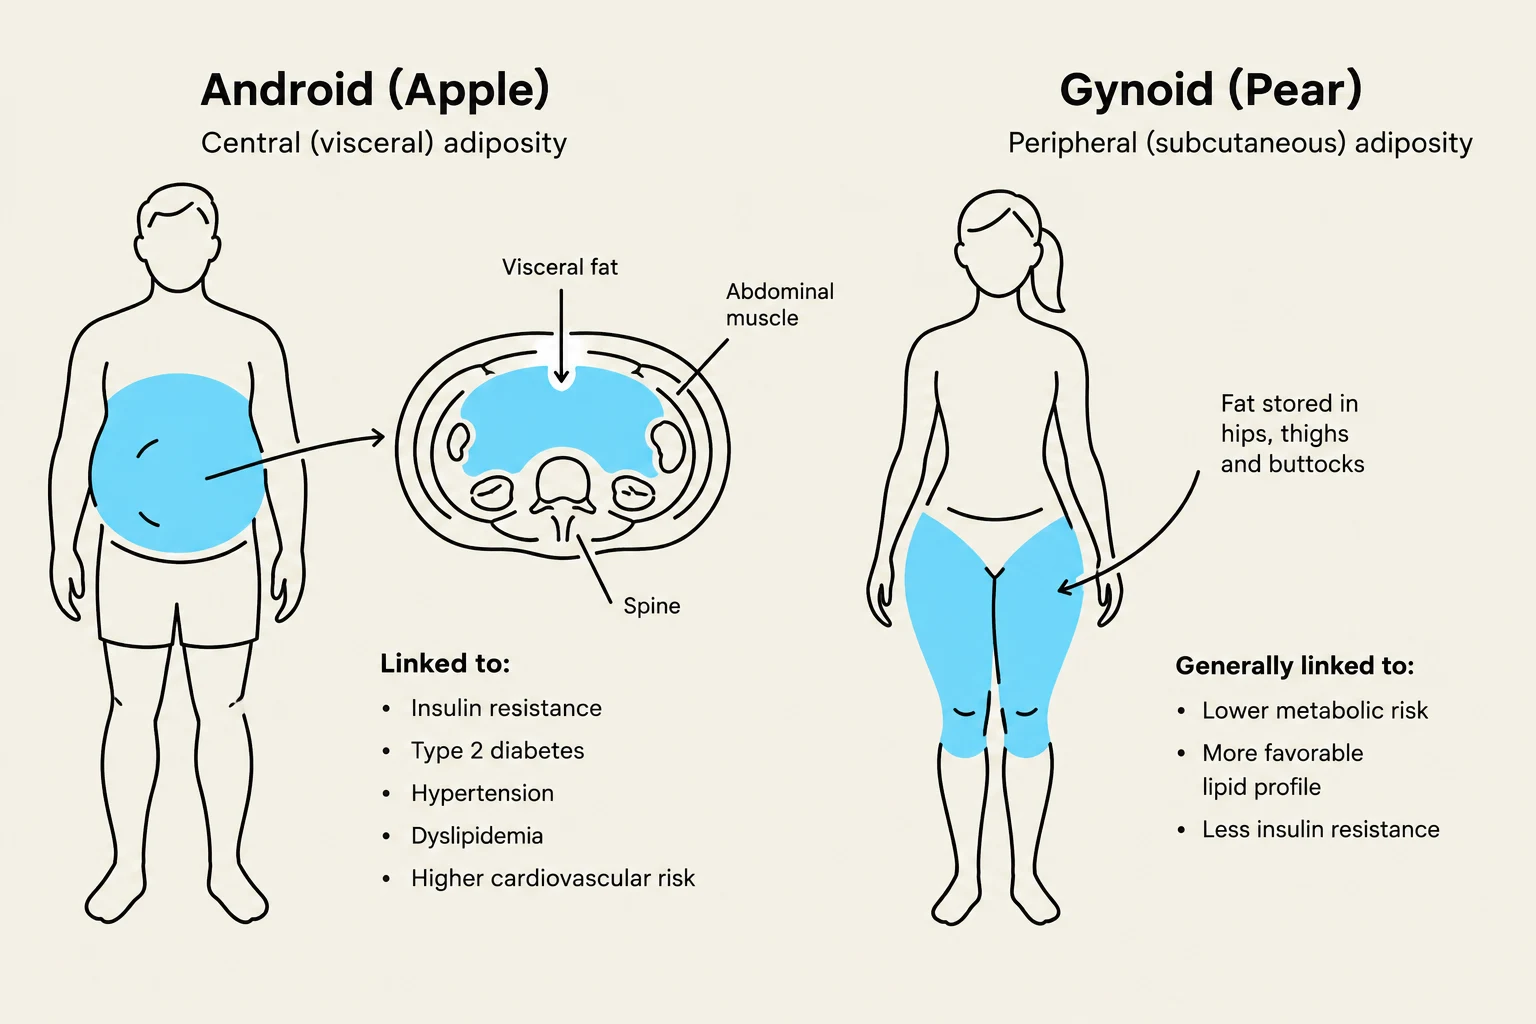
Android (Apple) Morphology: Characterized by a WHR >0.9 in men or >0.8 in women. This indicates excess visceral fat, which acts as a pro-inflammatory endocrine organ, releasing cytokines that drive systemic inflammation and atherosclerosis.
Gynoid (Pear) Morphology: Characterized by a WHR <0.9 in men or <0.8 in women, indicating fat storage in the hips and thighs, which carries lower metabolic risk.
This illustration compares Android (Apple) and Gynoid (Pear) body fat distribution patterns, detailing their associated health risks and characteristics.
Pathogenesis of Cardiovascular Disease
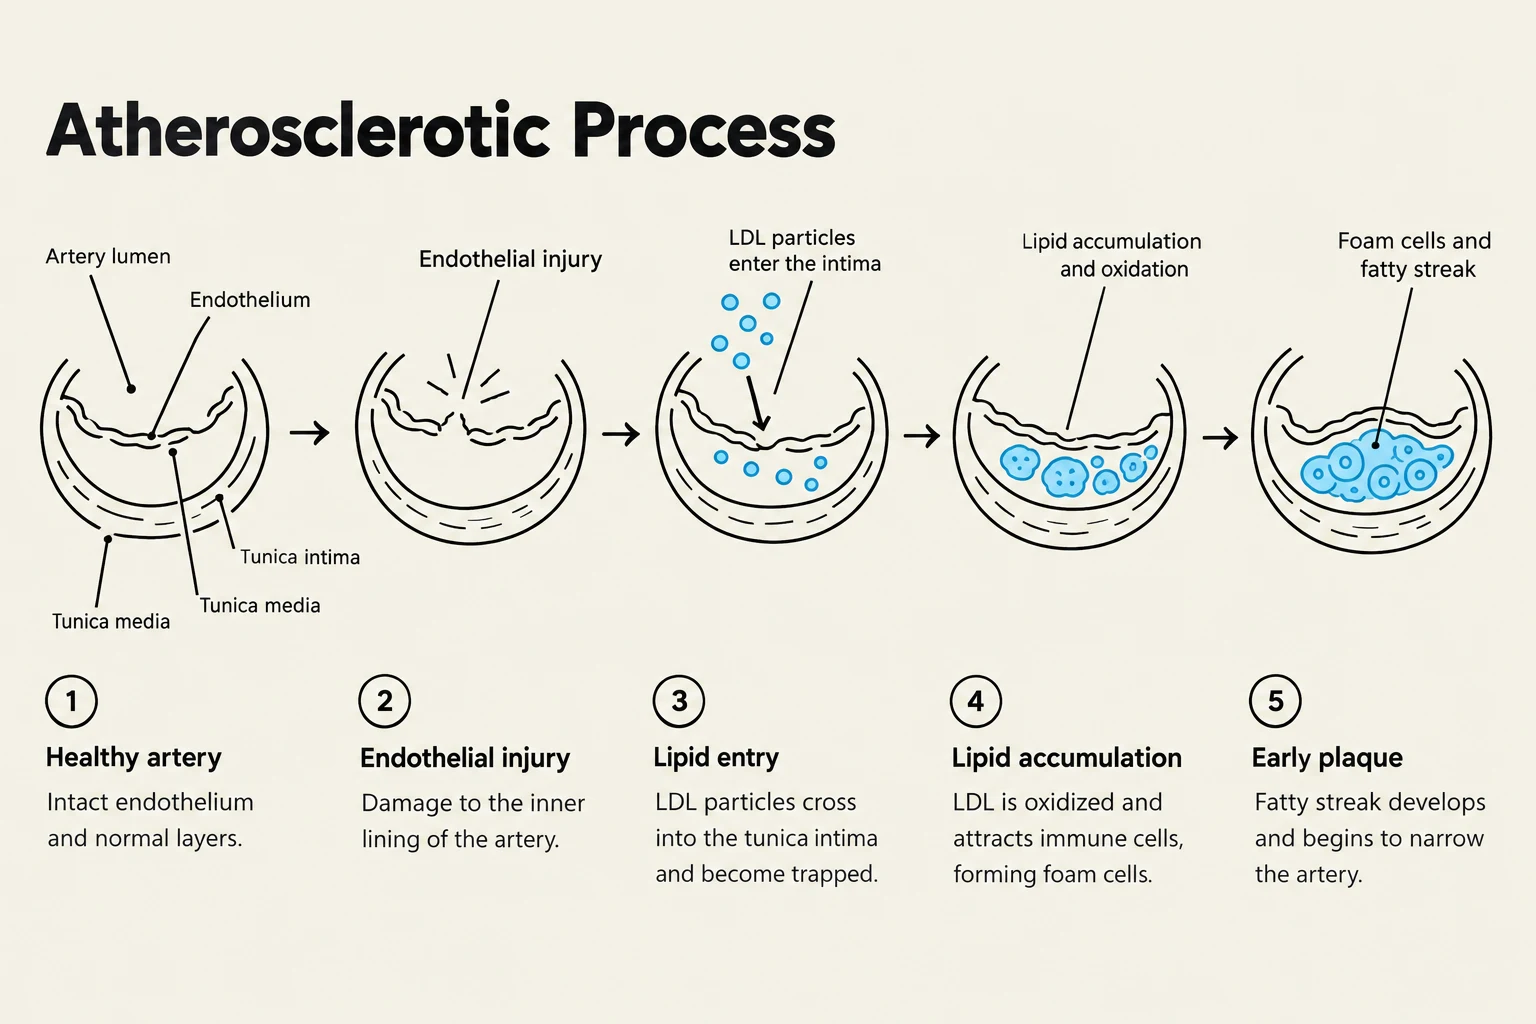
Cardiovascular disease often begins with the progressive degradation of the arterial system, specifically through atherosclerosis. This is a specific form of arteriosclerosis (the general thickening and hardening of arteries) involving the accumulation of atheromas (fibrofatty plaques) within the tunica intima (the inner lining of the artery).
The Progression to Occlusion
As lipids (such as oxidized LDL) accumulate, they form plaques that narrow the arterial lumen. This narrowing creates a mismatch between oxygen supply and demand, leading to Coronary Artery Disease (CAD). The clinical danger escalates if a plaque ruptures:
Thrombus: A stationary blood clot that forms at the site of the injury.
Embolus: A detached mass (clot, air, or fat) that travels through the bloodstream.
Embolism: The sudden occlusion of a distal vessel by a traveling embolus.
Clinical Differentiation: Angina vs. Myocardial Infarction
A critical skill for clinicians is differentiating between transient ischemia and permanent tissue death:
Feature
Stable Angina
Myocardial Infarction (MI)
Vascular Status
Partial blockage (stenosis)
Complete thrombotic occlusion
Tissue Status
Ischemia without necrosis
Myocardial necrosis (cell death)
Trigger
Physical exertion/stress
Can occur at rest
Duration
Brief; relieved by rest
Persists >15 minutes; crushing pain
Cardiac Markers
Absent from blood
Present (e.g., Troponin)
Clinical Synthesis: Because cardiac myocytes are permanent cells, they cannot undergo hyperplasia to replace dead tissue. When an MI occurs, the dead cells are replaced by non-functional scar tissue, which can eventually lead to the heart's inability to pump effectively, resulting in heart failure.
Diagram illustrating the five stages of the atherosclerotic process, from a healthy artery to an early plaque.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.