The Nursing Process: Assessment, Reasoning, and Decision-Making
An in-depth exploration of the nursing process, emphasizing evidence-based practice, diagnostic reasoning using the hypothetico-deductive model, critical thinking, and priority setting in patient care.
In the complex environment of modern healthcare, nursing is far more than a series of tasks; it is a continuous cycle of observation, reasoning, and action. At the heart of high-quality patient care lies the ability to transform raw data into meaningful clinical judgments. This process is driven by evidence-based practice, a disciplined approach that ensures nursing interventions are grounded in science, clinical expertise, and the unique needs of the patient.
The Foundation: The Nursing Process and Data Collection
This diagram illustrates different approaches to patient care, categorized as Complete Total Health, Episodic/Problem-Centered, Follow-up, and Emergency, all stemming from a central Patient Database.
The nursing process serves as the systematic framework for all nursing care. It begins with assessment, which acts as the "point of entry" for an ongoing cycle of care. To make accurate clinical judgments, a nurse must construct a robust database. This database is composed of subjective data (what the patient tells you), objective data (what you observe or measure), patient medical records, and laboratory results.
Depending on the clinical situation, nurses collect different types of databases to meet specific needs:
Complete Total Health Database: This provides a comprehensive baseline of a patient's current and past health status, allowing the nurse to measure all future changes.
Episodic or Problem-Centered Database: A focused "mini" database used to address a specific issue or a single problem.
Follow-up Database: Used to evaluate the status of previously identified problems at regular intervals.
Emergency Database: A rapid collection of data performed simultaneously with life-saving measures during a crisis.
Clinical Reasoning and the Hypothetico-Deductive Model
The hypothetico-deductive model illustrates a continuous loop of scientific inquiry, involving attending to cues, formulating hypotheses, gathering relevant data, and evaluating hypotheses.
Once data is collected, the nurse must engage in diagnostic reasoning to interpret what that data means for the patient's health. One of the most effective ways to structure this thinking is through the hypothetico-deductive model.
In this model, the nurse follows a logical progression:
Attend to initial cues: Notice the pieces of information (e.g., a change in skin color or a lab value).
Formulate diagnostic hypotheses: Create tentative explanations for those cues.
Gather relevant data: Perform further assessments to test those hypotheses.
Evaluate hypotheses: Use ongoing data collection to confirm or rule out the initial ideas.
This model ensures that the nurse is not just reacting to symptoms but is investigating the underlying cause through a continuous, evidence-based loop.
Evidence-Based Practice (EBP) and Critical Thinking
Evidence-Based Practice (EBP) is the integration of four critical components: research evidence, clinical expertise, clinical knowledge, and the patient's own values and preferences. Clinical decision making is the practical application of this integration—combining the best available literature with the clinician's physical exam and the patient's unique situation.
The Role of "Hunches" and Critical Thinking
Critical thinking involves more than just following protocols; it often involves a "hunch" or an intuitive feeling that something is wrong. However, a professional nurse does not act on a hunch alone.
Clinical Tip: If you have a "hunch" (e.g., a patient's blood pressure is high because they are in pain), do not act on intuition alone. Instead, use a collaborative approach. Consult with other team members to substantiate your hunch with evidence or clinical observation.
The Evolution of Nursing Competency
As nurses gain experience, their ability to perform clinical reasoning and decision-making evolves through distinct stages:
Stage
Description
Novice
Just starting out; relies heavily on strict rules to guide performance.
Proficient
Has 2–3 years of experience; begins to see actions within the context of the patient's overall goals.
Expert
Has attained mastery; understands the patient situation as a whole and uses intuitive analysis to make judgments.
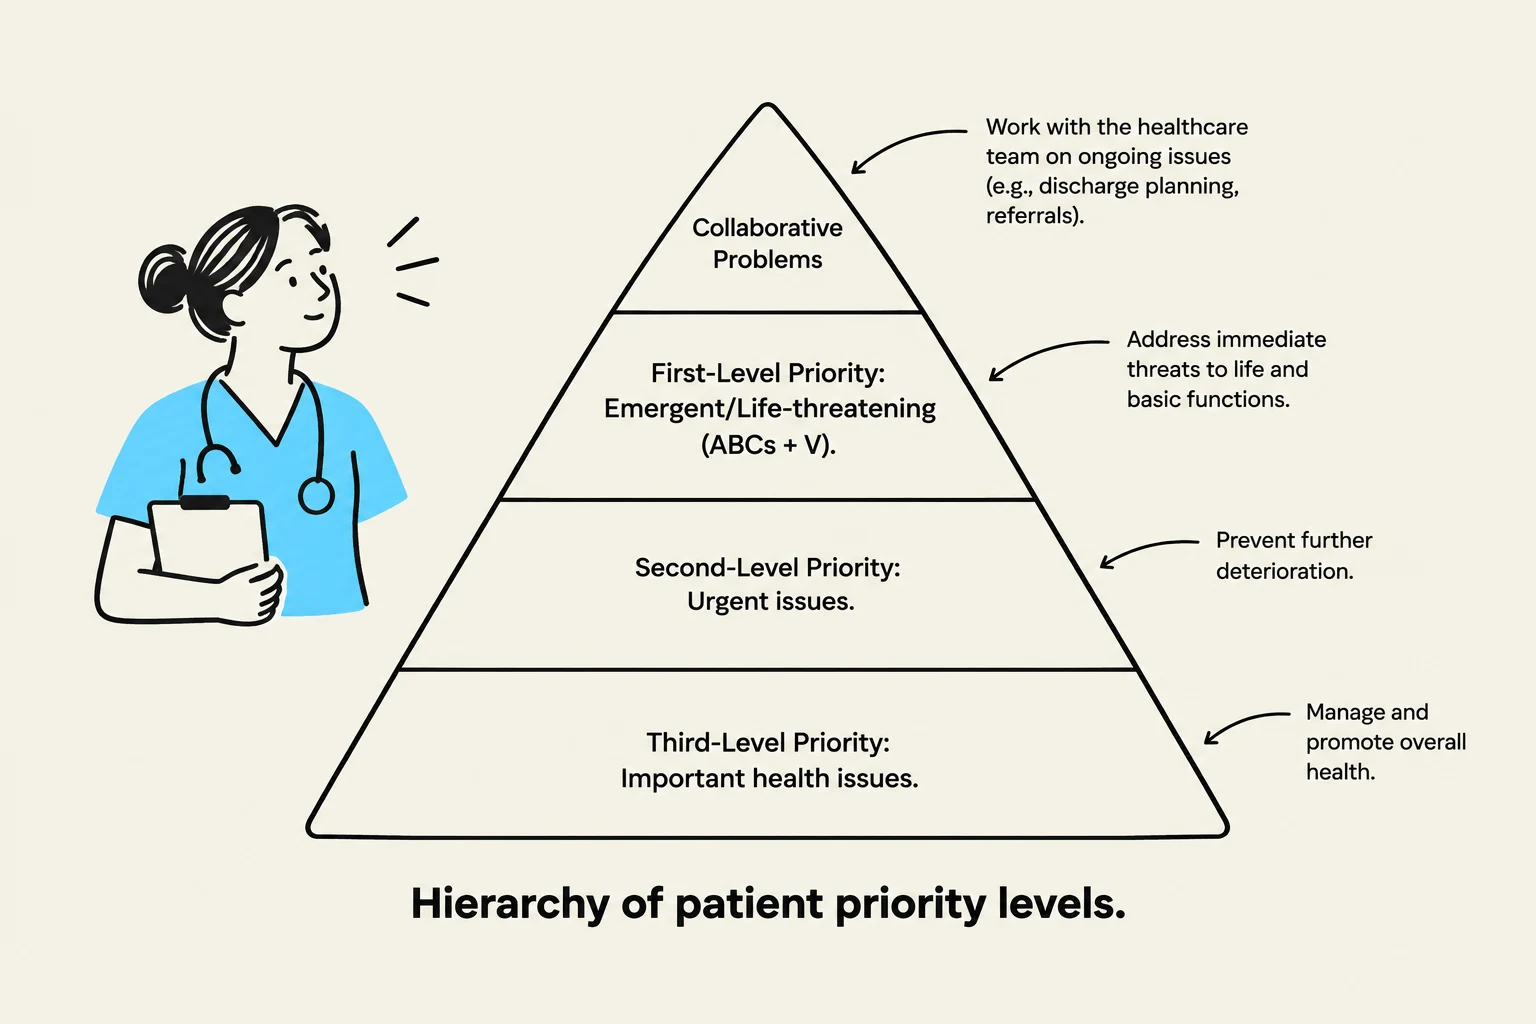
Hierarchy of patient priority levels, illustrating collaborative problems, emergent/life-threatening issues, urgent issues, and important health issues.
Priority Setting: Managing the Dynamic Patient
Because a patient's condition can change in an instant—such as a stable patient suddenly experiencing a seizure—nurses must use a dynamic framework to set priorities.
Levels of Priority
Nurses categorize patient needs into four levels to ensure the most critical issues are addressed first:
First-Level Priority: Emergent, life-threatening, and immediate issues. These focus on the ABCs (Airway, Breathing, Circulation) plus V (Vital signs).
Second-Level Priority: Urgent issues that require intervention to prevent further deterioration.
Third-Level Priority: Important health issues that are not immediate and can be addressed after more urgent problems are resolved.
Collaborative Problems: Issues that require a multi-disciplinary approach to treatment.
Worked Example: Emergency Department Triage
Consider four patients arriving at an Emergency Department:
Patient A (48-year-old male with chest pain): This is a Level 1 priority. The nurse must immediately rule out a cardiac event by assessing airway, breathing, circulation, and obtaining an EKG.
Patient B (68-year-old male after a ground-level fall): This is a Level 2 priority. While not immediately life-threatening, the nurse must evaluate for mental status changes or potential vascular issues that could escalate to Level 1.
Patient C (5-year-old with a toy in his ear, playing quietly): This is a Level 2 priority. The child is stable, but the object must be removed promptly to prevent damage.
Patient D (19-year-old female with frequent headaches): This is a Level 2 priority. While the headaches are a concern that requires investigation, the patient is currently stable.
Crucial Note: If Patient D suddenly has a seizure, her status immediately shifts from a Level 2 to a Level 1 priority. This demonstrates that clinical decision-making is a continuous process of reassessment.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.