


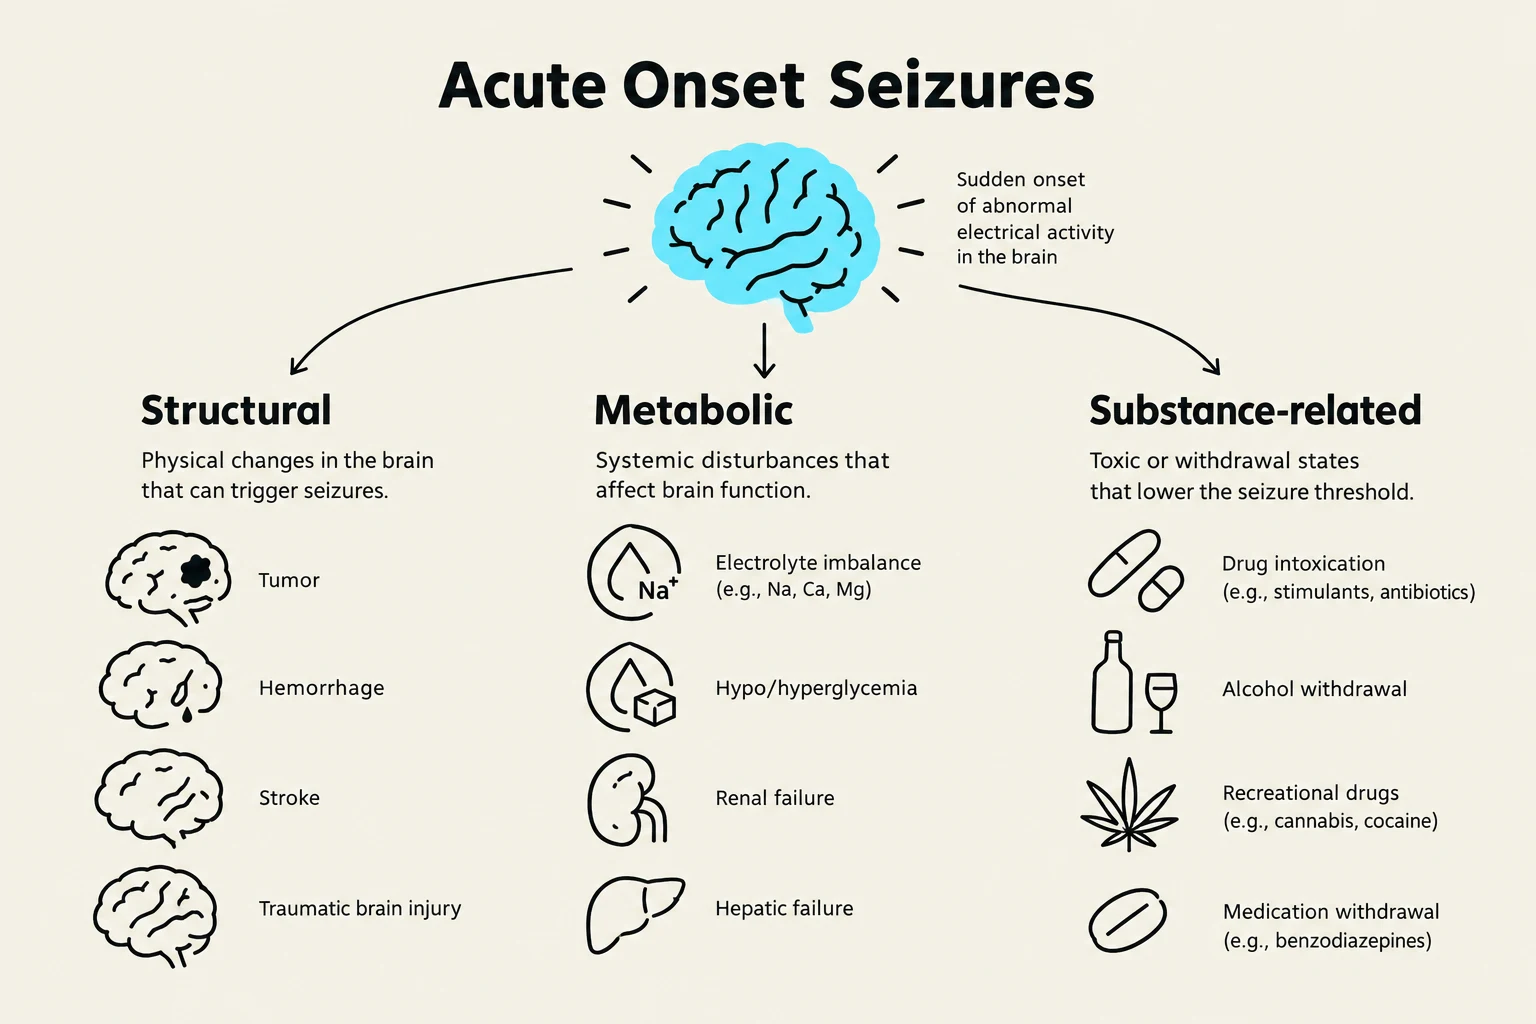
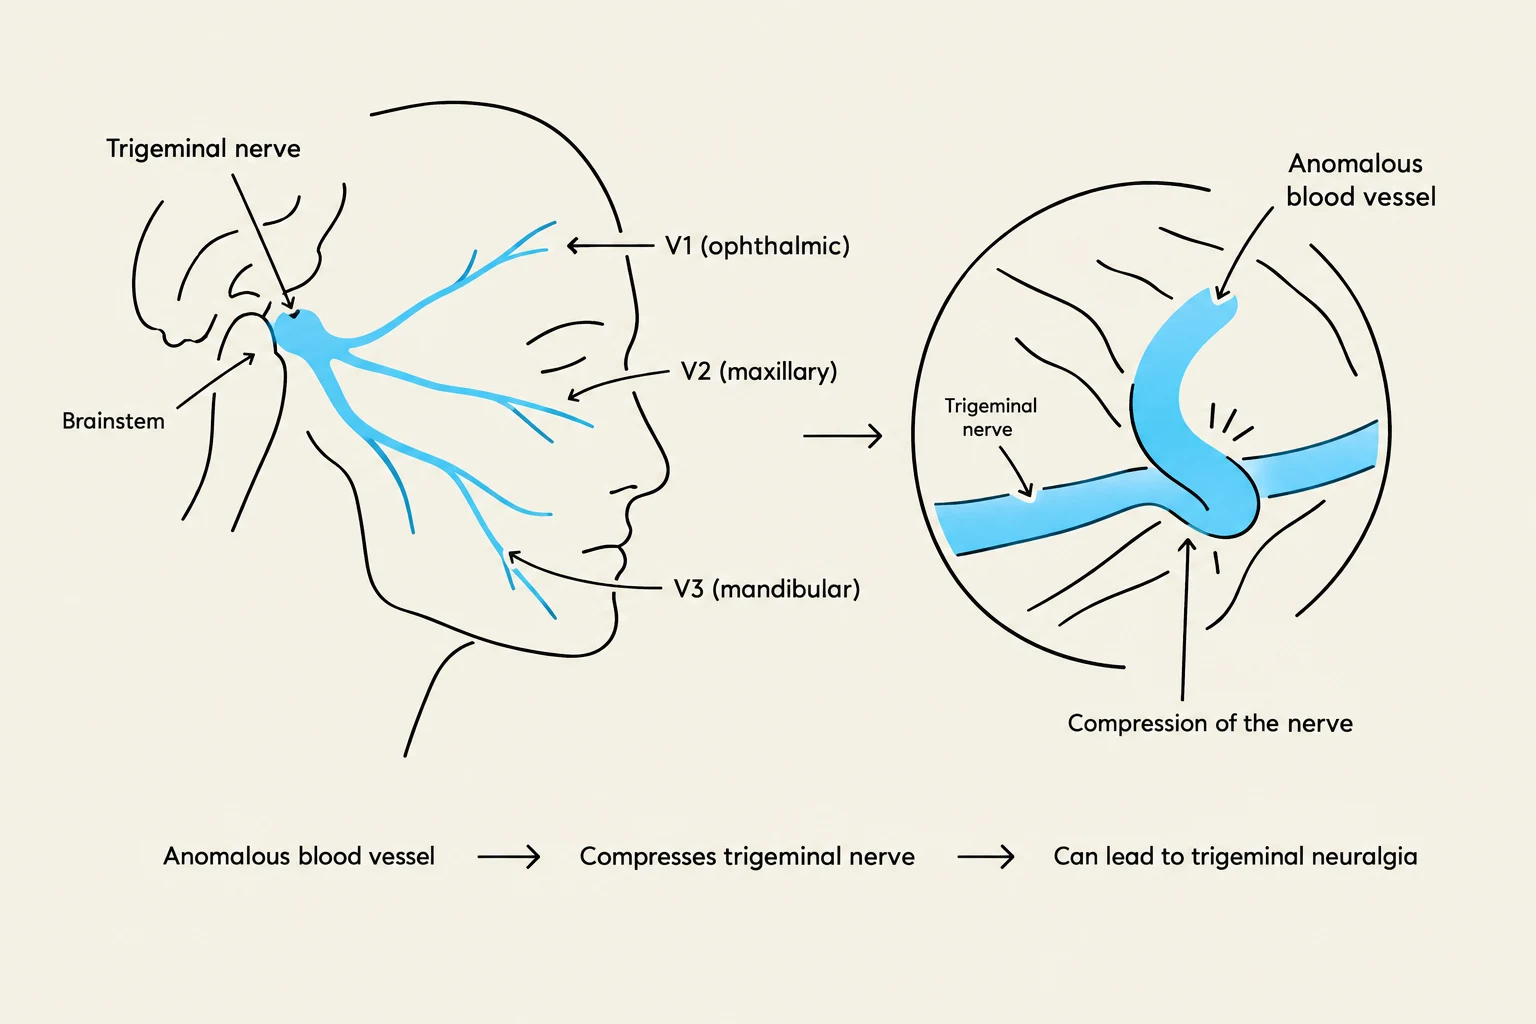
Neurological emergencies and chronic pain syndromes require precise classification to ensure appropriate management. This review explores the complexities of seizure types, the diverse causes of acute onset seizures, and the clinical management of trigeminal neuralgia.
Epilepsy Classifications
Epilepsy is fundamentally a "classification game". The primary distinction in seizure classification is whether the electrical discharge begins in a specific area of the brain or involves both hemispheres simultaneously.
Focal Onset Seizures
Focal onset seizures (formerly known as partial seizures) occur when only a restricted part of one cerebral hemisphere is activated. These are further categorized by their clinical presentation:
- Aware vs. Impaired Awareness: Awareness refers to the patient's knowledge of themselves, their environment, and the events occurring during the seizure. In focal seizures with impaired awareness, the patient may experience a loss of consciousness or a state where they are not fully present.
- Motor Symptoms: These involve physical movement and include clonic (rapid rhythmic jerking), tonic (sustained stiffening), atonic (sudden loss of muscle tone), myoclonic (brief shock-like jerks), or hyperkinetic activity. It may also manifest as automatisms (repetitive, semi-coordinated movements) or epileptic spasms.
- Nonmotor Symptoms: These can be sensory (paresthesias, visual, or auditory phenomena), cognitive (speech arrest, déjà vu), emotional (sudden fear), or autonomic (sweating, epigastric sensations, or pupillary dilation).
A critical clinical progression to watch for is a focal to bilateral tonic-clonic seizure, where a seizure starting in one area spreads to involve both hemispheres.

Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated