Enteral Nutrition: Delivery, Monitoring, and Safety Standards
An overview of enteral nutrition (EN), including its benefits, delivery methods (gravity-controlled and pump-assisted), safety standards like the ENFit system, clinical calculations, monitoring parameters, and complication management.
Enteral nutrition (EN) is the preferred method of nutritional support for patients with a functional or partially functional gastrointestinal (GI) tract. Because it utilizes the natural digestive processes, EN offers significant benefits over parenteral nutrition, including improved nutrient utilization, maintenance of gut pH and flora, and the preservation of the gut mucosa's immunologic barrier, which helps decrease the risk of gut-related sepsis. However, successful EN therapy requires precise delivery methods, standardized equipment to prevent errors, and rigorous clinical monitoring to manage complications.
Safety Standards: The ENFit System
One of the most critical aspects of enteral nutrition is ensuring the correct delivery of formula to the correct site. Historically, misconnections—such as accidentally infusing enteral formula into an intravenous (IV) line, a tracheal tube, or a nasal cannula—have led to patient morbidity and even death.
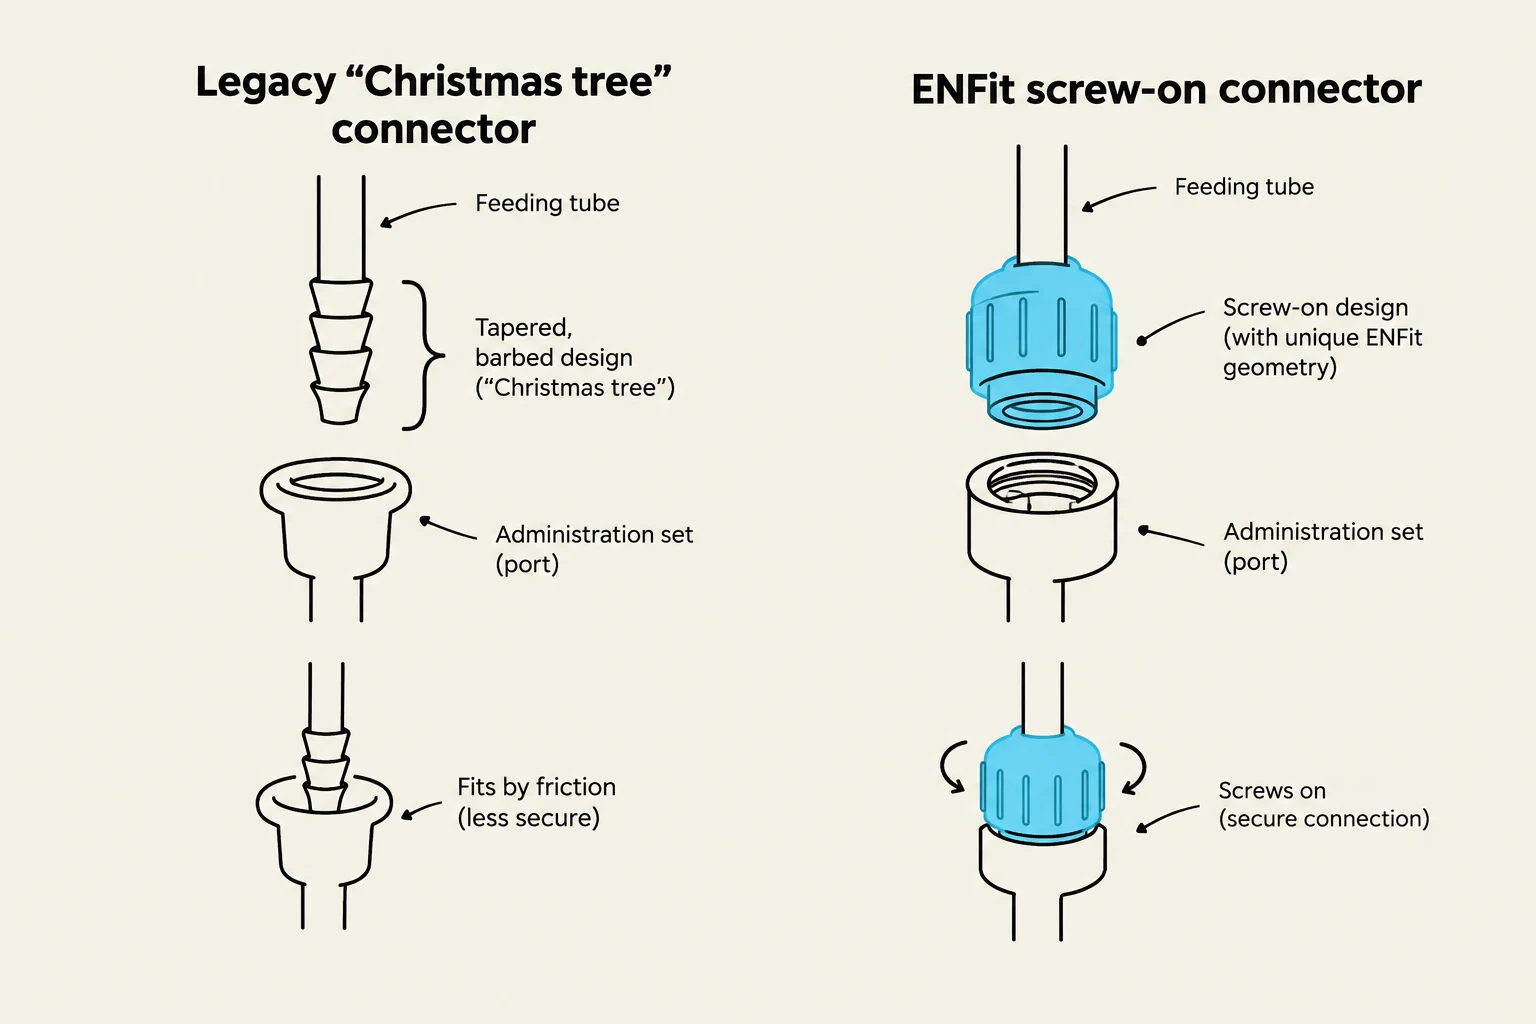
To mitigate these risks, the International Organization for Standardization (ISO 80369-3) developed the ENFit standard. Unlike the older "Christmas tree" style male connectors that could easily be attached to various IV ports, ENFit utilizes a specialized screw-on mechanism. This female connector is designed to fit only with other enteral-specific devices, such as feeding pumps and syringes, making it physically impossible to connect to standard IV tubing.
Comparison of a legacy "Christmas tree" connector with a tapered, barbed design that fits by friction, and an ENFit screw-on connector with a secure screw-on design.
Enteral Nutrition Delivery Methods
The choice of delivery method depends on the patient's clinical setting, neurological status, and GI tolerance. Methods are broadly categorized into gravity-controlled and pump-assisted delivery.
Gravity-Controlled Delivery
This method is most appropriate for patients who are neurologically intact and can protect their airway. It is frequently used in home care or non-acute settings because it is economical and mimics physiologic meal patterns.
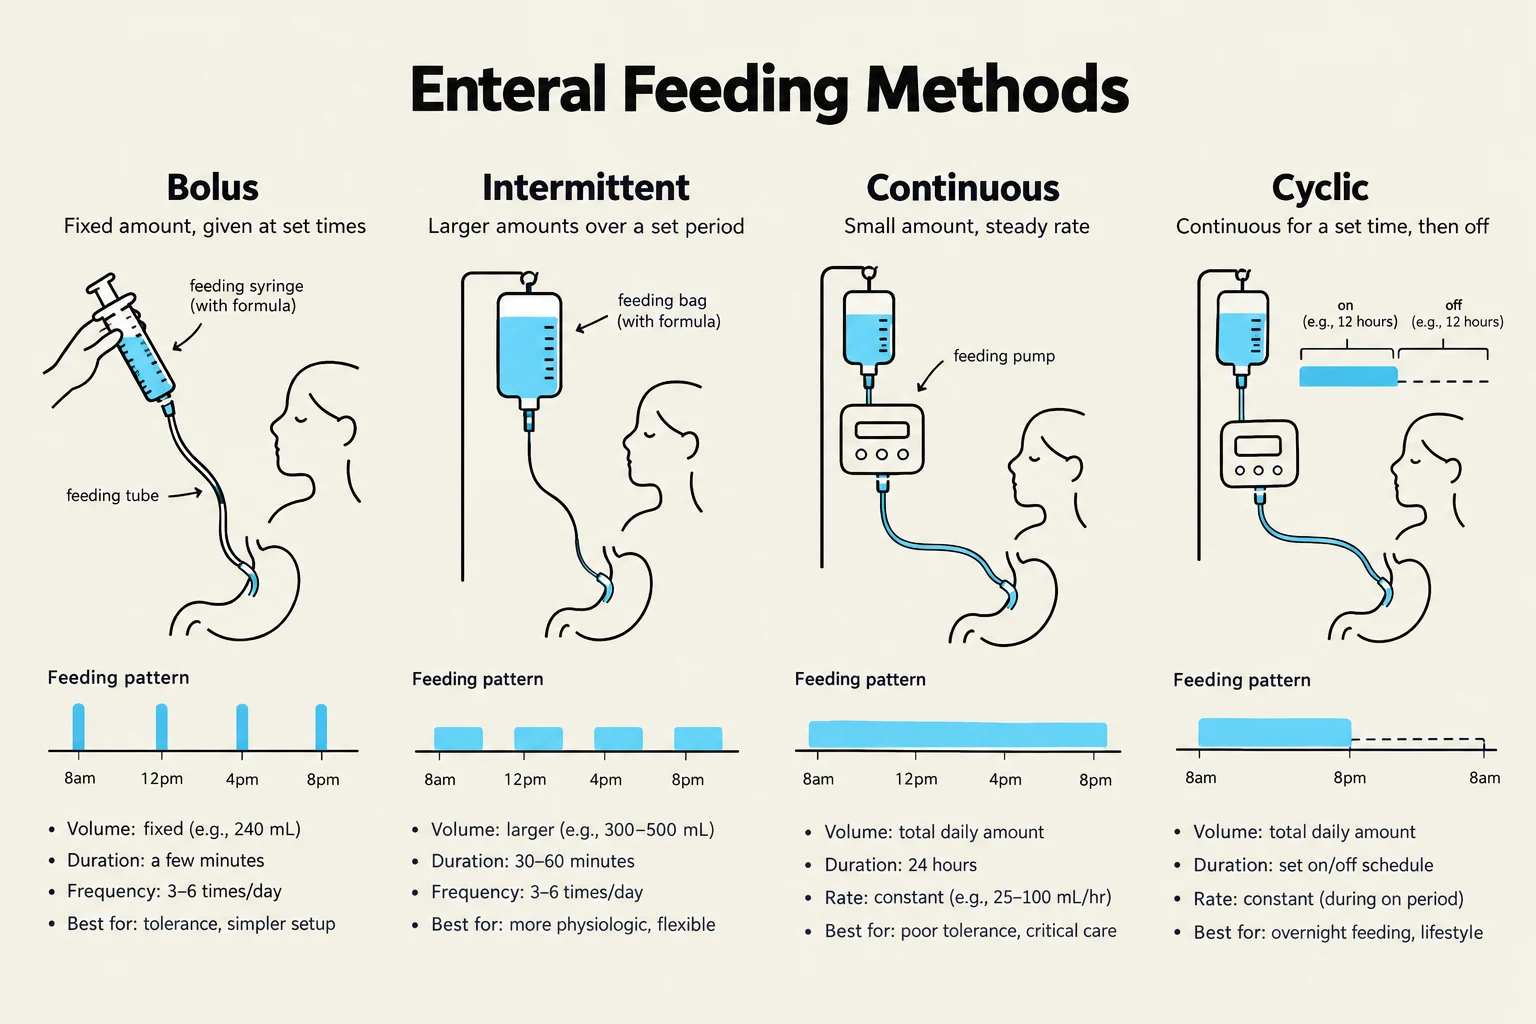
Bolus Feeding: Formula is infused rapidly, typically over approximately 15 minutes, via a syringe or gravity assist.
Intermittent Feeding: Similar to bolus in volume and frequency, but the delivery is slowed over 30 to 45 minutes.
While physiologic, gravity methods may be poorly tolerated by patients with gastroparesis, uncontrolled gastroesophageal reflux disease (GERD), or gastric outlet obstruction.
Pump-Assisted Delivery
Pump-assisted methods are common in acute care and for critically ill patients, such as those requiring mechanical ventilation.
Continuous (ATC) Feeding: Infused "around the clock" (ATC) for 24 hours a day. This method is ideal for patients who cannot tolerate bolus feedings and helps decrease the risk of gastric distention.
Cyclic Feeding: Infused over a specific window of 8 to 20 hours daily. This allows for periods of "gut rest" and maximal nutrient absorption, often during nocturnal hours, which can increase patient mobility during the day.
This diagram illustrates four methods of enteral feeding: Bolus, Intermittent, Continuous, and Cyclic, detailing their characteristics, feeding patterns, and best use cases.
Clinical Calculations and Implementation
Clinicians must translate nutritional requirements (calories and protein) into specific volumes of formula. For high-risk critically ill patients, the goal is to achieve >80% of these requirements within 48 to 72 hours of hospitalization.
Worked Example: Volume Calculation
If a patient requires 2,000 kcal per day and the prescribed formula provides 1.2 kcal/mL, the daily volume is calculated as follows:
Total VolumeTotal VolumeTotal Volume=kcal per mLTotal kcal needed=1.2 kcal/mL2,000 kcal=1,667 mL
Once the volume is determined, it is divided by the delivery method. For continuous feeding over 24 hours:
24 hr1,667 mL≈70 mL/hr
Clinical Tip: Refeeding Syndrome
If a patient is at risk for refeeding syndrome (e.g., those with anorexia nervosa or extreme weight loss), EN should be initiated at only 25–50% of the goal rate and advanced slowly over 5–7 days. Daily monitoring of potassium, magnesium, and phosphorus is mandatory during this period.
Monitoring and Complications
Effective EN management requires continuous assessment of gastrointestinal tolerance, hydration, and nutritional status.
Monitoring Parameters
Common monitoring guidelines include:
Weight: Before initiation and at least twice weekly.
Intake and Output (I/O): Daily.
Electrolytes (K, Mg, P): Daily until stable, then weekly.
Gastric Residual Volume (GRV): Checked every 4–6 hours for gastric feedings.
Regarding Gastric Residual Volume (GRV), residuals of 400–500 mL are generally considered tolerable. It is recommended that EN should not be held unless GRV exceeds 500 mL, provided there are no other signs of intolerance. Note that residuals should not be checked when feeding via the jejunum.
Managing Complications
GI Intolerance: Symptoms include distension, pain, or nausea. Management may involve verifying tube placement, adjusting formula osmolality, or using promotility agents like metoclopramide.
Diarrhea: Defined as >200 mL of stool or >3 stools per day. Causes can range from medications to pathogens; elemental formulas or soluble fiber may be used to aid absorption.
This flowchart outlines the management of gastrointestinal intolerance, detailing steps for verifying tube placement, assessing symptoms, adjusting feeding plans, and monitoring patient response.
Transitioning to Oral Diet
The ultimate goal of EN is to provide temporary support until the patient can meet their needs through oral intake. As a patient begins to consume an oral diet, EN should be adjusted to prevent overfeeding and to encourage appetite. A common clinical threshold for discontinuing EN is when the patient is successfully consuming 60–75% of their total energy and protein requirements orally.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.