


The management of endometrial cancer is a highly individualized process. Treatment decisions are not based solely on the anatomical extent of the tumor, but are increasingly driven by a combination of histological subtype, FIGO stage, and molecular profiles. Because different subtypes—such as endometrioid, serous, or carcinosarcoma—behave differently, clinicians must categorize disease into two broad management pathways: uterine-confined disease and advanced or extrauterine disease.
Uterine-Confined Disease: Surgical Staging and Primary Treatment
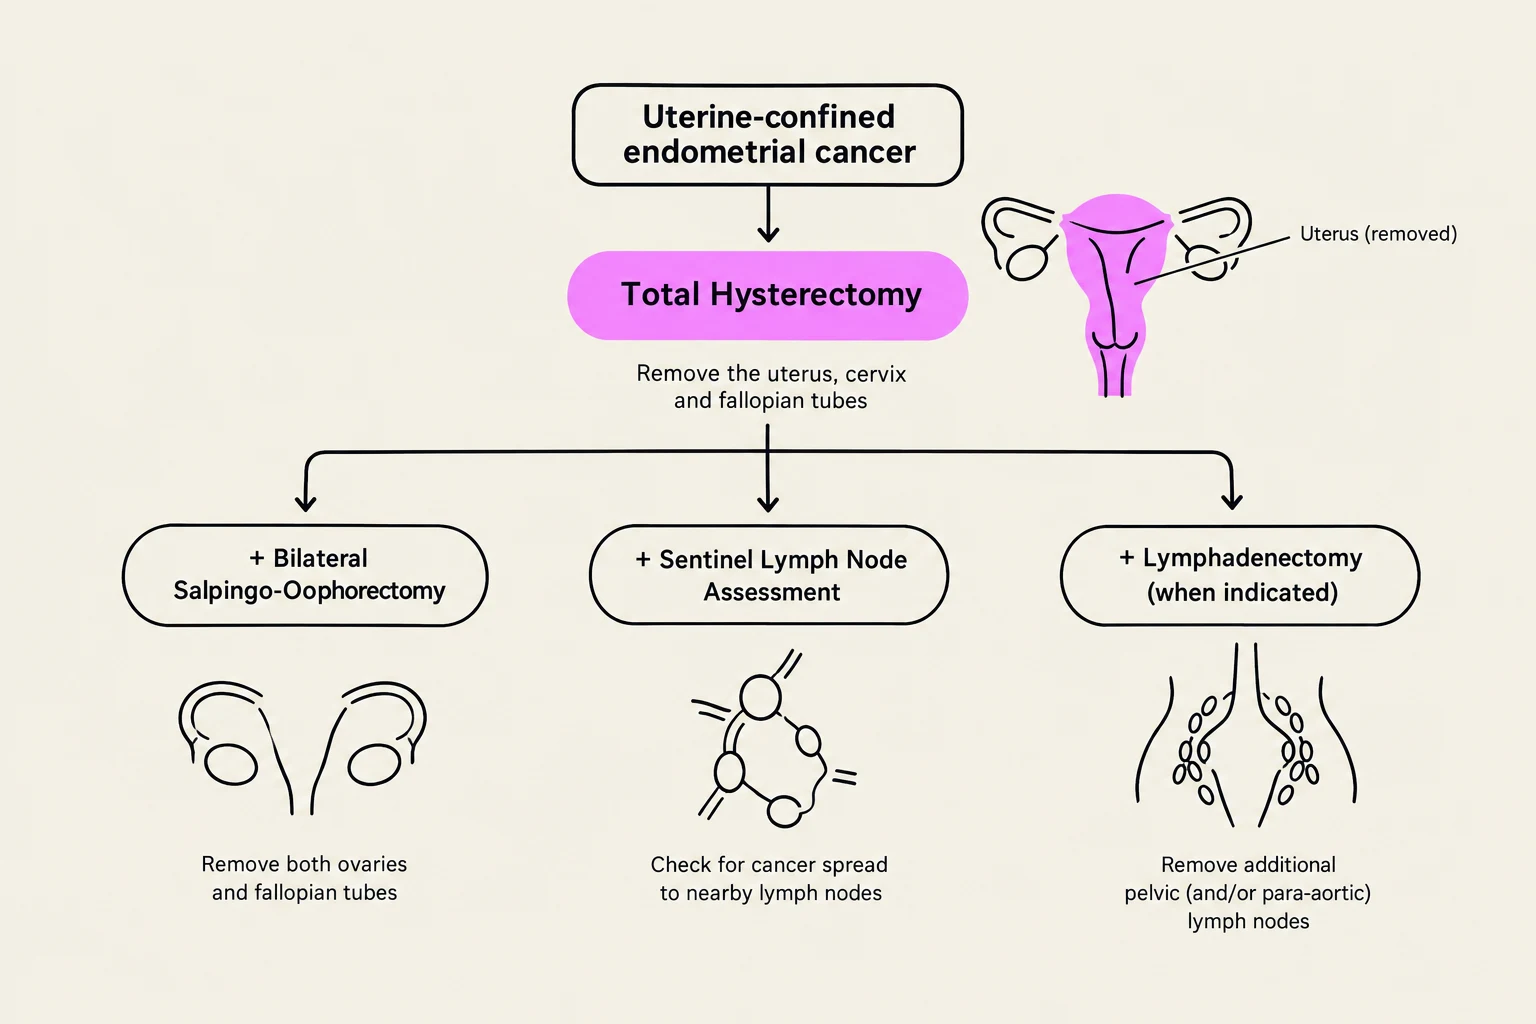
For patients with disease limited to the uterus who are suitable for surgery, the standard of care is a Total Hysterectomy (TH) combined with Bilateral Salpingo-Oophorectomy (BSO). To ensure accurate staging, surgical staging is performed to assess the extent of the disease within the pelvic and abdominal regions.
In certain select cases, such as premenopausal patients with very early-stage (Stage IA, Grade 1) endometrioid cancer and normal-appearing ovaries, ovarian preservation may be considered, provided there is no family history of Lynch syndrome or ovarian cancer and an absence of $p53$ abnormalities or lymphovascular space invasion (LVSI).
Clinical Note: Surgical staging is critical. The degree of staging required depends heavily on preoperative and intraoperative findings to determine if the disease is truly confined to the uterus.
Adjuvant Therapy for Low to High-Risk Disease
Once surgical staging is complete, the risk profile of the tumor dictates whether adjuvant therapy is necessary.
- Low-risk (Stage IA, Grade 1/2): Observation is often the preferred route. However, vaginal brachytherapy is strongly suggested for patients 60 years old or those with evidence of lymphovascular space invasion (LVSI).
- Intermediate to High-risk (Stage IB or Grade 3): For these patients, vaginal brachytherapy is preferred to reduce the risk of local recurrence while minimizing the toxicity associated with more extensive radiation.
- Advanced Adjuvant Options: While External Beam Radiation Therapy (EBRT) improves locoregional control, it has not consistently shown an overall survival (OS) benefit in low-risk patients. For high-risk uterine-confined disease (e.g., deep myometrial invasion), chemoradiotherapy—combining systemic therapy with EBRT or brachytherapy—may be considered, as supported by the PORTEC-3 trial.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated