Eating Disorders and Medication Nutrient Interactions
An overview of the distinctions between major eating disorders (Anorexia Nervosa, Bulimia Nervosa, Binge Eating Disorder) and the mechanisms by which medications influence nutritional status through absorption, metabolism, and excretion.
Understanding the intersection of psychological health and physiological stability is critical for healthcare providers. Eating disorders represent extreme disturbances in eating habits that can severely impact health or even lead to death. Simultaneously, the medications used to treat various conditions can create a complex web of interactions with nutrients, altering how the body absorbs, processes, and eliminates essential elements. This article explores the distinctions between major eating disorders and the mechanisms by which medications influence nutritional status.
Understanding Eating Disorders
Eating disorders are primarily characterized by a patient's relationship with food, eating patterns, and body image. While they share common psychological roots, such as an intense fear of being overweight, they manifest through very different physiological patterns.
Anorexia Nervosa
Anorexia nervosa is marked by relentless self-starvation in an effort to reduce body weight below normal. Patients often suffer from a distorted body image, perceiving themselves as overweight even when they are extremely underweight. Physical complications are severe and can include:
Brittle nails and dull, dry, or brittle hair.
Muscle atrophy, anemia, and lethargy.
Amenorrhea (absence of menstruation).
Electrolyte imbalances and metabolic acidosis or alkalosis.
Bulimia Nervosa
Bulimia nervosa involves recurrent episodes of binge eating followed by compensatory behaviors intended to rid the body of consumed calories. These behaviors include self-induced vomiting (purging), excessive exercise, fasting, or the overuse of laxatives and diuretics. Unlike anorexia, patients with bulimia are typically normal weight or slightly overweight. Physical signs include:
Chronic throat inflammation and dental decay due to gastric acid exposure.
Calluses on the knuckles (from purging).
Gastroesophageal reflux disease (GERD) and dehydration.
Binge Eating Disorder
Binge eating disorder is characterized by eating large quantities of food at one time with a loss of control. While patients experience intense feelings of shame, distress, and guilt, the defining difference is the absence of compensatory behaviors like purging or excessive exercise.
This illustration compares the core behaviors, body weight, key features, and health risks associated with anorexia and bulimia.
How Medications Impact Nutrition
Medications can influence a patient's nutritional status through three primary physiological pathways: absorption, metabolism, and excretion.
Medication Absorption
Most medications are absorbed in the small intestine. Several factors can impede this process:
Gastric Motility: Increased motility can move substances through the tract too quickly for full absorption.
Acidity/Alkalinity: Extreme changes in GI pH can hinder absorption. For example, histamine-2 blockers and proton pump inhibitors reduce stomach acidity, which can impede the absorption of Vitamin B12, iron, and folate.
Dietary Factors: High-fiber diets may decrease the absorption of certain medications.
To protect medications from being destroyed by stomach acid, they may be administered as enteric-coated tablets. Conversely, some medications like aspirin or ibuprofen are taken with food specifically to decrease gastric irritation.
Medication Metabolism
Metabolism occurs primarily in the liver, where substances are broken down into simpler forms through chemical and enzymatic processes. Certain substances and drugs can significantly alter these enzymatic pathways:
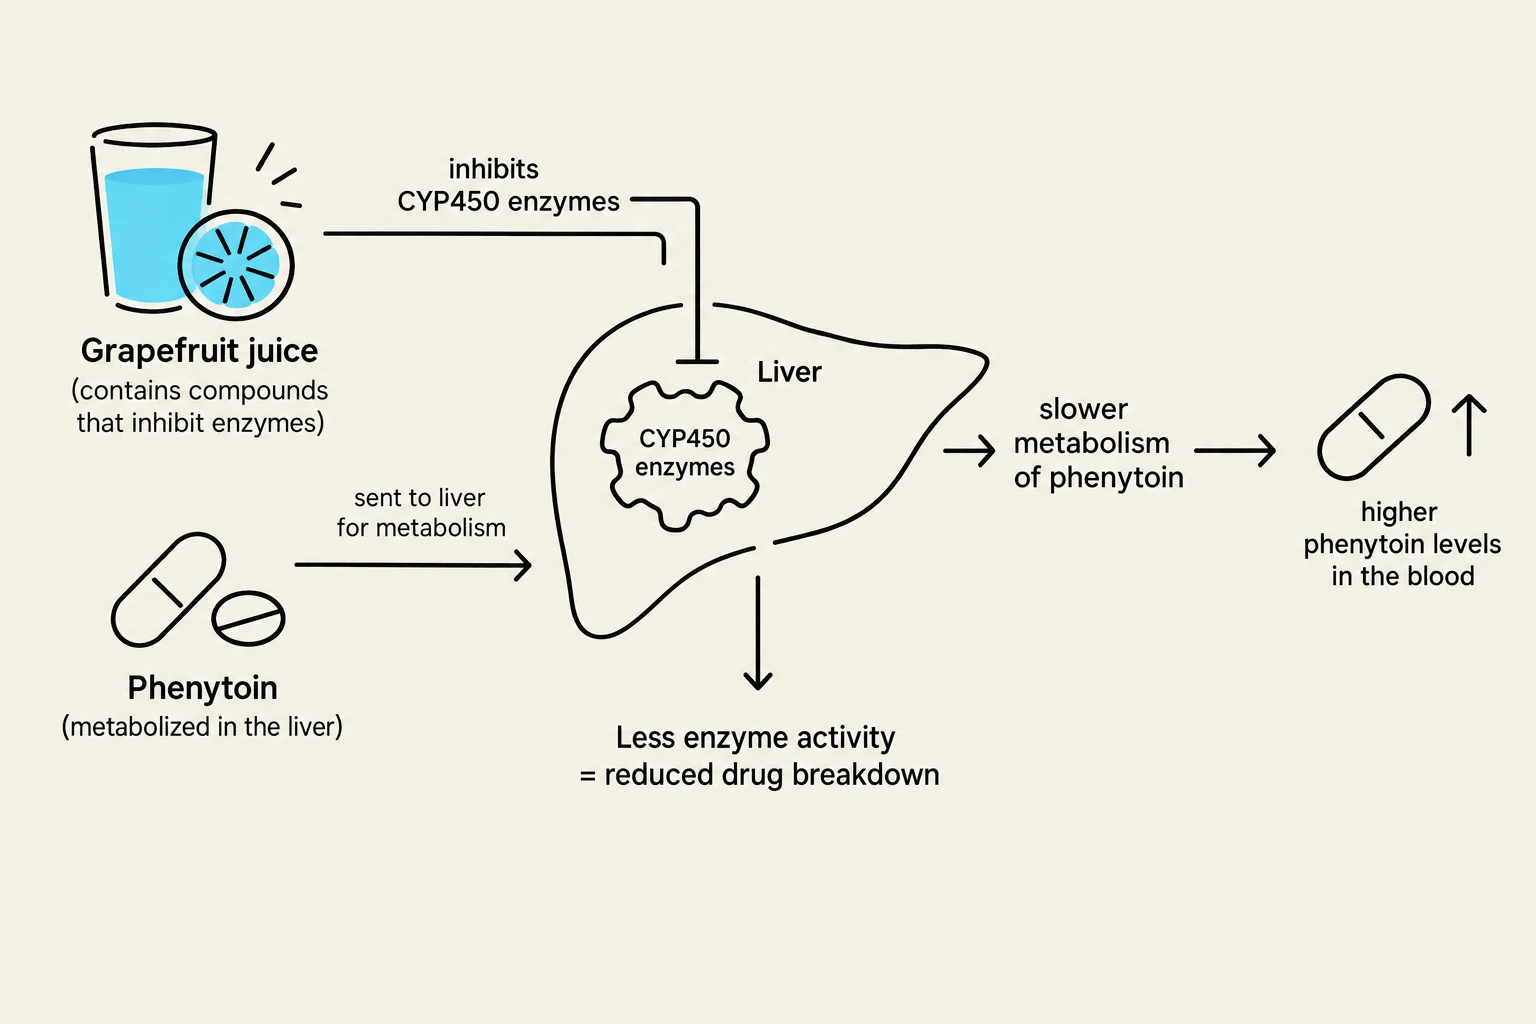
Grapefruit Juice: This can inhibit enzymes necessary for metabolism, potentially leading to increased medication toxicity by causing levels to rise significantly.
Phenytoin: This anticonvulsant induces liver enzymes that accelerate the metabolism of folate, Vitamin D, and Vitamin K.
Corticosteroids: These can lead to unintentional weight gain.
Exam Tip: When a patient is prescribed Warfarin (Coumadin), they must be educated to avoid foods with moderate to high levels of Vitamin K, as it can weaken the anticoagulant's effect. Additionally, herbal supplements like garlic, ginkgo, and ginseng should be avoided as they may enhance warfarin's effects, increasing the risk of hemorrhage.
This diagram illustrates how grapefruit juice inhibits CYP450 enzymes in the liver, leading to slower metabolism of phenytoin and consequently higher phenytoin levels in the blood.
Medication Excretion
Excretion is the removal of medications or their metabolites from the body, a process primarily managed by the kidneys. The rate of excretion is a critical factor in therapeutic effectiveness:
Slow Excretion: If the kidneys do not excrete the drug fast enough, blood levels can rise, leading to toxicity.
Rapid Excretion: If the drug is excreted too quickly, its therapeutic effect may be greatly reduced.
Electrolyte and Nutrient Excretion
Certain medications act as diuretics or alter metabolic pathways, causing the loss of vital nutrients through excretion:
Furosemide (Lasix): This diuretic increases the excretion of several electrolytes, including potassium, sodium, chloride, calcium, and magnesium. Nurses must monitor fluid and electrolyte status closely, as potassium supplementation is often required.
Isoniazid (INH): Used for tuberculosis, this medication increases the excretion of Vitamin B6. To prevent deficiency, patients are typically started on Vitamin B6 supplementation immediately.
The Lithium-Sodium Relationship
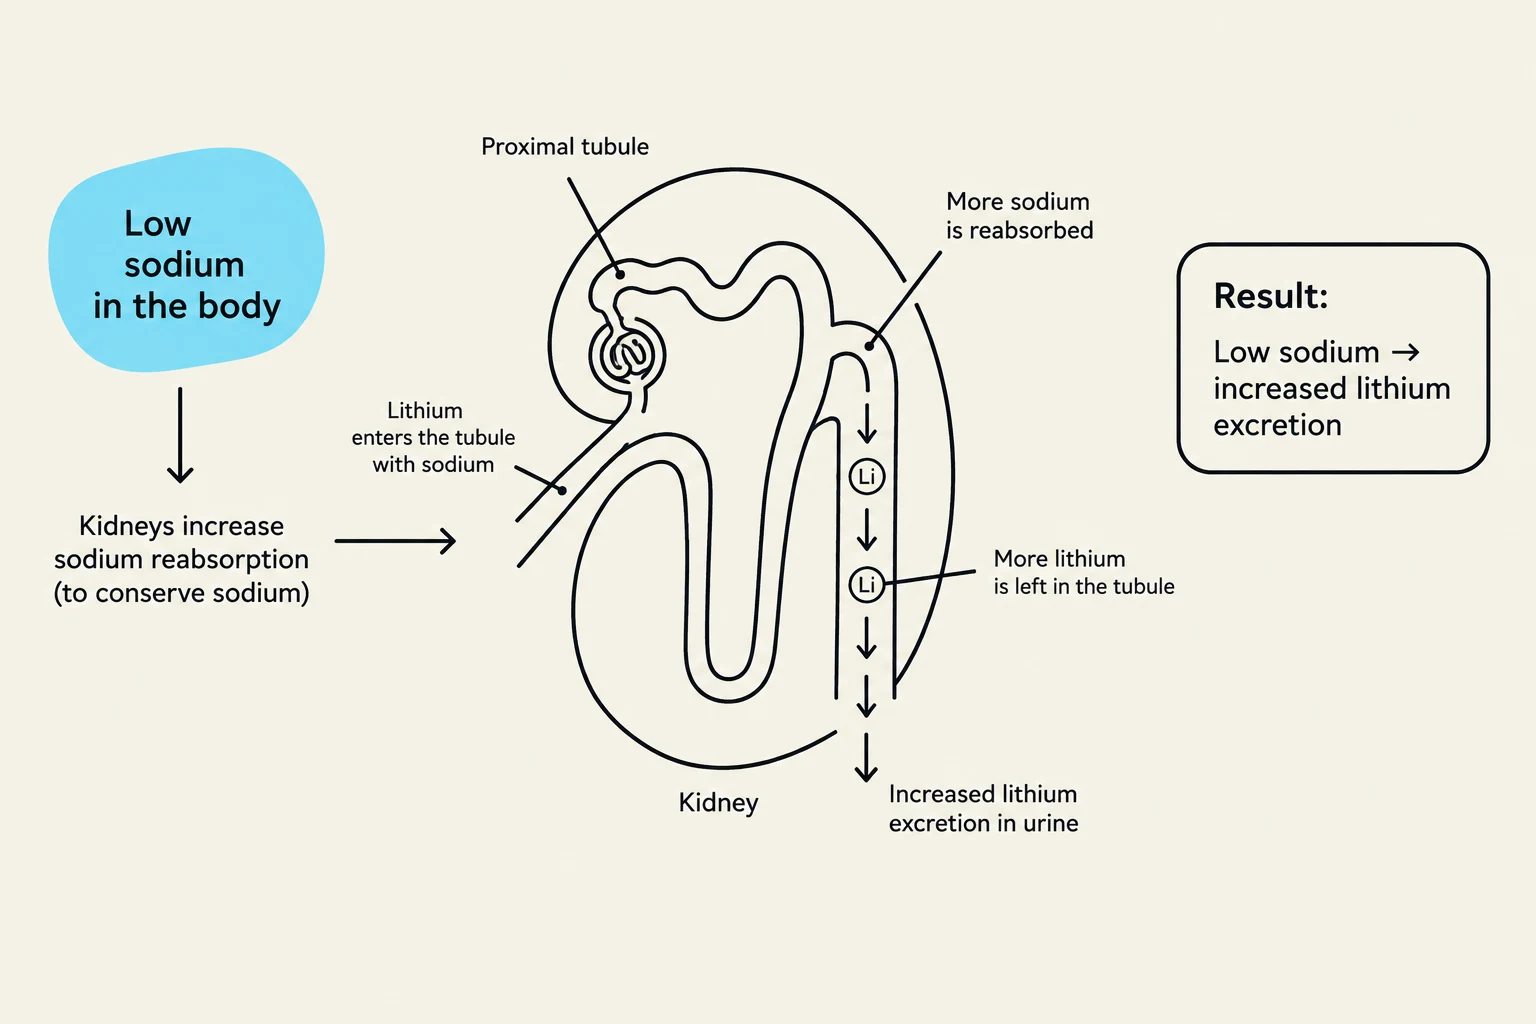
Lithium is a mood-stabilizing medication whose excretion is heavily influenced by the body's sodium levels. This relationship is a critical safety concern for nursing staff:
If Sodium is Low→Kidneys retain Lithium→Risk of ToxicityIf Sodium is High→Kidneys excrete Lithium→Reduced Therapeutic Effect
This diagram illustrates how low sodium levels in the body can lead to increased lithium excretion by the kidneys. When sodium is low, the kidneys increase sodium reabsorption to conserve it. This process also leads to more lithium being reabsorbed into the tubule, and consequently, more lithium is excreted in the urine.
Clinical Note: Monitoring "Intake and Output" (I&Os) is essential when managing patients on these medications. The "I" includes oral fluids, IV fluids, and enteral/parenteral nutrition, while the "O" includes urine, emesis, liquid stool, blood, and suctioned gastric contents.
Summary Table of Key Interactions
Medication
Primary Mechanism
Impacted Nutrient/Electrolyte
Clinical Consequence
Proton Pump Inhibitors
Absorption
Vitamin B12, Iron, Folate
Nutrient deficiency
Phenytoin
Metabolism
Folate, Vit D, Vit K
Accelerated depletion
Furosemide
Excretion
K+, Na+, Cl-, Ca2+, Mg2+
Electrolyte imbalance
Isoniazid (INH)
Excretion
Vitamin B6
Deficiency (requires supplement)
Lithium
Excretion
Sodium (Na+)
Toxicity (if Na+ is low)
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.