An overview of diabetes mellitus, covering diagnostic methods, collaborative care strategies including nutritional therapy and drug management, self-monitoring of blood glucose, and the management of acute complications like hypoglycemia, DKA, and HHS.
Diabetes mellitus is a chronic multisystem disease characterized by abnormal insulin production, impaired insulin utilization, or a combination of both. Because insulin is the primary "storage hormone" responsible for transporting glucose from the bloodstream into the cells for energy, its dysfunction leads to persistent hyperglycemia. Effective management requires a multifaceted approach involving precise diagnosis, collaborative care, and rigorous self-monitoring to prevent both acute and chronic complications.
Diabetes Mellitus Diagnostic Studies
To diagnose diabetes, clinicians rely on four primary laboratory methods. These tests measure different aspects of glucose metabolism to provide a clear picture of a patient's glycemic status.
Hemoglobin A1C Test
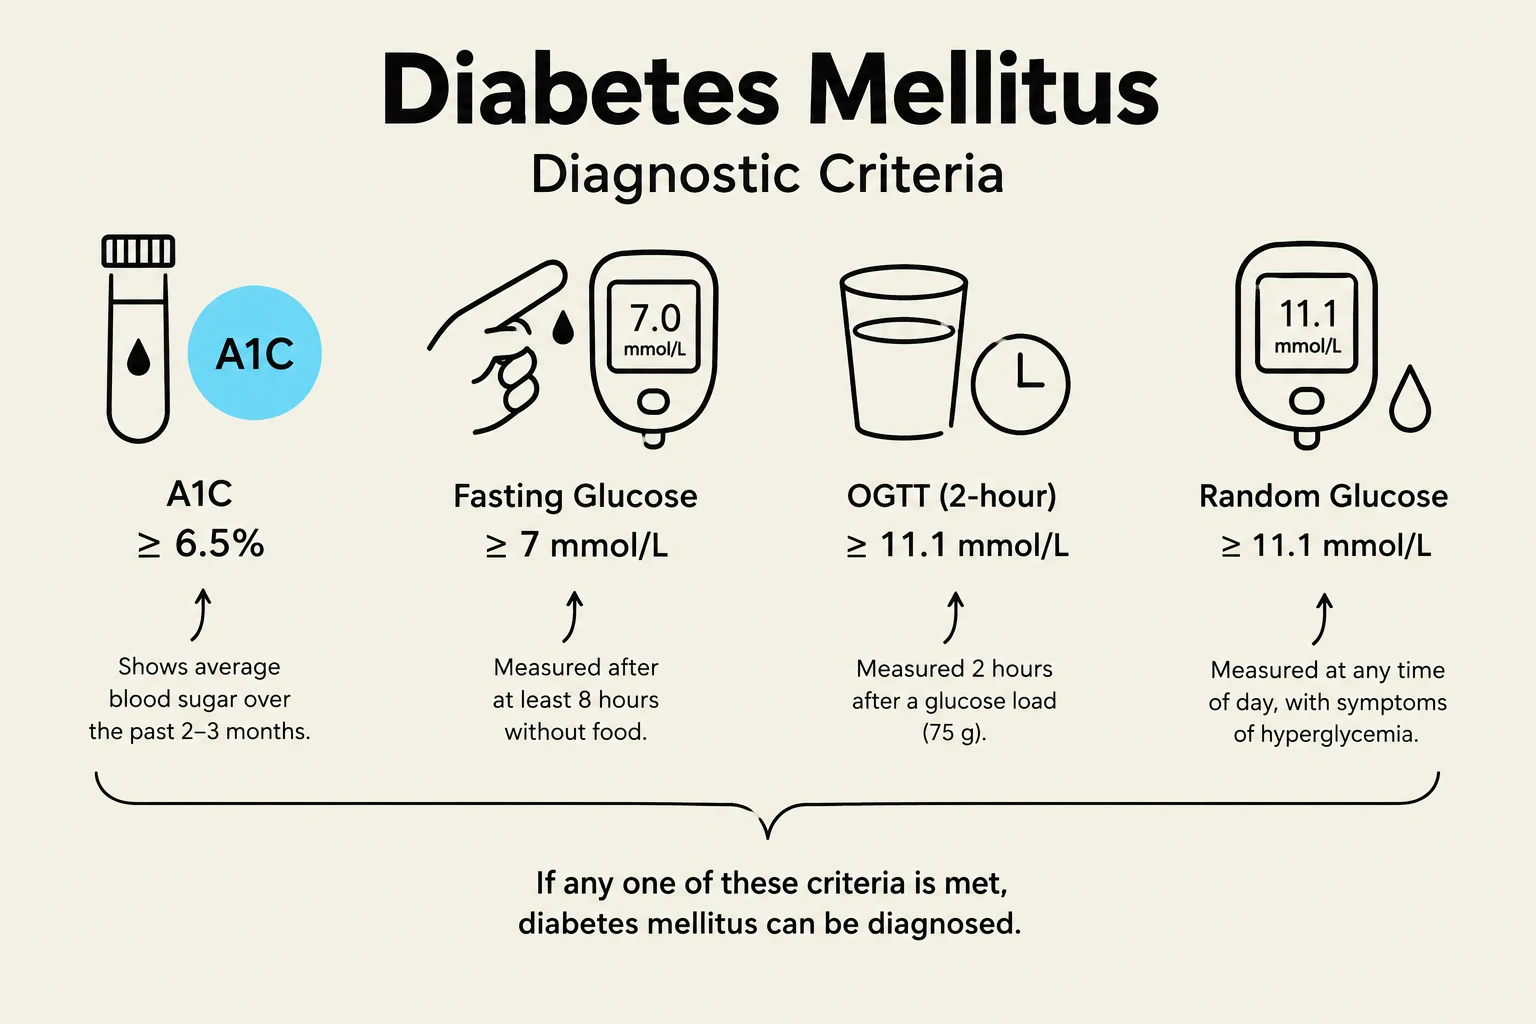
The Hemoglobin A1C test is a highly recommended diagnostic tool because it provides a long-term view of glycemic control. It measures the amount of glucose attached to hemoglobin molecules over the lifespan of a red blood cell, which is approximately 120 days. A level of ≥6.5% is indicative of diabetes.
Fasting Plasma Glucose (FPG)
This test measures blood glucose levels after the patient has not eaten for a specified period. A fasting plasma glucose level of ≥7 mmol/L is a criterion for a diabetes diagnosis.
Oral Glucose Tolerance Test (OGTT)
The OGTT involves administering a specific glucose load—typically 75 g—to the patient. The patient's blood glucose is then measured two hours later; a level ≥11.1 mmol/L indicates diabetes.
Random or Casual Plasma Glucose
In cases where a patient presents with classic symptoms of diabetes (such as polyuria, polydipsia, and polyphagia), a random or casual plasma glucose measurement of ≥11.1 mmol/L can be used for diagnosis.
Diagnostic criteria for diabetes mellitus, including A1C, fasting glucose, OGTT, and random glucose levels.
Collaborative Care Management
Managing diabetes is not the responsibility of the clinician alone; it requires a collaborative care model involving the patient, diabetes nurse educators, and registered dietitians. This team-based approach integrates several pillars of care:
Nutritional Therapy
Nutritional therapy is considered the cornerstone of diabetes care. While a "carbohydrate-free" diet is neither appropriate nor recommended, nutrient balance is essential.
Carbohydrates: Patients should be mindful of the glycemic index (GI) and ensure that less than 10% of daily energy comes from sucrose (sugar).
Fats: Intake of combined saturated and trans-fats should be kept below 7% of total energy, with an emphasis on polyunsaturated omega-3 fatty acids.
Protein: Protein should contribute approximately 15% to 20% of total energy, though some guidelines suggest limiting it to 15%.
Alcohol: Patients must be cautioned that alcohol can cause severe hypoglycemia and promotes hypertriglyceridemia.
Drug Therapy
Pharmacological intervention varies depending on the type of diabetes and the patient's needs.
Insulin Therapy:
Exogenous insulin is required for all Type 1 diabetics and is prescribed for Type 2 diabetics when lifestyle changes and oral agents are insufficient. Insulin is administered subcutaneously (the abdomen is the preferred site) and cannot be taken orally because it would be digested.
Oral Antihyperglycemic Agents (OHAs):
These are used primarily in Type 2 diabetes to improve insulin sensitivity, decrease hepatic glucose production, or increase insulin secretion. Common classes include biguanides, sulphonylureas, and α-glucosidase inhibitors.
Exercise
Exercise is an essential component of management as it increases insulin receptor sites, lowers blood glucose, and aids in weight loss. However, patients should monitor glucose levels before, during, and after exercise to prevent hypoglycemia, and may need small carbohydrate snacks during activity.
Self-Monitoring of Blood Glucose (SMBG)
SMBG is a critical skill that enables patients to make real-time decisions regarding their diet, exercise, and medication.
Clinical Tip: Proper SMBG Technique
To ensure accurate results and minimize pain, patients should follow these steps:
Wash hands with soap and water. Avoid alcohol swabs, as they may artificially lower results if not dried completely.
Promote blood flow. Wash hands in warm water or let the arm hang down for a few minutes before the puncture.
Minimize pain. Use the side of the finger pad rather than the center, as there are fewer nerve endings there.
Safety. Always use a new lancet for every puncture.
This illustration demonstrates the steps for performing a finger-stick blood glucose test, including washing hands, preparing the lancing device, pricking the side of the finger, and collecting blood on a test strip. It also highlights key points for the procedure.
Managing Complications: Hypoglycemia vs. Hyperglycemia
Patients must be able to distinguish between the two most common acute complications: hypoglycemia (low blood sugar) and hyperglycemia (high blood sugar).
Hypoglycemia
Defined as blood glucose <4 mmol/L, hypoglycemia can cause hunger, fatigue, confusion, diaphoresis (sweating), and tremors.
The 15-15 Rule: If the patient is alert, provide 15 g of a simple carbohydrate (e.g., 175 mL of juice), wait 15 minutes, and recheck. Repeat until glucose is >4 mmol/L.
Severe cases: If the patient is unconscious, administer 1 mg of glucagon IM/subcutaneously or 20–50 mL of 50% dextrose IV.
Hyperglycemia and Acute States
Hyperglycemia presents with polyuria, polydipsia, and polyphagia. Two serious acute complications are:
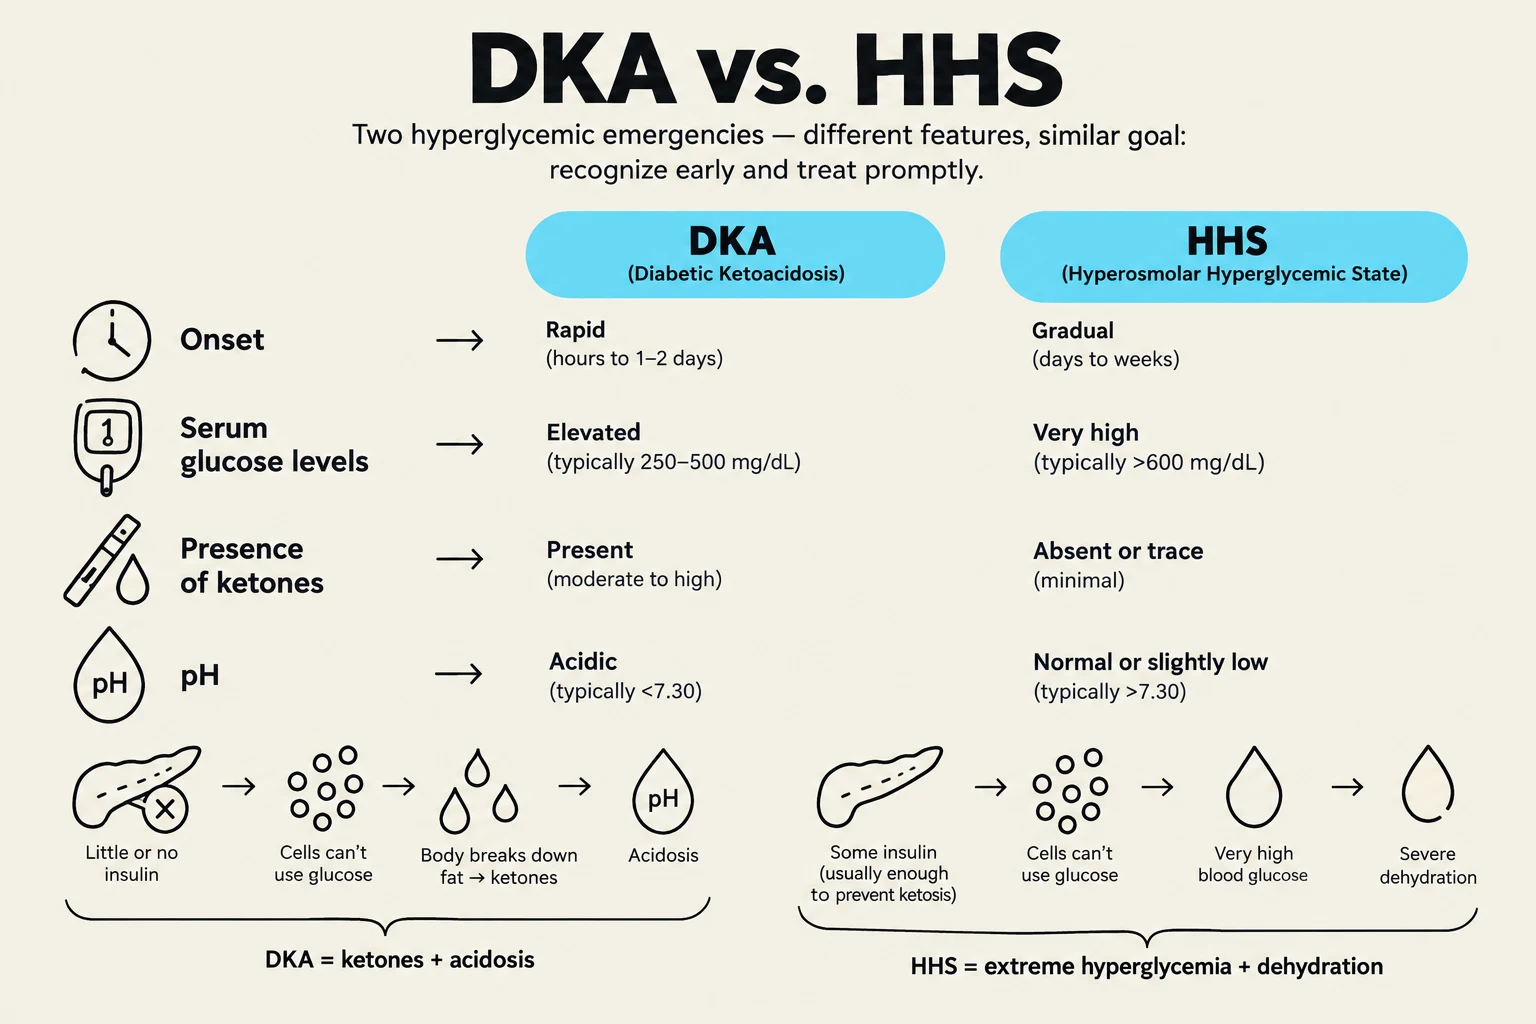
Diabetic Ketoacidosis (DKA): More common in Type 1; characterized by ketones in the urine, metabolic acidosis, and "fruity" breath.
Hyperosmolar Hyperglycemic State (HHS): More common in Type 2 (especially those >60 years); characterized by extremely high glucose (>34 mmol/L) and profound dehydration, but typically without significant ketosis.
This diagram compares Diabetic Ketoacidosis (DKA) and Hyperosmolar Hyperglycemic State (HHS), two hyperglycemic emergencies, highlighting their distinct features and a shared goal of prompt recognition and treatment.
Exam Alert: Somogyi Effect vs. Dawn Phenomenon
Both result in high morning glucose, but the cause and treatment are opposites:
Somogyi Effect: "So Much Insulin." Occurs due to nighttime hypoglycemia followed by a rebound. Treatment: Decrease insulin or adjust timing.
Dawn Phenomenon: "Dial it up." Occurs due to natural hormone release (growth hormone/cortisol) in the predawn hours. Treatment: Increase insulin or adjust timing.
Summary Table for Quick Review
Condition
Key Feature
Primary Management
Hypoglycemia
Glucose <4 mmol/L
15 g simple carbs (15-15 Rule)
DKA
Ketones + Acidosis
IV fluids + Insulin
HHS
Extreme Hyperglycemia
Aggressive fluid replacement
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.