


In clinical neurology, observing a patient's physical posture during a period of unconsciousness or neurological distress can provide critical diagnostic clues. When the brain suffers significant injury or dysfunction, the body may exhibit abnormal posturing—involuntary, rigid movements that reflect the location and severity of the neurological damage.
Two of the most significant types of abnormal posturing are decorticate and decerebrate posturing. While they may look similar to an untrained eye due to the rigidity of the lower limbs, they are fundamentally different in how the upper body responds to neurological stimuli. Understanding these differences is essential for assessing the depth of brain injury and the level of brainstem involvement.
Understanding Abnormal Posturing
Abnormal posturing occurs when the central nervous system can no longer coordinate smooth, voluntary movement, leading to involuntary muscle contractions that hold the body in specific, rigid positions. These postures are often observed when a patient is in a supine position (lying on their back) and is unresponsive to external stimuli.
The distinction between these postures often hinges on whether the body is exhibiting flexion (bending toward the center) or extension (straightening out).
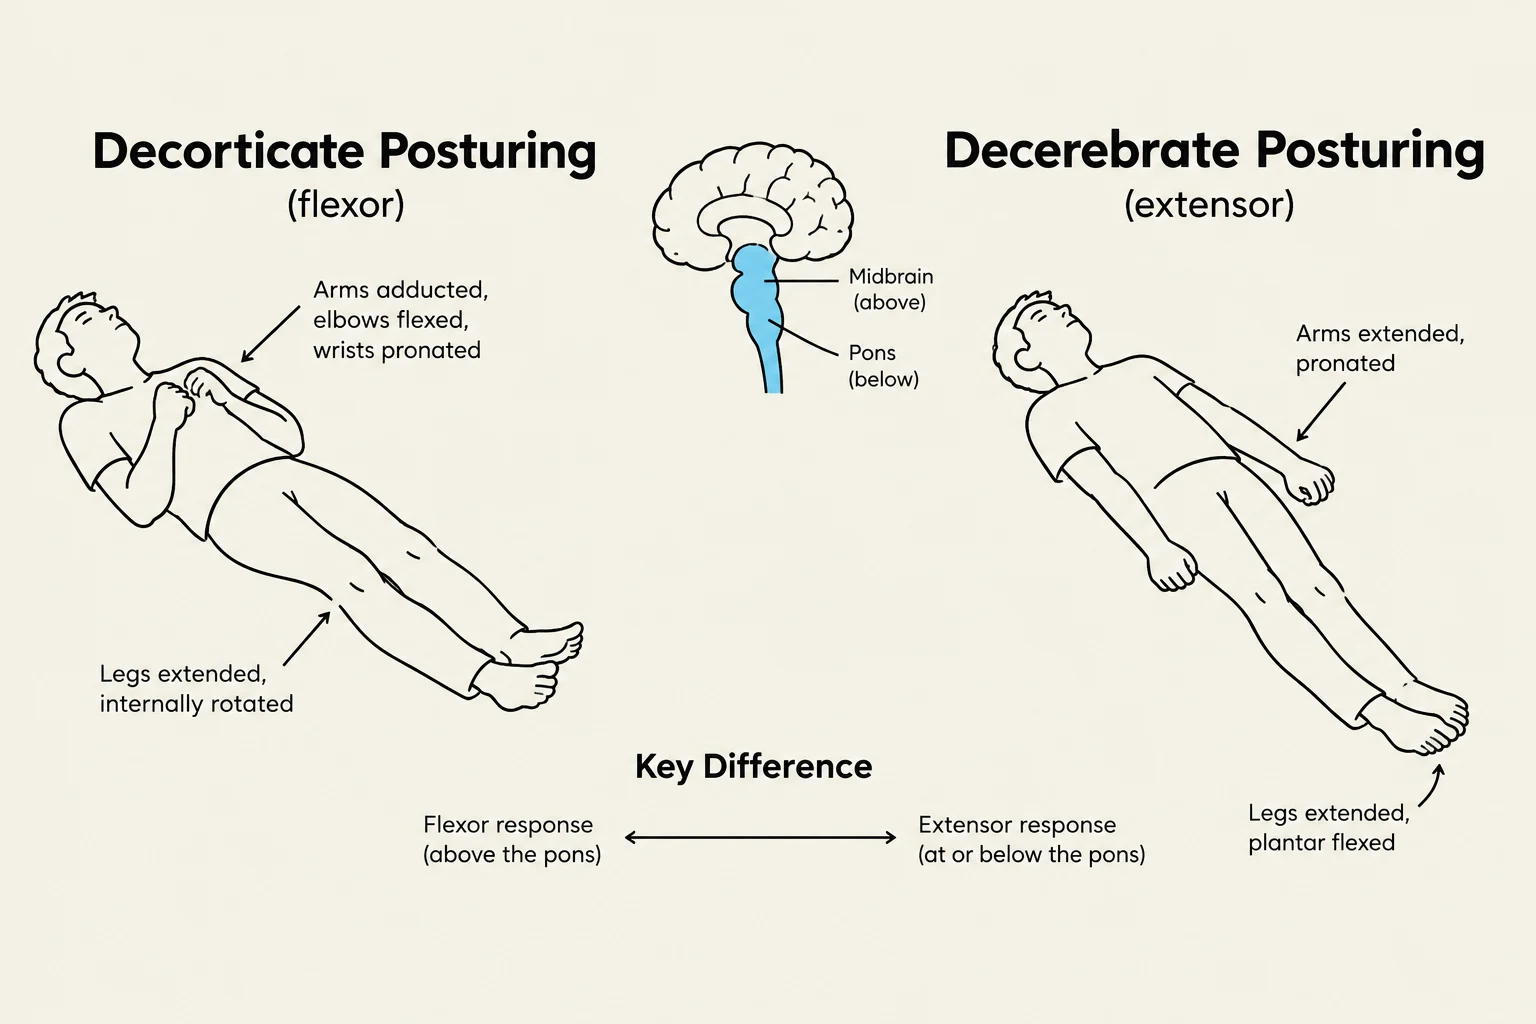
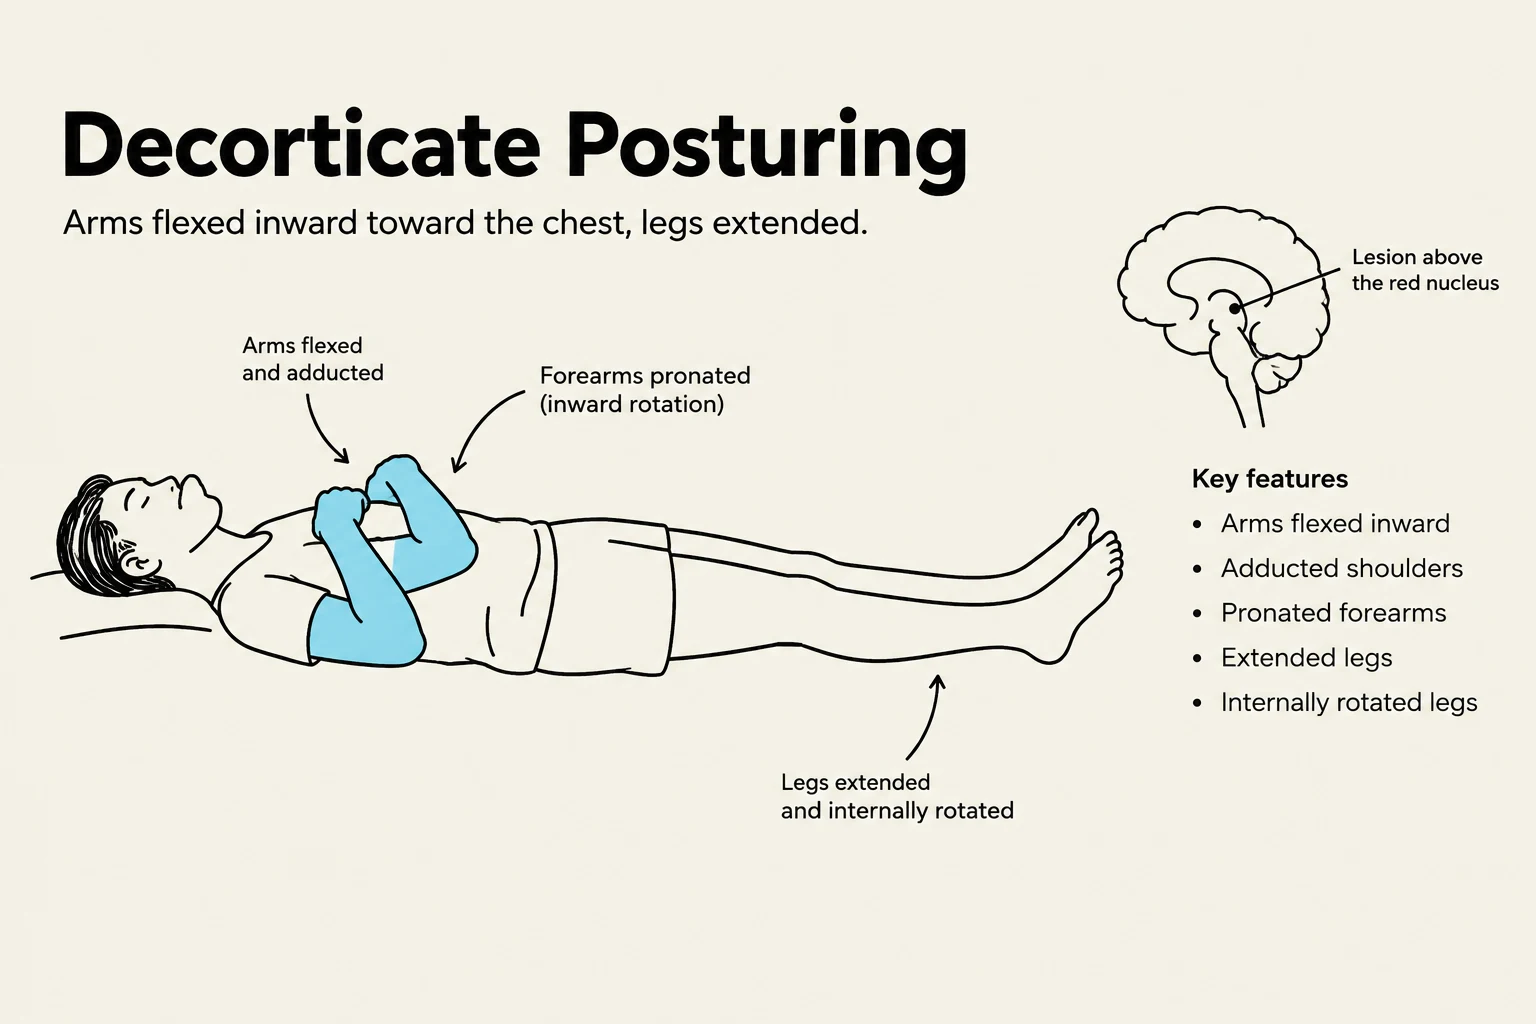
Decorticate Posturing: The "Flexed" Response
Decorticate posturing is characterized by a "flexed" appearance, where the upper body limbs are pulled inward toward the "core" or chest area.

Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated