Dawn Phenomenon vs. Somogyi Effect in Diabetes Management
This content explains the differences between the Dawn Phenomenon and the Somogyi Effect, two causes of morning hyperglycemia in individuals with diabetes. It details their physiological mechanisms, diagnostic methods, and contrasting treatment strategies.
For many individuals living with diabetes, waking up to a high blood glucose reading can be a source of significant confusion and frustration. After a night of not eating, one might logically expect blood sugar levels to be stable or even lower. However, many patients experience "morning hyperglycemia"—a spike in glucose levels upon waking.
While there are many reasons for high blood sugar, two specific physiological processes are often to blame: the Dawn Phenomenon and the Somogyi Effect. Although they result in the same outcome (high morning glucose), their causes, nighttime patterns, and required treatments are diametrically opposed. Understanding the difference is critical for safe and effective diabetes management.
The Dawn Phenomenon: The Body’s Natural Wake-Up Call
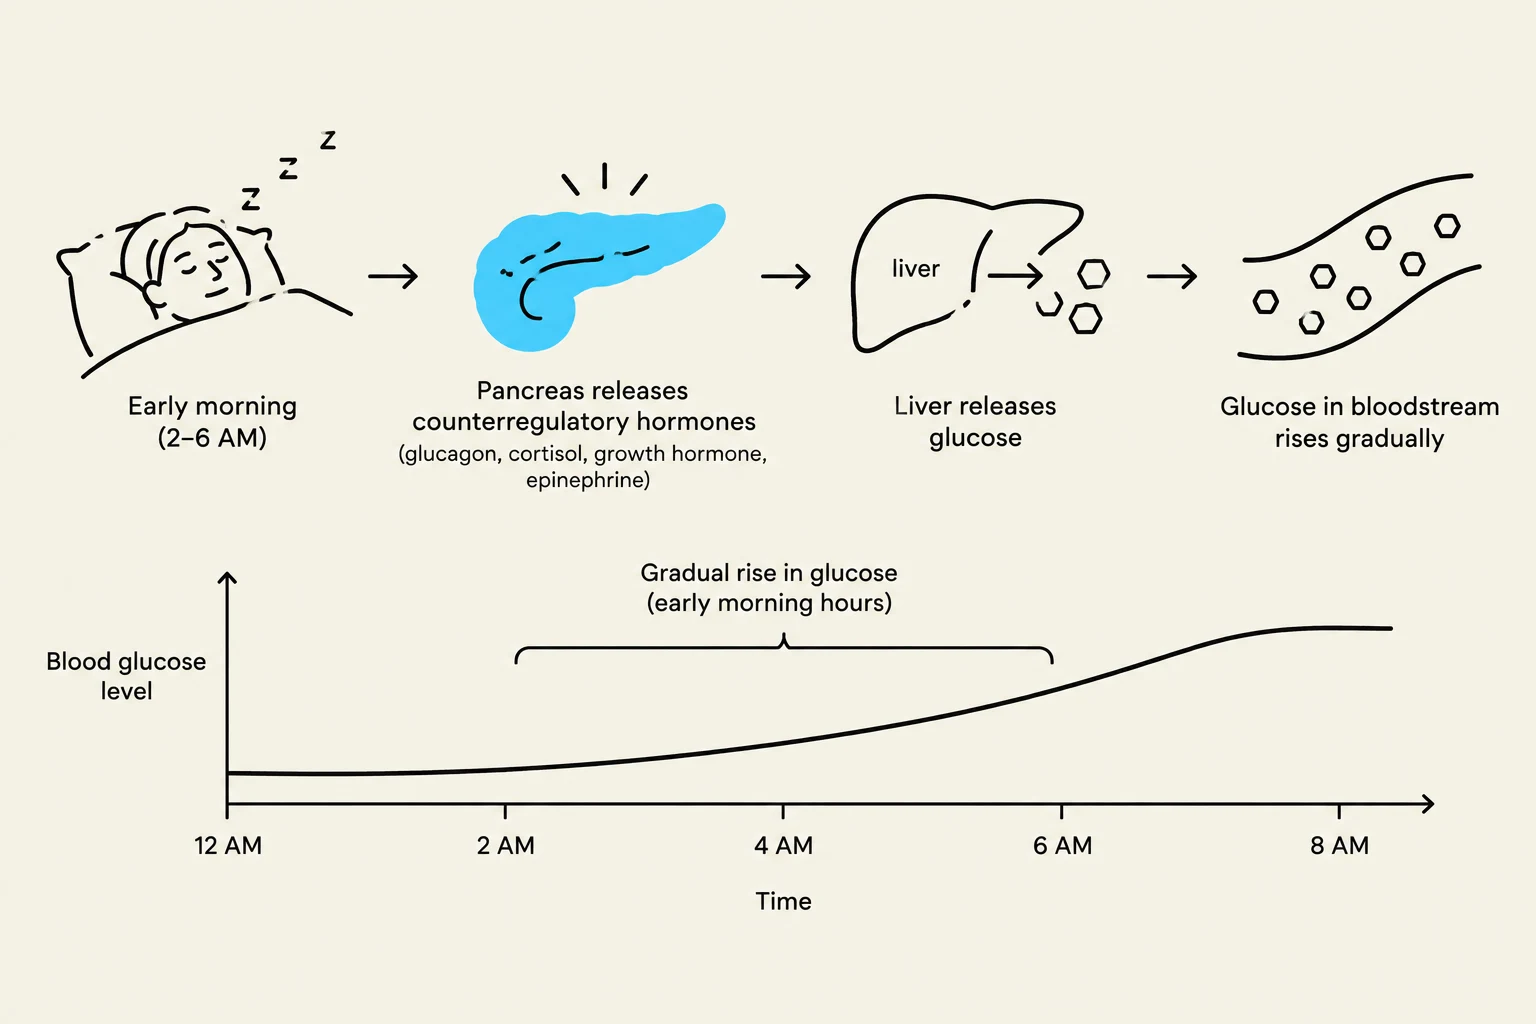
The Dawn Phenomenon is a natural physiological process where blood glucose levels rise in the early morning hours. As the body prepares to wake up, it undergoes a series of hormonal shifts designed to provide the necessary energy for the day ahead.
In a healthy metabolic system, the body releases "counter-regulatory hormones" to signal the liver to release stored glucose into the bloodstream. These hormones include:
Cortisol
Glucagon
Epinephrine
In people with diabetes, the "Insulin Guards"—the insulin required to move that glucose into the cells—are either insufficient or unable to respond effectively to these rising sugar levels. Consequently, the glucose accumulates in the bloodstream, leading to high fasting levels in the morning.
Diagram illustrating the physiological process of glucose regulation in the early morning hours, involving the pancreas releasing counterregulatory hormones, the liver releasing glucose, and a subsequent gradual rise in blood glucose levels.
Mnemonic for Students:DAWN = Day Approaching Without Night-low.
The Somogyi Effect: The Chaotic Rebound
The Somogyi Effect is a much more volatile process. Unlike the gradual rise seen in the Dawn Phenomenon, the Somogyi Effect is a "rebound" response to an underlying problem: nighttime hypoglycemia.
This typically occurs when there is too much insulin in the system during the late-night or early-morning hours. If insulin levels are too high, they push glucose levels down too far, causing blood sugar to drop dangerously low during the night.
When the body detects this sudden drop (hypoglycemia), it enters a state of panic. It triggers an emergency release of counter-regulatory hormones—Epinephrine, Cortisol, and Glucagon—to force the liver to dump massive amounts of glucose into the blood to save the body from the low. By the time the patient wakes up, the blood sugar has "rebounded" to a high level.
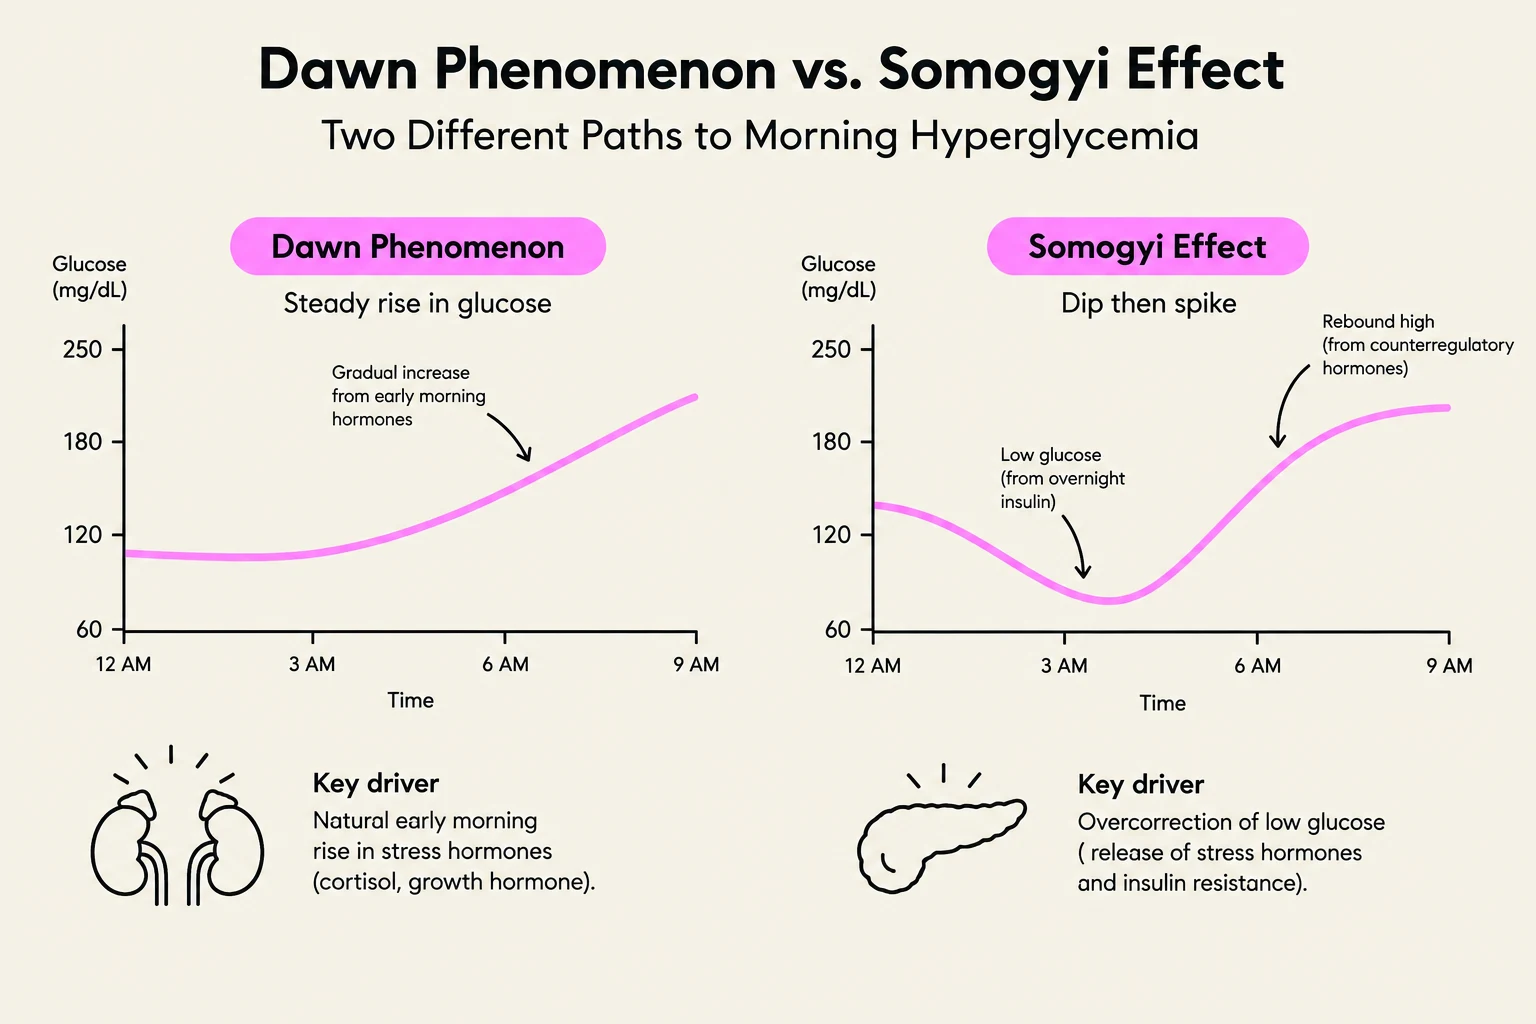
The Somogyi effect describes how nighttime hypoglycemia can lead to rebound hyperglycemia in the morning due to the body releasing counterregulatory hormones and stored glucose.
Mnemonic for Students:SOMOGYI = Sugar Overnight Makes Overreaction, Glucose Yields Increase.
How to Distinguish Between the Two
Because both phenomena result in morning hyperglycemia, a patient cannot distinguish between them simply by looking at their morning finger-stick reading. The "Golden Rule" for diagnosis is to check blood glucose levels in the middle of the night, specifically around 3:00 a.m..
Feature
Dawn Phenomenon
Somogyi Effect
Nighttime Glucose (3 a.m.)
Normal or High
Low (Hypoglycemia)
Primary Cause
Natural hormone surge
Excessive nighttime insulin
Morning Result
High Blood Sugar
High Blood Sugar (Rebound)
This graphic illustrates two distinct physiological responses, the Dawn Phenomenon and the Somogyi Effect, both leading to morning hyperglycemia. The Dawn Phenomenon describes a steady rise in glucose due to early morning hormones, while the Somogyi Effect involves a dip in glucose followed by a rebound high, driven by overcorrection of low glucose and counterregulatory hormones.
Clinical Case Studies
To better understand these concepts, let's examine two common clinical scenarios.
Case 1: The Steady Rise
A 16-year-old boy with type 1 diabetes wakes up with fasting blood glucose levels of 210–230 mg/dL. He follows his insulin regimen strictly and does not experience night sweats or shaking. When his physician asks him to check his glucose at 3:00 a.m., the result is 165 mg/dL.
Diagnosis:Dawn Phenomenon.
Reasoning: The 3 a.m. reading is normal/high, and there are no symptoms of nighttime hypoglycemia.
Case 2: The Rebound
A 12-year-old girl with type 1 diabetes presents with morning glucose of 240 mg/dL. Her mother reports that the child often has nightmares and night sweats. A 3:00 a.m. glucose check reveals a level of 52 mg/dL.
Diagnosis:Somogyi Effect.
Reasoning: The 3 a.m. reading shows hypoglycemia, which triggered the body's emergency glucose release.
Treatment Strategies
Correcting these issues requires opposite approaches. Treating a Somogyi Effect as if it were the Dawn Phenomenon can be dangerous, as adding more insulin to a patient already experiencing nighttime lows will worsen the hypoglycemia.
To fix Somogyi Effect: Decrease the nighttime insulin dose or provide a small nighttime snack to prevent the initial drop.
To fix Dawn Phenomenon: Adjust insulin timing, such as administering insulin later in the evening (e.g., around 22:00).
Exam Tip: If a question mentions "night sweats," "nightmares," or "shaking" alongside high morning sugar, think Somogyi Effect immediately. These are classic signs of nighttime hypoglycemia.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.