Cytoreductive Surgery for Recurrent Ovarian Cancer
This content explains the role of cytoreductive surgery in managing recurrent ovarian cancer, focusing on patient selection, clinical trials, and predictive models like the AGO Score and iMODEL.
When ovarian cancer returns after initial treatment, clinicians face a critical decision: should the patient undergo secondary cytoreductive surgery, or should treatment proceed directly to systemic therapy? While the goal of surgery is to remove as much visible tumor as possible—ideally achieving a complete gross resection (CGR)—the decision is complex. Current evidence suggests that surgery is not a replacement for systemic treatment but rather an additive therapy that works most effectively when followed by platinum-based chemotherapy.
The Goal of Cytoreduction and the Importance of Resection
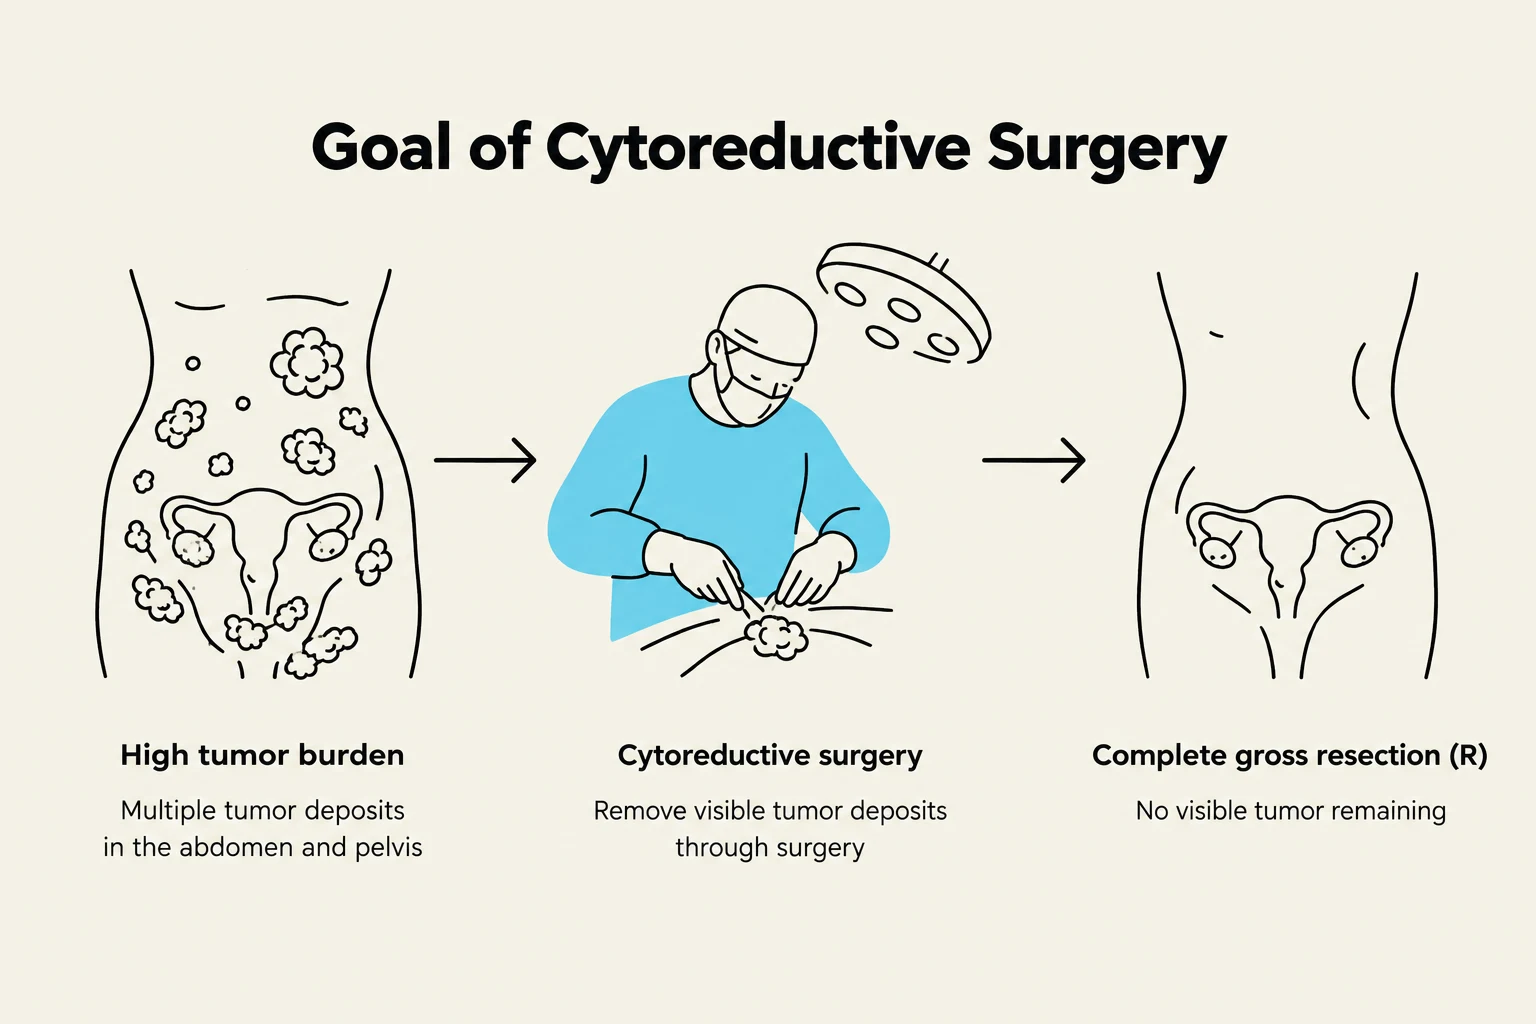
In the context of recurrent ovarian cancer, cytoreductive surgery (also known as debulking) aims to reduce the tumor burden to the greatest extent possible. The ultimate clinical objective is to achieve a complete resection rate (often referred to as R0 resection), meaning no macroscopic residual disease remains.
The impact of surgery on patient outcomes is heavily dependent on this surgical success. Clinical data indicates that the survival benefit is most pronounced in patients who achieve complete resection. If surgery fails to achieve a complete resection, the potential for improved survival diminishes, and the patient may face unnecessary surgical morbidity.
This diagram illustrates the goal of cytoreductive surgery, showing the progression from a high tumor burden to complete gross resection.
Analyzing the Landmark Clinical Trials
The debate over the utility of surgery in recurrent disease has been shaped by several major prospective randomized trials. These studies differ significantly in their design, patient selection, and outcomes.
The DESKTOP III Trial: A Positive Milestone
The AGO DESKTOP III trial is considered a landmark study because it utilized a validated selection process for both patients and surgical centers. By selecting patients based on the AGO Score, the trial demonstrated a significant survival benefit.
Overall Survival (OS): The median OS was 53.7 months in the surgery arm compared to 46.0 months in the non-surgery arm (Hazard Ratio [HR] 0.75; p=0.02).
Progression-Free Survival (PFS): The median PFS was significantly improved at 18.4 months versus 14.0 months (p<0.001).
The SOC-1 Trial: Supporting PFS Benefits
The SGOG SOC-1 trial, conducted in academic centers in China, also provided support for surgery, specifically regarding disease control. Using the iMODEL selection criteria, the trial showed a significant improvement in Progression-Free Survival (PFS), with a median of 17.4 months in the surgery group compared to 11.9 months in the non-surgery group (p<0.001). However, at the time of reporting, the overall survival data remained immature.
The GOG-213 Trial: The Outlier
In contrast to the positive findings of DESKTOP III and SOC-1, the GOG-213 trial did not show a significant benefit in either OS or PFS. Several factors may explain this discrepancy:
Study Design: GOG-213 included two studies in one, involving Bevacizumab (an anti-angiogenic agent).
Selection Criteria: Unlike the highly selective AGO or iMODEL approaches, GOG-213 used more individualized selection.
The Bevacizumab Factor: There is a clinical question of whether the use of Bevacizumab might "replace" the impact of surgery or if surgery becomes less beneficial when such potent systemic agents are used.
Exam Tip: When comparing these trials, remember that DESKTOP III and SOC-1 used rigorous, model-based pre-operative selection (AGO Score and iMODEL, respectively), whereas GOG-213 had a more heterogeneous population and included Bevacizumab, which may have masked the surgical benefit.
Precision Patient Selection: AGO Score and iMODEL
To avoid the pitfalls seen in trials like GOG-213, clinicians use predictive models to identify patients most likely to benefit from surgery.
The AGO Score
Developed through the DESKTOP I and II studies, the AGO Score is used to predict the likelihood of achieving complete gross resection (CGR). A patient is considered "AGO Score positive" if they meet all three of the following criteria:
ECOG performance status = 0 (excellent functional status).
No residual disease after primary surgery (or initially FIGO stage I/II).
Absence of ascites (defined as <500 mL).
The iMODEL Selection Criteria
The iMODEL is a more complex scoring system derived from pooled analyses of retrospective studies. It considers a broader range of impact factors to predict resectability:
FIGO stage (I/II vs. III/IV)
Residual disease (RD) after primary surgery
Platinum-free interval (PFI) (longer intervals, ≥16 months, are more favorable)
ECOG performance status (0–1 is ideal)
CA125 levels at recurrence (≤105 U/ml is more favorable)
Presence of ascites (absence is more favorable)
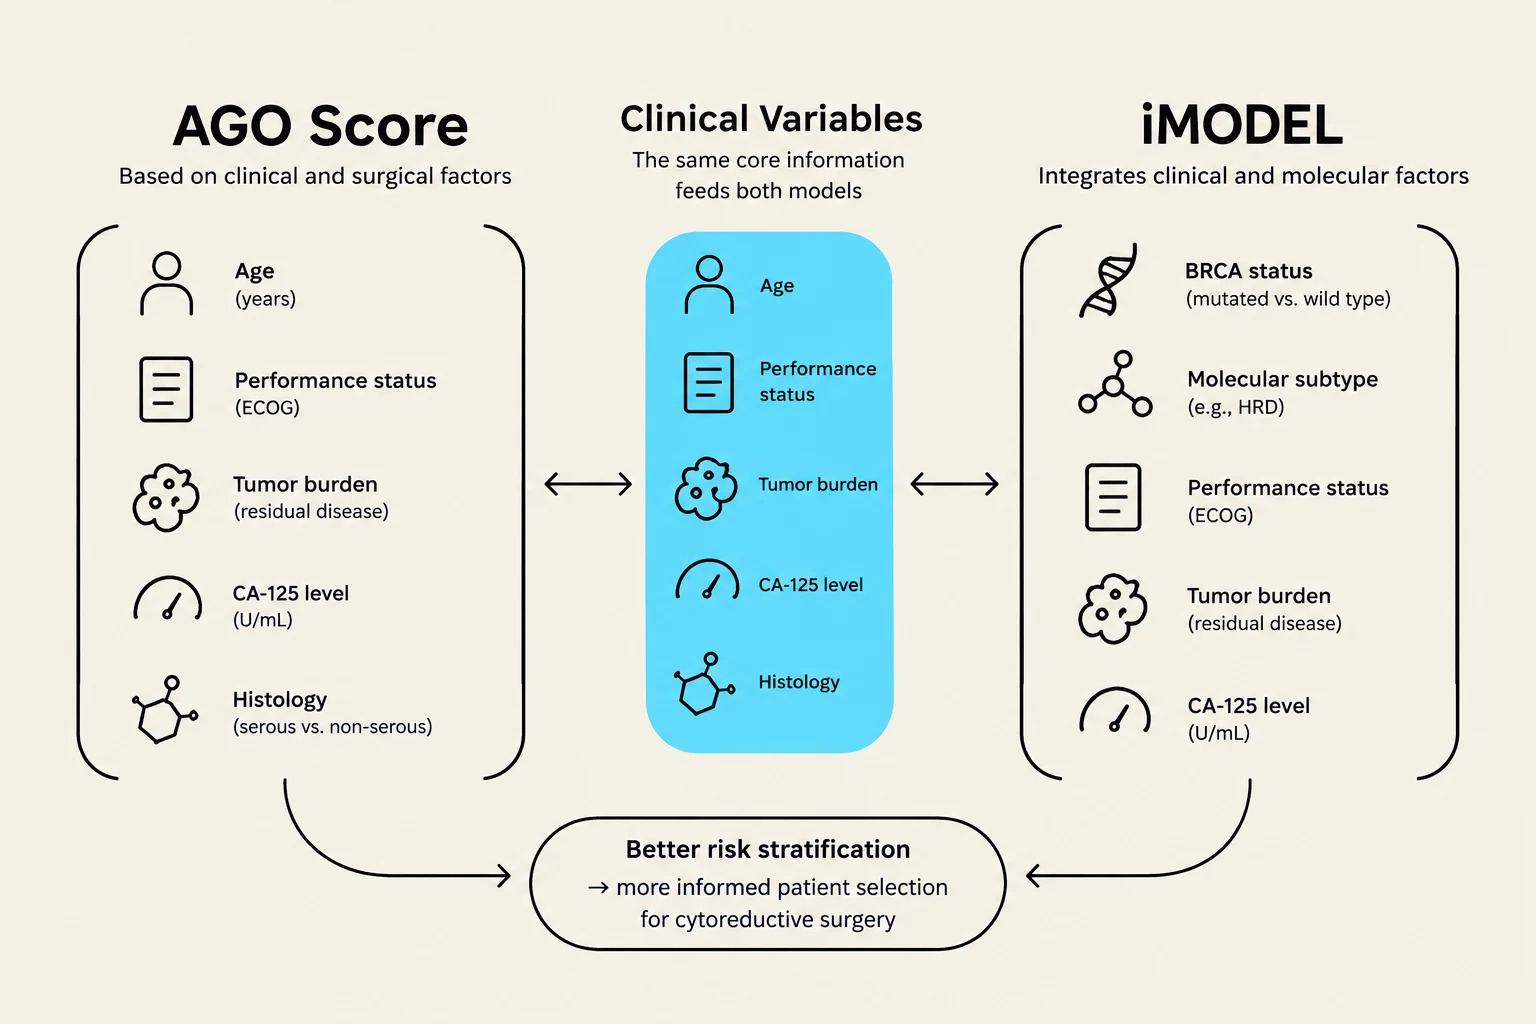
This diagram illustrates two models, AGO Score and iMODEL, which use clinical and molecular factors to stratify risk and inform patient selection for cytoreductive surgery.
Clinical Decision Making
The decision to offer secondary cytoreduction should be individualized but guided by the patient's disease biology. Generally, ideal candidates are those with platinum-sensitive disease—defined as a recurrence occurring more than six months after the completion of adjuvant platinum-based chemotherapy.
Patients with an early recurrence (platinum-resistant disease) often show a decreased response to additional chemotherapy and are generally not considered ideal candidates for secondary cytoreduction.
Summary Table: Selection Logic
Feature
Favorable for Surgery
Unfavorable for Surgery
PFI
>6 months (Platinum-sensitive)
<6 months (Platinum-resistant)
Ascites
Absent or <500 mL
Present / Large volume
Performance Status
ECOG 0–1
ECOG 2–3
Primary Surgery
Complete resection (R0)
Residual disease remaining
Conclusion
While not all clinical trials have yielded positive results, the weight of evidence from validated, prospective studies like DESKTOP III suggests that cytoreductive surgery provides a significant survival benefit when applied to the right patients. The key to success lies in careful patient selection using tools like the AGO Score or iMODEL and ensuring that surgery is performed in competent centers where it can be integrated with subsequent platinum-based chemotherapy.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.