This document outlines the clinical management of cervical cancer, covering staging, histologic subtypes, early-stage and advanced disease treatment, pathology principles, biomarkers, and survivorship care.
The clinical management of cervical cancer is a highly stratified process determined by the tumor's histologic type, clinical stage, and the patient's individual goals, such as the desire for fertility preservation. While squamous cell carcinoma is a common presentation, management must also account for adenocarcinoma and rarer, more aggressive subtypes like small cell neuroendocrine carcinoma. Modern guidelines emphasize a transition from purely surgical approaches in early stages to intensive, multi-modal chemoradiation for locally advanced disease, increasingly incorporating molecular profiling to guide systemic therapy.
Clinical Staging and Histologic Subtypes
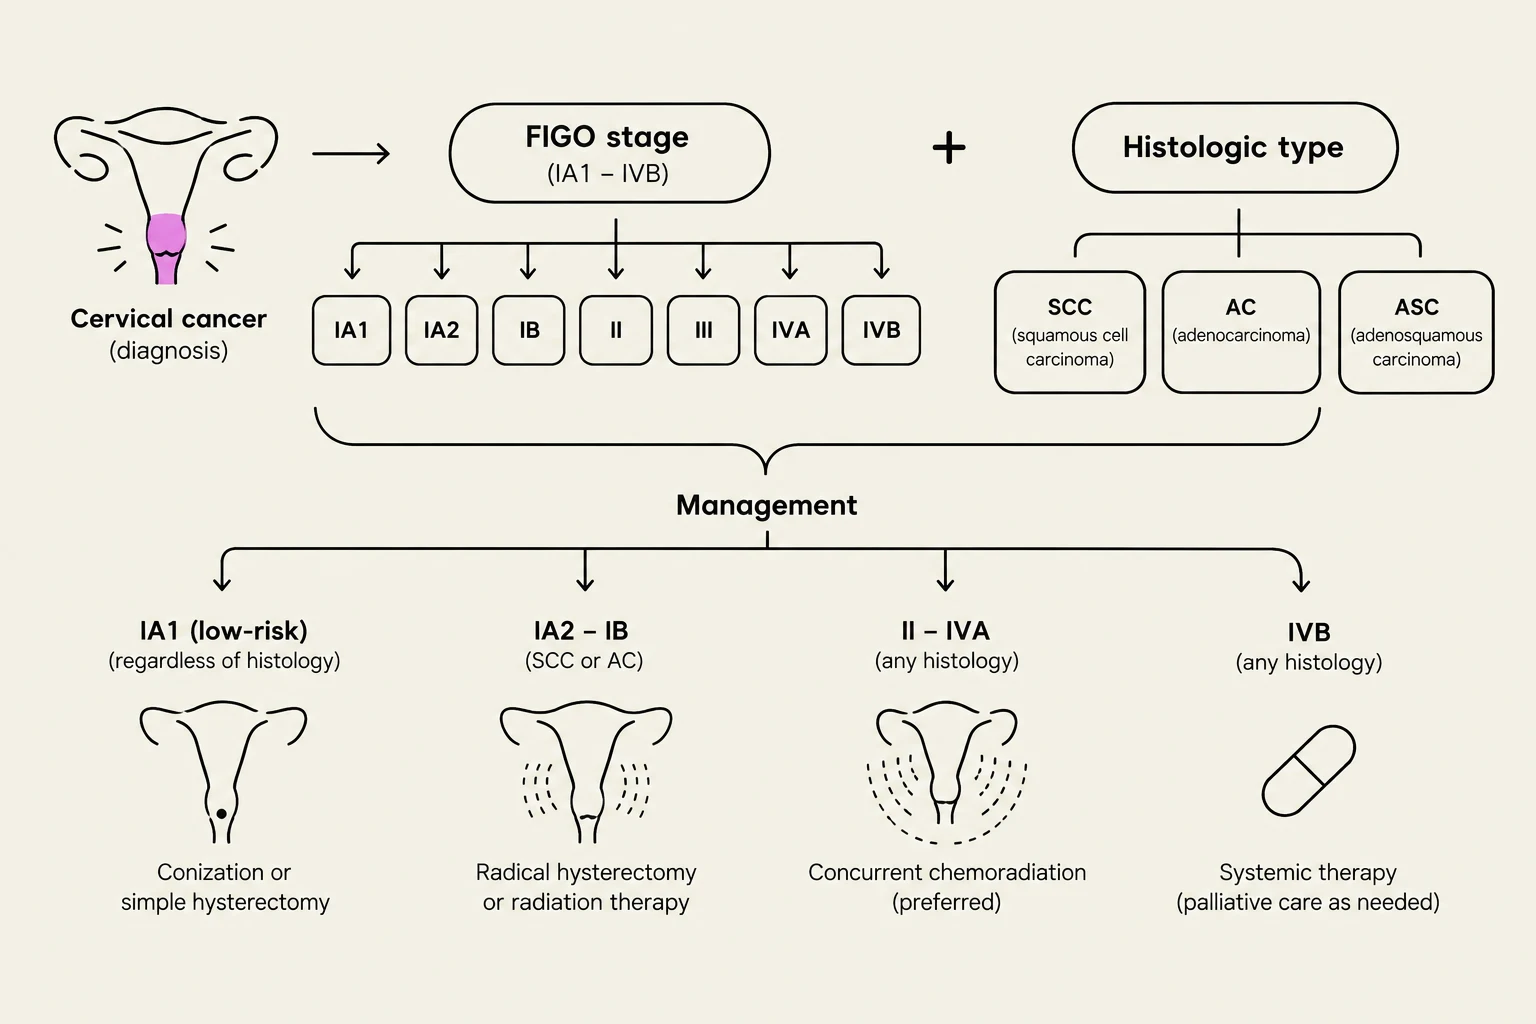
Staging is the cornerstone of cervical cancer management and follows the updated 2018 FIGO staging system. The management pathway diverges significantly based on whether the tumor is a squamous cell carcinoma, endocervical adenocarcinoma, or adenosquamous carcinoma.
Histologic subtypes play a critical role in prognosis and treatment selection. For instance, small cell neuroendocrine carcinoma (NECC) of the cervix is a distinct, highly aggressive entity that requires a specific workup and often follows different systemic therapy principles compared to standard squamous or adenocarcinoma cases. Furthermore, clinicians must distinguish between HPV-associated and HPV-independent tumors, as HPV status is a fundamental component of the pathologic assessment.
This diagram illustrates the FIGO staging and histologic types of cervical cancer, along with their corresponding management strategies.
Early-Stage Management and Fertility Preservation
For patients with early-stage disease (Stage IA to IB1) who wish to maintain reproductive potential, fertility-sparing surgery is a primary consideration.
Stage IA1 and IA2
Management of Stage IA1 is heavily dictated by the presence or absence of lymphovascular space invasion (LVSI).
If LVSI is absent and margins are negative, the patient may undergo observation or a Type A hysterectomy.
If LVSI is present, a Type A hysterectomy combined with sentinel lymph node (SLN) mapping or pelvic lymphadenectomy is recommended to assess nodal involvement.
For Stage IA2–IB1, if specific conservative criteria are met—such as a tumor size ≤2 cm, a depth of invasion <10 mm, and no LVSI—conservative options like cold knife conization (CKC) or LEEP may be utilized.
Stage IB and Surgical Staging
As the disease progresses to Stage IB1 or Stage IB2, the complexity of surgery increases. For Stage IB1 patients who do not meet conservative criteria, or for select Stage IB2 patients, a radical trachelectomy combined with SLN mapping is often the preferred fertility-sparing approach.
Exam Tip: When considering fertility-sparing surgery, always check for "ineligible" histologic types. Neuroendocrine histology and gastric-type adenocarcinoma are contraindications for these conservative procedures due to their aggressive nature.
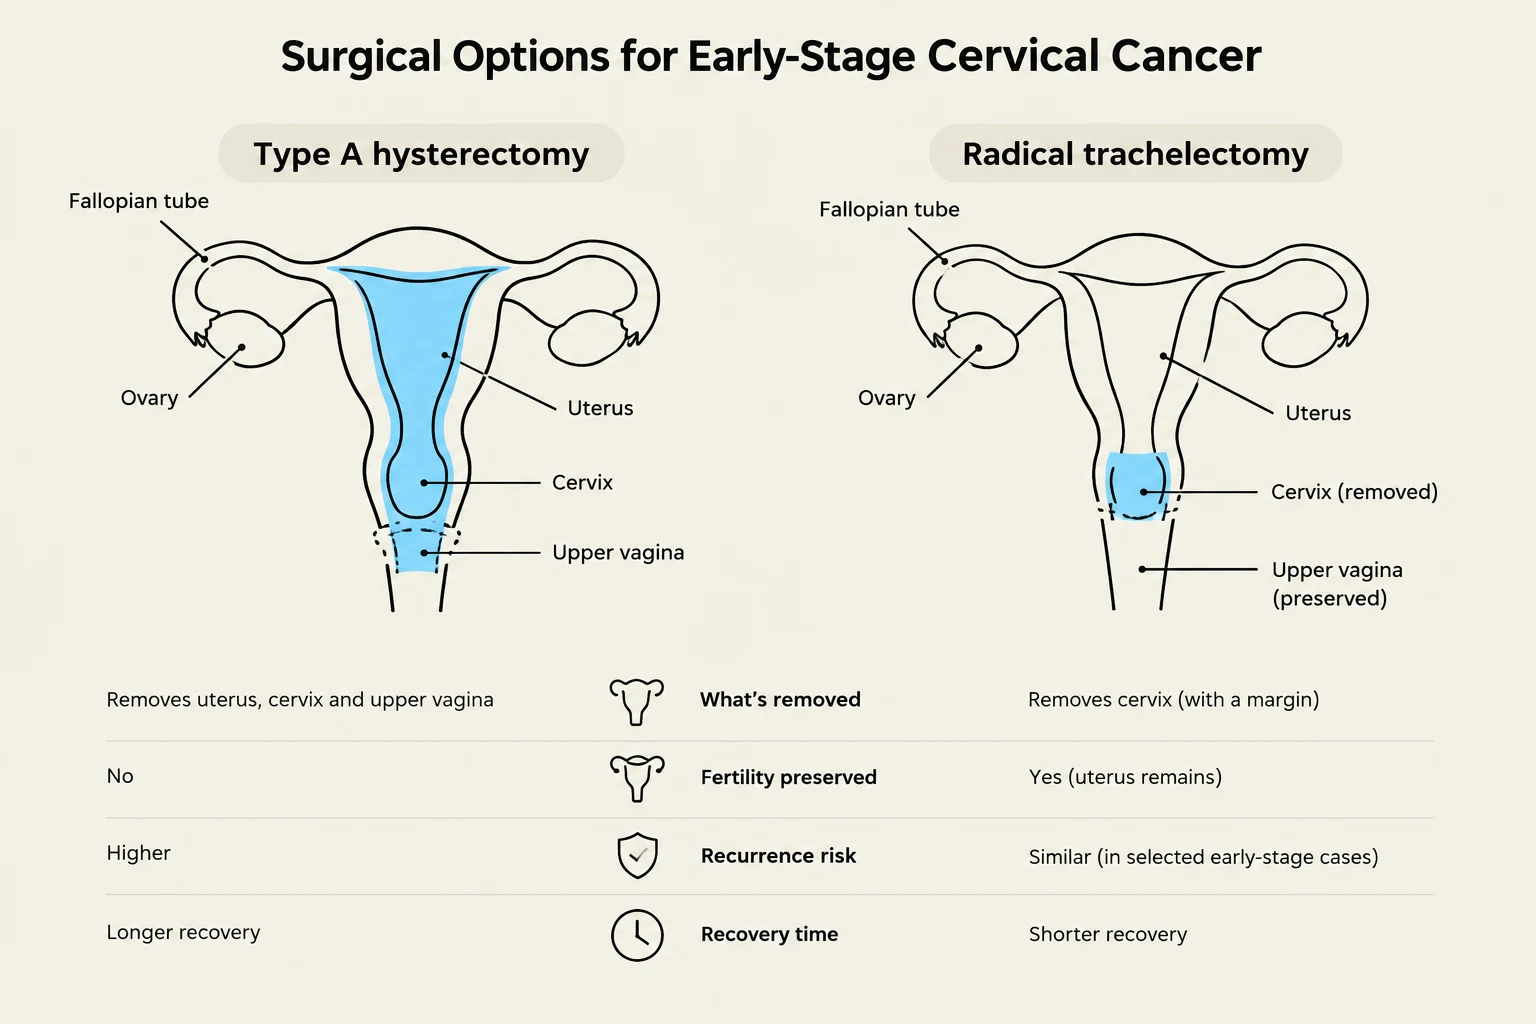
Comparison of Type A hysterectomy and Radical trachelectomy for early-stage cervical cancer, detailing what is removed, fertility preservation, recurrence risk, and recovery time.
Locally Advanced and Advanced Disease
When the disease reaches Stage IB3 or Stage IIA–IVA, the focus shifts from surgical resection to multi-modal intensive therapy.
Primary Treatment for Locally Advanced Disease
The standard of care for locally advanced stages involves a combination of:
Pelvic External Beam Radiation Therapy (EBRT).
Brachytherapy (internal radiation).
Concurrent platinum-containing chemotherapy, typically utilizing cisplatin or carboplatin.
Recent updates to the guidelines include the INTERLACE protocol, which involves induction chemotherapy followed by chemoradiation, offering an alternative for select patients. For certain FIGO stages within the IIB–IVA range, the immunotherapy agent pembrolizumab may be added to the concurrent chemoradiation regimen.
Metastatic Disease (Stage IVB)
For Stage IVB or cases involving locoregional recurrence with distant metastases, the priority is systemic therapy. If the primary tumor is controlled and the disease is amenable, local ablative therapies or resection may be considered.
Principles of Pathology and Biomarkers
Accurate pathologic assessment is vital for determining both the stage and the eligibility for targeted therapies.
Pathologic Assessment
Pathologists must evaluate:
HPV status: This is essential for all cervical adenocarcinomas, ideally via HPV in situ hybridization (ISH) or molecular testing, though p16 IHC may be used if necessary.
Silva pattern of invasion: This specific pattern is applicable to HPV-associated endocervical adenocarcinoma.
Nodal assessment: The number and location of lymph nodes, including the identification of isolated tumor cells, must be documented.
Molecular Profiling and Targeted Therapy
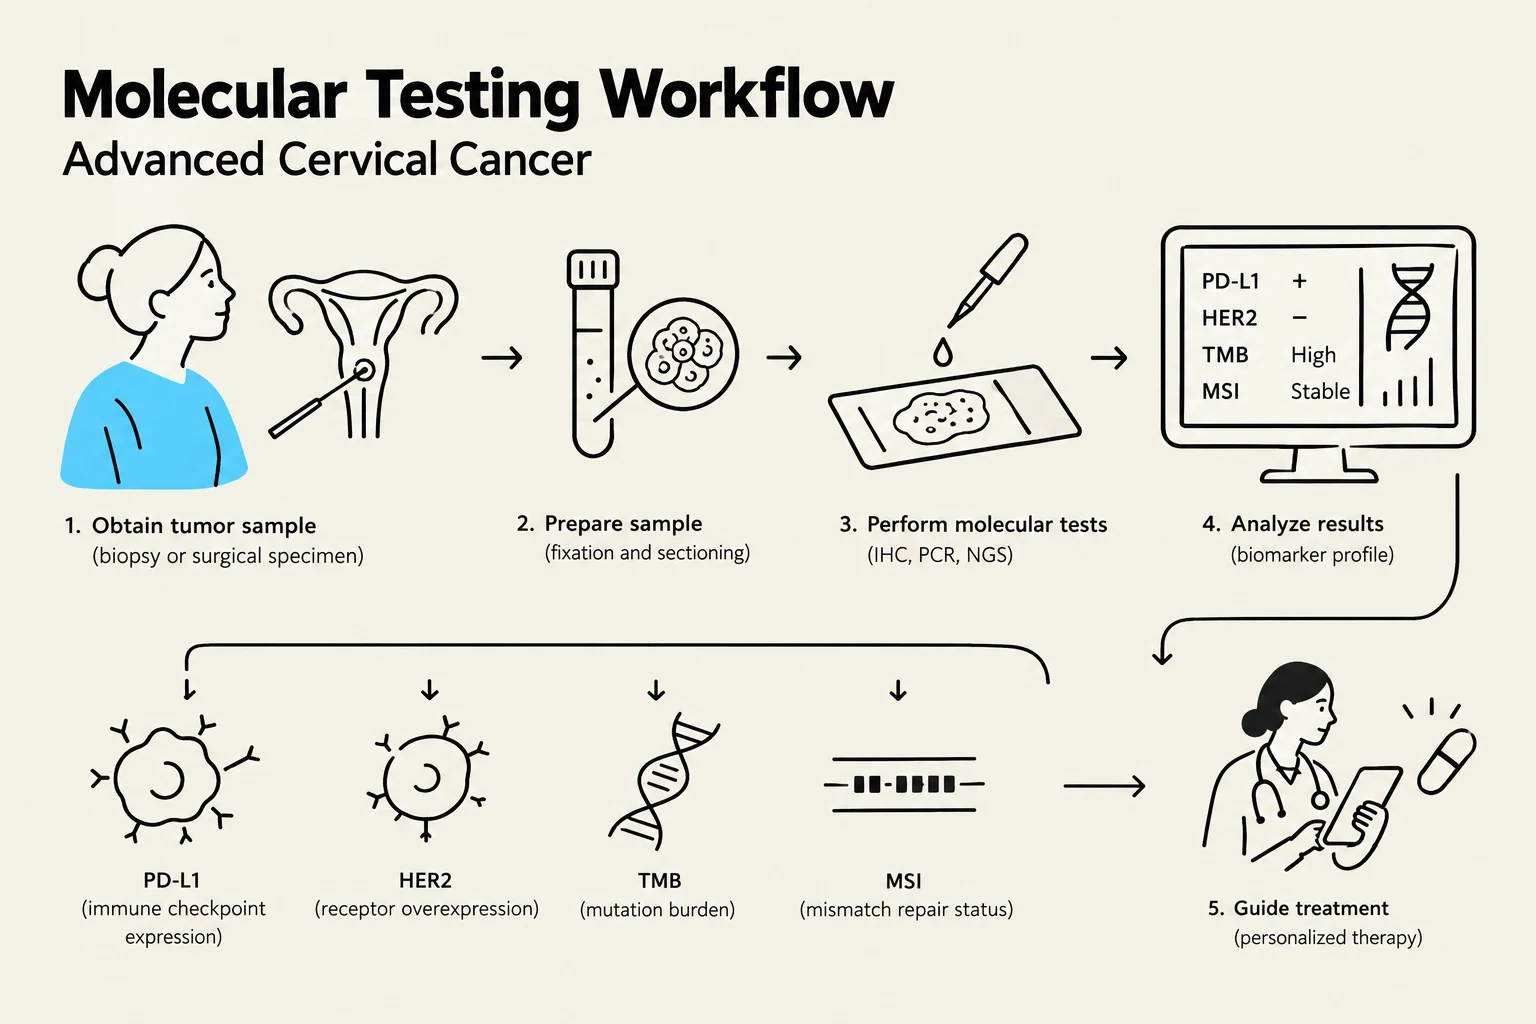
In the setting of advanced, recurrent, or metastatic disease, Multigene Panel Testing (MGPT) is recommended to identify actionable biomarkers. Key biomarkers include:
PD-L1: To guide immunotherapy.
HER2(ERBB2): Overexpression is associated with higher recurrence rates and may provide options for anti-HER2 targeted therapy.
MMR/MSI and TMB: To identify candidates for immunotherapy (e.g., dostarlimab for MSI-H/dMMR tumors).
NTRK1/2/3 and RET: To identify rare opportunities for pan-tumor targeted therapies.
This diagram illustrates the workflow for molecular testing in advanced cervical cancer, from obtaining a tumor sample to guiding personalized treatment based on biomarker analysis.
Survivorship and Long-term Care
Because treatments for cervical cancer—particularly radiation and radical surgery—can lead to significant side effects, survivorship care is a critical component of management. Patients should be monitored for:
Genitourinary symptoms: Including vulvovaginal dryness.
Vaginal stenosis: Post-radiation care often requires the use of vaginal dilators, moisturizers, and in select cases, local vaginal estrogen to improve tissue quality.
Psychosocial implications: Early menopause and sexual dysfunction require multidisciplinary support, including referrals to pelvic floor therapy or psychotherapy.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.