An overview of the cervical spine's anatomy, including the upper and lower cervical complexes, neurovascular structures, and somatic dysfunction. It also covers diagnostic testing and osteopathic manipulative treatment techniques like counterstrain.
The cervical spine is a complex anatomical region responsible for supporting the head, facilitating a wide range of motion, and protecting vital neurovascular structures. Clinical presentations involving the neck are highly prevalent, with an incidence of 10-20% per year in primary care settings. Understanding the distinction between mechanical, chemical, electrical, and vascular causes of pain is essential for accurate diagnosis and effective treatment.
Cervical Anatomy: Structural Organization
The cervical spine is organized into two distinct functional groups: the upper cervical complex and the lower cervical complex.
The Upper Cervical Complex
The upper cervical complex consists of the occiput (C0), the atlas (C1), and the axis (C2). These vertebrae exhibit atypical mechanics that differ significantly from the rest of the spine.
Occipitoatlantal (OA) Joint: This joint is formed by the articulation of the occipital condyles with the superior articular surfaces of the atlas. It is primarily responsible for flexion and extension of the head.
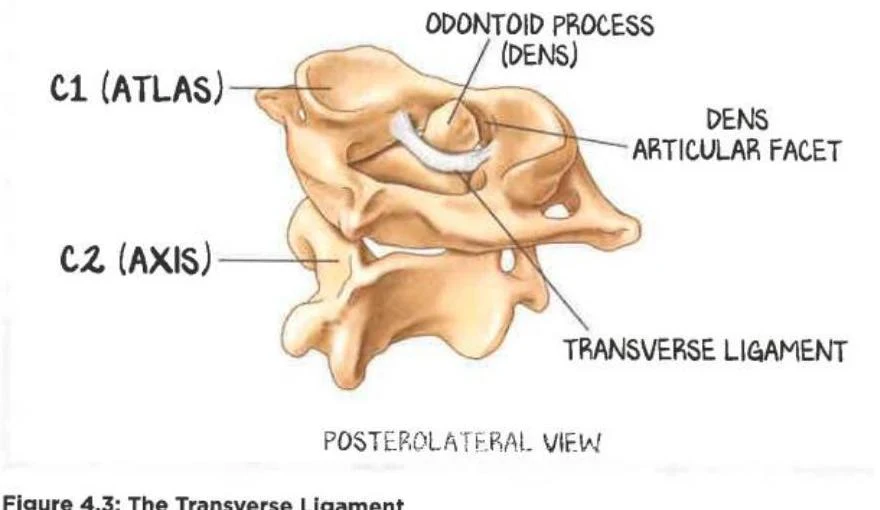
Atlantoaxial (AA) Joint: This joint is located between the atlas (C1) and the axis (C2). The defining feature of the axis is the dens axis (odontoid process), a bony projection that serves as a pivot point for rotation.
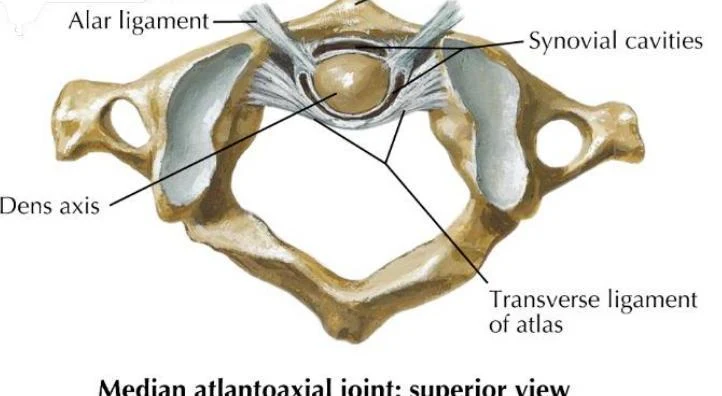
Stability and Ligaments: The stability of the AA joint is critically dependent on the transverse ligament, which secures the dens against the anterior arch of the atlas.
An illustration showing the posterior-lateral view of the C1 (Atlas) and C2 (Axis) vertebrae, highlighting the odontoid process (dens), articular facet, and transverse ligament.
Median atlantoaxial joint: superior view
The Lower Cervical Complex
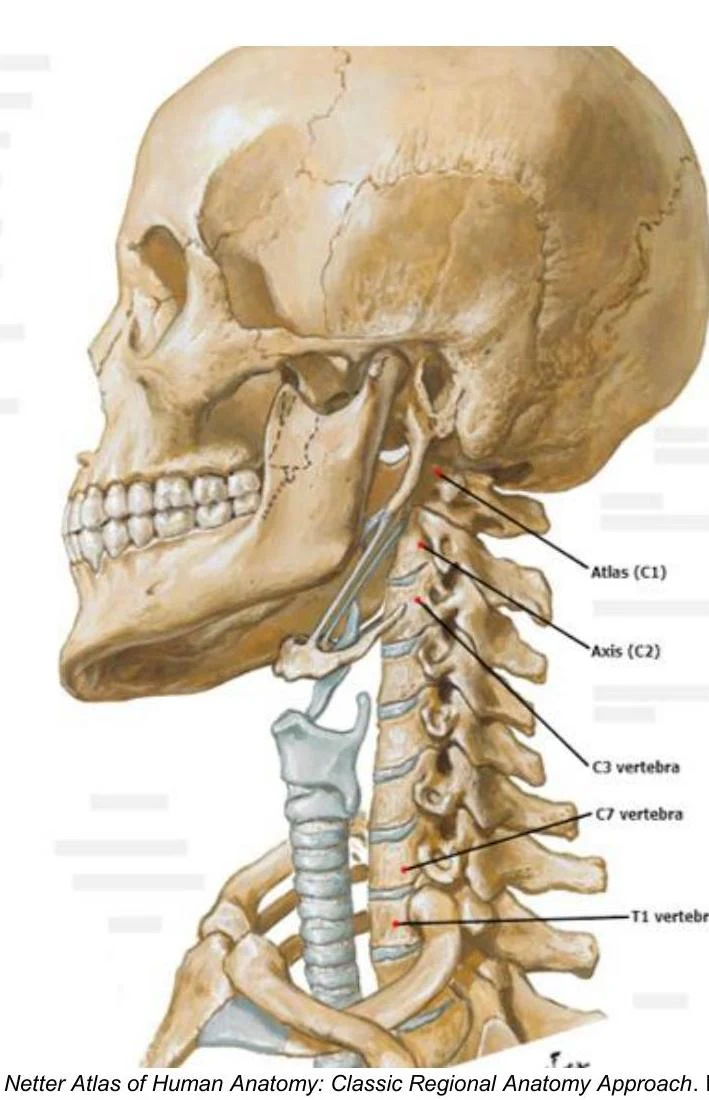
The lower cervical complex comprises the vertebrae from C3 through C7. Unlike the upper cervical vertebrae, these segments follow Type II-like mechanics, where rotation and sidebending occur in the same direction.
An illustration of the human cervical vertebrae, including the Atlas (C1), Axis (C2), C3 vertebra, C7 vertebra, and T1 vertebra.
Neurovascular Considerations
The cervical spine is a high-traffic corridor for essential structures. Clinicians must be aware of the following:
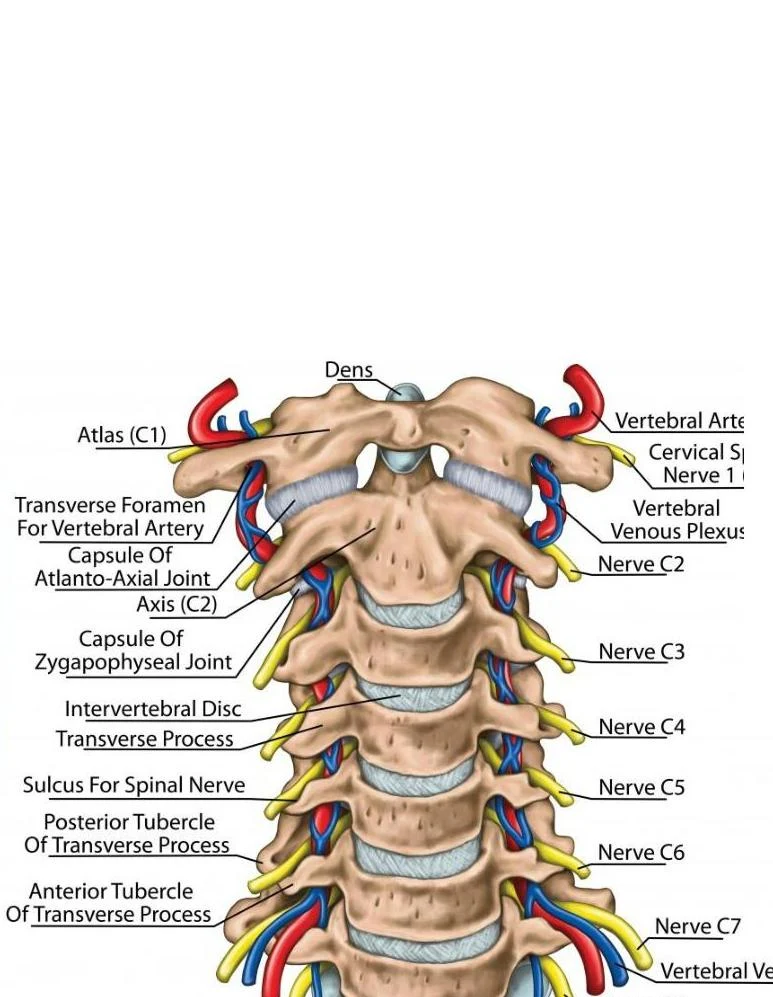
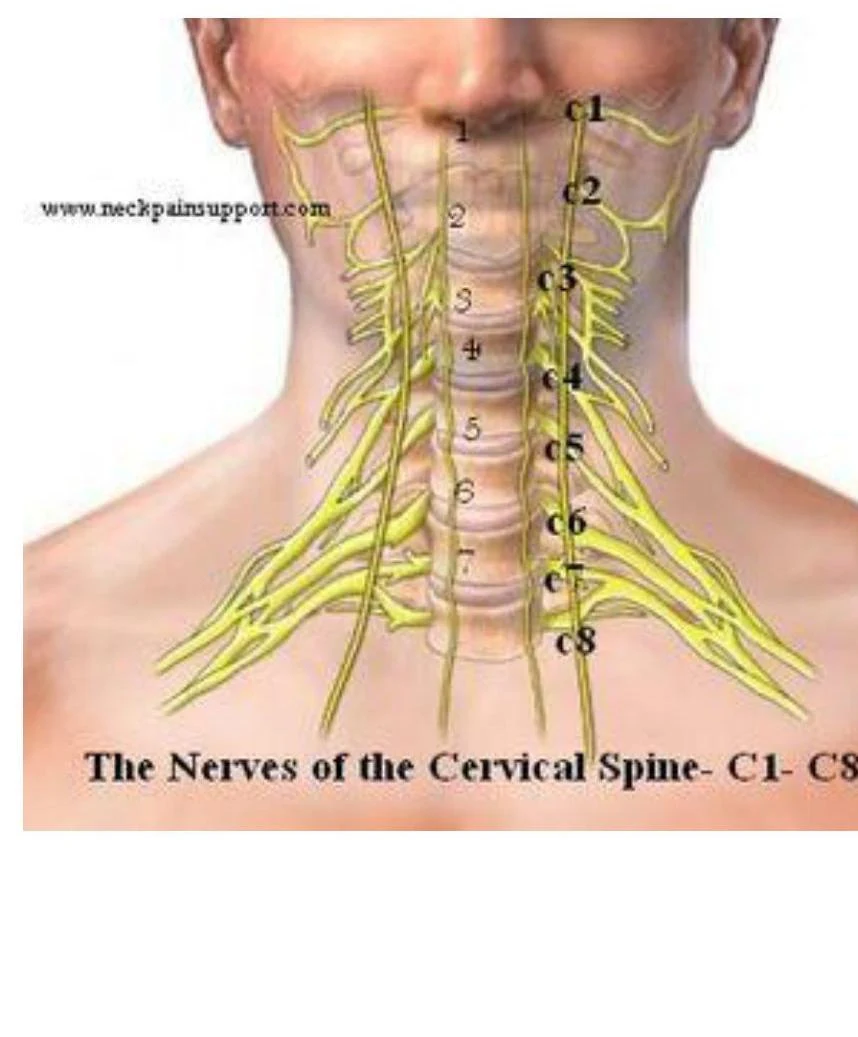
Nerves: There are 8 cervical nerve roots serving the cervical region. Damage or compression can lead to radicular pain or cervical myelopathy (spinal cord compression).
Arteries: The vertebral arteries travel through the transverse foramen of the cervical vertebrae. Integrity of these vessels is vital for maintaining posterior circulation.
Musculature: Various muscle groups, including the sternocleidomastoid, trapezius, and scalenes, contribute to both stability and potential somatic dysfunction.
An illustration of the cervical vertebrae, highlighting the atlas (C1) and axis (C2), along with associated arteries, veins, and nerves.
An illustration showing the nerves of the cervical spine, labeled C1 through C8.
Somatic Dysfunction and Motion Mechanics
Somatic dysfunction refers to an impaired or altered function of the related components of the somatic system. Diagnosis requires an understanding of segmental range of motion (ROM).
Atypical Mechanics (Upper Cervical)
The OA and AA joints do not follow standard spinal rules:
OA Joint (Non-neutral Type I-like): In flexion and extension (Type II), rotation and sidebending occur in opposite directions. When naming the dysfunction, sidebending is named prior to rotation (e.g., OA ESRRL).
AA Joint (Type II with rotation only): The AA joint is primarily involved in rotation. It does not exhibit significant flexion/extension or sidebending in a clinical diagnostic context.
Typical Mechanics (Lower Cervical)
For C2-C7, rotation and sidebending occur in the same direction (Type II mechanics). When naming, rotation is named prior to sidebending (e.g., C2 FR SR).
Diagnostic Testing
Active Motion Testing: The patient moves through their own ROM. Clinicians should observe from the perpendicular plane (lateral for flexion/extension; anterior/posterior for rotation/sidebending).
Passive Motion Testing: The clinician moves the patient's segment. This may achieve greater ROM but carries a higher risk of injury.
Clinical Caution: Use extreme caution with passive testing if the patient has a history of trauma (e.g., MVA), recent falls, sports injuries, local tumors, or cervical radiculopathy.
Translation Testing: Used for diagnosing OA and C2-C7. A right translation (force from left to right) produces left sidebending.
A model of the cervical spine, with an arrow pointing to a vertebra.
Counterstrain is a passive positional procedure designed to relieve pain by reducing inappropriate proprioceptor activity.
The Counterstrain Procedure
Locate the tender point via palpation.
Compress the tender point and assess pain (e.g., 10/10).
Without lifting the finger, passively move the patient into a position of comfort.
Reassess pain. If pain is ≤3/10, hold the position for 90 seconds.
Return the patient to neutral and reassess.
Common Tenderpoint Locations
Tenderpoints are categorized as anterior or posterior.
Anterior Cervical Points (Examples):
AC1 (Mandible): Located on the posterior aspect of the ascending ramus of the mandible at the earlobe level. Treatment: Marked rotation away.
AC2–AC6: Located on the posterosuperior surface of the clavicle at the SCM attachment. Treatment: Flex to C7, sidebend toward, rotate away (F St Ra).
Posterior Cervical Points (Examples):
PC1 (Inion): Located on the inferior nuchal line, lateral to the inion. Treatment: Flexion of the OA joint, sidebend toward, rotate away (F St Ra).
PC4–PC8 (Midline): Located on the inferior or inferolateral aspect of the spinous process. Treatment: Extension to the level of the segment, sidebend toward, rotate away (e-E Sa Ra).
Exam Tip: When diagnosing OA dysfunction using translation, remember that translation and sidebending are inversely related. A preference for left translation implies a preference for right sidebending.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.