


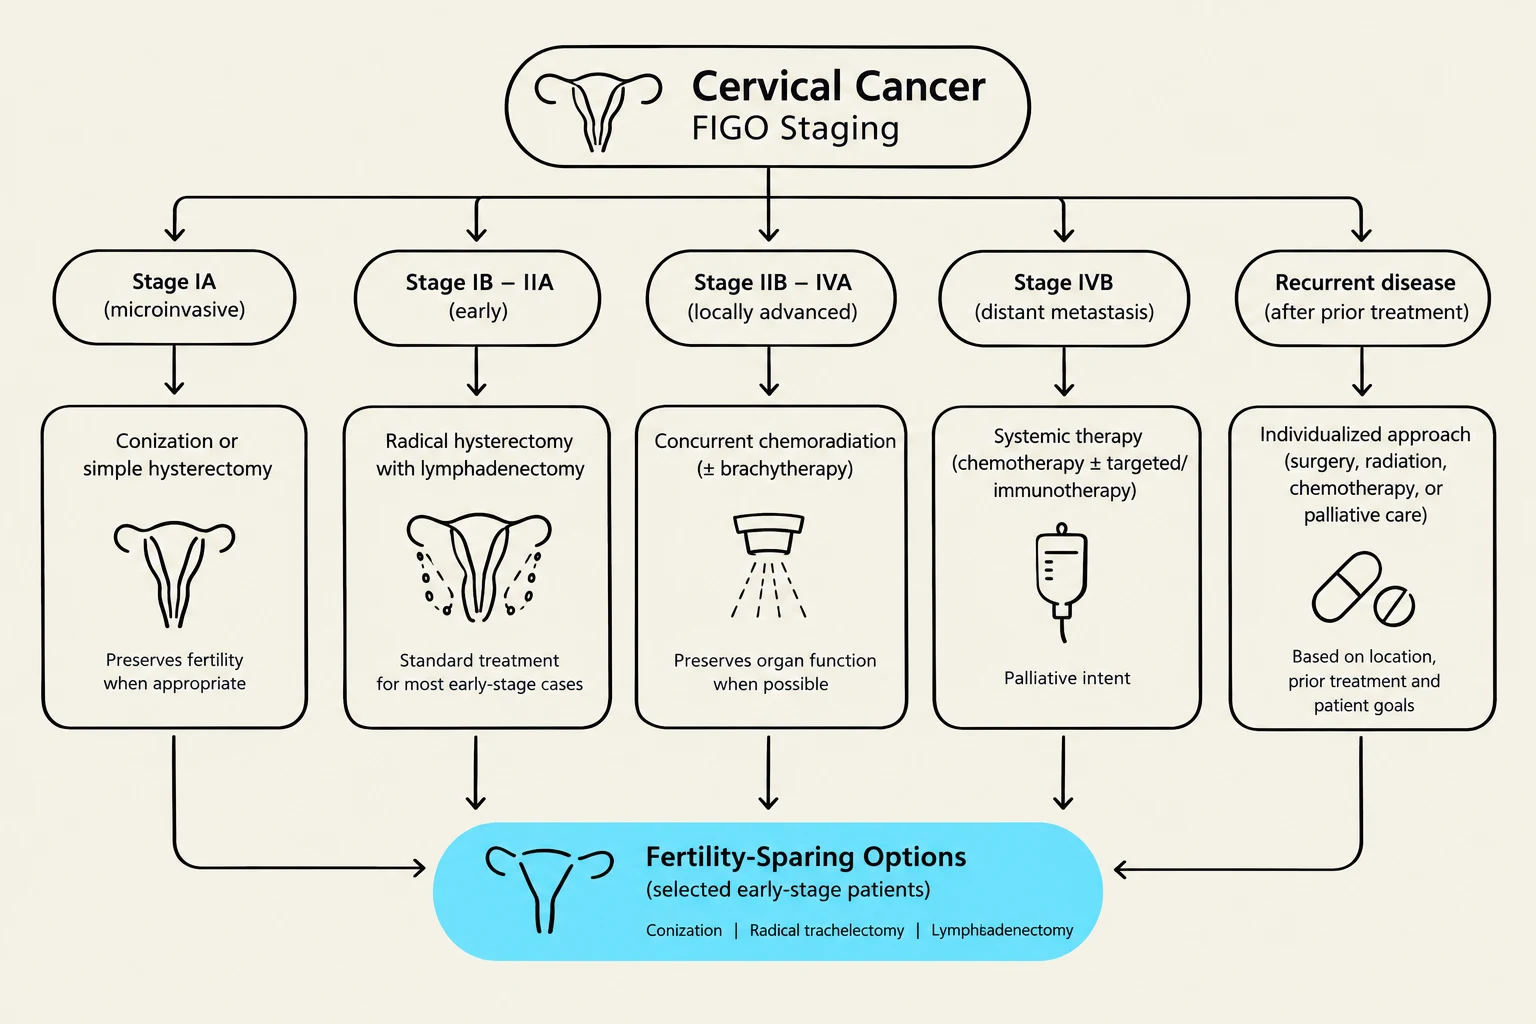
When managing cervical cancer, the surgical approach is a delicate balance between oncologic safety—ensuring the complete resection of malignant tissue—and the patient's desire for future fertility. The decision-making process is primarily driven by the clinical stage of the disease and the specific histological characteristics of the tumor. For patients in the early stages, specifically IA1 through IB1, various fertility-sparing procedures can be considered if they meet strict conservative surgery criteria.
Surgical Staging and Clinical Decision Making
Surgical staging is the cornerstone of cervical cancer management. It determines whether a patient is a candidate for conservative, fertility-sparing surgery or if they require more definitive, non-fertility-sparing interventions like a radical hysterectomy or chemoradiation.
The clinical stage dictates the treatment pathway:
- Stages IA1–IB1: These are the primary candidates for fertility-sparing procedures, provided specific criteria (such as the absence of lymphovascular space invasion in certain stages) are met.
- Stages IB2 and beyond: As the disease progresses to IB2, IB3, or Stage IIA, the risk of spread increases significantly. For these stages, more aggressive treatments, such as pelvic external beam radiation therapy (EBRT) combined with brachytherapy and chemotherapy, are often required.
Exam Tip: Always check for Lymphovascular Space Invasion (LVSI). The presence of LVSI can shift a patient from a conservative surgery pathway to a more intensive treatment regimen, even if the tumor size is small.

Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated