Cervical Cancer: Staging, Treatment, and Management
An overview of cervical cancer management, covering staging systems like FIGO 2018, risk assessment including lymphovascular space invasion (LVSI), and treatment modalities for early-stage, locally advanced, and metastatic disease. Discusses fertility-sparing options, adjuvant therapies, chemoradiation, and survivorshi
Cervical cancer management is a highly stratified process that requires a precise understanding of tumor extent, histology, and patient-specific goals. The primary objective of treatment is to achieve long-term survival while minimizing long-term morbidity, such as sexual dysfunction or infertility. Modern management relies heavily on the FIGO 2018 staging system to guide therapeutic decisions, moving from conservative surgical approaches in early stages to intensive multimodal therapy in advanced disease.
Staging and Risk Assessment
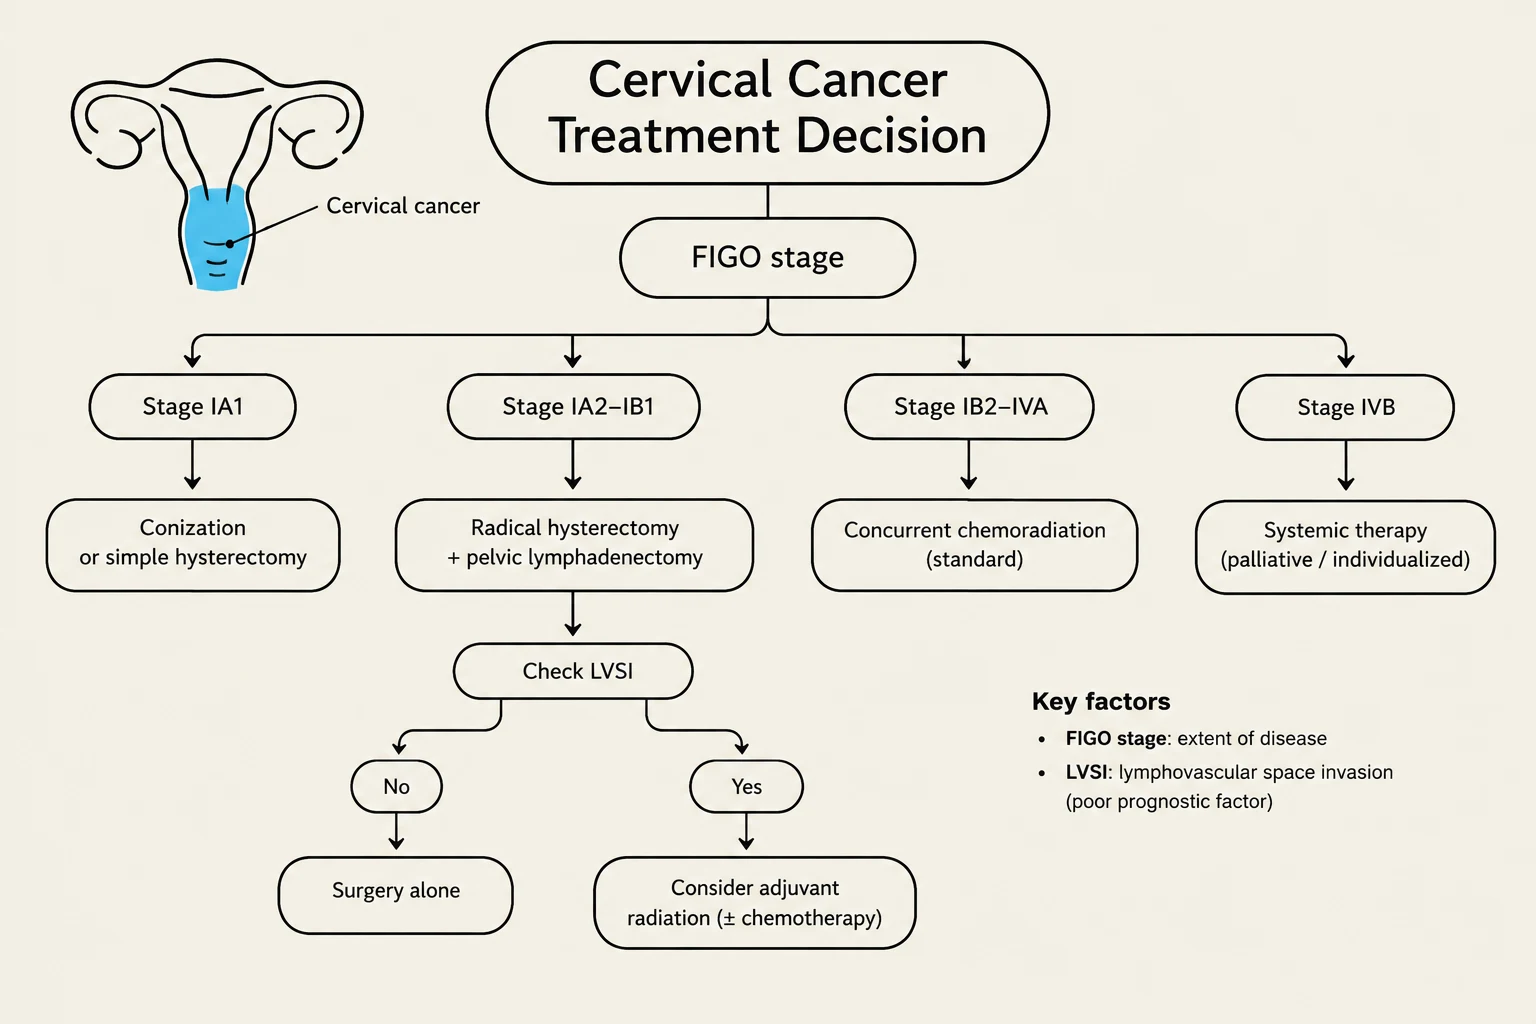
The foundation of any treatment plan is the clinical stage assigned via the FIGO (International Federation of Gynecology and Obstetrics) system. Staging determines whether a patient is a candidate for surgery, radiation, or systemic therapy.
Beyond the clinical stage, pathologists look for specific risk factors that may necessitate more aggressive intervention. One critical factor is lymphovascular space invasion (LVSI), which refers to the presence of tumor cells within the lymphatic or blood vessels. The presence of LVSI significantly increases the risk of regional or distant spread.
Flowchart illustrating the decision-making process for cervical cancer treatment based on FIGO stage and lymphovascular space invasion (LVSI).
Exam Tip: When evaluating early-stage cervical cancer, always check for LVSI. Even in Stage IA1, the presence of LVSI can shift the management strategy toward more intensive monitoring or surgical staging.
Early-Stage Disease (Stage IA–IIA1)
For patients with early-stage disease, the treatment pathway diverges based on whether the patient wishes to preserve fertility.
Fertility-Sparing Options
For patients with Stage IA, IB1, or select IB2 disease who desire future pregnancy, conservative surgical options are available:
Cone Biopsy: A localized excision of the cervix used for very early disease. To be considered successful, the specimen must have at least a 1-mm negative margin.
Radical Trachelectomy: A more extensive procedure that removes the cervix and surrounding tissue while preserving the uterine body and fallopian tubes.
It is important to note that these options are generally contraindicated in patients with high-risk histologies, such as small cell neuroendocrine carcinoma.
Non-Fertility-Sparing Options
For patients who have completed childbearing, the standard is surgical resection. This may include a Type A or Type B hysterectomy (ranging from simple to radical) combined with pelvic lymphadenectomy to assess for nodal involvement. To improve the accuracy of nodal assessment, surgeons often utilize sentinel lymph node (SLN) mapping, which identifies the first nodes to receive lymphatic drainage from the tumor.
Adjuvant Therapy and the Sedlis Criteria
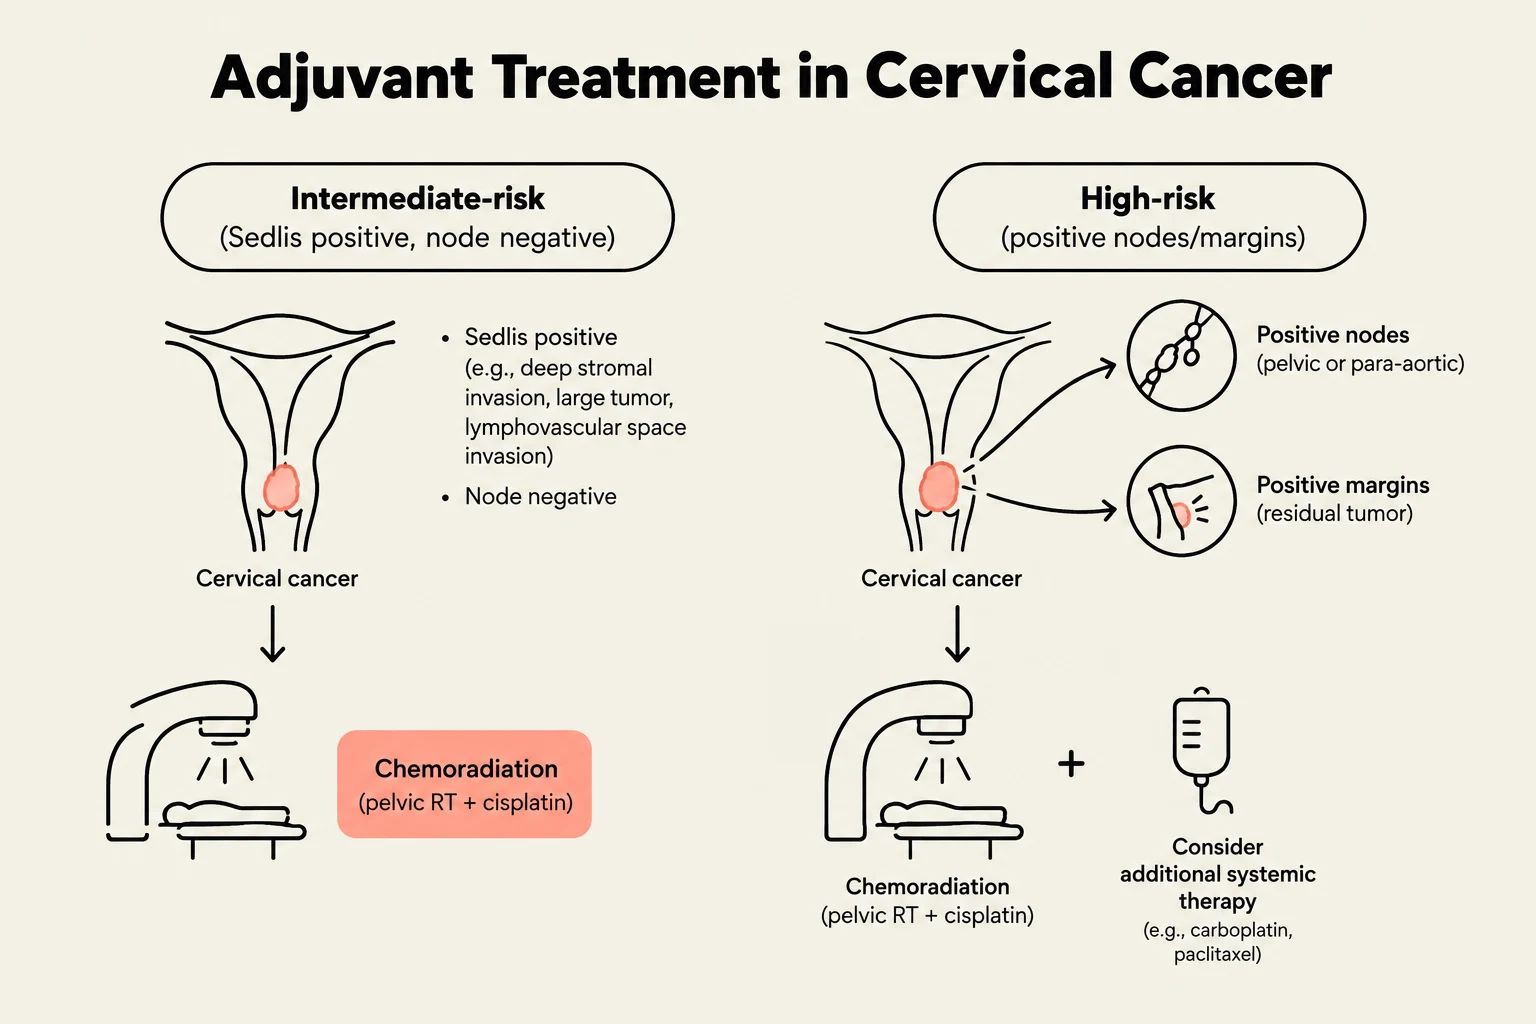
Not all surgical patients require treatment after the operation. Clinicians use the Sedlis Criteria to determine if adjuvant radiation therapy (RT) is necessary for node-negative, margin-negative patients.
The Sedlis Criteria include:
Stromal invasion >1/3 of the cervical stroma.
Presence of lymphovascular space invasion (LVSI).
Tumor diameter >4 cm.
If a patient meets these intermediate-risk criteria but has negative lymph nodes, adjuvant pelvic radiation therapy is recommended. However, if the patient is classified as "high-risk" (e.g., positive nodes, positive margins, or parametria involvement), adjuvant chemoradiation—combining external beam radiation therapy (EBRT) with concurrent platinum-containing chemotherapy—is indicated to improve survival.
This diagram illustrates adjuvant treatment strategies for cervical cancer, differentiating between intermediate-risk and high-risk cases based on tumor characteristics and treatment approaches.
Locally Advanced and Advanced Disease (Stage IB3–IVA)
As the disease progresses into Stage IB3 through Stage IVA, surgery is no longer the primary modality. Instead, the standard of care shifts to concurrent chemoradiation.
This multimodal approach typically consists of:
External Beam Radiation Therapy (EBRT).
Brachytherapy (internal radiation).
Platinum-containing chemotherapy (usually cisplatin, or carboplatin if cisplatin is not tolerated) acting as a radiosensitizer to make the radiation more effective.
For patients with FIGO 2014 Stage III–IVA, recent guidelines also recommend the addition of pembrolizumab (an immunotherapy) to the chemoradiation regimen as a Category 1 option.
Metastatic Disease (Stage IVB)
When the cancer has spread to distant organs (Stage IVB), the goal of treatment shifts from cure to palliation and systemic control. Management focuses on systemic chemotherapy (often platinum-based regimens) and individualized EBRT to manage symptoms caused by metastatic lesions.
Special Considerations and Survivorship
Small Cell Neuroendocrine Carcinoma (NECC)
NECC is a rare but highly aggressive variant of cervical cancer. It requires aggressive multimodality treatment, often involving cisplatin/etoposide regimens combined with immunotherapy such as atezolizumab or durvalumab.
Post-Treatment Surveillance and Side Effects
Following successful treatment, patients enter a surveillance phase involving regular physical exams and cervical/vaginal cytology to detect any recurrence. High-risk patients require more frequent follow-ups, such as every 3 months.
Survivorship care is critical, as radiation therapy can lead to long-term complications like vaginal stenosis (narrowing) and dryness. To manage these side effects, clinicians recommend:
The use of vaginal dilators to prevent stenosis.
Vaginal moisturizers and water-based lubricants.
Local vaginal estrogen in select patients to improve tissue quality.
Clinical Pearl: Always ask all patients, regardless of sexual activity, about genitourinary symptoms like dryness. Early referral to pelvic floor therapy or sexual therapy can significantly improve quality of life.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.