This guide details the management of cervical cancer in pregnant individuals, emphasizing the multidisciplinary approach required to balance maternal oncologic treatment with fetal well-being. It covers diagnostic workup, clinical staging using the FIGO system, and management strategies tailored to the specific trimest
Managing cervical cancer during pregnancy presents a profound clinical dilemma: the necessity of treating maternal malignancy versus the imperative to preserve fetal viability. This requires a highly coordinated, multidisciplinary approach involving gynecologic oncologists and maternal-fetal medicine (MFM) specialists. Management strategies are not uniform; they are strictly dictated by the FIGO clinical stage of the cancer and the current gestational trimester of the pregnancy.
Workup and Clinical Staging
The initial diagnostic workup for a pregnant patient suspected of having cervical cancer begins with a thorough history and physical examination, including a cervical biopsy and pathologic review. Depending on the clinical presentation, clinicians may also consider HIV testing or examination under anesthesia (EUA) with cystoscopy or proctoscopy if there is suspicion of bladder or bowel involvement.
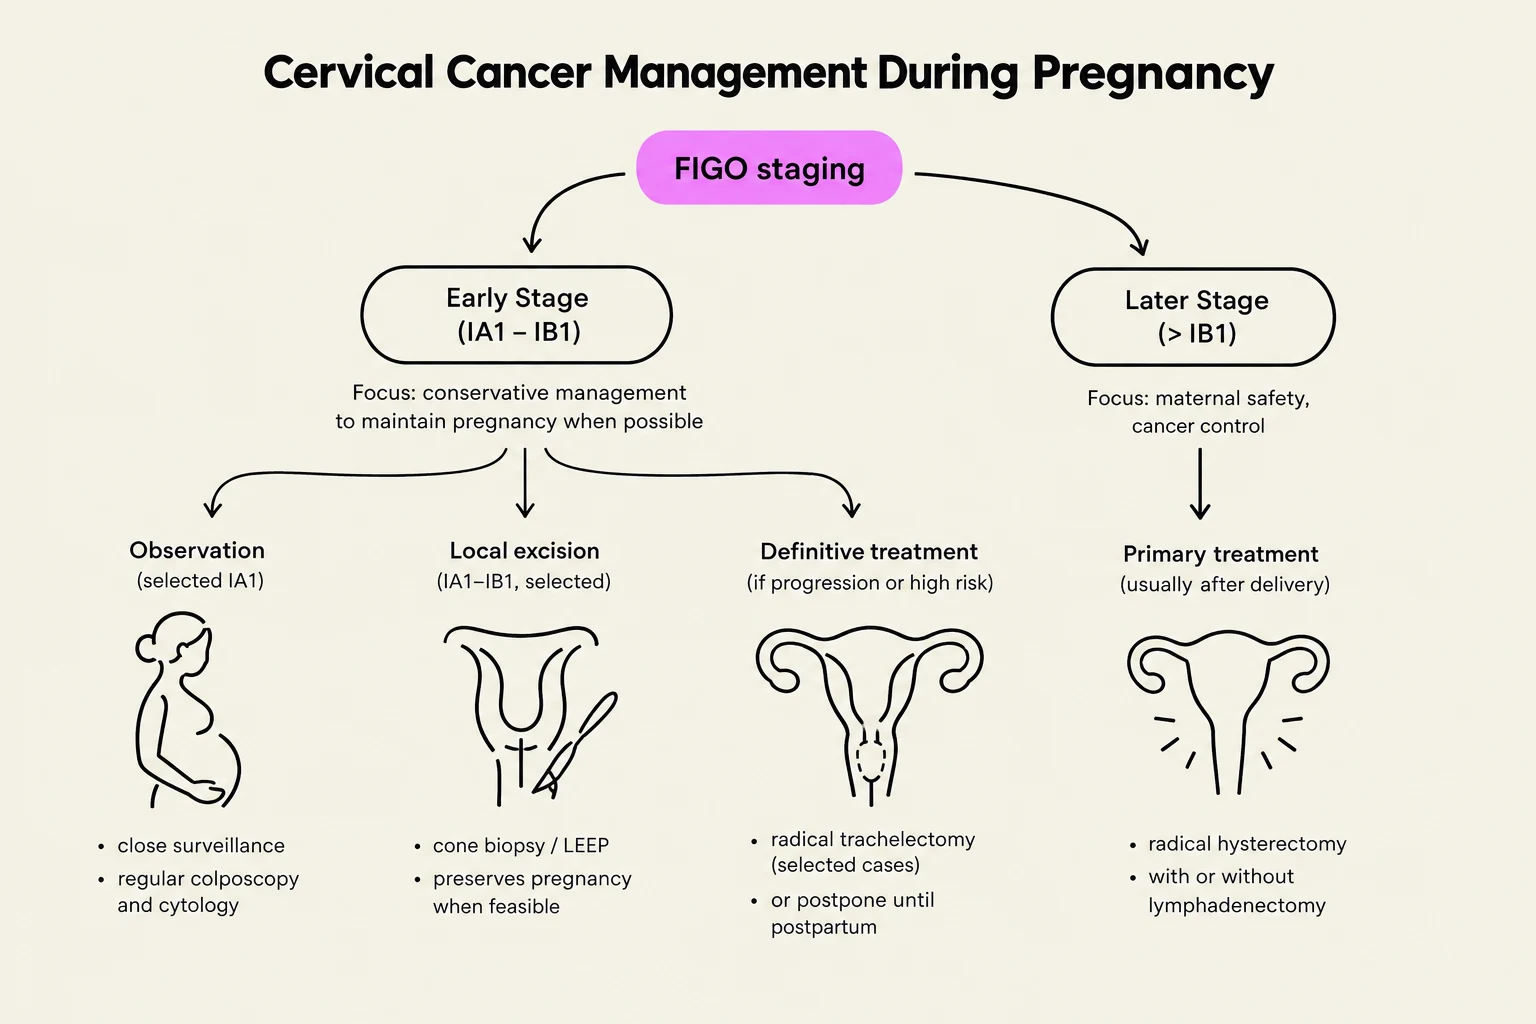
Staging is based on the updated 2018 FIGO staging system. The management pathway diverges significantly based on whether the cancer is classified as early-stage (IA1–IB1) or advanced/recurrent (IB2–IVA and IVB).
Clinical Pearl: For early-stage disease, the goal is often fertility preservation through conservative surgery, whereas advanced disease necessitates systemic therapy or chemoradiation where fetal survival may be secondary to maternal oncologic control.
This flowchart outlines the management of cervical cancer during pregnancy, differentiating between early and later stages based on FIGO staging. It details treatment options such as observation, local excision, definitive treatment, and primary treatment, considering factors like pregnancy preservation and maternal safety.
Principles of Imaging
Imaging is critical for assessing tumor extent and identifying lymph node involvement, but it must be performed with extreme caution to minimize fetal radiation exposure.
Preferred Modality: MRI of the abdomen and pelvis without contrast is the preferred imaging modality for staging.
Advanced Imaging: PET/MRI may be considered in specific clinical scenarios.
Avoidance: CT scans are generally avoided due to the risks of ionizing radiation to the fetus.
Biopsy Caution: CT-guided biopsies are discouraged unless the clinical plan involves immediate termination of pregnancy or delivery.
Management by Trimester
The timing of intervention is the most critical factor in balancing maternal and fetal outcomes.
First Trimester
In the first trimester, the primary goal is often to delay invasive interventions to avoid pregnancy loss.
Early Stage (IA1–IB1): If the patient desires to continue the pregnancy, surgical interventions like conization are typically delayed until after the 13th week. If pregnancy is not desired, termination followed by primary oncologic treatment is recommended.
Advanced Stage (IB2–IVA/IVB): Termination is generally preferred. If the patient chooses to continue the pregnancy, systemic therapy (typically carboplatin and paclitaxel) is delayed until the 13th or 14th week.
Second Trimester
The second trimester (roughly 13–27 weeks) offers a window for more definitive interventions.
Early Stage (IA1–IB1): If a LEEP or cone biopsy confirms Stage IA1 with no lymphovascular space invasion (LVSI) and negative margins, the patient may undergo close surveillance. For patients with suspicious lymph nodes, minimally invasive surgical (MIS) pelvic lymphadenectomy or interventional radiology (IR) biopsy may be considered between 13 and 20 weeks.
Advanced Stage: Systemic therapy can be safely continued through the second trimester to ensure maternal disease control.
Third Trimester
As the patient approaches term, the focus shifts toward delivery planning.
Early Stage: Treatment is often deferred until the postpartum period. However, in some cases, a Cesarean section combined with a simple or radical hysterectomy may be an option.
Advanced Stage: Systemic therapy can continue until fetal maturity but must be held 3–4 weeks prior to the planned delivery. For patients already beyond 34 weeks gestation, oncologic intervention is deferred until after delivery, which should be performed via a high hysterotomy/fundal Cesarean section.
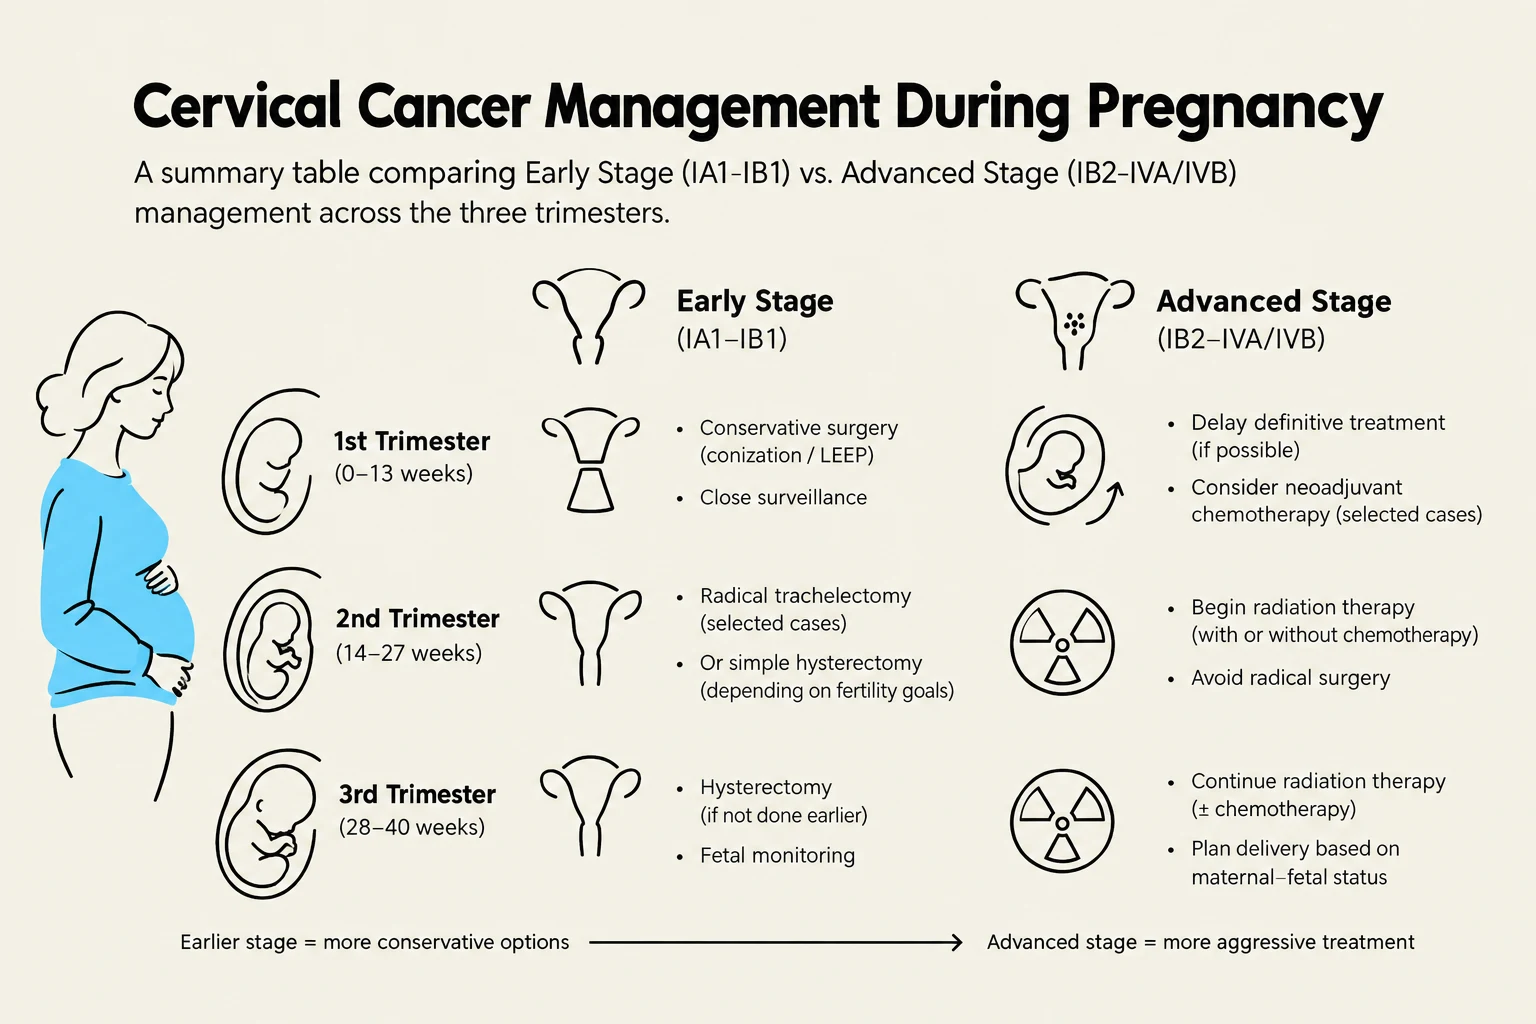
This diagram illustrates the management of early-stage cervical cancer during pregnancy, outlining considerations and treatment approaches for each trimester.
Systemic Therapy Administration
For advanced or recurrent disease, systemic therapy is a cornerstone of management. The standard regimen often involves platinum-based chemotherapy, such as carboplatin and paclitaxel.
When administering these agents, clinicians must be mindful of the timing relative to delivery to prevent neonatal exposure to cytotoxic drugs. In the context of advanced disease, induction chemotherapy followed by chemoradiation (following the INTERLACE protocol) may be considered.
Post-Delivery Care and Surveillance
Once the patient has delivered, the focus shifts entirely to oncologic treatment and long-term survivorship.
Radiation Therapy: Following an uncomplicated delivery, radiation treatment can typically be initiated 2–3 weeks postpartum.
Surveillance: During the pregnancy, patients undergoing conservative management require frequent monitoring, including physical exams and colposcopy every 4–6 weeks.
Survivorship: Post-treatment, patients should be monitored for late effects, including genitourinary symptoms and sexual dysfunction. The use of vaginal dilators, moisturizers, or local estrogen may be recommended to manage vaginal stenosis following radiation.
Exam Tip: If a question asks for the preferred imaging modality for staging cervical cancer in a pregnant patient, the answer is MRI without contrast. Avoid CT due to fetal radiation risks.
This table outlines the management of cervical cancer during pregnancy, comparing early and advanced stages across the three trimesters. It details treatment options such as surgery, chemotherapy, and radiation therapy, considering the stage of cancer and gestational period.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.