An introduction to the cardiovascular system, covering heart anatomy, physiology, electrical conduction, common diseases, and clinical assessment techniques including physical examination and EKG interpretation.
The cardiovascular system is a complex network of the heart and blood vessels designed to deliver oxygenated blood and nutrients to cells, distribute hormones, and transport waste products to disposal sites. Understanding the intricate relationship between cardiac anatomy, electrical conduction, and clinical presentation is essential for the effective assessment and management of patients experiencing cardiac emergencies.
Cardiovascular Anatomy and Physiology
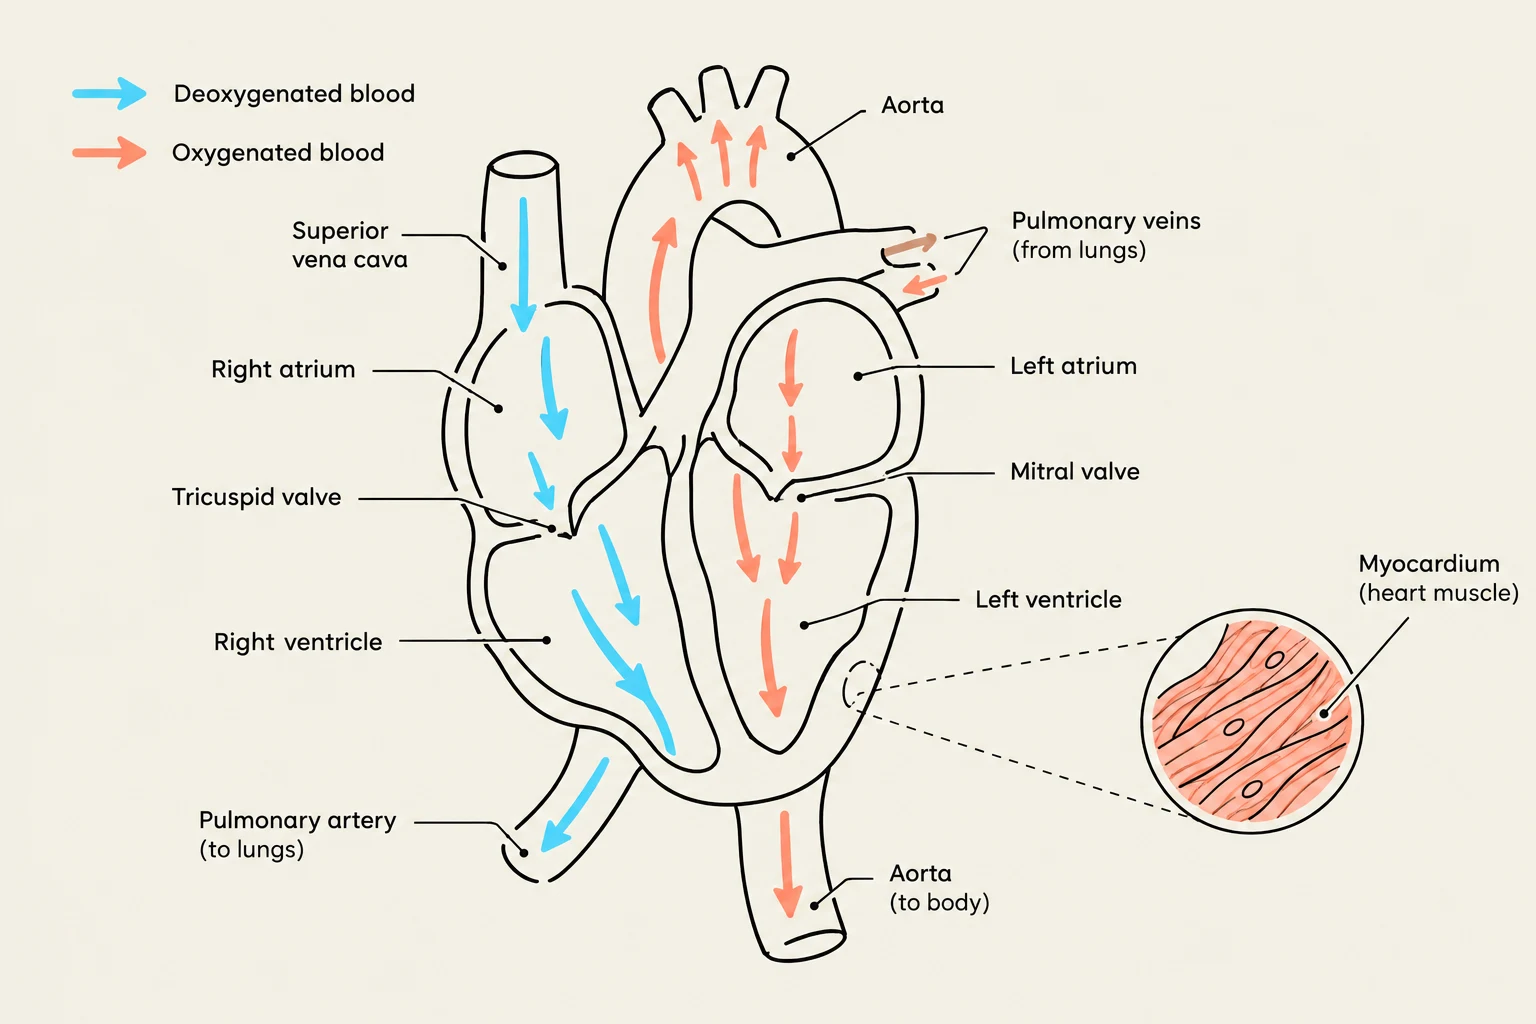
The heart functions as two separate pumps working in tandem. The right heart (right atrium and right ventricle) serves as a low-pressure system responsible for pulmonary circulation, pumping deoxygenated blood to the lungs. The left heart (left atrium and left ventricle) is a high-pressure system that pumps oxygenated blood throughout the entire body.
The heart is composed of four chambers:
Right Atrium: Receives deoxygenated blood from the superior vena cava, inferior vena cava, and coronary sinus.
Left Atrium: Receives oxygenated blood from the lungs via the pulmonary veins.
Right Ventricle: Pumps deoxygenated blood to the lungs.
Left Ventricle: Pumps oxygenated blood to the body.
The muscular wall responsible for the contraction and efficient ejection of blood is the myocardium, the middle layer of the heart wall. To maintain this function, the heart relies on the coronary arteries. The Left Main Coronary Artery (LMCA) supplies the left ventricle and the interventricular septum, while the Right Coronary Artery (RCA) supplies the right atrium, right ventricle, portions of the left ventricle, and parts of the conduction system.
Diagram illustrating the flow of oxygenated and deoxygenated blood through the human heart, including key chambers and valves.
Electrical Conduction and Cellular Properties
Cardiac function is driven by unique cellular properties: automaticity, excitability, conductivity, and contractility. The electrical impulse that triggers contraction is managed by the cardiac conduction system, which includes the SA node (the dominant pacemaker), the AV node (which delays the impulse to allow atrial emptying), the Bundle of His, the right and left bundle branches, and the Purkinje fibers.
The movement of electricity is driven by depolarization (the stimulation of muscle fibers to contract via changes in electrolyte concentrations, specifically the entry of Na+ and Ca2+) and repolarization (the return to a resting state as Na+ and Ca2+ channels close and $K^+$ is pumped in).
The autonomic nervous system regulates this rhythm:
Sympathetic Stimulation: Releases norepinephrine to increase heart rate and strengthen the force of contraction.
Parasympathetic Stimulation: Acts via the vagus nerve to release acetylcholine (ACh), which slows the SA node firing rate and conduction through the AV node.
Cardiovascular Disease and Acute Syndromes
Cardiovascular disease (CVD) is a broad term for disorders of the heart and blood vessels. A specific and common subset is Coronary Heart Disease (CHD), which affects the coronary arteries.
When blood flow to the myocardium is abruptly reduced, it can lead to Acute Coronary Syndromes (ACS), which include unstable angina, NSTEMI, and STEMI. If the blockage causes myocardial tissue death, it is classified as a Myocardial Infarction (AMI). A complete cessation of mechanical cardiac activity is known as cardiac arrest.
Clinical Note: When assessing a patient, always treat the patient, not the monitor. Arrhythmias must be evaluated within the context of the patient's overall clinical condition.
Clinical Assessment Techniques
Primary Survey
In emergency settings, the primary survey follows the ABCDE sequence: Airway, Breathing, Circulation, Disability, and Exposure. However, if a patient is unresponsive and cardiac arrest is suspected, the order shifts to CABDE.
Physical Examination and History
A thorough history should investigate common complaints such as chest pain, dyspnea, fainting, palpitations, and fatigue. For patients experiencing palpitations, clinicians should ask about onset, frequency, and duration.
During the physical exam, clinicians should look for:
Skin Condition: Pale, mottled, or cyanotic skin may indicate circulation problems, while flushed, warm skin may suggest other issues.
Jugular Veins: Inspect for increased jugular pressure.
Edema: Bilateral pitting edema may indicate right ventricular failure (RVF), whereas one-sided edema may suggest a localized blockage.
Heart Sounds:
S1: Closure of tricuspid and mitral valves.
S2: Closure of pulmonary and aortic valves.
S3/S4: Abnormal sounds often associated with heart failure or myocardial infarction.
Murmurs: Caused by turbulent blood flow through irregular or constricted valves.
A flowchart illustrating the clinical assessment process, including the ABCDE primary survey, history taking, targeted examination, investigations, and treatment for acute coronary syndrome (ACS).
Vital Signs and Pulse Findings
Blood pressure (BP) and pulse assessments provide critical data regarding hemodynamic stability.
Blood Pressure: Normal SBP is <120 and DBP is <80. In emergencies, an SBP <90 indicates hypotension or shock, while a widened pulse pressure can signal later stages of shock.
Pulse Deficit: This is the difference between the apical pulse and the peripheral pulse.
Pulsus Alternans: A beat-to-beat difference in the strength of the pulse.
Electrocardiogram (EKG) Interpretation
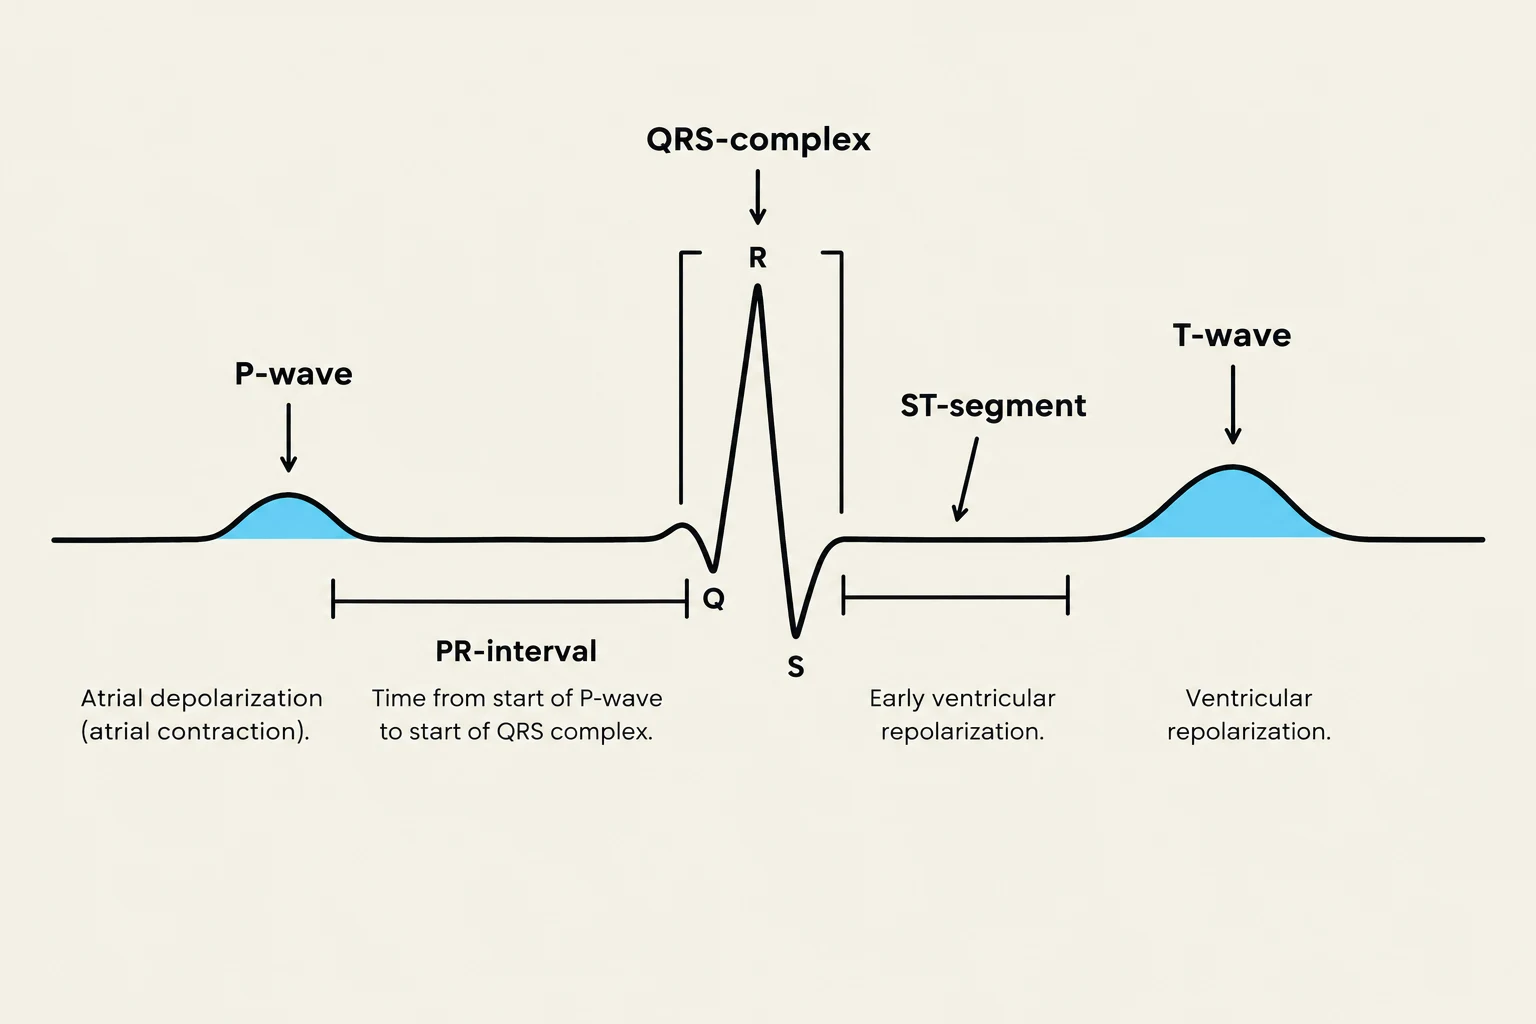
The EKG provides an electrical snapshot of the heart's conduction. A standard 12-lead EKG includes three limb leads, three augmented limb leads, and six precordial leads.
Key components of an EKG waveform include:
P-wave: Represents atrial depolarization.
PR-interval (PRI): The time required for the impulse to traverse the atria and AV junction (Normal: 0.12–0.20 seconds).
Diagram illustrating the components of a normal electrocardiogram (ECG) waveform, including the P-wave, QRS complex, and T-wave, along with their associated intervals and segments, and their physiological meanings.
Exam Tip: When calculating heart rate using the 6-second method, count the number of QRS complexes in a 6-second strip and multiply by 10.
Summary Table: Common Cardiac Rhythms
Rhythm
Rate
Characteristics
Normal Sinus Rhythm
60–100 bpm
Upright P-wave, normal PRI and QRS
Sinus Bradycardia
<60 bpm
Upright P-wave, may cause hypotension
Sinus Tachycardia
101–180 bpm
Upright P-wave, may be due to pain or hypoxia
Atrial Fibrillation
Variable
Irregularly irregular, chaotic baseline
Atrial Flutter
Variable
Sawtooth or "picket fence" F-waves
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.