Pregnancy places an extraordinary demand on the human body, particularly the cardiovascular system. For individuals with pre-existing or newly developed heart conditions, these physiological shifts can transition a manageable condition into a life-threatening emergency. Understanding the distinction between different types of cardiac disease, the underlying pathophysiology, and the critical nursing interventions required to prevent maternal and fetal complications is essential for safe obstetric care.
Classifications of Cardiac Disease
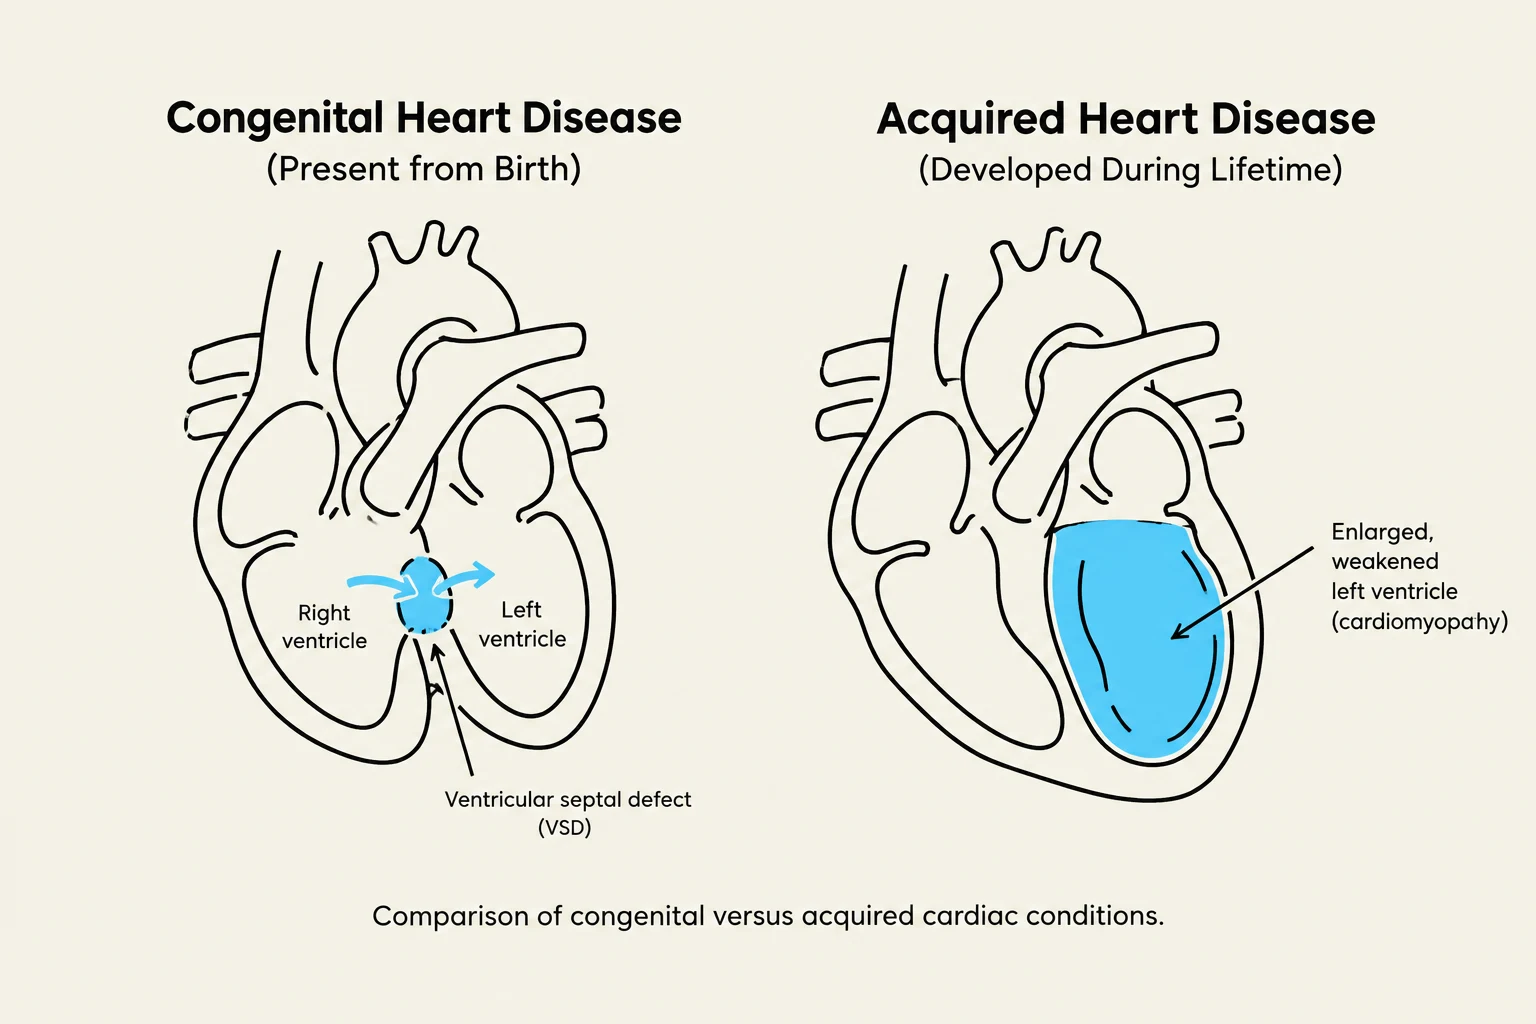
Comparison of congenital versus acquired cardiac conditions, illustrating a ventricular septal defect in congenital heart disease and an enlarged, weakened left ventricle in acquired heart disease (cardiomyopathy).
Cardiac conditions encountered during pregnancy are generally categorized into two groups based on their origin:
Congenital Heart Disease: These involve structural defects that are present from birth. While some defects may be detected prenatally, others may remain asymptomatic until the hemodynamic stresses of pregnancy bring them to light.
Acquired Heart Disease: This refers to cardiac conditions that develop during a person's lifetime, independent of congenital defects.
Risk Factors and Vulnerable Populations
Certain demographics and medical histories significantly increase the risk of maternal mortality related to heart disease:
Age: Women over the age of 40 are at a much higher risk for heart-related pregnancy complications.
Race/Ethnicity: Black, American Indian, and Alaskan Native women face higher risks of death from heart-related complications compared to Asian, White, and Hispanic women.
Medical History: Pre-existing obesity and hypertension (high blood pressure) are major contributors to increased cardiac risk.
Pathophysiology and Hemodynamic Changes
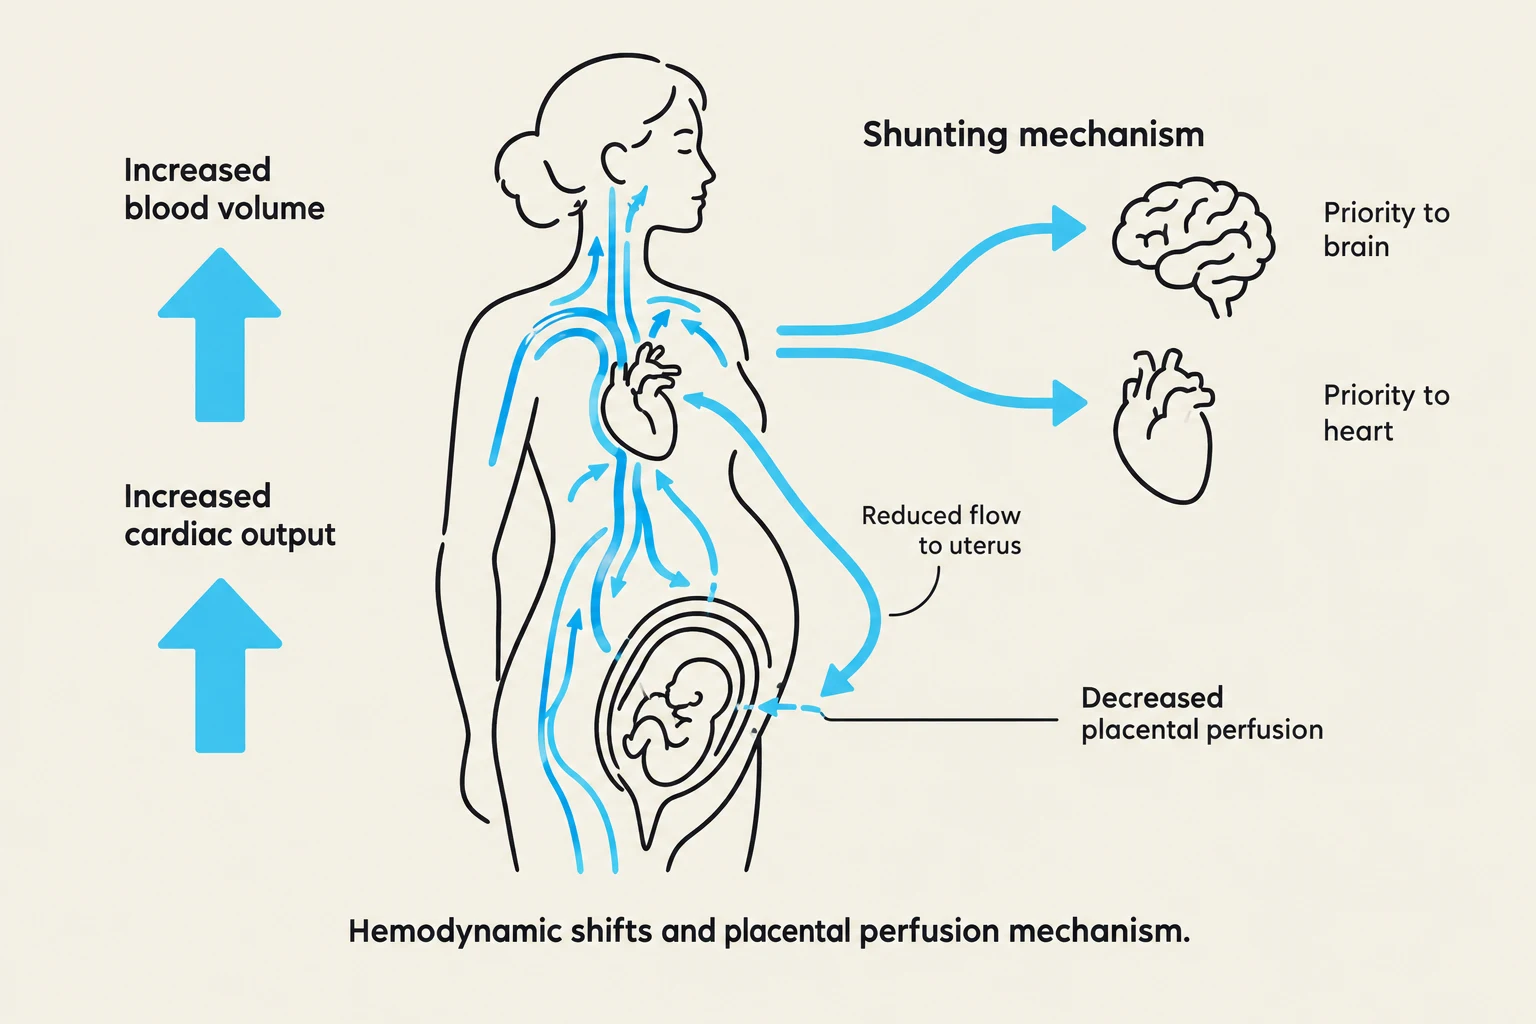
This diagram illustrates the hemodynamic shifts and placental perfusion mechanism during pregnancy, showing how blood flow is shunted to prioritize the brain and heart, leading to reduced flow to the uterus and decreased placental perfusion.
The primary driver of cardiac complications in pregnancy is the profound change in hemodynamics. As pregnancy progresses, the body undergoes significant shifts in blood volume and cardiac output to support the growing fetus. These changes can overstress an already compromised cardiovascular system, potentially leading to cardiac decompensation—a state where the heart can no longer meet the body's metabolic demands.
A critical consequence of maternal cardiac instability is its impact on the fetus. If maternal blood pressure or blood volume decreases significantly, the body may shunt blood away from the uterus to protect vital maternal organs. This reduction in placental perfusion can lead to fetal distress, intrauterine growth restriction (IUGR), or other adverse outcomes.
Clinical Alert: Recognizing Warning Signs
Because some cardiac symptoms can mimic normal pregnancy changes (such as fatigue or mild swelling), patients must be educated to report any changes immediately. Warning signs include:
Dyspnea (shortness of breath with little to no activity)
Cyanosis (bluish discoloration of skin/mucosa)
Palpitations or chest pain
Syncope (fainting or passing out)
Unusual fatigue or severe swelling
Nursing Management and Risk Reduction
The primary goal of nursing care is to stabilize the patient's hemodynamic status and prevent the progression toward heart failure.
Nursing Assessment
Nurses must perform frequent and meticulous assessments, including:
Vital Signs: Monitoring for fluctuations in blood pressure and heart rate.
Fluid Status: Tracking daily weight and strict Intake and Output (I&O) to monitor for fluid retention or signs of pulmonary edema.
Cardiac Assessment: Listening to heart sounds and observing for signs of decompensation.
Fetal Surveillance
To ensure the fetus is tolerating the maternal condition, nurses should:
Encourage the patient to monitor and record daily fetal movement.
Utilize serial nonstress testing (NST) as prescribed to evaluate fetal well-being.
Lifestyle and Energy Conservation
Managing the patient's daily activities is vital to reducing the workload on the heart:
Energy Conservation: Patients should prioritize rest periods and be encouraged to rest in a side-lying position.
Nutrition and Hydration: Ensure adequate hydration and a nutritious, high-fiber diet to prevent straining and constipation, which can cause dangerous spikes in blood pressure (the Valsalva maneuver).
Pharmacological Interventions
Medications must be administered carefully under strict provider orders. Common cardiac medications include:
Diuretics (e.g., Lasix): To manage fluid overload.
Digitalis: To improve cardiac contractility.
Antiarrhythmics: To manage irregular heart rhythms.
Heparin: For anticoagulation.
⚠️ Critical ContraindicationWarfarin is contraindicated in pregnancy due to its teratogenic effects. Nurses must ensure this medication is not administered to pregnant patients.
Management During Labor and Delivery
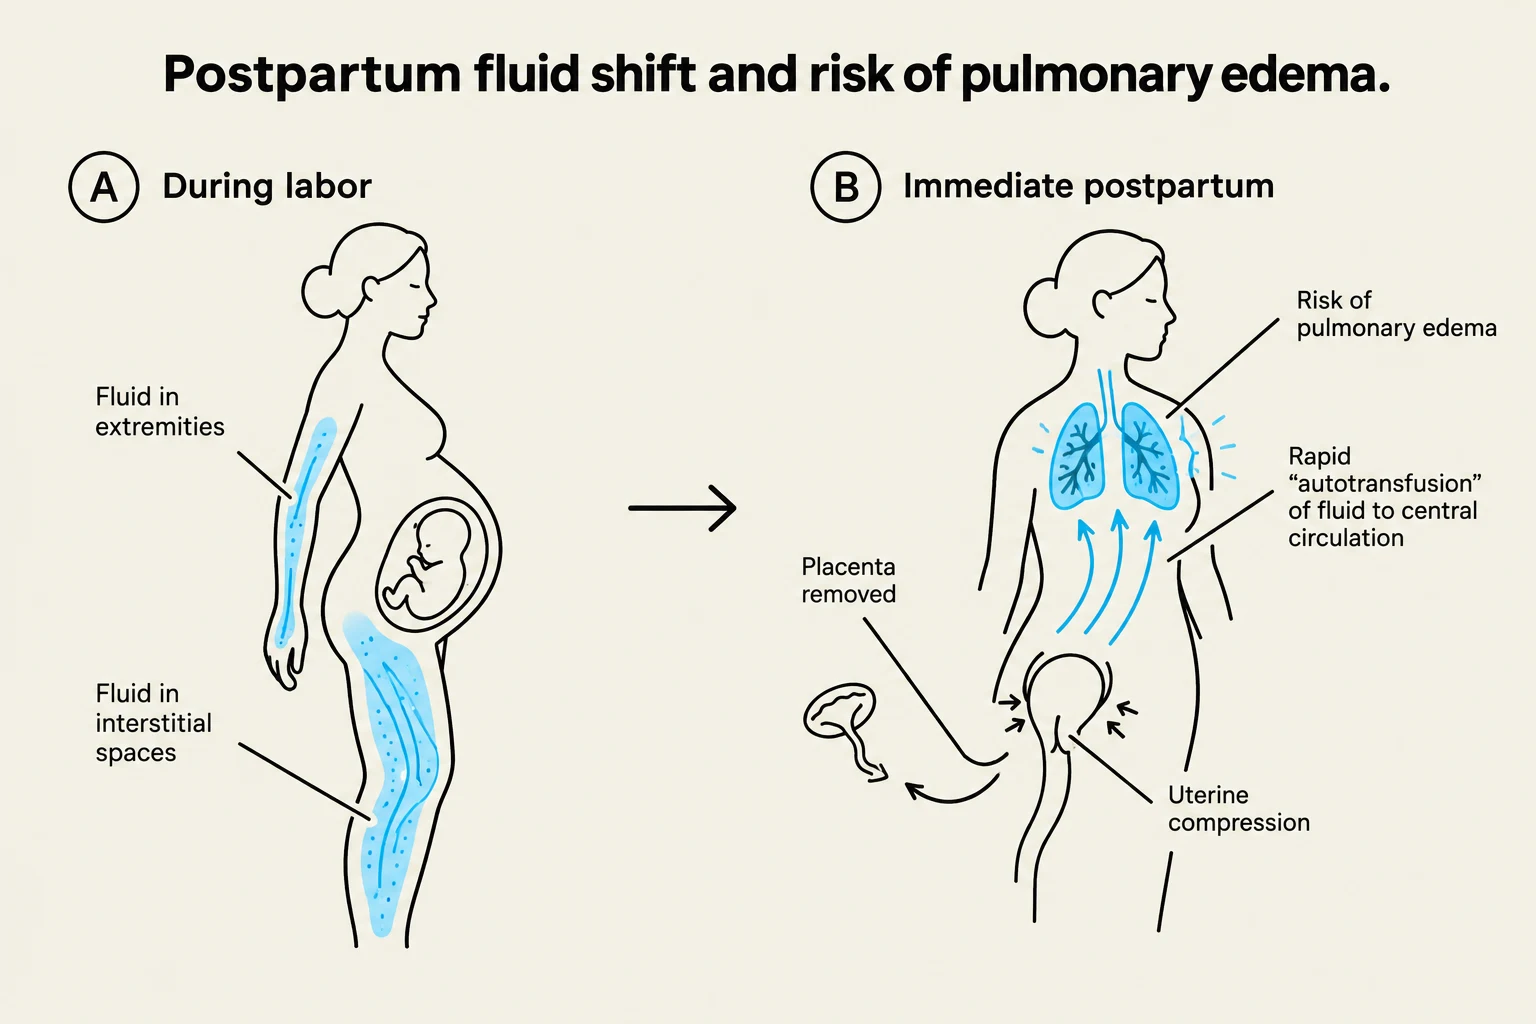
Diagram illustrating postpartum fluid shifts and the associated risk of pulmonary edema, showing fluid distribution during labor and immediate postpartum changes.
The intrapartum period is a high-risk time for cardiac patients due to the physical exertion of labor and the rapid fluid shifts that occur during and after birth.
Positioning: The patient should be positioned to optimize cardiac output.
Oxygenation: Administer oxygen as prescribed to maintain maternal and fetal saturation.
Assisted Birth: Depending on the clinical situation, medical interventions such as an epidural or vacuum-assisted birth may be utilized.
Postpartum Vigilance: Nurses must remain highly observant for signs of heart failure or pulmonary edema immediately following delivery, as the patient may become fluid overloaded during the postpartum period.
Long-term Follow-up
A diagnosis of cardiac disease during pregnancy requires a lifelong approach to care. Patients must be educated on the importance of increased postpartum follow-up with their OB-GYN to monitor their recovery. Furthermore, patients must be instructed to disclose their cardiac history to all future healthcare providers to ensure safety in any future pregnancies or medical procedures.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.