Bariatric Surgery: Selection Criteria and Preoperative Optimization
This guide details the criteria for selecting patients for bariatric surgery, including BMI thresholds and the management of obesity-related comorbidities. It outlines the essential preoperative medical, nutritional, and lifestyle evaluations necessary to optimize patient health and minimize surgical risks.
Bariatric surgery, often referred to as metabolic surgery, has evolved from a purely restrictive procedure into a sophisticated multidisciplinary intervention. For patients living with severe obesity, these procedures offer a superior pathway for long-term weight loss and the remission of life-threatening comorbidities compared to standard medical management alone. However, the success of these interventions depends heavily on rigorous patient selection and a comprehensive preoperative workup designed to minimize surgical risks and optimize metabolic health.
Patient Selection and Indications
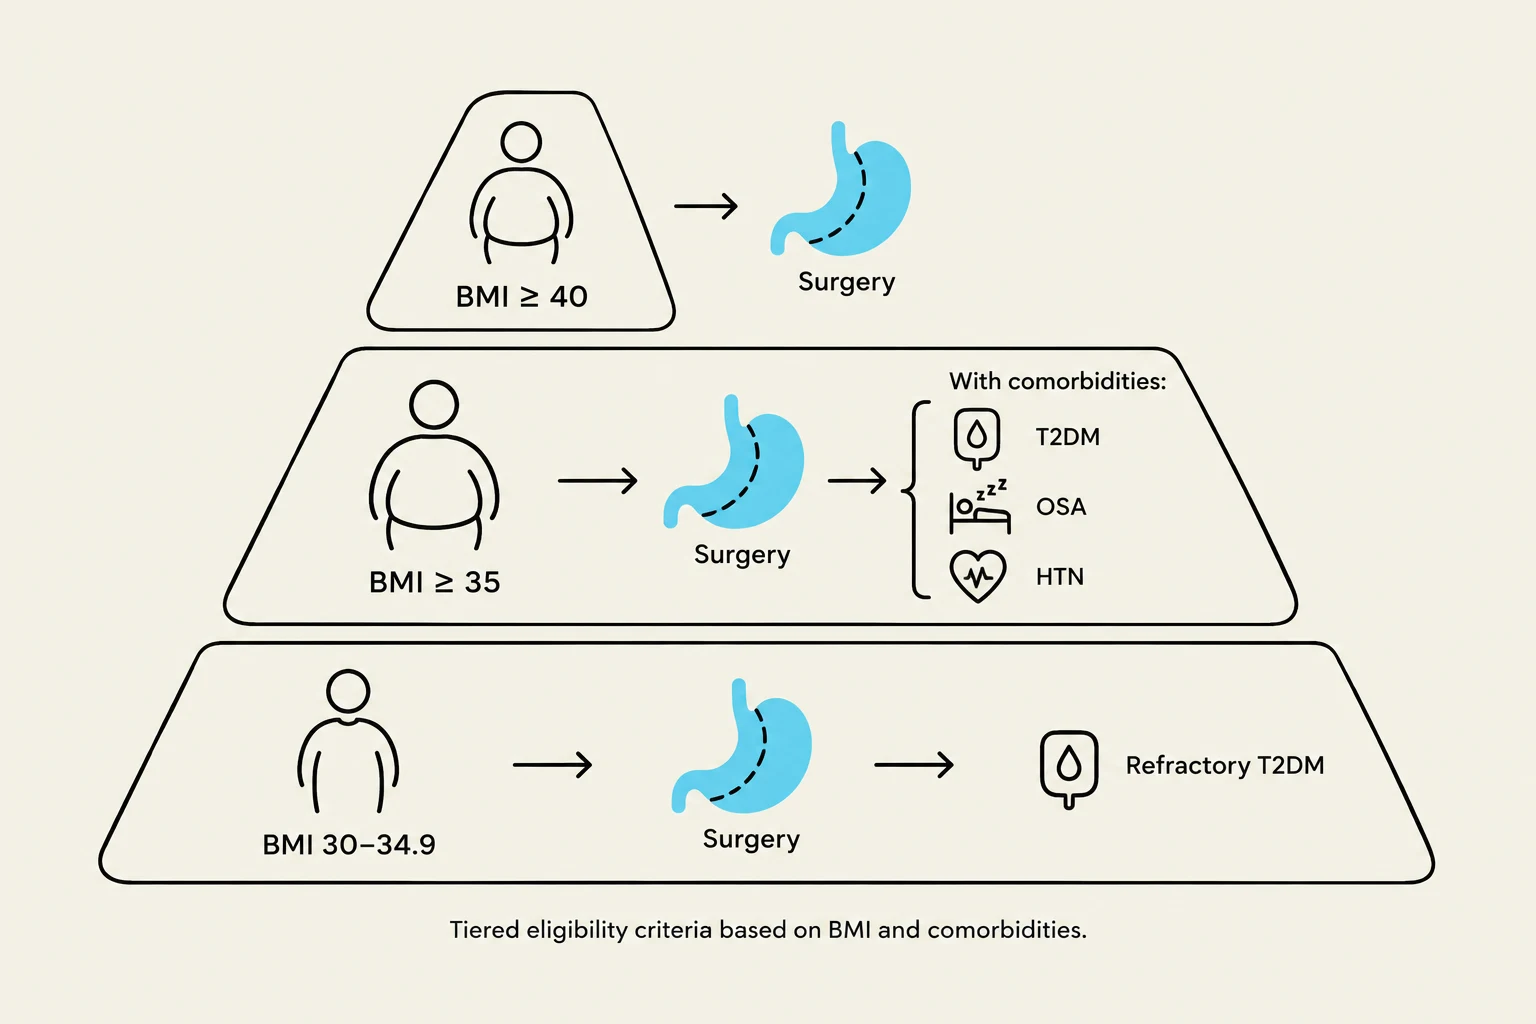
Tiered eligibility criteria based on BMI and comorbidities.
The decision to proceed with bariatric surgery is based on a patient's Body Mass Index (BMI) and the presence of obesity-related complications. Clinical guidelines generally categorize eligibility into three tiers:
BMI ≥ 40 kg/m²: Surgery is indicated regardless of the presence of comorbidities.
BMI ≥ 35 kg/m²: Surgery is indicated if the patient has at least one major obesity-related complication. Key complications include Type 2 Diabetes (T2DM), hypertension, hyperlipidemia, obstructive sleep apnea (OSA), non-alcoholic steatohepatitis (NASH), coronary artery disease, and debilitating arthritis.
BMI 30–34.9 kg/m²: Surgery may be considered for patients with Class I obesity if they have significant obesity-related diseases (particularly T2DM) that are refractory to optimal medical and behavioral management.
Clinical Note: Age is not an absolute contraindication. Outcomes and complication rates for patients over 60 years of age are comparable to younger populations.
Preoperative Medical Evaluation
A comprehensive evaluation is mandatory to ensure the patient is stable for surgery. This multidisciplinary assessment includes several critical domains:
Cardiac and Pulmonary Assessment
Obesity is an independent risk factor for cardiovascular disease. Patients may present with shortness of breath or chest pain, and physical examinations can be challenging due to body habitus.
Cardiac: Evaluation may include ECG, echocardiography (to detect ventricular dysfunction), or nuclear stress testing.
Pulmonary: Impaired lung volumes and respiratory mechanics are common in patients with high BMI.
Sleep Apnea: The prevalence of OSA in the bariatric population can exceed 90%. Screening is often performed using tools like the STOP-Bang questionnaire. If high risk is identified, a formal level 1 polysomnogram (PSG) is the gold standard for diagnosis.
Endoscopy and Gastrointestinal Screening
The utility of preoperative endoscopy is individualized. It is strongly recommended for patients undergoing sleeve gastrectomy who present with dyspepsia, reflux, or dysphagia to rule out hiatal hernia, esophagitis, or Barrett’s esophagus. Additionally, screening for H. pylori is recommended, particularly for those undergoing gastric bypass, to prevent the development of peptic ulcers.
Smoking and Nicotine Cessation
Smoking cessation is mandatory. Nicotine increases the risk of marginal ulceration, stricture formation, and impaired wound healing. Ideally, patients should achieve cessation at least six weeks to six months prior to surgery to minimize postoperative complications.
Nutritional Optimization
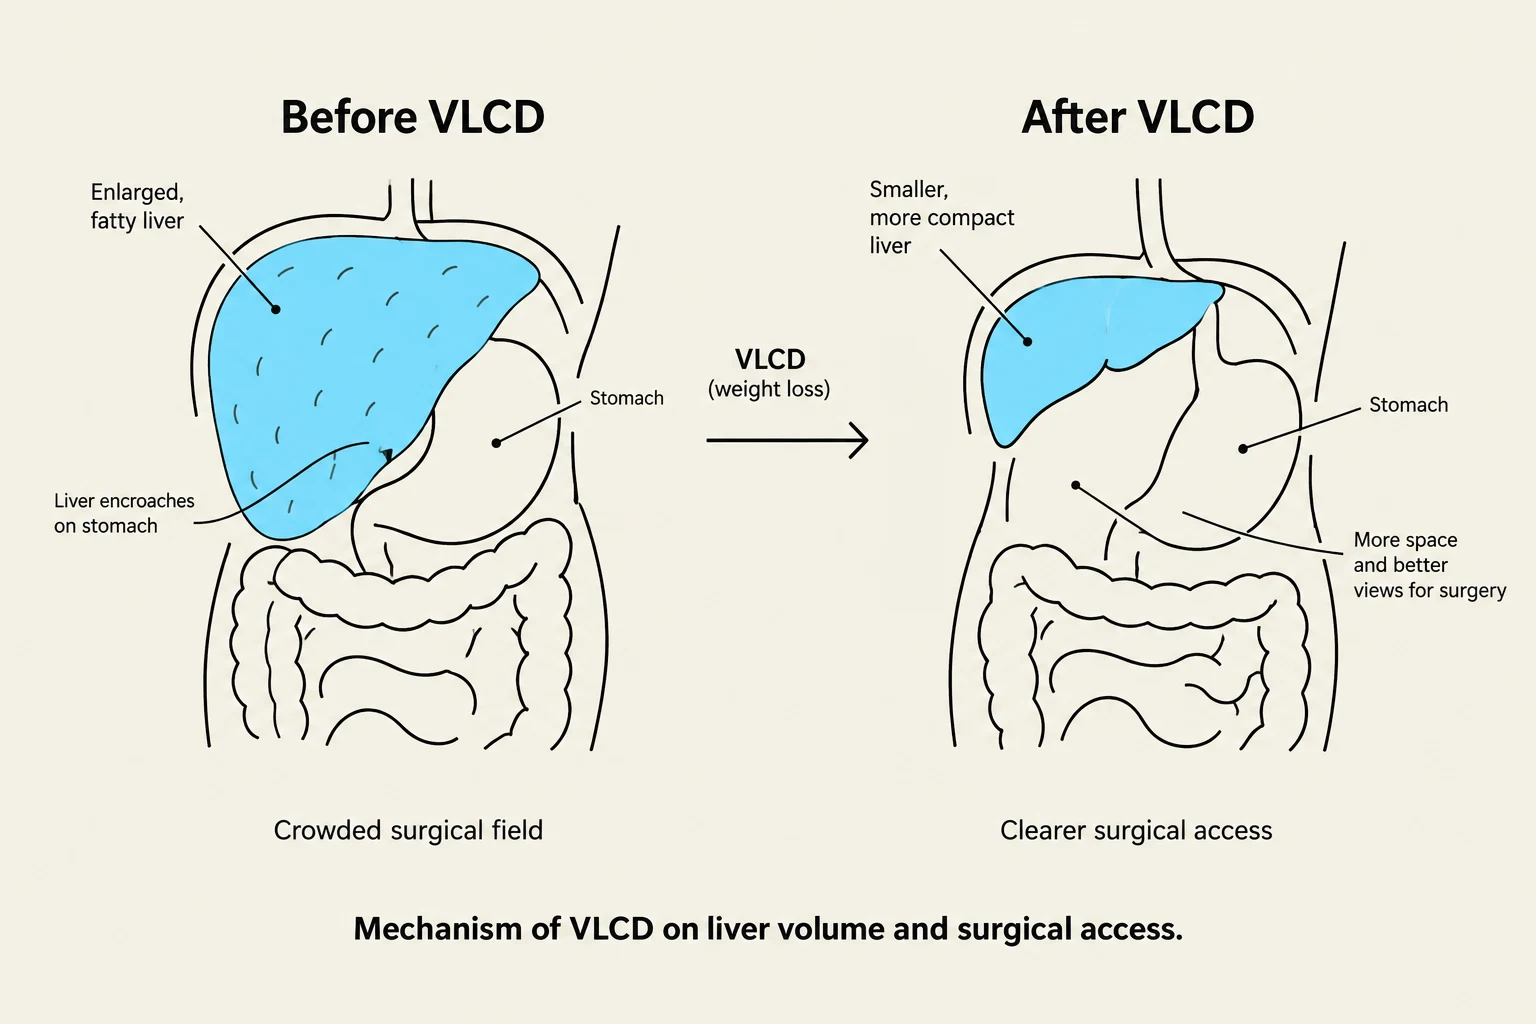
This diagram illustrates the effect of Very Low Calorie Diet (VLCD) on liver size and surgical access. Before VLCD, the liver is enlarged and fatty, encroaching on the stomach, leading to a crowded surgical field. After VLCD, the liver shrinks, providing more space and better views for surgery.
Malnutrition and Micronutrient Deficiencies
Patients with obesity are at a higher risk for inadequate nutritional status and malnutrition. A comprehensive nutritional evaluation by a registered dietitian is recommended for all candidates.
Preoperative lab work should include a complete blood count, creatinine, iron panel, vitamin D, calcium, albumin, and vitamin B12. Optimization of vitamin D, B12, and iron is specifically recommended prior to surgery.
Preoperative Weight Loss (VLCD)
Many protocols utilize a Very Low-Calorie Diet (VLCD)—typically consisting of 650–900 kcal/day via protein supplements—for 2–3 weeks before surgery. While VLCDs do not necessarily reduce major surgical risks, they can reduce liver volume by up to 19% and visceral adipose tissue by 17%, which increases the technical simplicity of the procedure for the surgeon.
Management of Type 2 Diabetes (T2DM)
Bariatric surgery is highly effective for the management of T2DM, often inducing remission. However, preoperative management is critical to prevent perioperative complications.
Glycemic Targets: While targets like $A1C < 7%$ are ideal, clinicians must recognize that patients with high insulin resistance may require less aggressive targets.
Medication Adjustments: During a VLCD, insulin requirements often drop dramatically (sometimes by 50% for intermediate/long-acting insulin).
Safety Precautions: To avoid hypoglycemia, clinicians should consider avoiding sulfonylureas and meglitinides while the patient is on a VLCD. Additionally, SGLT2 inhibitors must be stopped to prevent the risk of diabetic ketoacidosis.
Surgical and Endoscopic Options
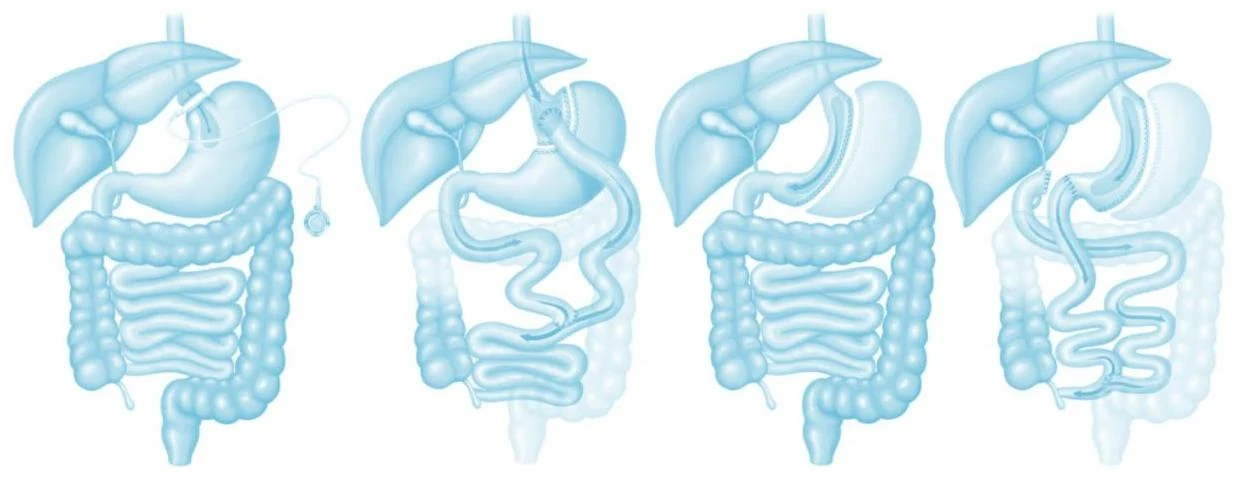
This diagram illustrates four types of bariatric surgery: Adjustable Gastric Banding, Sleeve Gastrectomy, Roux-en-Y Gastric Bypass, and Duodenal Switch. It shows the correlation between intestinal bypass and metabolic efficacy.
The choice of procedure should be tailored to the patient's needs, goals, and expected metabolic response.
Diagram illustrating the steps of a bariatric surgery procedure.From left to right: Adjustable gastric banding, Roux-en-Y gastric bypass, sleeve gastrectomy and biliopancreatic diversion with duodenal switch. Copyright: Graphic department, Quebec Heart and Lung Institute, Laval University. Reprinted with permission.
Surgical Procedures
Procedure
Mechanism
Expected Outcomes
Key Risks
Sleeve Gastrectomy
Restrictive
~25% TWL; ~30% T2DM resolution
GERD, Barrett’s esophagus
Roux-en-Y Gastric Bypass (RYGB)
Restrictive & Malabsorptive
~30% TWL; ~40% T2DM resolution
Dumping syndrome, anastomotic ulcers
Duodenal Switch (DS)
Highly Malabsorptive
~40% TWL; ~80% T2DM resolution
Protein malnutrition, vitamin deficiency
Adjustable Gastric Banding
Restrictive
~20% TWL
Band erosion, weight regain
TWL = Total Weight Loss
Endoscopic Procedures
For patients seeking less invasive options, several endoscopic methods exist:
Intragastric Balloons: Requires retrieval after 3–6 months; effectiveness may be limited by weight regain after extraction.
Aspiration Therapy (e.g., AspireAssist®): A percutaneous device for Class II/III obesity showing ~19% weight loss at four years, but requires long-term nutritional surveillance.
Endoscopic Bypass: Aims to mimic the metabolic effects of RYGB but carries risks such as acute pancreatitis (3%) and device migration.
Exam Tip: Remember the "Rule of Thumb" for metabolic efficacy: The greater the intestinal bypass, the greater the potential for weight loss and metabolic improvement (Banding < Sleeve < RYGB < Duodenal Switch).
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.