


Effective clinical judgment in respiratory nursing requires a deep understanding of both the anatomy of the thoracic cavity and the pathophysiology of obstructive and malignant diseases. When assessing a client, the nurse must look beyond simple breath sounds to identify patterns of airflow limitation, structural changes in the chest wall, and specific risk factors that may indicate the presence of Chronic Obstructive Pulmonary Disease (COPD) or lung cancer.
Understanding COPD and Airflow Limitation
Chronic Obstructive Pulmonary Disease (COPD) is a preventable and treatable condition characterized by progressive airflow limitation that is not fully reversible. This limitation is typically driven by inflammatory responses within the lungs. COPD is a broad term that encompasses several distinct but often overlapping conditions, most notably emphysema and chronic bronchitis.
- Emphysema: This condition involves damage to the alveoli, often leading to a loss of elasticity in the lung tissue.
- Chronic Bronchitis: This is characterized by inflammation of the bronchi, often resulting in productive cough and airway obstruction.
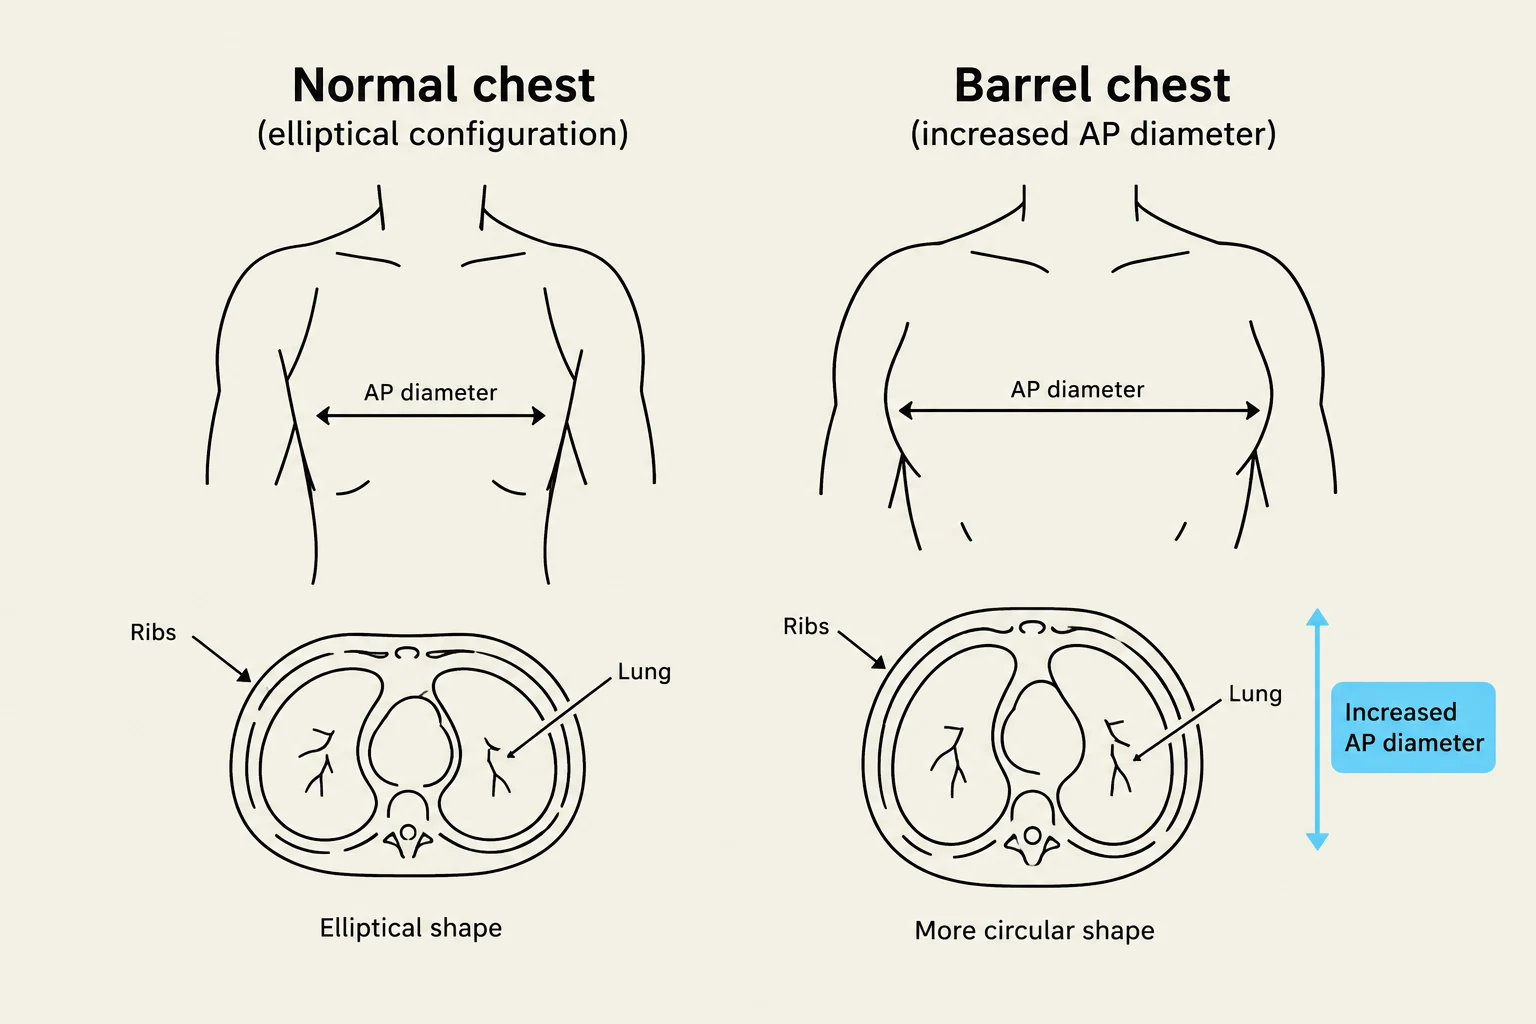
A key clinical finding in many COPD patients is the "barrel chest" configuration. In a normal chest, the anteroposterior (AP) diameter is smaller than the lateral diameter, maintaining a ratio of approximately $1:2$. However, in clients with COPD, the chest becomes rounder, and the AP-to-lateral diameter ratio shifts toward $1:1$.
Risk Assessment for Respiratory Disease
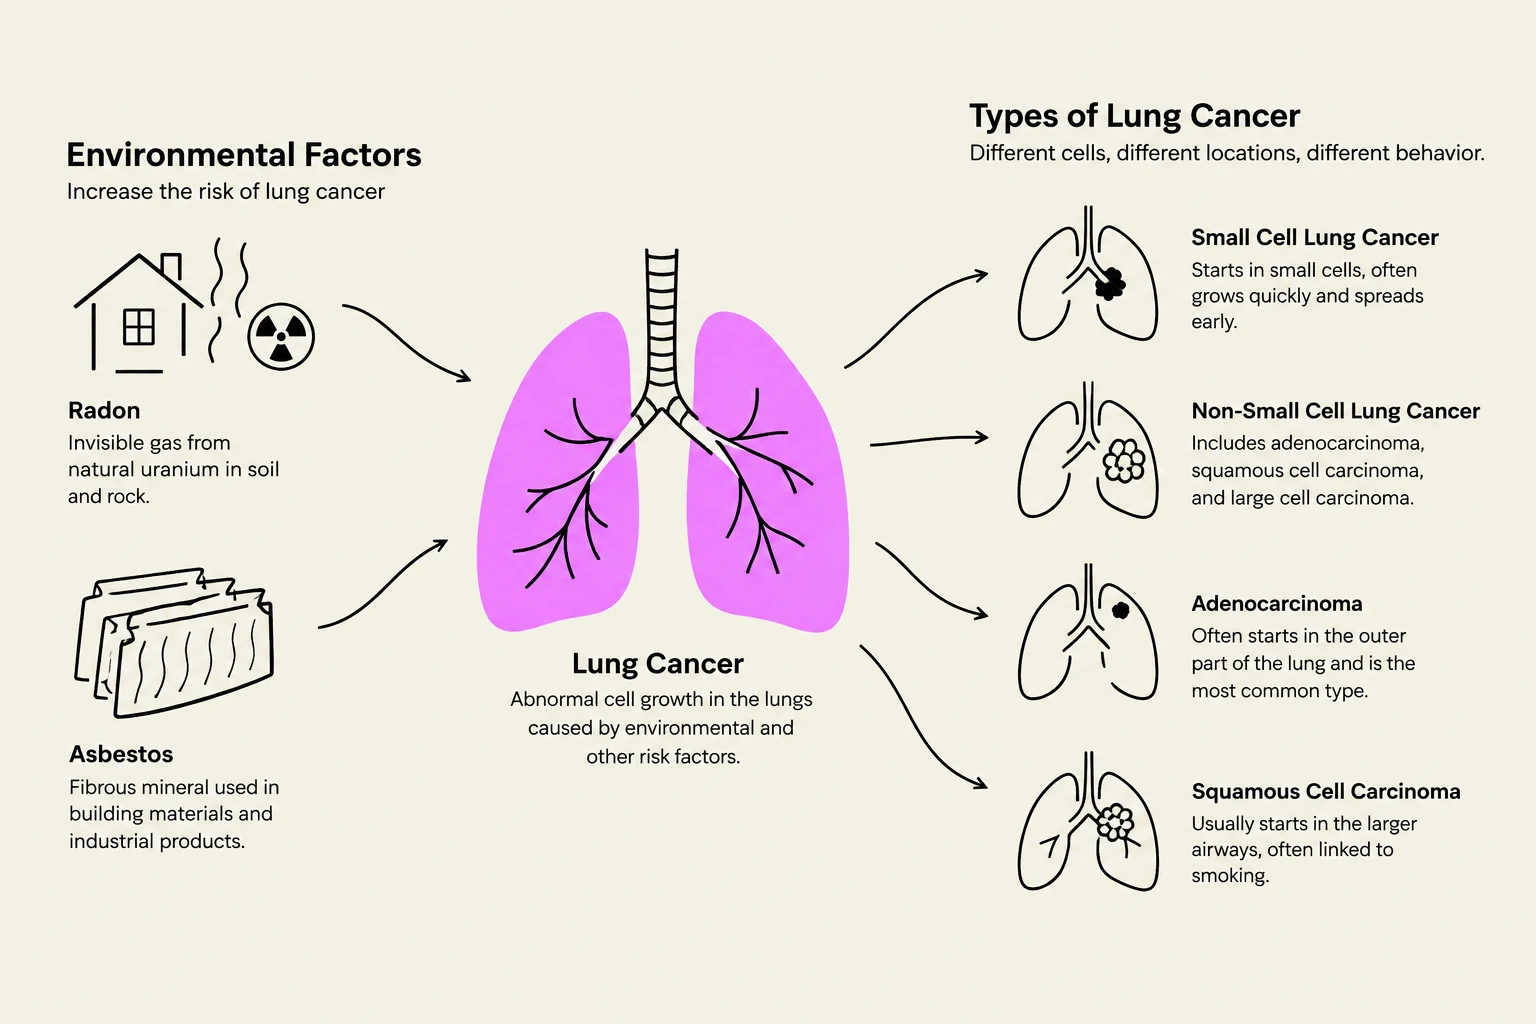
Identifying risk factors is a critical component of the nursing history and physical assessment. For COPD, the most significant risk factor is cigarette smoke exposure, which includes active smoking (tobacco, pipes, cigars, or marijuana) and secondhand smoke. Other contributors include:
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated