This guide explains the critical first step in patient education: assessing learning needs. It covers identifying knowledge, attitude, and skill gaps, as well as potential barriers, to tailor effective healthcare interventions.
In the realm of healthcare, education is not a "one-size-fits-all" intervention. Providing information without first understanding the recipient's starting point is a common pitfall that leads to poor adherence and suboptimal health outcomes. Assessing learning needs is the critical first step in the teaching process, acting as a diagnostic phase where the educator identifies specific gaps in knowledge, attitudes, or skills. By utilizing a combination of clinical assessment and collaborative dialogue, healthcare providers can tailor their interventions to meet the unique requirements of each patient.
The Three Pillars of Learning Needs
To conduct a thorough assessment, an educator must look beyond simple facts. Learning needs are generally categorized into three distinct domains: knowledge, attitudes, and skills.
Knowledge Gaps: This refers to what the patient knows (or does not know) about their condition, medications, or treatment plan. For example, a patient may understand that they have diabetes but may lack knowledge regarding how carbohydrate intake affects blood glucose levels.
Attitudinal Gaps: This involves the patient's beliefs, values, and feelings toward their health or treatment. A patient might possess the necessary knowledge but may hold a negative attitude toward a specific medication due to fear of side effects or cultural beliefs.
Skill Gaps: This is the practical ability to perform a task. A patient may know they need to inject insulin (knowledge) and believe it is important (attitude), but they may lack the manual dexterity or technique to perform the injection correctly (skill).
The three domains of learning: cognitive (knowledge), affective (attitude), and psychomotor (skill), work together to create complete learning and better patient care.
Exam Tip: When evaluating a patient's readiness to learn, always check for all three domains. A patient who fails to follow a regimen may not have a "knowledge" problem; they may have an "attitude" problem or a "skill" deficit.
Clinical Assessment and Collaborative Identification
Effective assessment is not a lecture; it is a collaborative process. It requires the healthcare provider to move from a position of "expert" to a "partner" in the patient's care.
Clinical Observation and Assessment
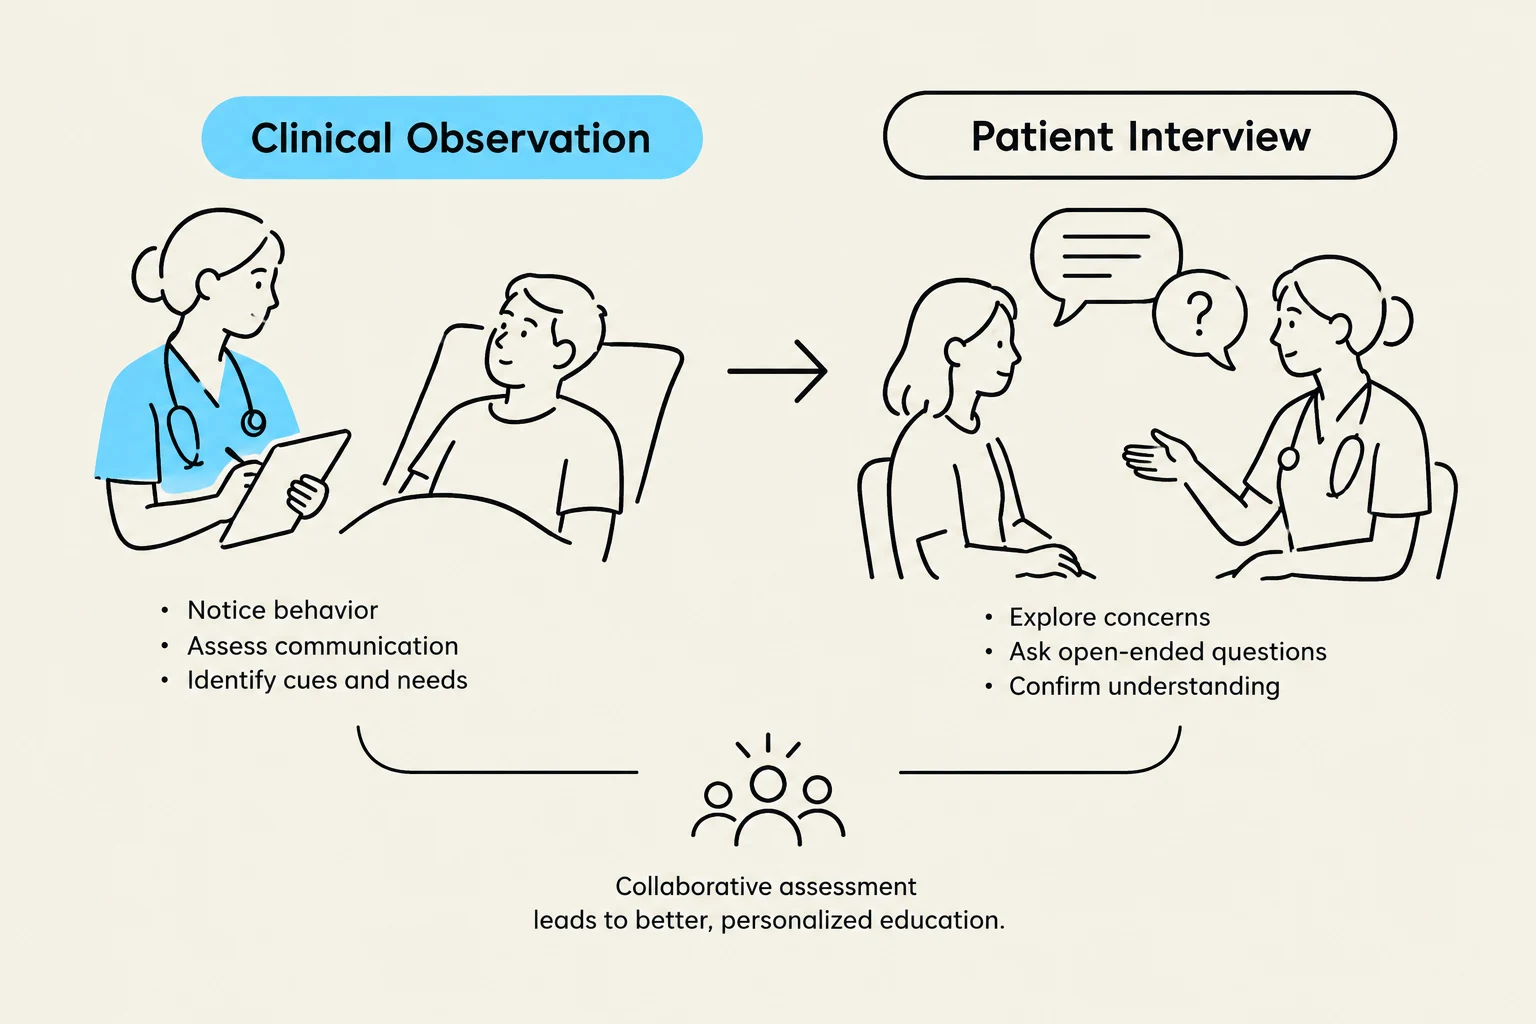
Clinical assessment involves using professional observation and standardized tools to gauge a patient's current state. This might include assessing cognitive function, sensory impairments (such as vision or hearing loss), or physical limitations that could hinder learning. For instance, if a patient has significant visual impairment, a written pamphlet will be an ineffective teaching tool, regardless of how well it is written.
Collaborative Dialogue
Collaboration is achieved through active listening and open-ended questioning. Instead of asking, "Do you understand your diet?" (which often invites a simple "yes"), use prompts that encourage the patient to express their current understanding and concerns.
Worked Example: The Post-Operative Patient
Imagine a patient scheduled for hip replacement surgery.
The Knowledge Assessment: Ask, "What have you heard about the recovery process after this surgery?" This reveals their baseline information.
The Attitude Assessment: Ask, "What concerns you most about going home after the surgery?" This identifies emotional barriers or misconceptions.
The Skill Assessment: Observe the patient attempting to use a walker or get in and out of bed. This identifies physical limitations or technique errors.
This illustration depicts two methods of patient assessment: clinical observation and patient interview, highlighting that collaborative assessment leads to better, personalized education.
Identifying Barriers to Learning
A comprehensive assessment must also identify potential barriers that could prevent the patient from successfully acquiring new information. These barriers can be categorized into several factors:
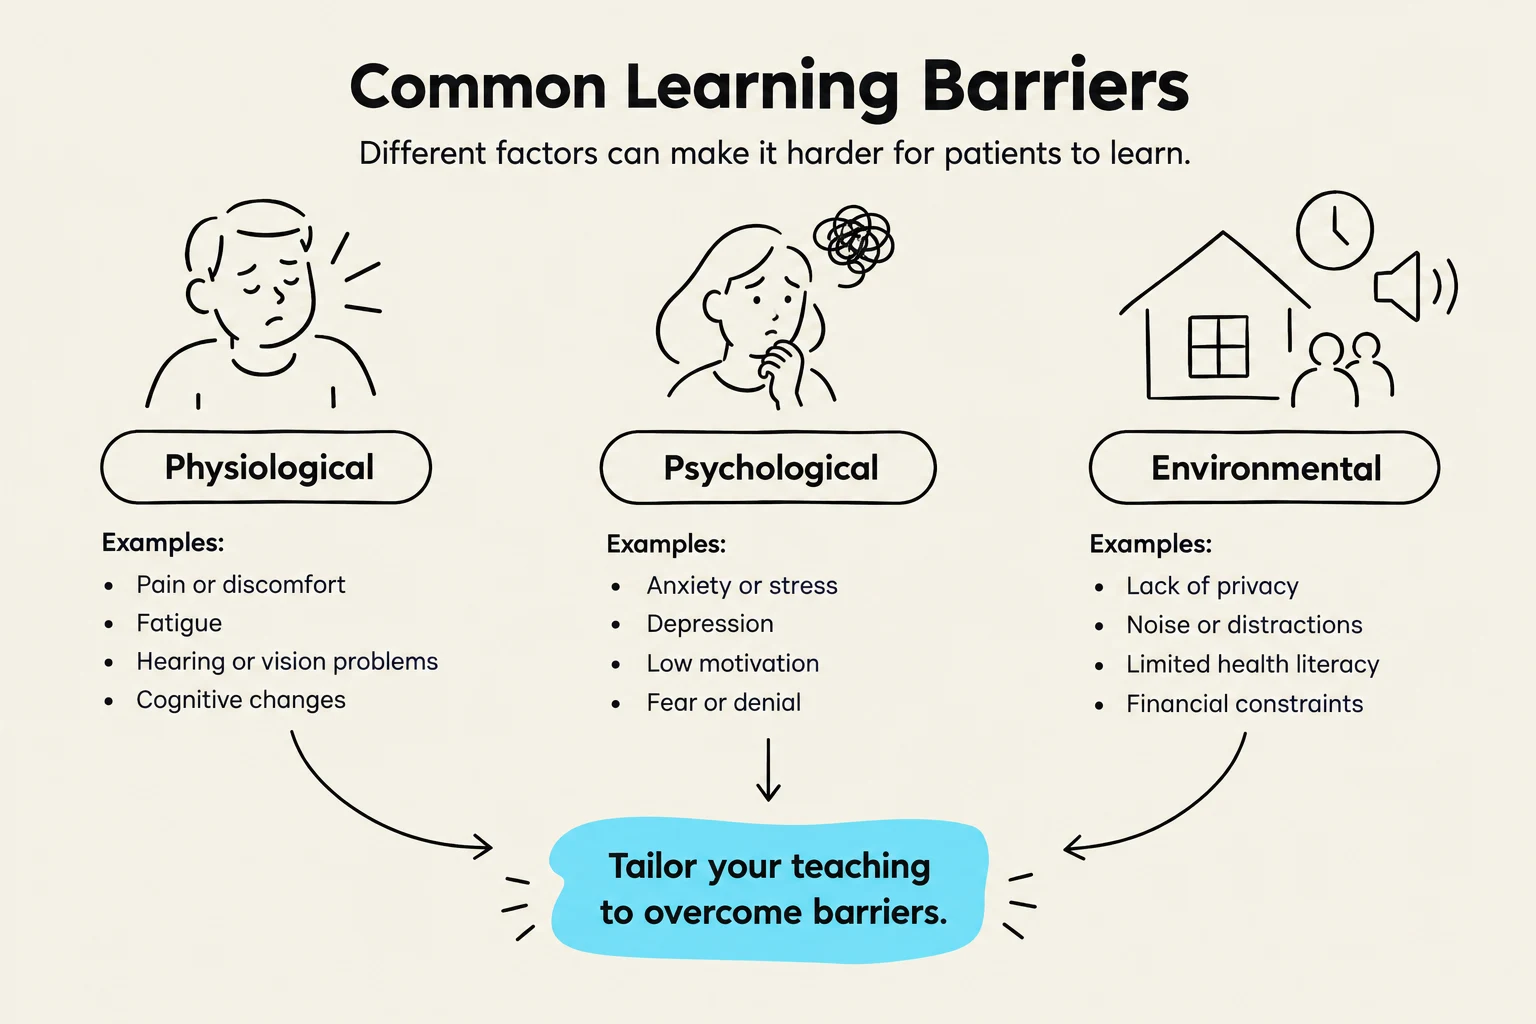
Physiological Barriers: Pain, fatigue, or acute illness can significantly diminish a patient's ability to concentrate or retain information.
Psychological Barriers: Anxiety, depression, or denial regarding a diagnosis can create mental blocks that prevent learning.
Environmental/Social Barriers: Lack of privacy, high noise levels in a hospital, or limited literacy levels can impede the effectiveness of the teaching session.
By identifying these barriers during the initial assessment phase, the educator can implement strategies to mitigate them—such as scheduling teaching sessions when the patient is least fatigued or providing materials in the patient's primary language.
This diagram illustrates common learning barriers categorized into physiological, psychological, and environmental factors, with examples and a concluding recommendation to tailor teaching to overcome these barriers.
Summary of the Assessment Process
To ensure no critical need is missed, educators can follow a systematic approach to assessment:
Assess Readiness: Is the patient physically and emotionally ready to learn right now?
Evaluate Baseline: What is their current level of knowledge, attitude, and skill?
Identify Barriers: What internal or external factors might interfere with learning?
Collaborate: Work with the patient to set realistic, measurable learning goals based on the findings.
By treating assessment as a dynamic, multi-dimensional process, healthcare providers ensure that their teaching is relevant, respectful, and, most importantly, effective in improving patient health.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.